University of Southern California/Van Nuys Prognostic Index (USC/VNPI)

  • The USC / VNPI:
    • Estimates which patients with DCIS can be managed by:
    • Excision alone vs
    • Excision plus radiation vs
    • Those who require mastectomy
  • There are three groups of patients in the index:
    • Group 1 patients have:
      • Non-high nuclear grade DCIS without necrosis
    • Group 2 patients have:
      • Non-high nuclear grade DCIS with necrosis
    • Group 3 patients have:
      • High nuclear grade DCIS with or without necrosis
  • The original Van Nuys Prognostic Index:
    • Introduced in 1996, had two additional variables:

      • They were:
        • Size of DCIS and margin width
    • A score from 3 to 9 was derived by:
      • Assigning 1, 2, or 3 points to each of the 3 variables as shown below in the Table 1:
  • Patients who scored 3 or 4:
    • Derived little benefit from radiation
  • Patients who scored 5, 6, or 7:
    • Derived substantial benefit from radiation
  • Patients who scored 8 or 9:
    • Had a high risk of relapse despite radiation and are best managed:
      • By mastectomy
  • In 2003:
    • The name became the University of Southern California / Van Nuys Prognostic Index
    • A 4th variable was added to the score:
      • Patients who were younger than age 40 years:
        • Received a score of 3
      • Patients from ages 40 to 60 years:
        • Received score of 2
      • Patients older than age 60 years:
        • Received a score of 1
    • The range of possible scores then became 4 to 12:
      • Patients with a score of 4, 5, or 6:
        • Did not receive a statistically significant benefit from radiation
      • Patients with scores of 7, 8, and 9:
        • Who were treated with radiation:
          • Received a significant reduction in local disease-free recurrence:
            • Of 12% to 15%
      • Patients with scores of 10, 11, and 12:
        • Had a local recurrence rate of almost:
          • 50% at five-years despite radiation
  • By 2010 the number of patients was large enough to allow analysis by individual scores as opposed to groups of scores, and the following was reported:
    • To achieve a local recurrence rate of less than 20% at 12 years:
      • These data support excision alone:
        • For all patients scoring 4, 5, or 6 and patients who score 7 but have margin widths ≥ 3 mm
      • Excision plus radiation therapy achieves the less than 20% local recurrence requirement at 12 years for patients:
        • Who score 7 and have margins < 3 mm, patients who score 8 and have margins ≥ 3 mm, and for patients who score 9 and have margins ≥ 5 mm
      • Mastectomy is suggested for patients:
        • Who score 8 and have margins < 3 mm, who score 9 and have margins < 5 mm, and for all patients who score 10, 11, or 12 to keep the local recurrence rate less than 20% at 12 years
  • REFERENCES
    • Silverstein MJ. The University of Southern California/Van Nuys Prognostic Index for ductal carcinoma in situ of the breast. Am J Surg. 2003;186:337-343.
    • Silverstein MJ, Lagios MD. Choosing treatment for patients with ductal carcinoma in situ: fine tuning the University of Southern California/Van Nuys Prognostic Index. J Natl Cancer Inst Monogr. 2010;2010:193-196.
    • Silverstein MJ, Lagios MD. Treatment selection for patients with ductal carcinoma in situ (DCIS) of the breast using the University of Southern California/Van Nuys (USC/VNPI) Prognostic Index. Breast J. 2015;21:127-132.
    • Silverstein MJ, Lagios MD, Craig PH, et al. A prognostic index for ductal carcinoma in situ of the breast. Cancer. 1996;77:2267-2274.

#Arrangoiz #BreastSurgeon #CancerSurgeon #BreastCancer #SurgicalOncologist
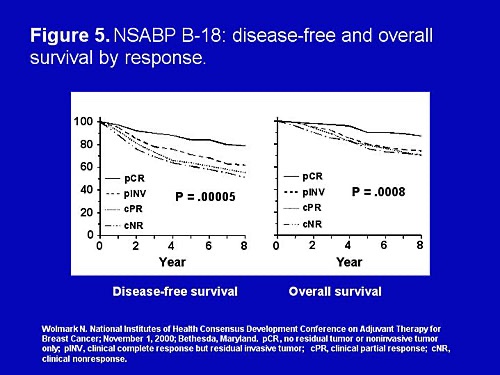
National Surgical Adjuvant Bowel and Breast Project B-18

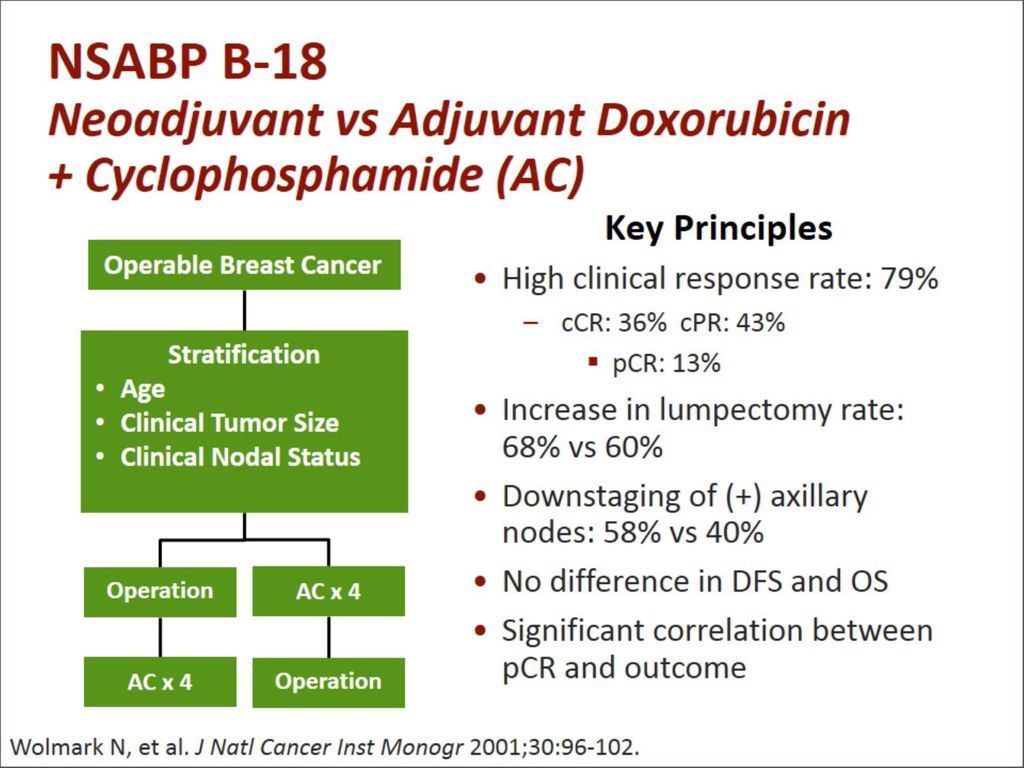
  • The National Surgical Adjuvant Bowel and Breast Project B-18:
    • Was designed to determine whether preoperative chemotherapy:
      • Would result in improved survival:
        • Compared to postoperative chemotherapy
    • Secondary aims included:
      • Evaluation of pCR rates
      • Comparison of breast conservation rates and ipsilateral recurrence rates between the two groups
  • Between 1988 and 1993:
    • 1523 patients with:
      • Clinical T1 to T3, N0 to N1 operable breast cancer were enrolled in the trial
    • 763 were randomized to preoperative therapy while
    • 760 were randomized to postoperative therapy
  • At 16-years of follow-up:
    • There was no difference in:
      • Disease-free survival:
        • HR = 0.93, 95% CI, 0.81 to 1.06
          • p = 0.27 or
      • Overall survival:
        • HR = 0.99, 95% CI, 0.85 to 1.16
          • p = 0.90
            • Between the postoperative and preoperative chemotherapy groups
  • In the preoperative group:
    • A pCR was documented in:
      • 13% of patients
  • Preoperative chemotherapy patients had a:
    • Significantly increased incidence of having:
      • Pathologically negative nodes compared to postoperative chemotherapy patients:
        • 58% vs. 42%, respectively
          • p<0.0001
  • The rate of breast conservation was higher:
    • Among women who received neoadjuvant chemotherapy compared to women who received postoperative chemotherapy:
      • 68% versus 60%, respectively
        • p = 0.001
          • The significant downstaging of tumors greater than 5 cm in the preoperative chemotherapy arm:
            • Primarily drove this breast conservation trend
  • There was a trend toward a higher rate of:
    • Ipsilateral breast tumor recurrence with preoperative vs postoperative chemotherapy:
      • 13% of 506 patients vs 10% of 450 patients, respectively:
        • Although this difference was not statistically significant (p = 0.21)
  • Retrospective series later found:
    • No difference in surgical complications:
      • Between women who received preoperative or postoperative chemotherapy
  • REFERENCES
    • Fisher B, Bryant J, Wolmark N, et al. Effect of preoperative chemotherapy on the outcome of women with operable breast cancer. J Clin Oncol. 1998;16(8):2672-2685.
    • Boughey JC, Peitinger F, Meric-Bernstam F, et al. Impact of preoperative versus postoperative chemotherapy on the extent and number of surgical procedures in patients treated in randomized clinical trials for breast cancer. Ann Surg. 2006;244(3):464–470.
    • Rastogi P, Anderson SJ, Bear HD, et al. Preoperative chemotherapy: updates of National Surgical Adjuvant Breast and Bowel Project Protocols B-18 and B-27. J Clin Oncol. 2008;26(5):778-785.

#ARRANGOIZ #BreastSurgeon #CancerSurgeon #SurgicalOncologist

Intraoperative Facial Nerve Monitoring during Parotidectomy

#Arrangoiz #HeadandNeckSurgeon #CancerSurgeon #SalivaryGlandSurgery

July Parathyroid Awareness Month

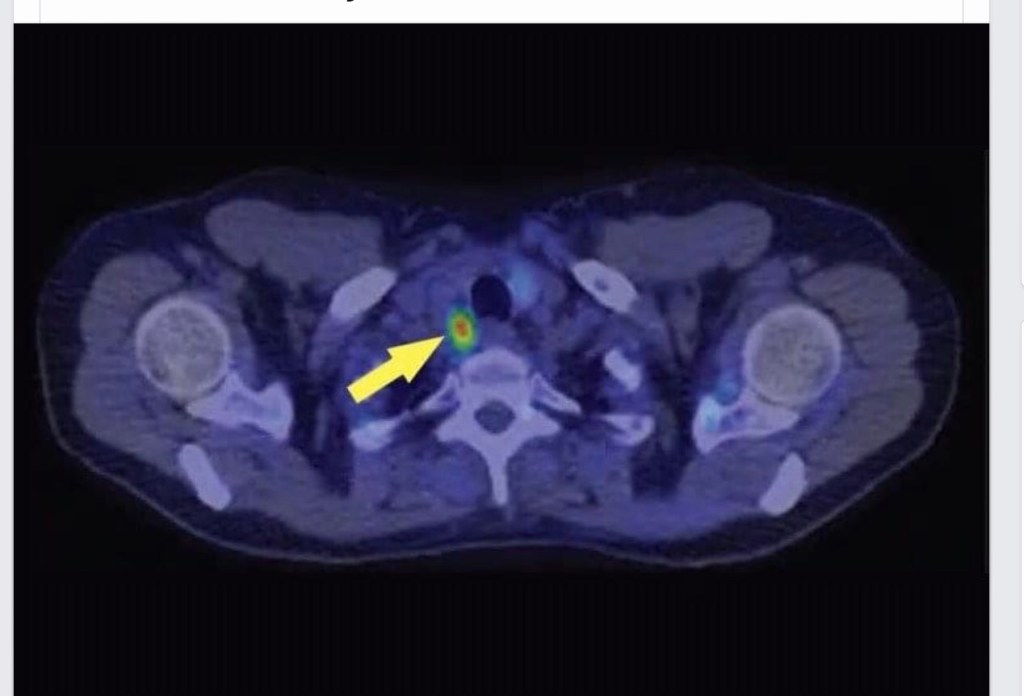
👉In patients with failure to localize on traditional imaging studies, PET choline may be an option and is offered at select centers around the country.

#CheckYourCalcium #Arrangoiz #ParathyroidSurgeon #ParathyroidExpert #HeadandNeckSurgeon

Rodrigo Arrangoiz MS, MD, FACS

  • I went to medical school at the Anahuac University in Mexico City, which is one of the most prestigious medical schools in Mexico:
    • I graduated Suma Cum Laude from this medical school and was the president of the student medical council.
  • I trained in general surgery at Michigan State University where I was named chief resident during my fifth year of residency which was a great honor.
  • My complex surgical oncology fellowship which included a head and neck training was performed at the Fox Chase Cancer Center in Philadelphia, Pennsylvania.
  • At the same time, I undertook a Masters in Science (Clinical Research for Health Care Professionals) at Drexel University in Philadelphia, Pennsylvania.
  • I also performed a two-year global online fellowship in Head and Neck Surgery and Oncology with the International Federations of Head and Neck Societies / Memorial Sloan Kettering Cancer Center.
    • I encountered patients with very complex problems, and the greatest lesson I learned was there are always treatment options, utilizing all different types of techniques including radiation, chemotherapy and surgery.
      • This comprehensive training has provided me with an extensive understanding of the multidisciplinary approach to treating patients with cancer.
  • I have developed a particularly strong interest in the surgical and multimodal treatment of patients with breast cancer, head and neck cancer (including thyroid and parathyroid cancer), and endocrine diseases (benign and malignant thyroid and parathyroid diseases), using traditional surgery, regional therapies, and minimally invasive techniques.
    • I am an expert in the treatment of thyroid cancer including; active surveillance for early, small papillary thyroid cancers, minimally invasive thyroid surgery, selective and comprehensive neck dissections.
    • For the management of parathyroid disease, I offer a minimally invasive radio-guided technique called MIRP (minimally invasive radio-guided parathyroidectomy) through a 2 cm incision which will allow the patient to have a great cosmetic result and quick return to normal life after the operation.
    • I am extremely aware of the impact that a breast cancer diagnosis has on a patient. I do my best to promote a positive atmosphere in which to start my patients’ course of treatment and take the time to explain the pros and cons of each treatment option, so that they can make an informed decision.
      • My management philosophy also includes, not just an emphasis on successful treatment, but also preserving a good cosmetic outcome. I feel fortunate to be a fellowship trained, very highly specialized clinician, because this combination of factors allows me, and our treatment team to focus on one thing all day, every day, and do it well: curing cancer. I think there is nothing more rewarding that I could do as a clinician.
  • I hold my patients as my number one priority. I will spend as much time as necessary educating, answering questions and providing guidance for each individual patient to help them throughout each stage of their management. I believe in honest discussions, where both the patients and family’s goals and expectations are openly communicated. We will work together as a team to put together an evidence based personalized treatment plan. My personal goal is to treat and care for every patient with the same compassion and honesty as if they were a friend or family member.

👉Will join the Center for Advanced Surgical Oncology at Palmetto General Hospital as a breast / thyroid / parathyroid / head and neck surgeon in July, 2020

#Arrangoiz #Surgeon #CancerSurgeon #HeadandNeckSurgeon #BreastSurgeon #SurgicalOncologist #PalmettoGeneralHospital #CenterforAdvancedSurgicalOncology

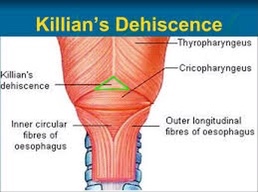
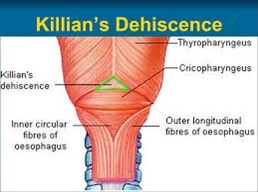
Killian’s dehiscence

  • Killian’s dehiscence:
    • Also known as:
      • Killian’s triangle
      • Laimer triangle
      • Laimer-Killian triangle
      • Laimer-Haeckermann area
    • Is a triangular area in the wall of the pharynx:
      • Between the thyropharyngeal and cricopharyngeus muscle of the inferior constrictor of the pharynx:
        • It represents a potentially weak spot:
          • Where a pharyngoesophageal diverticulum (Zenker’s diverticulum) is more likely to occur

#Arrangoiz #HeadandNeckSurgeon #CancerSurgeon #Surgeon #Teahcer

Zenker Diverticulum

  • Zenker diverticulum:
    • Is a pulsion-pseudodiverticulum:
      • Results from herniation of mucosa and submucosa:
        • Through the Killian triangle (or Killian dehiscence):
          • A focal weakness in the hypopharynx:
            • At the normal cleavage plane between the fibres of the inferior pharyngeal constrictor (thyropharyngeus muscle) and the cricopharyngeus muscles

#Arrangoiz #Surgeon #CancerSurgeon #HeadandNeckSurgeon #Teacher

Regional Nodal Metastases in Hypopharyngeal SCC

  • In more than 80% of patients:
    • Tumors spread to involve the local lymph nodes are detected on physical examination or by imaging at first presentation
  • The lymphatics fluid flows mostly via collectors into the lymph nodes of :
    • Levels II and III:
      • A direct relationship to level I has not been detected
    • Drainage to involve level IV occurs frequently
  • The lymphatic drainage of the posterior pharyngeal wall occurs:
    • Mainly first into:
      • The retropharyngeal lymph nodes:
        • Accounts for over 40% cases
  • In hypopharyngeal cancers:
    • Because of its advanced stage at presentation and its involvement or extension to cross the midline:
      • The risk of contralateral metastases is high, with histological identification of tumor in:
        • More than 20% of cases treated surgically, and supports the therapeutic decision:
          • To treat both sides of the neck, either by surgery or by radiotherapy in the N0 neck

#Arrangoiz #Teacher #Surgeon #CancerSurgeon #HeadandNeckSurgeon #NasopharyngealCancer

Overall Survival rate for the Cancers of Hypopharynx and Esophagus

  • The overall survival rate:
    • For the cancers of hypopharynx and esophagus:
      • Remains disappointing:
        • The reported 5-year overall survival rates:
          • Range from 30% to 50%
  • The poor survival rate is, in part, due to:
    • Frequent multicentricity
    • Submucosal spreading
    • High likelihood of advanced primary and nodal disease on presentation

#Arrangoiz #Teacher #CancerSurgeon #SurgicalOncologist #HeadandNeckSurgeon

T Stage of Nasopharyngeal Carcinoma (NPC) 8th Edition AJCC

  • TX – Primary tumor cannot be assessed
  • T0 – No tumor identified, but EBV-positive cervical node(s) involvement
  • T1 – Tumor confined to nasopharynx, or extension to oropharynx and/or nasal cavity without parapharyngeal involvement
  • T2 – Tumor with extension to parapharyngeal space, and/or adjacent soft tissue involvement (medial pterygoid, lateral pterygoid, prevertebral muscles)
  • T3 – Tumor with infiltration of bony structures at skull base, cervical vertebra, pterygoid structures, and/or paranasal sinuses
  • T4 – Tumor with intracranial extension, involvement of cranial nerves, hypopharynx, orbit, parotid gland, and/ or extensive soft tissue infiltration beyond the lateral surface of the lateral pterygoid muscle

#Arrangoiz #CancerSurgeon #HeadandNeckSurgeon #NasopharngealCancer #Teacher