BACKGROUND The number of people diagnosed with thyroid cancer in the United States has been increasing steadily over the last several decades. Fortunately, most cases of this disease will be a non-aggressive subtype, called classical papillary thyroid cancer, which, when treated correctly, is very unlikely to be dangerous. This being said, there are other, less common forms of thyroid cancer that are more dangerous than papillary thyroid cancer. These more aggressive thyroid cancer subtypes tend to grow faster and spread (metastasize) to other parts of the body sooner. Such aggressive cancer subtypes include diffuse sclerosing variant, tall cell variant, poorly differentiated thyroid cancer and insular variant.
There are a number of important questions about these uncommon, more aggressive thyroid cancer subtypes that remain to be answered. Unlike classical papillary thyroid cancer, we do not know for sure if the number of people diagnosed with these thyroid cancer types is increasing over time. We also do not know exactly how dangerous these cancer types are, at least compared to classical papillary thyroid cancer. The study described here tries to answer these two questions by evaluating the medical records of large groups of people previously treated for thyroid cancer. By answering these questions, the study authors hope to better understand aggressive types of thyroid cancer and, in particular, to get a better idea of how to treat them.
THE FULL ARTICLE TITLE Ho AS et al 2020 Incidence and mortality risk spectrum across aggressive variants of papillary thyroid carcinoma. JAMA Oncol. Epub 2020 Mar 5. PMID: 32134428.
SUMMARY OF THE STUDY The study authors reviewed the medical records of people who were treated for any kind of thyroid cancer in the United States during the 16 year period between 2000 and 2016.
These medical records were identified by examining two large data bases that store information about people being treated for cancer, including the U.S. National Cancer Data Base and the U.S. Surveillance, Epidemiology, and End Results (SEER) data base. In the end, the authors found 5,447 cases of aggressive subtype thyroid cancer, compared to 35,812 cases of classical papillary thyroid cancer. They also found that these aggressive cancer types became increasingly more common during the 16 year study period and that the number of aggressive type thyroid cancer cases grew faster than the number of classical papillary thyroid cancer cases diagnosed in the same timeframe. Similarly, the authors learned that the aggressive subtype thyroid cancers identified were, on average, bigger than the classical papillary thyroid cancer type and were more likely to spread into both neighboring tissues and to other parts of the body. In addition, when the aggressive thyroid cancer types were evaluated individually, the study team found that the four thyroid cancer types evaluated were not equally dangerous. The insular variant type was found to be the most dangerous, with the lowest survival rate, followed by poorly differentiated thyroid cancer, tall cell variant and, least dangerous, diffuse sclerosing variant. In fact, the overall rate of survival for people diagnosed with diffuse sclerosing variant was similar to those diagnosed with classical papillary thyroid cancer, suggesting that the diffuse sclerosing variant subtype may not be particularly dangerous.
WHAT ARE THE IMPLICATIONS OF THIS STUDY? The study authors concluded that aggressive thyroid cancer types are becoming increasingly common and confirmed that 3 of the 4 aggressive cancers are more dangerous than classical papillary thyroid cancer. The diffuse sclerosing variant was found to be similar to the classical papillary thyroid cancer. Moreover, these investigators found that the rate at which these cancer types are being diagnosed is growing faster than that of other classical papillary thyroid cancer. The findings of this study are important because they alert us that relatively aggressive forms of thyroid cancer appear to be increasingly common and need to be treated more aggressively when diagnosed. Additionally, more studies are needed into how and why these thyroid cancer subtypes develop
👉The number of new thyroid cancer cases has increased over recent years, especially the number of small, low-risk papillary thyroid cancers.
👉It is clear now that treating these small cancers aggressively with surgery results in more potential harm to patients than if the small cancer was simply watched.
👉Because of this, simply watching, known as active surveillance, became a promising alternative to surgery for these low-risk cancers in select patients.
👉Active surveillance involves closely monitoring the thyroid cancer over time, instead of treating it with immediate surgery.
👉Prior studies have shown that active surveillance is safe in papillary thyroid cancers measuring 1 cm or smaller and confined to the thyroid without any lymph node involvement or spread outside of the neck.
👉However, little is known about outcomes of active surveillance for patients with larger cancers measuring 1 to 2 cm and confined to the thyroid.
👉This study compared outcomes of active surveillance for these patients to this with cancers less than 1 cm.
👉The authors also examined outcomes of patients who had surgery for these small cancers.
👉THE FULL ARTICLE TITLE: Sakai T et al 2019 Active surveillance for T1bN0M0 papillary thyroid carcinoma. Thyroid 29:59–63. Epub 2019 Jan 8. PMID: 30560718.
👉The study included patients who were followed at the Cancer Institute Hospital in Tokyo, Japan, since 1995.
👉Among 406 patients with papillary thyroid cancer less than 1 cm, 360 (89%) underwent active surveillance and 46 (11%) underwent surgery.
👉Among 392 patients with papillary thyroid cancer 1 to 2 cm, 331 (84%) underwent active surveillance and 61 (16%) underwent surgery.
👉The patients in the active surveillance program were followed with physical exam, neck ultrasound and chest X-rays every 6 to 12 months after diagnosis.
👉These patients were evaluated for increase in cancer size, development of spread to the lymph nodes and spread to other parts of the body.
👉The follow-up was 7.3 – 7.9 years.
👉If progression of the cancer was seen or the patient changed their mind, surgery was performed.
👉The authors found that the 5- and 10-year rates of progression were similar in patients with papillary thyroid cancer less than 1 cm compared with those with 1 cm to 2 cm cancers during active surveillance.
👉A total of 11 patients with 1 to 2 cm cancers had surgery after active surveillance and none had the cancer come back.
👉Of the patients with 1 to 2 cm cancers who had immediate surgery, 8 had the cancer come back.
👉The rate of cancer coming back was significantly higher for cancers ≥ 1.5 cm than < 1.5 cm in this group.
👉WHAT ARE THE IMPLICATIONS OF THIS STUDY? 1. This study showed that patients with 1 to 2 cm papillary thyroid cancers had similar progression rates to patients with less than 1 cm cancers during active surveillance. 2. Additionally, delayed surgery was not associated with any harm in these patients. 3. These findings are important as they show that active surveillance of small thyroid cancers, especially those less than 15 mm in size, is safe. 4. Expanding active surveillance to larger cancers would decrease the number of thyroid surgeries and subsequent complications. However, more research is still needed to determine exactly which thyroid cancer patients are ideal for active surveillance, considering age, other health issues and the expertise of treatment team.
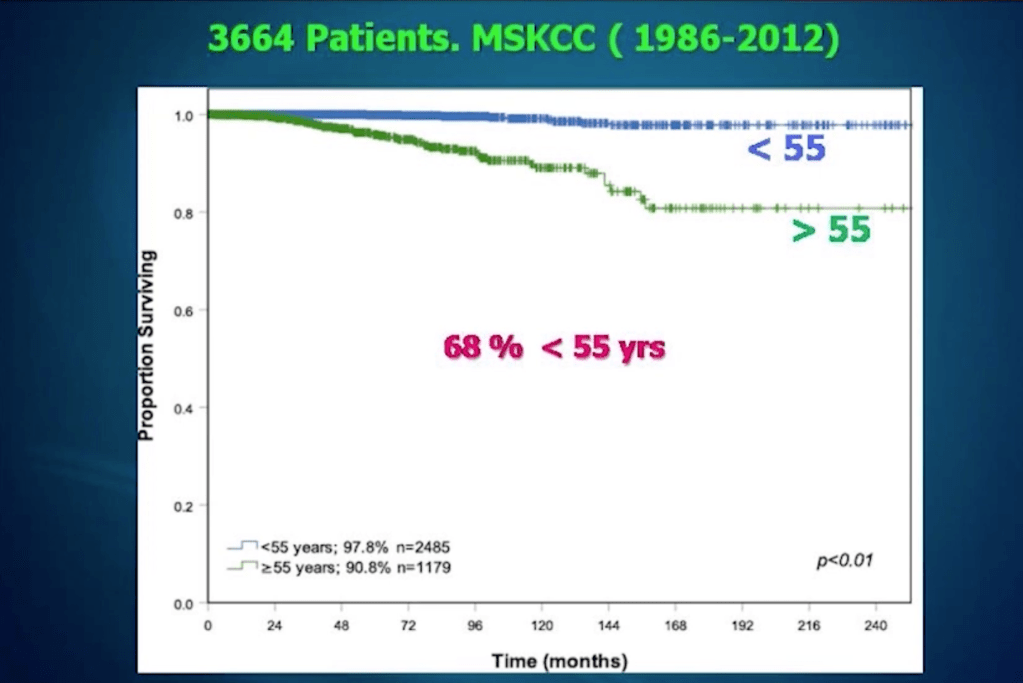
Disease Specific Survival – Age Stratification at 55 years
Age is a very strong predictor of outcome:
In differentiated thyroid cancer
Nearly 2/3 of the patients are younger that 55 years of age
They have a great long term survivorship:
Nearly 100% at 20 years
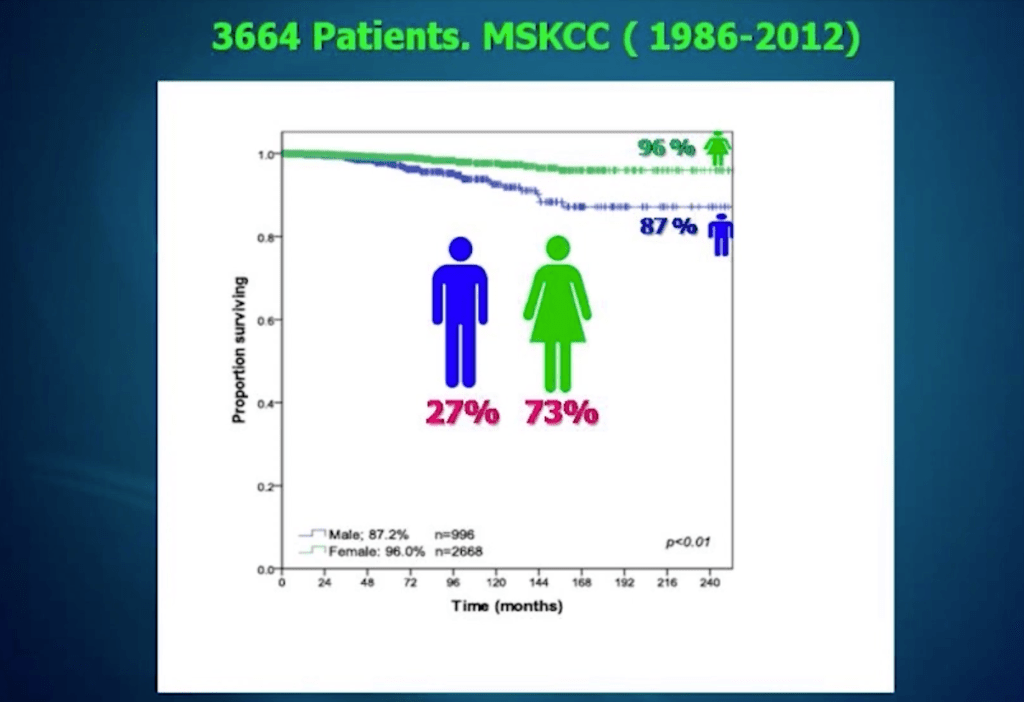
Disease Specific Survival – Gender
The majority of patients with thyroid cancer are women:
In this study from MSKCC
73% of the cases were in women
Women have a slightly better 20 year survival (96%) compared to men (87%)
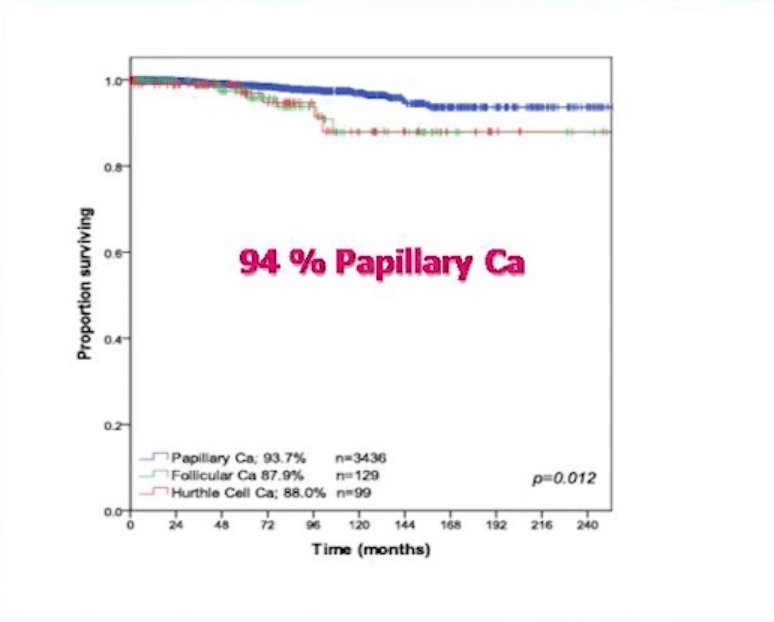
Disease Specific Survival – Tumor Histology
94% of patients had papillary thyroid carcinoma with a very good longterm survival (93.7%) compared to follicular (87.9%) and Hurthle cell carcinomas (88%)
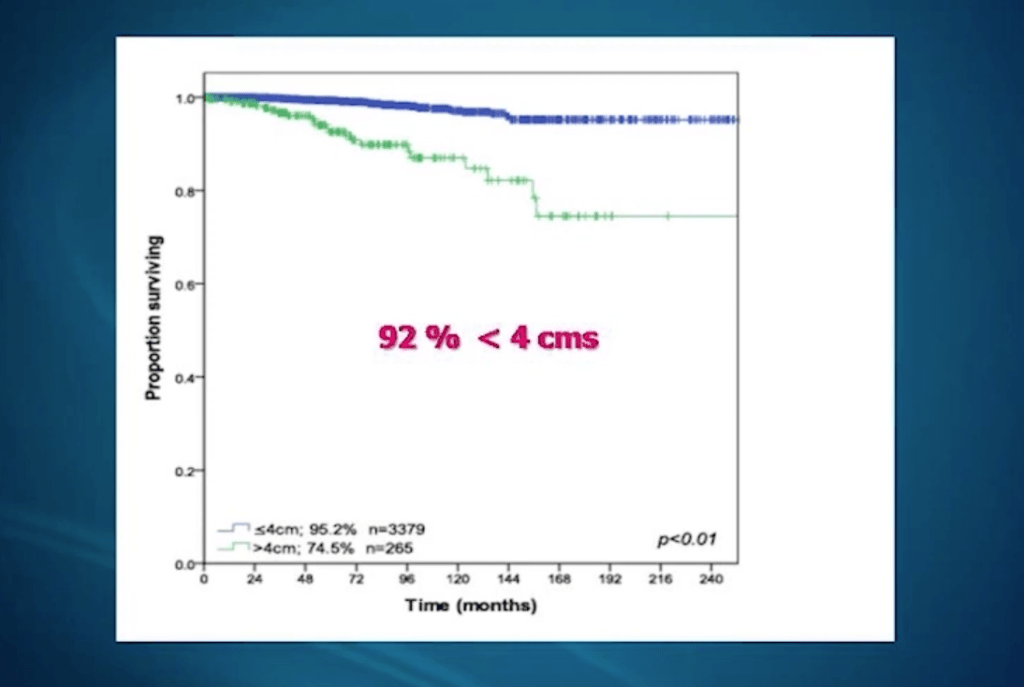
Disease Specific Survival – Tumor Size
In this study from MSKCC 92% of the patients had tumors less than 4 cm in size:
Tumors less that 4 cm in size had an excellent long term survival (95.2%) compared to tumors larger than 4 cm (74.5%)
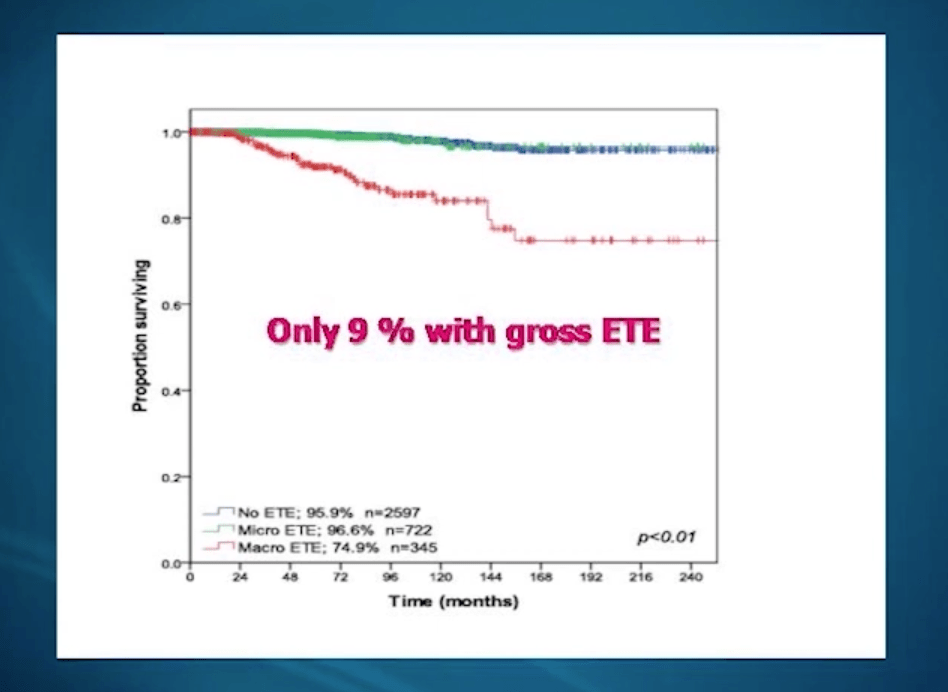
Disease Specific Survival – Extrathyroid Extension
Gross extra-thyroid extension (ETE) only occurs in a minority of patients (9%):
This patients have a worse overall survival (74.9%) compared intra-thyroidal tumors (95.9%) and tumors with microscopic (96.6%) extra-thyroidal extension
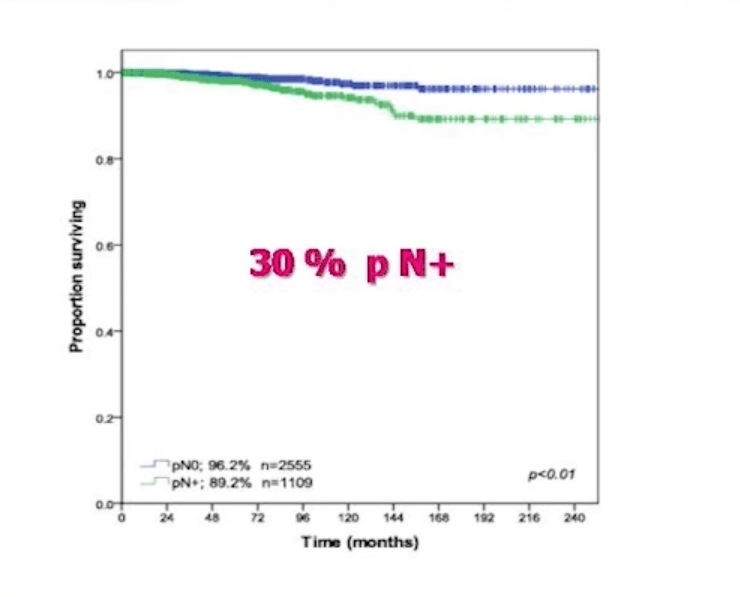
Disease Specific Survival – Lymph Node Metastases N0 vs N+
Lymph node metastasis in general has a negative impact in long term survival:
However this difference is relatively small:
96.2% in node negative patients vs. 89.2% in node positive patients
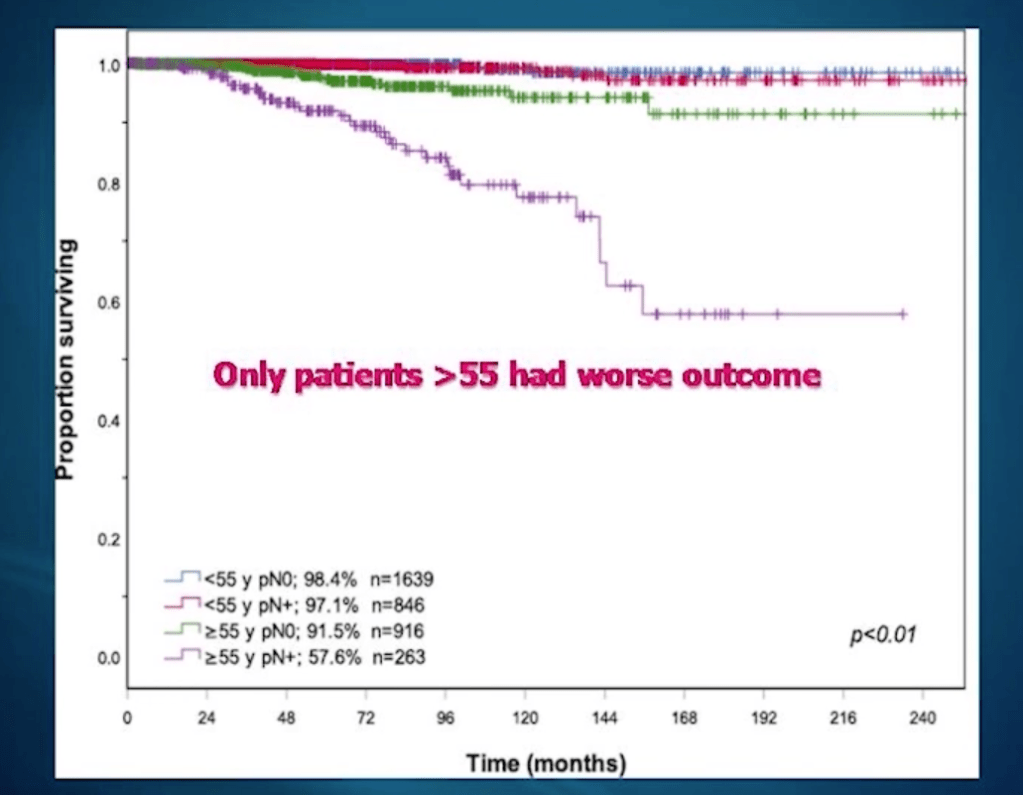
Studying the effect of lymph node metastasis in thyroid cancer survival:
Lymph node metastasis only had an adverse effect on survival in older patients (older than 55 years):
There is a progressive decline in disease specific survival as the years go bye
Young patients with and without nodal metastasis have excellent long term survival
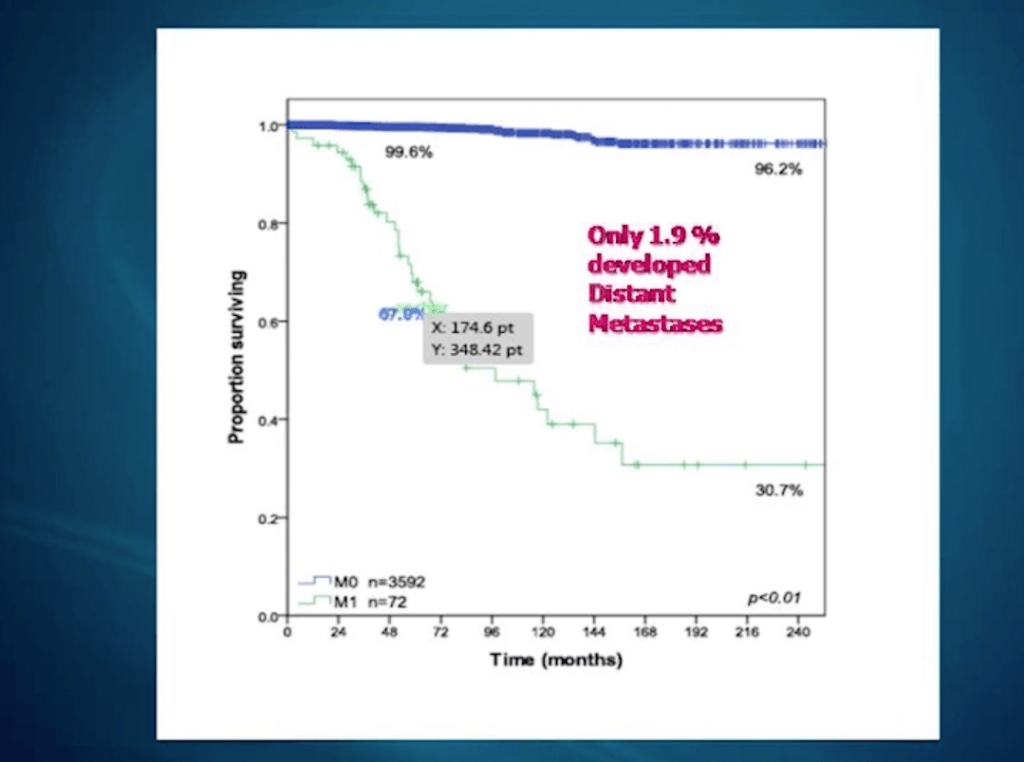
Disease Specific Survival – Lymph Node Metastases and AgeDisease Specific Survival – Distant Metastasis
Distant metastasis will have an impact on long term survival:
Fortunately only 1.9% of differentiated thyroid cancers with present with distant metastasis
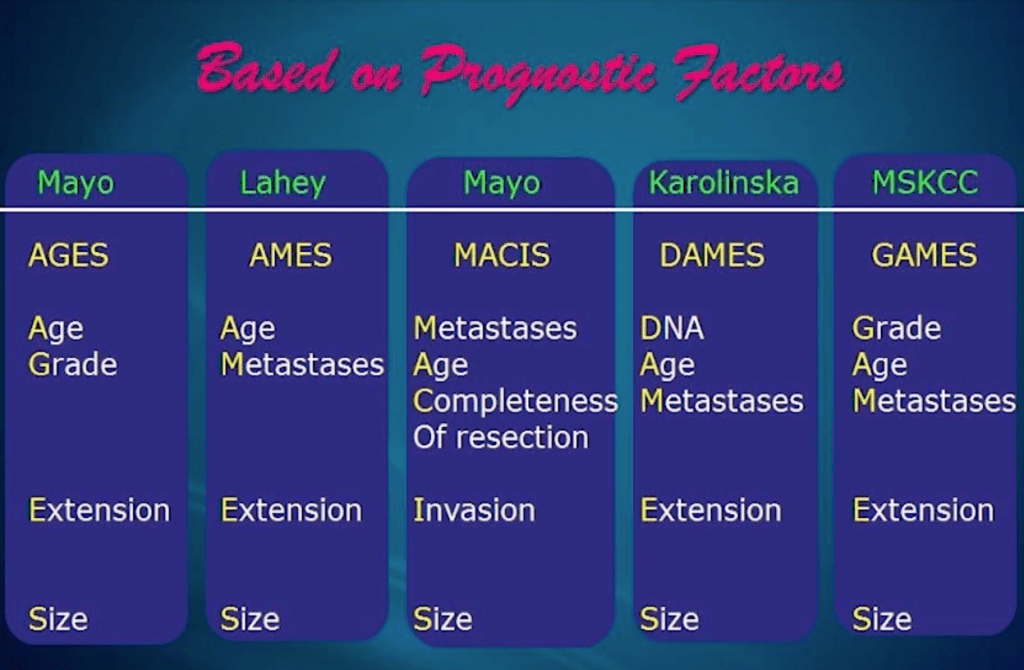
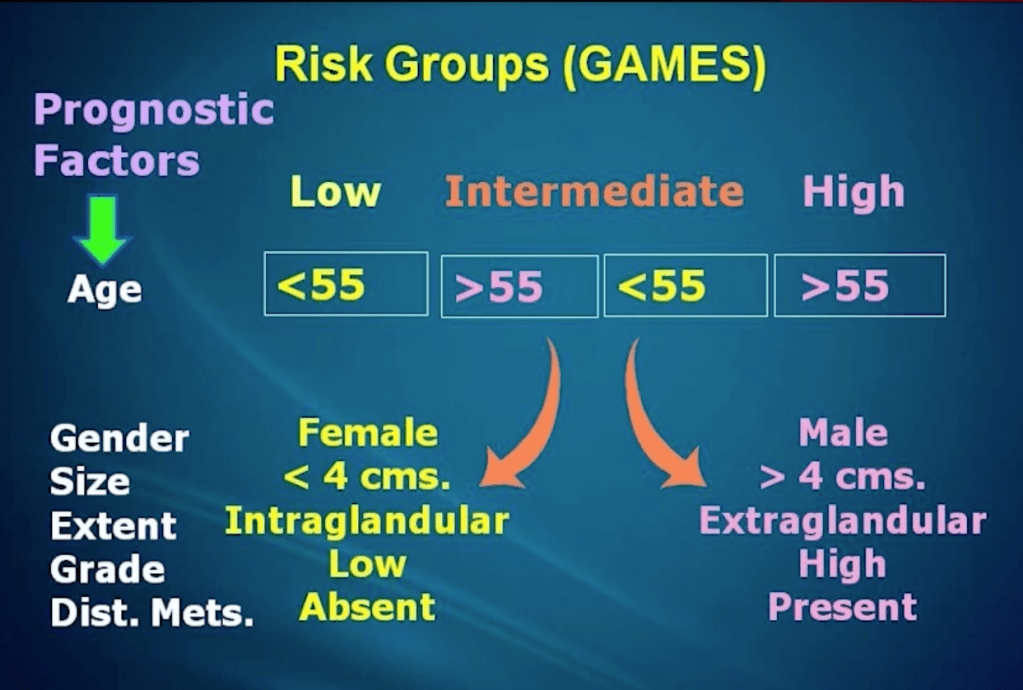
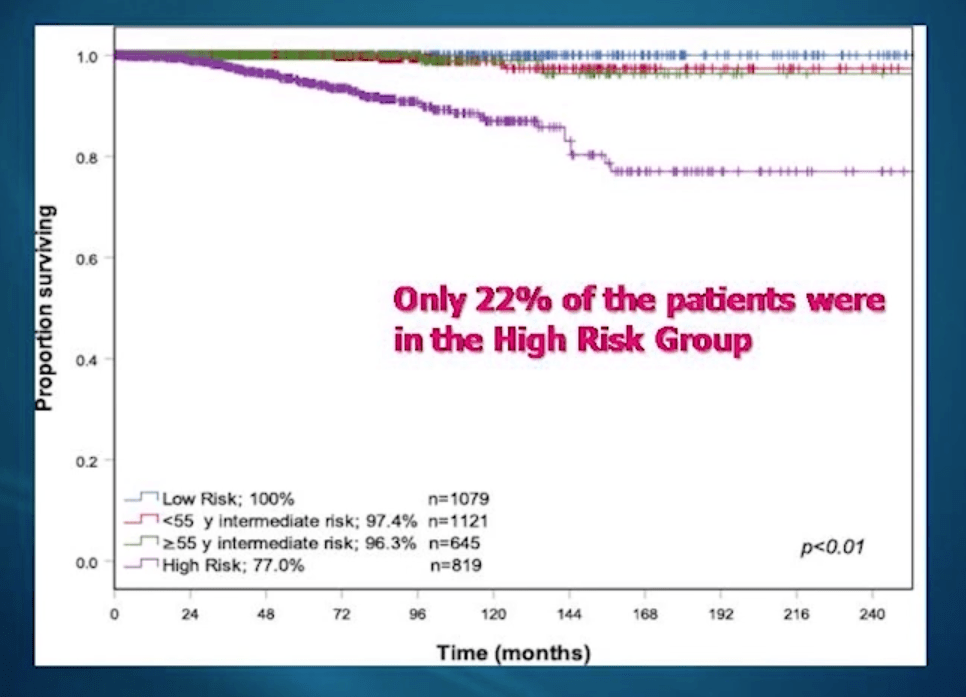
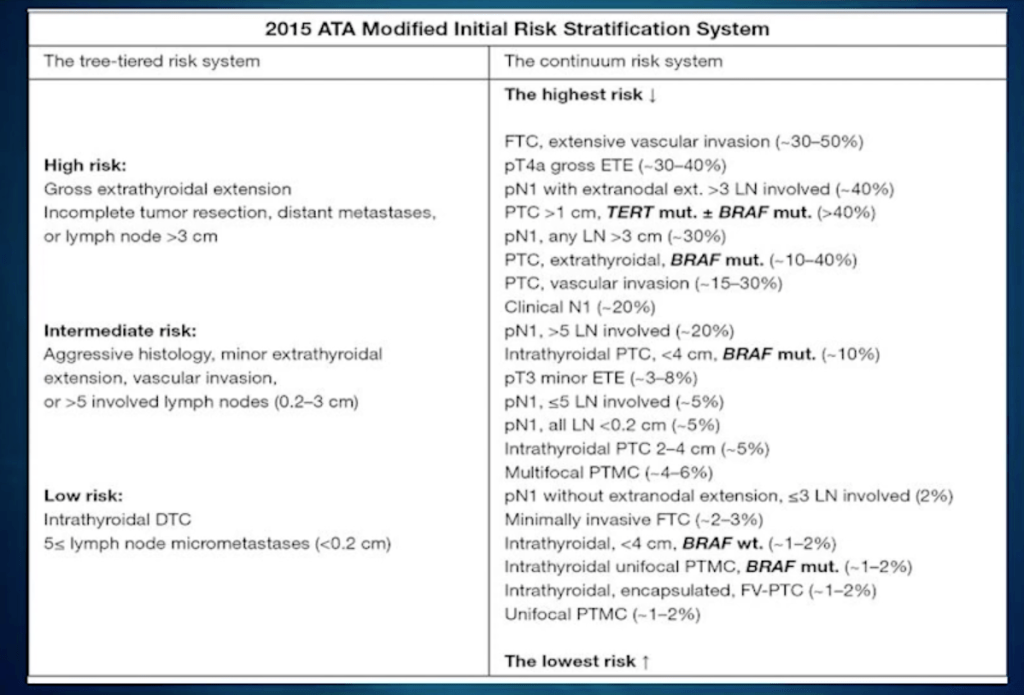
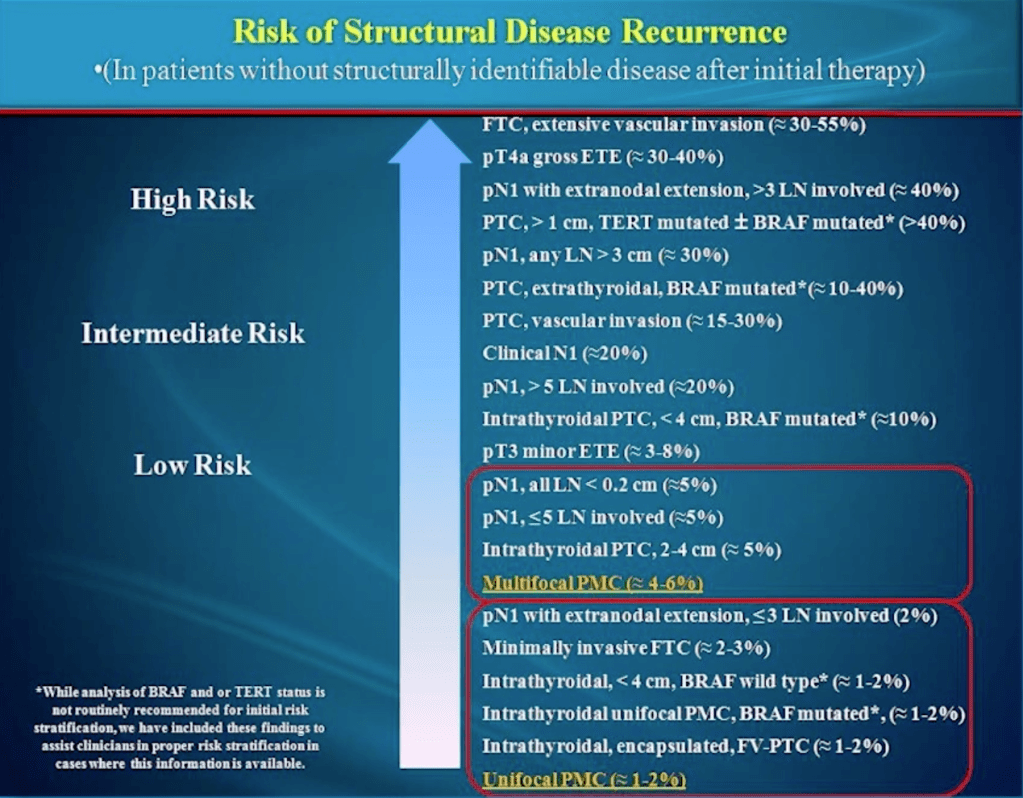
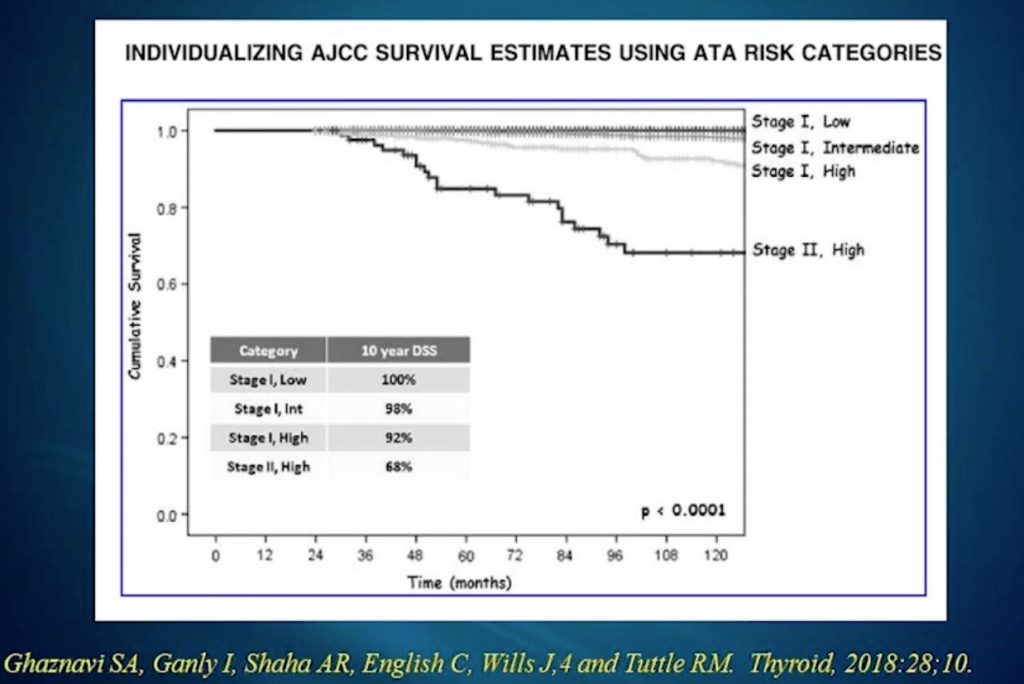
Differentiated Thyroid Cancer – GAMESPatients in the GAMES low risk group have a 100% 20 year survival compared to the GAMES high risk group that only has a 77% 20 year survival. The intermediate GAMES group have a greater than 95% 20 year survival. Risk of RecurrenceTen-year DSS in 4881 DTC patients age less than 55 years at diagnosis by the 8th edition of the AJCC stage stratified by ATA risk category.
Only stage II patients with an ATA high risk category will have a a progressive increase in mortality as the years pass.
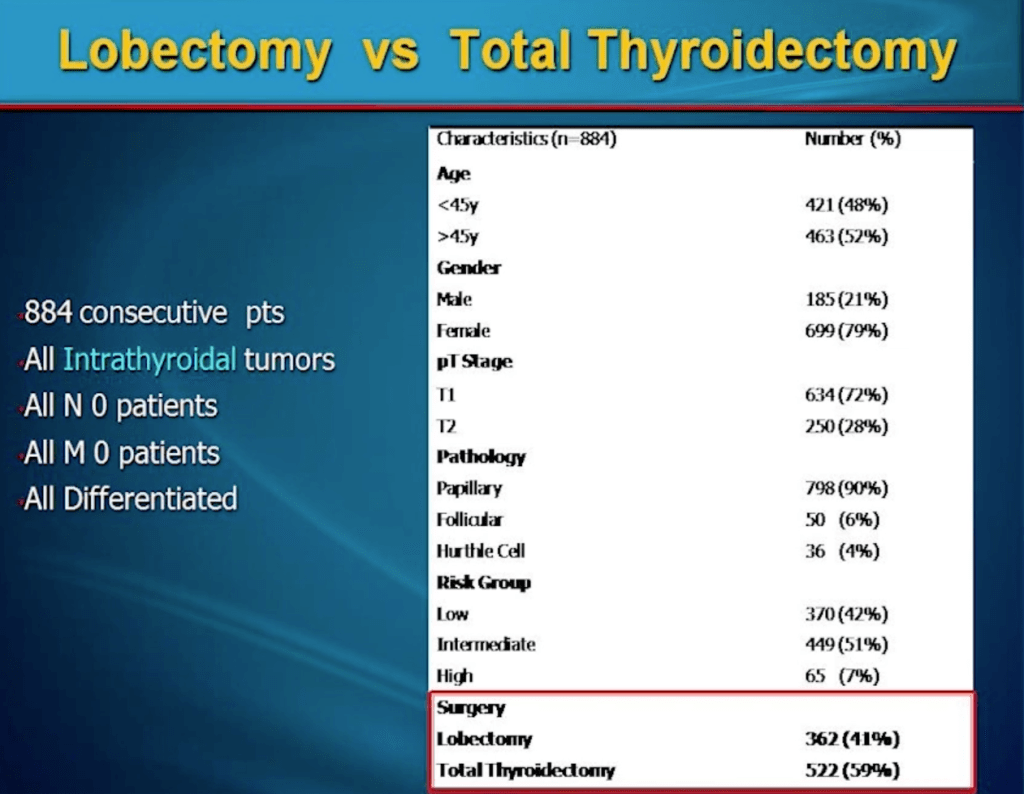
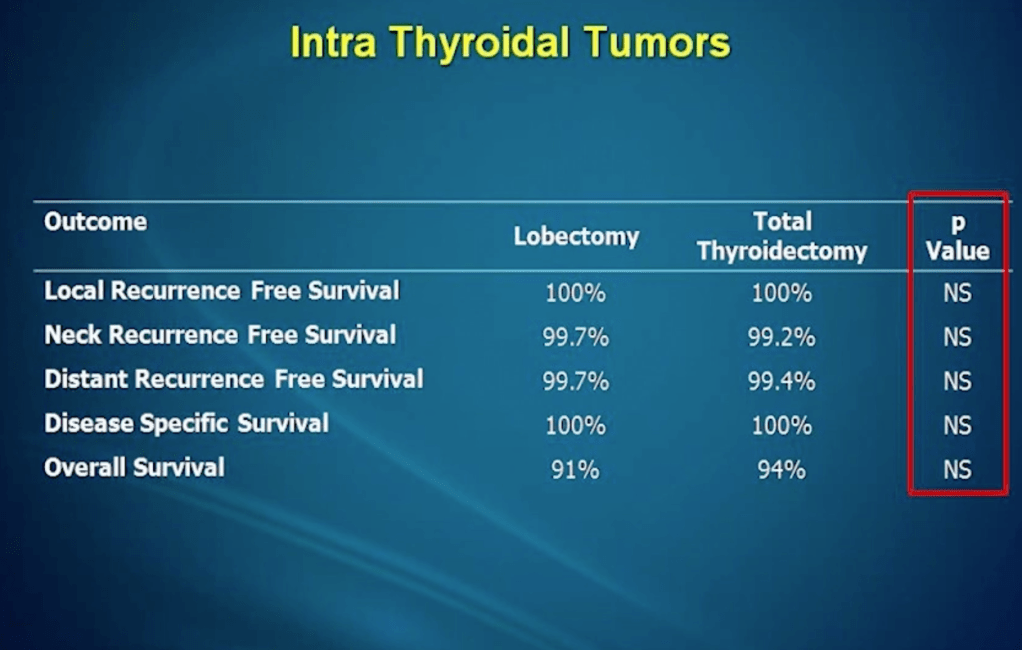
Lobectomy
The surgical outcome between total thyroidectomy and lobectomy is comparable when compared for:
Local recurrence free survival
Neck recurrence free survival
Distant recurrence free survival
Disease specific survival
Overall survival
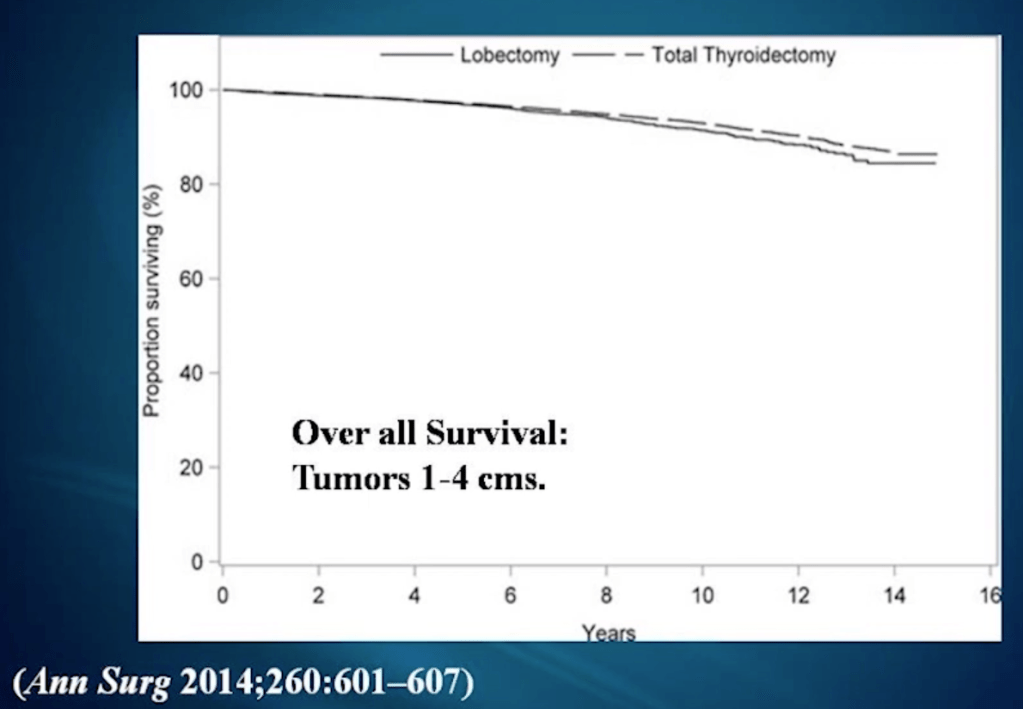
10 year survival – Lobectomy vs Total Thyroidectomy Extent of Surgery for Papillary Thyroid Cancer is Not Associated with a Survival Differance – An Analysis of 61,775 Patients (ACS, NCDB 1998-2006) Extent of Surgery for Papillary Thyroid Cancer is Not Associated with a Survival Differance – An Analysis of 61,775 Patients (ACS, NCDB 1998-2006) Isthmusectomy
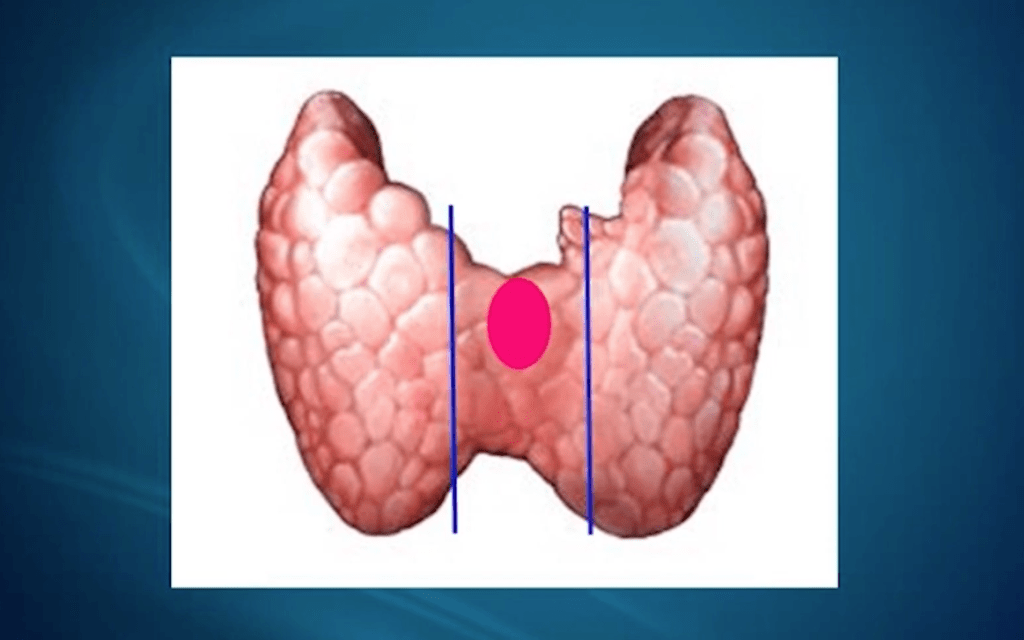
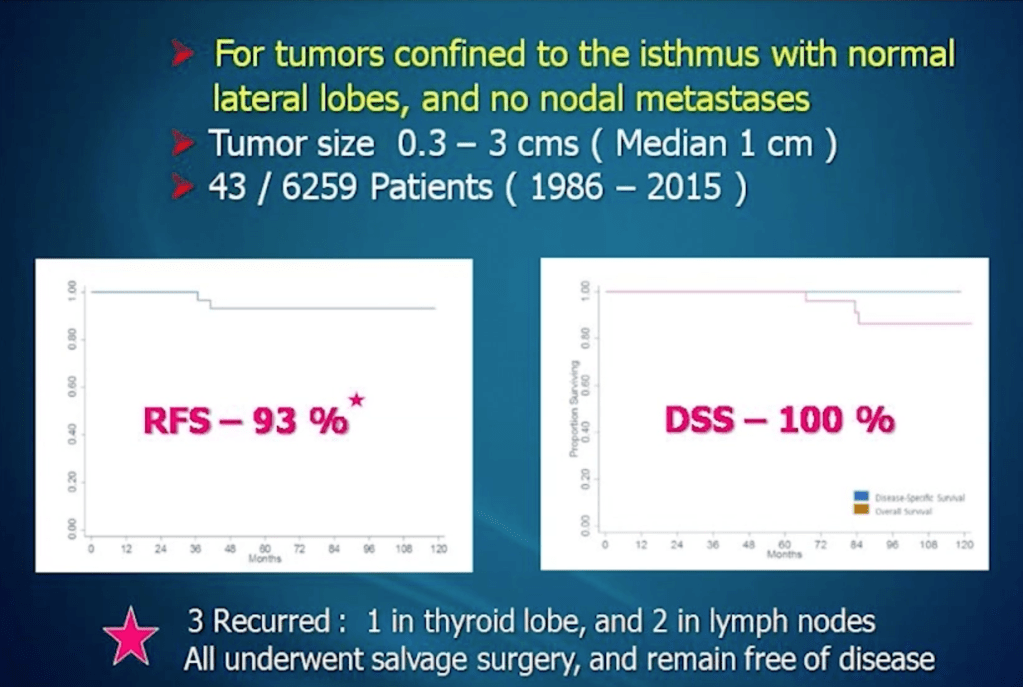
What to do if the differentiated thyroid cancer is located to the isthmus and the lateral lobes are normal and no lymph node metastasis?
Is simple isthmusectomy the appropriate procedure?
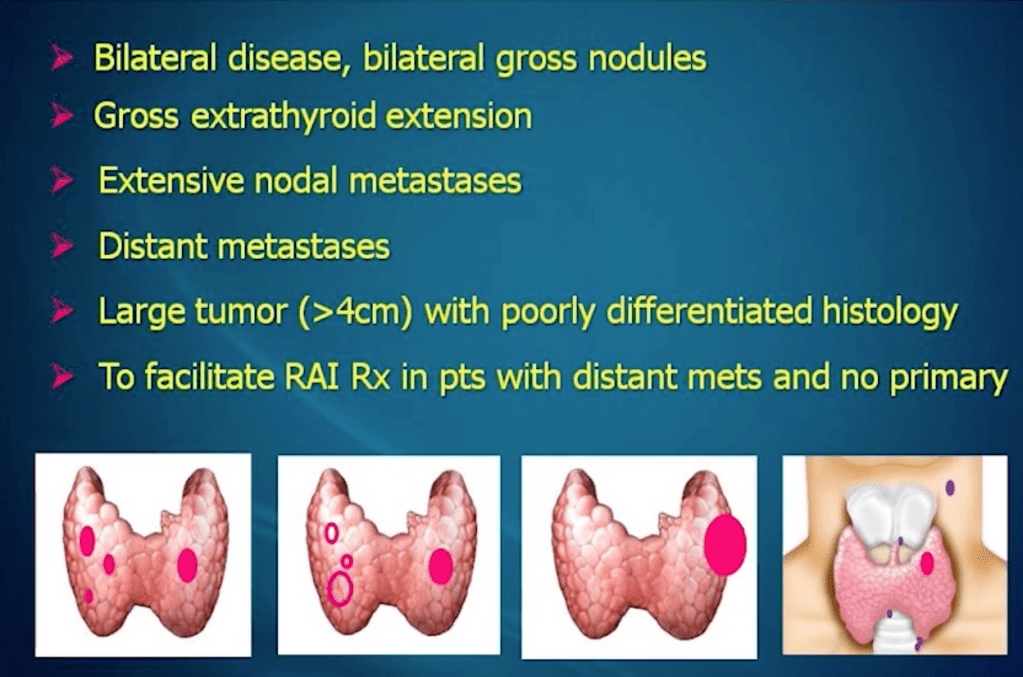
Indications for a Total Thyrtoidectomy
When to perform more that a total thyroidectomy?
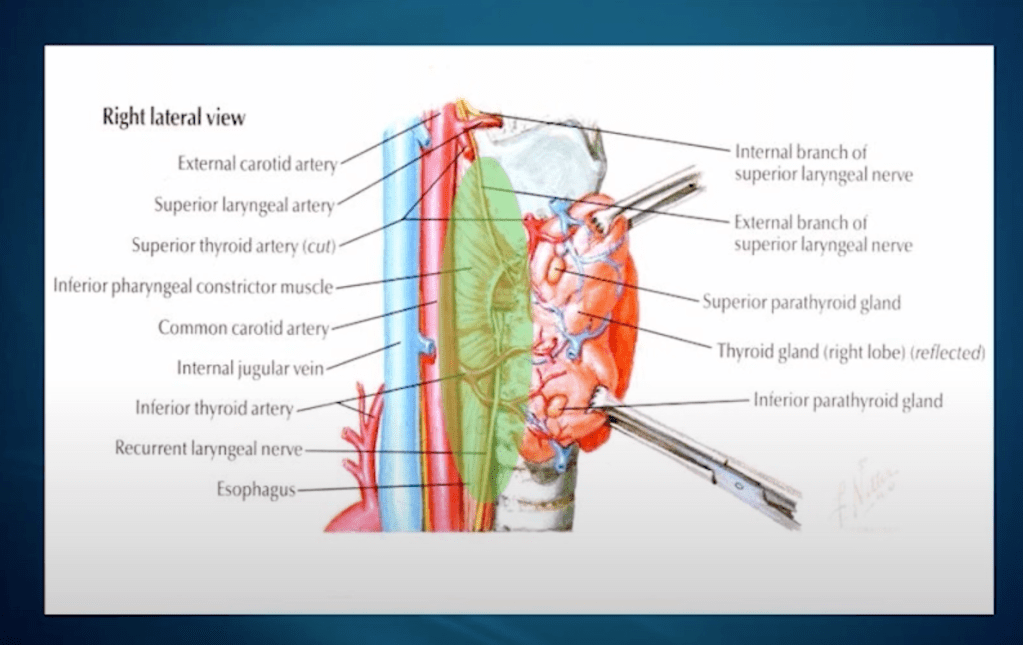
Gross extra thyroidal extension (anteriorly or posteriorly)
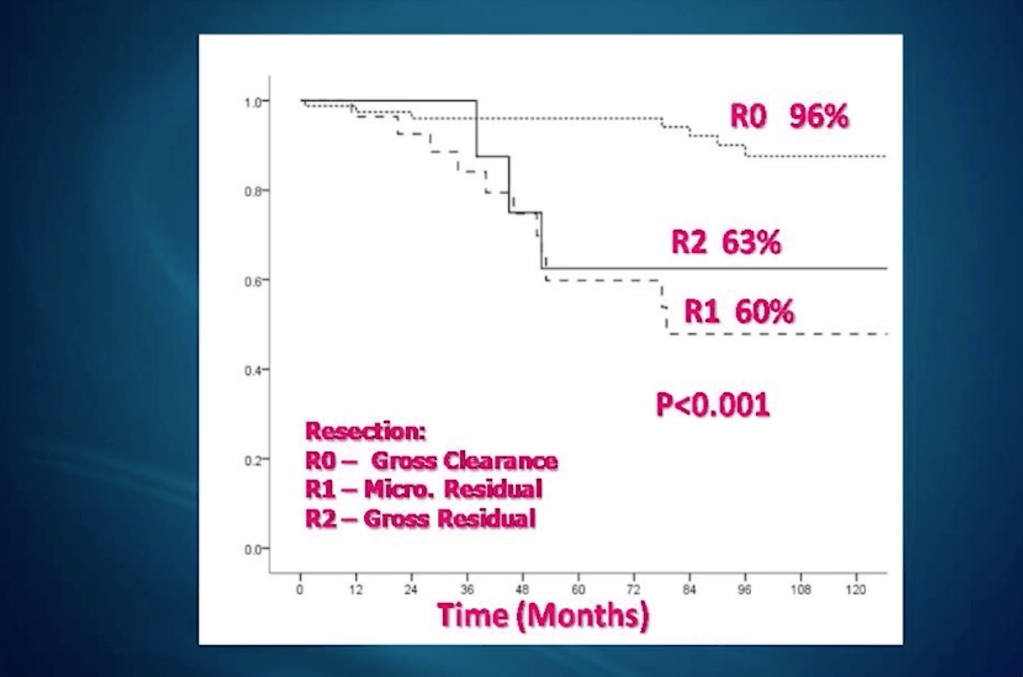
Surgery for Extrathyroid ExtensionLong term Survival after Resection of Locally Advanced Thyroid Cancer
An R0 resection is fundamental when operating for gross extrathryoidal extension and performing more than a total thyroidectomy:
Patients in which an R0 resection can be performed will have long term survival exceeding 95% compared to patient with an R1 resection (60%)
R1 or R2 resections leads to a 40% decrease in survival
Numerous histologic variants of PTC have been described based on architectural or cellular features
Acknowledgement of the tumor subtype is important:
As it can contribute to the risk stratification of individual tumors
The classic subtype of PTC and the follicular subtype of PTC (FVPTC) are associated with very favorable outcomes
More concerning histologic subtypes include:
Tall cell, hobnail subtype, and, perhaps to a lesser extent, columnar cell:
These tumors tend to present at an older age and with more advanced disease than is seen in classic PTC
These more aggressive histologic subtypes:
Also are associated with worse recurrence-free and disease-specific survival rates
Tumor Size
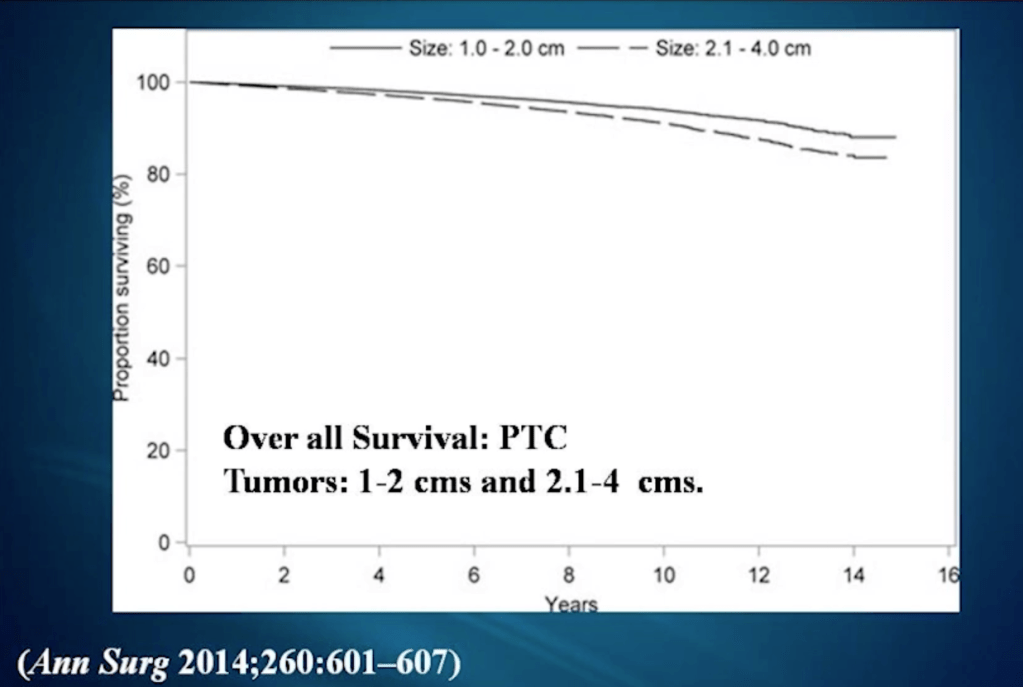
Primary tumor size is closely associated with the outcome of PTC, including both 10-year recurrence and cancer-specific mortality rates
Cancer-specific mortality rates increase incrementally from 2% for tumors 8 cm
Furthermore, larger tumors are associated with a higher rate of locoregional and distant metastases
Multifocality
Patients with PTC have a 32% to 45% chance of cancer elsewhere in the ipsilateral or contralateral lobe
Tumor multifocality is also found frequently in papillary thyroid microcarcinomas (PMCs)
Multifocal disease increases the risk of recurrence, particularly in patients who have had a lobectomy
With the current trend to performing lobectomy for the majority of low-risk cancers, some have raised concerns about the potential for increased recurrence rates
Indeed, some patients may develop recurrence in the remaining contralateral lobe, necessitating completion thyroidectomy at a later date:
Fortunately, it is the minority (7% at 10 years of follow-up) of patients who will require such an intervention
A large, long-term follow-up study of patients undergoing lobectomy for PTC:
14.6% of whom had multifocal disease, demonstrated a recurrence-free 20-year survival rate of 95% in the opposite lobe, 91% for lymph node (LN) recurrence, and a disease-specific survival rate of 97.8%
Predictors of recurrence or worse disease-specific survival were:
Age
Primary tumor > 4 cm
Clinically apparent LNs
Suggesting that properly selected patients will have an excellent prognosis after lobectomy of PTC
The implications of tumor multifocality on survival are controversial:
Some studies have determined that multifocal disease does not increase the risk of disease-specific mortality
However, when distinguishing unilateral multifocal from bilateral disease, other studies have demonstrated that survival was lower for bilateral tumors
Extrathyroidal Extension
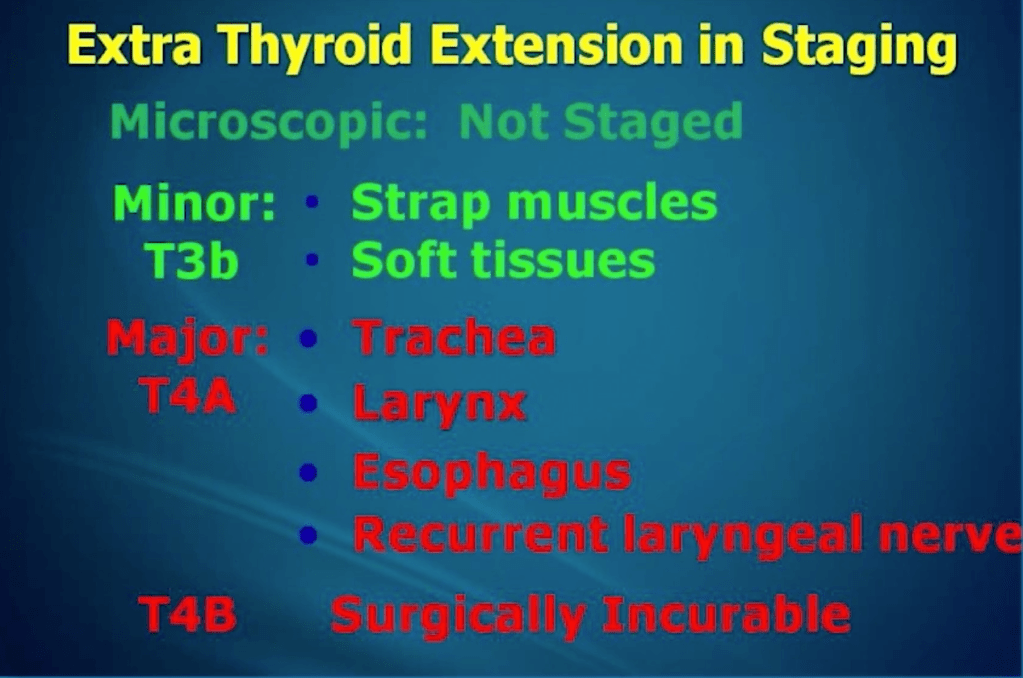
Extrathyroidal extension (ETE) of tumor beyond the thyroid capsule into the perithyroidal soft tissues and adjacent structures:
May be seen in up to 40% of surgical specimens and is an important prognostic factor in PTC
The specific extent of ETE should be described on the surgical pathology report
Minimal ETE is defined as:
Microscopic visualization of tumor into the immediate perithyroidal soft tissues
In contrast, extensive ETE is described as:
Gross tumor extension into subcutaneous soft tissues, larynx, trachea, esophagus, or the recurrent laryngeal nerve (RLN)
The prognostic implications of ETE in differentiated thyroid cancer is controversial, which may stem largely from a failure to distinguish between these distinct degrees of tumor spread
It is generally accepted that tumor extension into the surrounding tissues:
Which is visible intraoperatively or on preoperative imaging:
Is associated with a worse prognosis
The implications of minimal ETE on outcomes, however, is less clear:
Some retrospective studies have demonstrated that minimal ETE is associated with higher rates of LN metastases
Other studies found recurrence rates in those with minimal ETE were dependent on primary tumor size
In contrast others have found that minimal ETE is not associated with increased recurrence or decreased survival
A recent systematic review and meta-analysis of the effects of minimal ETE on survival and recurrence demonstrated:
No influence of minimal ETE on disease-related mortality but did indicate an increased risk of recurrence in patients with minimal ETE
The absolute recurrence risk increase for patients with lymph node negative disease was from 2.2% to 3.5% and for patients with lymph node positive disease the increase was from 6.2% to 7%:
Suggesting that the effects of minimal ETE on absolute risk for disease recurrence was small
Indeed, the 8th edition of The American Joint Committee on Cancer/The Tumor, Node, and Metastases (AJCC/TNM) cancer staging system removed the minimal ETE definition and its influence on overall tumor stage
This omission is an acknowledgment of the negligible effects of minimal ETE on tumor-associated mortality
Lymph Node Metastases
The incidence rates of cervical LN metastases identified at the time of initial surgery in patients with PTC varies widely, depending on the mode of nodal detection
Prophylactic LN dissections yield high rates of LN micrometastases (up to 65%)
Whereas gross nodal involvement detected by preoperative US or during surgery occurs in a smaller, but still substantial, percentage (20%) of patients
The manner of discovery is important as it is related to the prognostic significance of nodal involvement:
Those nodes incidentally identified on surgical pathology with microscopic tumor deposits:
Do not significantly alter risk of recurrence
Prophylactic nodal dissection, therefore, is not recommended as it does not lower recurrence-free survival and risks upstaging patients:
Resulting in unnecessary additional treatment
In contrast, grossly abnormal nodes:
Are associated with a worse recurrence-free survival:
Removal of these nodes is thus considered therapeutic
The number of involved nodes:
Is also related to the recurrence risk
Even with microscopic nodal deposits:
More than five involved nodes:
Carries a higher risk of recurrence compared with lower numbers of diseased nodes:
7% to 21% and 3% to 8%
The effects of LN metastases on survival is less clear:
There are conflicting reports regarding cancer-specific mortality in the presence of nodal involvement
An analysis of the Surveillance, Epidemiology, and End Results (SEER) database:
Determined that nodal metastases were associated with increased mortality only in those patients over the age of 45 years:
However, a more recent study of patients from the SEER database and the National Cancer Database (NCDB) of patients under the age of 45 years:
Found that increasing numbers of nodal metastases were associated with decreasing overall survival up to six nodes, after which more metastatic nodes conferred no additional mortality risk
Distant Metastases
Although distant metastases are uncommon in PTC:
They are present in approximately 5% of patients at the time of initial diagnosis:
Another 2.5% to 5% will develop distant metastases after initial therapy
The most common sites of involvement are:
Lung (50%) and bone (25%):
Followed by both lung and bone (20%) and other tumor sites (5%)
One study found a 50% survival rate of 3.5 years:
However, subsets of patients have better survival rates, especially postpubertal children, those with microscopic metastases, and patients with iodine-avid tumors
Additional prognostic information about distant metastases may be gained by performing 2-[18F]fluoro-2-deoxy-D- glucose-positron emission tomography (18FDG-PET) /computed tomography (CT) scanning:
One study found an inverse relationship between survival and degree of 18FDG-PET avidity of the most active lesion as well as the number of (18FDG-PET)–avid lesions
Patients with a positive 18FDG-PET scan had a 7.28-fold increased risk of dying from thyroid cancer compared with patients who had a negative scan
Oncogenes
The MAPK (mitogen-activated protein kinase) pathway:
Is an intracellular signaling cascade that results in:
Cell growth
Proliferation
Apoptosis
A mutation in one of these signaling components in the MAPK pathway is responsible for the majority of PTCs:
These mutations are almost always mutually exclusive:
Suggesting that a single molecular alteration is sufficient to drive oncogenesis
Detection of these mutations may be used to:
Identify malignancy on fine-needle aspiration (FNA)
To prognosticate for patients with thyroid cancer
To guide the systemic agent used in radioiodine-refractory disease
BRAF
BRAF is a serine / threonine kinase in the MAPK signaling pathway:
That regulates cellular differentiation, proliferation, and survival
The independent prognostic utility of a BRAF mutation remains in question, however
With such a high prevalence of this pathogenic variant and the excellent outcomes in the majority of thyroid cancer patients, the specificity of BRAF for prognostication is limited:
Further, because BRAF is often associated with high-risk clinical features, it is difficult to discern what component of the poor outcomes seen with this pathogenic variant are due to the mutation itself, independent of the pathologic elements
Indeed several studies attempting to determine whether BRAF serves as an independent predictor of recurrence have produced mixed results
The identification of a BRAF mutation instead may provide:
Direction for the management of radioiodine refractory tumors:
A recent clinical trial aimed at redifferentiating noniodine-avid tumors:
Used a BRAF-inhibitor, dabrafenib:
60% of patients exhibited new iodine uptake on diagnostic whole-body scans
After treatment with 5GBq of 88I at 3 months of follow-up, two patients had partial responses and four had stable disease
An ongoing trial is examining the effect of dabrafenib alone or in combination with a MEK inhibitor, trametinib:
In progressive, iodine-refractory, BRAF-mutated tumors (clinicaltrials.gov, NCT01723202)
TERT
Newly described in thyroid cancers, telomerase reverse transcriptase (TERT) promoter mutations:
Are found in low frequency in lower risk PTC (9%)
Increasing in frequency in more advanced PTC (51%):
PDTC (40%)
ATC (54% to 73%)
Telomerase is responsible for adding tandem repeats of the TTAAGGG sequence to the end of chromosomes:
To maintain genome stability
Whereas these enzymes are highly expressed in germline and stem cells, expression is reduced or even repressed in somatic cells
The loss of telomeres during somatic cell division:
Results in cells entering senescence
Reactivation of telomerase leads to immortalization:
By way of unrestricted proliferation and inactivation of replicative senescence
Although there are conflicting reports regarding the effect of a TERT mutation on prognosis in PTC:
A recent meta-analysis demonstrated that the presence of coexisting BRAF and TERT mutations was associated with a more aggressive clinical course and another study demonstrated higher mortality rates
Further study is needed to determine the feasibility of pharmacologic therapy targeting TERT mutations
Age at Diagnosis
Age at the time of tumor diagnosis is one of the most important contributing factors to prognosis:
There is a trend of worsening cause-specific survival for each decade starting at age 60 compared with younger patients (less than 20 years old)
An analysis of the NCDB revealed an incremental increase in 10-year mortality:
By 30% to 50% per 5 year increment beginning at age 35 years
A recent study determined that the age-associated increasing risk of mortality was associated with BRAF mutational status:
This multi-institutional study found that age is a strong, continuous, and independent mortality risk factor in patients with a BRAF V600E mutation but not in those with wild-type BRAF
Older patients are also more likely to harbor more aggressive histologic subtypes
In patients with distant metastases:
Those over the age of 40 years are less likely to demonstrate iodine avidity in their lung metastases
Children and adolescents:
Are more likely to have a more advanced tumor stage at the time of diagnosis
Up to 80% harbor nodal involvement and 15% to 20% develop pulmonary metastases rates that are nearly double those seen in adults
Despite the extent of disease at the time of diagnosis, children generally have excellent outcomes
In one systematic review of pediatric patients with pulmonary metastases, a complete response to radioactive iodine (RAI) therapy was seen in up to 50% and disease-specific mortality was 2.7%
Papillary thyroid carcinoma (PTC) is the most common subtype of thyroid cancer, and its genetics have been extensively studied. Here are some key genetic features and alterations associated with papillary thyroid carcinoma:
BRAF V600E mutation:
The BRAF V600E mutation is the most prevalent genetic alteration in PTC, occurring in approximately 40% to 60% of cases. This mutation leads to the activation of the MAPK signaling pathway, which plays a role in cell growth and proliferation. The presence of BRAF V600E mutation may be associated with a higher risk of disease recurrence and more aggressive tumor behavior.
RAS mutations:
RAS mutations, including NRAS and HRAS, are found in approximately 10% to 20% of PTC cases. These mutations also activate the MAPK signaling pathway, promoting cell growth and proliferation. RAS mutations are more common in older patients and are associated with a lower risk of disease recurrence compared to BRAF mutations.
RET/PTC rearrangements:
Rearrangements involving the RET gene, particularly RET/PTC1 and RET/PTC3, are found in a subset of PTC cases. These rearrangements result in the fusion of RET with other genes, leading to the constitutive activation of the RET tyrosine kinase. RET/PTC rearrangements are more commonly seen in radiation-induced PTC and are associated with a favorable prognosis.
Other genetic alterations:
Other less common genetic alterations found in PTC include NTRK rearrangements, EIF1AX mutations, and TERT promoter mutations. These alterations are present in a small proportion of PTC cases and may have implications for prognosis and targeted treatment strategies.
👉Multiple endocrine neoplasia type 2 (MEN2) is subclassified into two distinct syndromes: types 2A (MEN2A) and 2B (MEN2B).
👉Within MEN2A, there are four variants:
● Classical MEN2A
● MEN2A with cutaneous lichen amyloidosis (CLA)
● MEN2A with Hirschsprung disease (HD)
● Familial medullary thyroid cancer (FMTC)
👉In both MEN2A and MEN2B, there is an occurrence of multicentric tumor formation in all organs where the RET proto-oncogene is expressed.
👉The thyroid, parathyroid, adrenal glands, and accessory adrenals are at risk for developing tumors that may reduce life expectancy and quality of life.
Multiple endocrine neoplasia type 2A
Classical MEN2A
👉Classical multiple endocrine neoplasia 2A (MEN2A) is the most common MEN2A variant.
👉It is a heritable predisposition to medullary thyroid cancer (MTC), pheochromocytoma, and primary parathyroid hyperplasia.
👉The respective frequency of these tumors in classical MEN2A is over 90% for MTC, approximately 10% to 50% for pheochromocytoma, and 10% to 20% for multigland parathyroid hyperplasia.
👉The frequency of the development of MTC, pheochromocytoma, and parathyroid hyperplasia depends upon the specific RET mutation.
MEN2A with cutaneous lichen amyloidosis
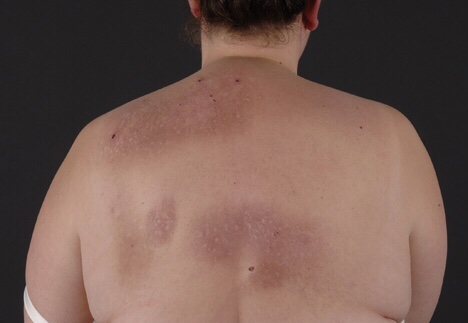
👉CLA (also known as lichen planus amyloidosis [LPA]) has been described in some families with multiple endocrine neoplasia 2A (MEN2A), predominantly those with the RET codon 634 mutation, although it has also been reported in a patient with a codon 804 mutation.
👉The diagnosis of CLA may precede the onset of clinically evident MTC (Image).
👉Patients with this variant develop pheochromocytomas and parathyroid hyperplasia with a similar frequency as those with classical MEN2A.
The skin lesion is usually described as pruritic, scaly, papular, pigmented, and located in the interscapular region or on the extensor surfaces of the extremities. Amyloid deposition has been documented histologically.
MEN2A with Hirschsprung disease (HD)
👉HD is a motor disorder of the gut that is caused by the failure of neural crest cells (precursors of enteric ganglion cells) to migrate completely during intestinal development.
👉The resulting aganglionic segment of the colon fails to relax, causing a functional obstruction.
👉At least eight genetic mutations have been identified in patients with HD.
👉The predominant gene affected is the RET proto-oncogene.
👉RET malfunction accounts for at least 50% of familial and 20% of sporadic cases of HD.
👉In one study, the prevalence of HD in MEN2 was 7.5%.
👉The frequency of HD in MEN2A depends upon the specificRET mutation.
👉The co-occurrence of HD and MEN2A is predominantly associated withRETmutations involving codons 609, 611, 618, and 620.
👉In such patients, HD may be the first presentation of MEN2A.
👉Patients with this variant of MEN2A develop MTC, pheochromocytomas, and parathyroid hyperplasia with a similar frequency as those with classical MEN2A.
Familial medullary thyroid cancer
👉FMTC is a variant of MEN2A in which there is a strong predisposition to MTC but not the other clinical manifestations of MEN2A (or 2B).
👉The clinical distinction of FMTC from MEN2A may be difficult on statistical grounds in small families; even in some large kindreds, the clinical designation of FMTC has been changed to MEN2A after the diagnosis of pheochromocytoma or hyperparathyroidism in a family member.
👉Because FMTC is the most limited variant of MEN2, making the wrong diagnosis of FMTC could result in missing a pheochromocytoma in a patient with MEN2.
👉Therefore, an FMTC kindred should be defined using the following rigorous criteria:
● More than 10 carriers in the kindred
● Multiple carriers or affected members over the age of 50 years
● An adequate medical history, particularly in older family members
👉Why pheochromocytomas and hyperparathyroidism infrequently develop in these families is still unknown since many FMTC and MEN2A families carry identical RET mutations.
👉In rare families, both HD and FMTC appear to segregate.
👉In a report summarizing data from 250 Italian kindreds with hereditary MTC, the prevalence of the FMTC phenotype amongRET mutation carriers was higher than MEN2A and MEN2B (57%, 34% and 6.8%, respectively).
👉This may be related to the introduction ofRETscreening in the work-up of apparently sporadic MTC and the more extensive search forRETmutations in non-hot spot regions of the gene.
Multiple endocrine neoplasia type 2B
👉The frequency of MEN2B has been estimated at roughly 6% of all MEN2 patients.
👉MEN2B shares the inherited predisposition to MTC and pheochromocytoma that occurs in MEN2A.
👉On the other hand, parathyroid hyperplasia is not a feature of this disorder.
👉There are additional important clinical differences.
👉Patients with MEN2B tend to have mucosal neuromas, typically involving the lips and tongue, and intestinal ganglioneuromas.
👉Disturbances of colonic function are common, including chronic constipation and megacolon.
👉Many of these patients have development abnormalities, a Marfanoid habitus, and myelinated corneal nerves.
👉MTC is the most common component of the MEN2B syndrome.
👉Furthermore, the tumor is often more aggressive and of earlier onset than in MEN2A; as a result, early diagnosis and prevention are particularly critical.
What is Head and Neck Surgery?:
It is asurgical sub-specialtythat deals mainly with benign and malignant tumors of the head and neck region, including:
The scalp, facial region, eyes, ears, nose, nasal fossae, paranasal sinuses, oral cavity, pharynx (nasopharynx, oropharynx, hypopharynx), larynx (supraglotic larynx, glottis larynx, subglotic larynx), thyroid gland, parathyroid gland, salivary glands (parotid glands, submandibular glands, sublingual glands, minor salivary glands), soft tissues of the neck, skin of the head and neck region.
Thehead and neck surgeon’s work area:Does not cover tumors or diseases of the brain and other areas of the central nervous system or those of the cervical spine:This is the neurosurgeon field.
Among thediagnostic proceduresperformed by the head and neck surgeon, are the following:
Nasopharyngolaryngoscopy:
Performed toexamine, evaluate and, possibly perform a biopsy, of oral cavity, pharyngeal and laryngeal lesions.
The surgeries most commonly performed by the head and neck surgeon are:
Total or near total thyroidectomies
Hemithryoidectomies (lobectomies)
Comprehensive neck dissections
Selective neck dissections
Maxillectomies:
Total maxillectomy
Subtotal maxillectomy
Infrastructure maxillectomy
Suprastructure maxillectomy
Medial maxillectomy
Mandibulectomy:
Segmental
Marginal
Tracheostomy
Salivary gland surgeries:
Parotid gland operations:
Limited superficial parotidectomy with identification and preservation of the facial nerve
Superficial parotidectomy with identification and preservation of the facial nerve
Near total parotidectomy with identification and preservation of the facial nerve
Total parotidectomy
Submandibular gland resection
Sublingual gland resection
Resection of tumors of the oral cavity:
Glossectomy
Resection of the floor of the mouth tumors
Resection of tumors of the pharynx
Resection of tumors of the larynx
Split-thickness skin grafts
Full-thickness skin grafts
Sentinel lymph node mapping and sentinel lymph node biopsy
Resection of malignant skin tumors (BCC, SCC, melanoma) of the head and neck region
Theformation of the head and neck surgeon includes masteringthe following subjects:
Surgical Anatomy
History and Basic Principles of Head and Neck Surgery
Epidemiology, Etiology, and Pathology of Head and Neck Diseases
Diagnostic Radiology of the Head and Neck Region
Tumors of the Scalp, Skin and Melanoma
Eyelids and Orbit
Nasal Cavity and Paranasal Sinuses
Skull Base and Temporal Bone
Lips and Oral Cavity
Pharynx and Esophagus
Larynx and Trachea
Cervical Lymph Nodes
Thyroid and Parathyroid Glands
Salivary Glands
Neurogenic Tumors and Paragangliomas
Soft Tissue Tumors
Bone Tumors and Odontogenic Lesions
Reconstructive Surgery
Oncologic Dentistry and Maxillofacial Prosthetics
Principles of Radiation Oncology
Principles of Chemotherapy
Molecular Oncology, Genomics and Immunology
Nutrition
Biostatistic
Rodrigo Arrangoiz MS, MD, FACSa head and neck surgeon / endocrine surgeon / surgical oncologist and is a member of Sociedad Quirúrgica S.C at the America British Cowdray Medical Center in Mexico City:
Rodrigo Arrangoiz MS, MD, FACS:
Is a member of theAmerican Head and Neck Society
He is a member of the American Thyroid Association:
Training:
• General surgery:
• Michigan State University:
• 2004 al 2010
• Surgical Oncology / Head and Neck Surgery / Endocrine Surgery:
• Fox Chase Cancer Center (Filadelfia):
• 2010 al 2012
• Masters in Science (Clinical research for health professionals):
• Drexel University (Filadelfia):
• 2010 al 2012
• Surgical Oncology / Head and Neck Surgery / Endocrine Surgery:
• IFHNOS / Memorial Sloan Kettering Cancer Center:
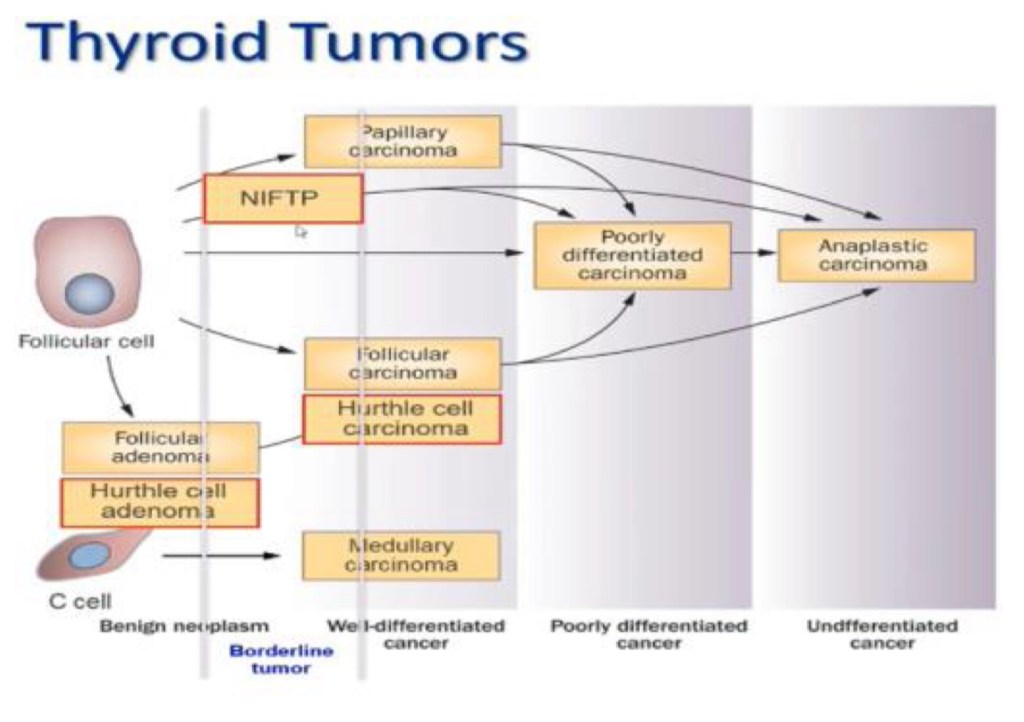
These thyroid tumors comprise the majority, more than 90% of the cases, of all thyroid neoplasms
Of all these subtypes, ATC is the rarest and is characterized by its extremely poor prognosis
Likewise, poorly differentiated carcinoma is characterized by its aggressive behavior and its unfavorable prognosis
Between the year 2010 and 2014:
63,229 patients per year were diagnosed with thyroid cancer:
Of these 89.4% had PTC, 4.6% had FTC, 2.0% had OCC, 1.7% had medullary thyroid carcinoma (MTC), and 0.8% had ATC
A follicular adenoma:
Is a benign tumor (clonal neoplasm):
That may serve as a precursor lesion for some follicular carcinomas
Less-differentiated thyroid cancers, namely poorly differentiated carcinomas, and anaplastic carcinomas:
Can develop de novo:
Although many of them arise through the process of a stepwise dedifferentiation of papillary and follicular carcinomas (Figure)
Thyroid nodules:
Are a major health problem worldwide
Studies have shown that the prevalence of palpable thyroid nodules:
Is roughly 5% in women and 1% in men:
Living in parts of the world with sufficient iodine
In contrast, high-resolution ultrasound:
Can detect thyroid nodules in around 19% to 68% of randomly selected people:
With higher frequencies in women and the elderly
The clinical significance of thyroid nodules lies in the need to exclude thyroid cancer:
Which occurs anywhere between 7% and 15% of the cases:
Depending on age, gender, radiation exposure history, and family history
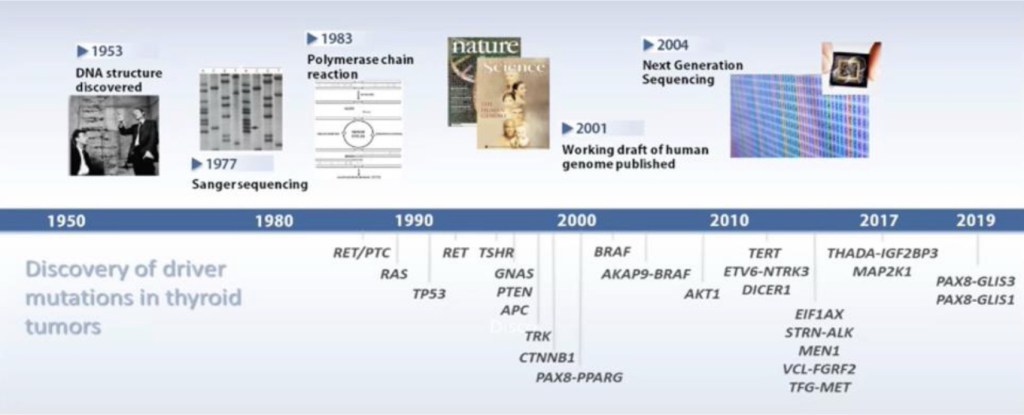
The discovery in 1953 of the double helix structure of deoxyribonucleic acid (DNA), by James Watson and Francis Crick:
Marked a milestone in the history of science and gave rise to modern molecular genetics that has rapidly advanced and has help to identify the driver mutations in in many cancers, including thyroid neoplasms:
The tall cell subtype of papillary thyroid carcinoma (PTC-TC):
Accounts for approximately 3% to 5% of all PTCs
Its incidence has been rising:
Partly due to evolving diagnostic criteria
The WHO 5th edition (2022) defines PTC-TC as:
PTC with ≥ 30% tall cells:
Height-to-width ratio ≥ 3:1
Patients tend to be older:
Mean ~ 50 years vs. 42 for classic PTC
PTC-TC have higher rates of:
Extrathyroidal extension (~ 60%)
Vascular invasion (~ 15%)
Lymph node metastasis
Advanced stage at presentation
Recurrence rates range from:
27% to 42% compared to 16% to 31% for classic PTC
5-year disease-specific survival of:
Approximately 82% vs. 98% for all PTC
An important recent distinction is:
Between PTC-TC (without high-grade features) and high-grade differentiated thyroid carcinoma with tall cell phenotype (HGDTC-TC):
Defined by ≥ 5 mitoses / 2 mm² and / or tumor necrosis
When HGDTC-TC is excluded PTC-TC has a more indolent course (10-year disease-specific survival ~99%)
Genetics and Molecular Features:
BRAF V600E mutation:
Present in ~ 80% to 90% of cases:
Drives MAPK pathway activation and suppresses sodium-iodide symporter expression:
Contributing to RAI refractoriness
TERT promoter mutations:
Independent predictor of recurrence:
More frequent in PTC-TC
BRAF V600E + TERT co-mutation:
Identifies a subset with particularly poor outcomes
Surgical Management:
Type of Thyroidectomy:
Standard indications for total thyroidectomy apply:
Distant metastases
Extrathyroidal extension
Lateral or gross central neck node metastases
Tumor > 4 cm
Bilateral disease
For tumors 1 cm to 4 cm without these features:
Either total thyroidectomy or lobectomy may be considered
Key evidence:
A 2026 SEER analysis of 1,463 PTC-TC patients showed total thyroidectomy had superior cancer-specific survival vs. lobectomy:
5-year CSS 97.8% vs. 90.7%, p = 0.019, independent of RAI
A Memorial Sloan Kettering study of T1 / T2 N0 PTC-TC:
Found no difference in outcomes with lobectomy alone, with 100% disease-specific survival in both groups
Summary:
For small (T1 / T2), node-negative PTC-TC without high-grade features:
Lobectomy may be adequate
Larger or higher-stage tumors:
Should undergo total thyroidectomy
Central Compartment Neck Dissection:
Therapeutic central neck dissection:
Recommended for clinically involved nodes (cN1a)
Prophylactic central neck dissection:
Not routinely indicated per NCCN
Thorough preoperative ultrasound of central and lateral compartments is essential:
With FNA of suspicious lateral nodes
Radioactive Iodine (RAI):
NCCN classifies tall cell histology as a “high-risk subtype”:
For which RAI is selectively recommended based on the combination of clinical factors
PTC-TC is classified in the ATA intermediate risk category
Key considerations:
BRAF V600E-driven PTC-TC downregulates the sodium-iodide symporter:
Making these tumors frequently RAI-refractory
For tumors > 2 cm:
RAI after total thyroidectomy improved overall survival:
83.4% vs. 70.0%
For tumors ≤ 2 cm:
No survival benefit from RAI was demonstrated
A SEER-based propensity-matched study:
Found no significant CSS benefit from RAI in PTC-TC overall:
HR 0.54, 95% CI 0.25–1.17
Repeated RAI should be limited to patients demonstrating continued therapeutic response
Follow-Up:
After total thyroidectomy with RAI, recommended surveillance includes:
Physical examination, TSH, thyroglobulin (Tg), and anti-thyroglobulin antibodies (TgAb)
Neck ultrasound at 6 to 12 months, then every 1 to 3 years for 5 to 8 years, then discontinue
Rising Tg or new TgAb:
Should prompt additional imaging:
Neck CT / MRI, chest / abdomen CT, FDG-PET, or RAI imaging
TSH suppression with levothyroxine:
Per risk stratification
For patients with no evidence of disease (NED) at low risk after 10 to 15 years:
No further thyroid cancer monitoring is indicated
RAI-Refractory Disease:
For RAI-refractory progressive disease:
Molecular analysis for actionable alterations should be pursued:
BRAF V600E → dabrafenib / trametinib or vemurafenib / cobimetinib
RET fusions → selpercatinib or pralsetinib
NTRK fusions → larotrectinib or entrectinib
ALK fusions → targeted therapy
References:
Shi X, Liu R, Basolo F, et al. Differential Clinicopathological Risk and Prognosis of Major Papillary Thyroid Cancer Variants. J Clin Endocrinol Metab. 2016.
Wu SS, Joshi N, Sharrett J, et al. Risk Factors Associated With Recurrence and Death in Patients With Tall Cell Papillary Thyroid Cancer. JAMA Otolaryngol Head Neck Surg. 2023.
Holoubek SA, MacKinney EC, Khokar AM, et al. Radioactive Iodine Does Not Improve Overall Survival for Patients With Aggressive Variants of Papillary Thyroid Carcinoma Less Than 2 Cm. Surgery. 2022.
Jin X, Koga S, Zhou X, Khan NZ, Baloch ZW. Clinicopathologic Characteristics of Papillary Thyroid Carcinoma, Tall Cell Subtype and Subtype With Tall Cell Features, an Institutional Experience. Hum Pathol. 2025.
Parvathareddy SK, Siraj AK, Qadri Z, et al. Tall Cell Variant Histology Predicts Poorer Disease-Free Survival in Papillary Thyroid Carcinoma: A Propensity-Matched Cohort Study. World J Surg. 2025.
Ghossein R, Katabi N, Dogan S, et al. Papillary Thyroid Carcinoma Tall Cell Subtype (PTC-TC)
Develop through a multistep process where they can be identified via cytopathology at different stages in their development
These does not occur in BRAF-like tumors:
Where they develop from the early stages as microcarcinomas
The problem is that in clinical practice we want the tumors to be classified in a binary distribution (benign or malignant):
Which is very difficult because of the multistep process of their development
Noninvasive follicular thyroid neoplasm with papillary nuclear features (NIFTP):
Has partially resolved this problem (NIFTP would be a seen in the later stages of this multistep process)
The diagnostic features of NIFTP include:
Follicular architecture
Nuclear features of PTC
Formation of a capsule with lack of invasion
This entity was previously known as encapsulated follicular variant of papillary carcinoma
The histologic criteria of NIFTP are depicted in Table.
Revised Diagnostic Criteria for NIFTP
NIFTP should be viewed as a borderline malignant tumor (equivalent to carcinoma in situ):
If no invasion is identified on the final pathology:
The risk of recurrence is very low:
Less than 1%
This lesion still requires surgical resection by a minimalistic approach usually is sufficient (thyroid lobectomy)
The molecular characteristics of NIFTP include:
RAS and RAS-like mutations:
BRAF V600E and TERT mutations:
Should not be identified in this lesion
NIFTP is considered a precursor lesion for:
Invasive encapsulated follicular variant of PTC (EFVPTC)
The introduction of NIFTP did not resolve the uncertainty in the pathological diagnosis of PTC:
A study from four different institutions (Memorial Sloan Kettering Cancer Center – MSKCC, Moffit Cancer Center – MCC, Cedar Sinai Medical Center in Los Angeles – CSMC, Mount Sinai Health System in New York – MSHS) with RAS-positive thyroid nodules by Marcardis et al:
Identified a wide variation in the prevalence of NIFTP in resected indeterminate thyroid nodules across several institutions:
Ranging from 5% to 46%
At MSKCC:
The most common overall and non-malignant diagnosis in RAS-mutated nodules was:
NIFTP
This was significantly greater than the NIFTP rate at the other three institutions:
Where the most common overall and benign diagnosis was follicular adenoma / nodular hyperplasia
Significant variations in the rates NIFTP (5% to 13%) and follicular adenoma / nodular hyperplasia (63% to 85%) in the other three institutions (MCC, CSMC, MSHS) also occurred
This reflects the same issue that some thyroid nodules may be identified at stages in their development where the nuclear features of PTC are clearly absent, some at stages where the nuclear features are clearly present, while others can be identified at different stages in the development of the nuclear features of PTC (in some of these stages the nuclear features of PTC are not fully expressed):
Depending on where the pathologist draws the line in this continuum more or less thyroid nodules, will be called cancers or NIFTP, leading to the difficulty in making a diagnosis (Figure)
The image depicts one tumor that has areas of well differentiated thyroid cancer, poorly differentiated thyroid cancer and anaplastic thyroid cancer. The well differentiated tumors preserver all markers differentiation (thyroglobulin, TTF-1, and cytokeratin) compared to the ATC which losses these markers.
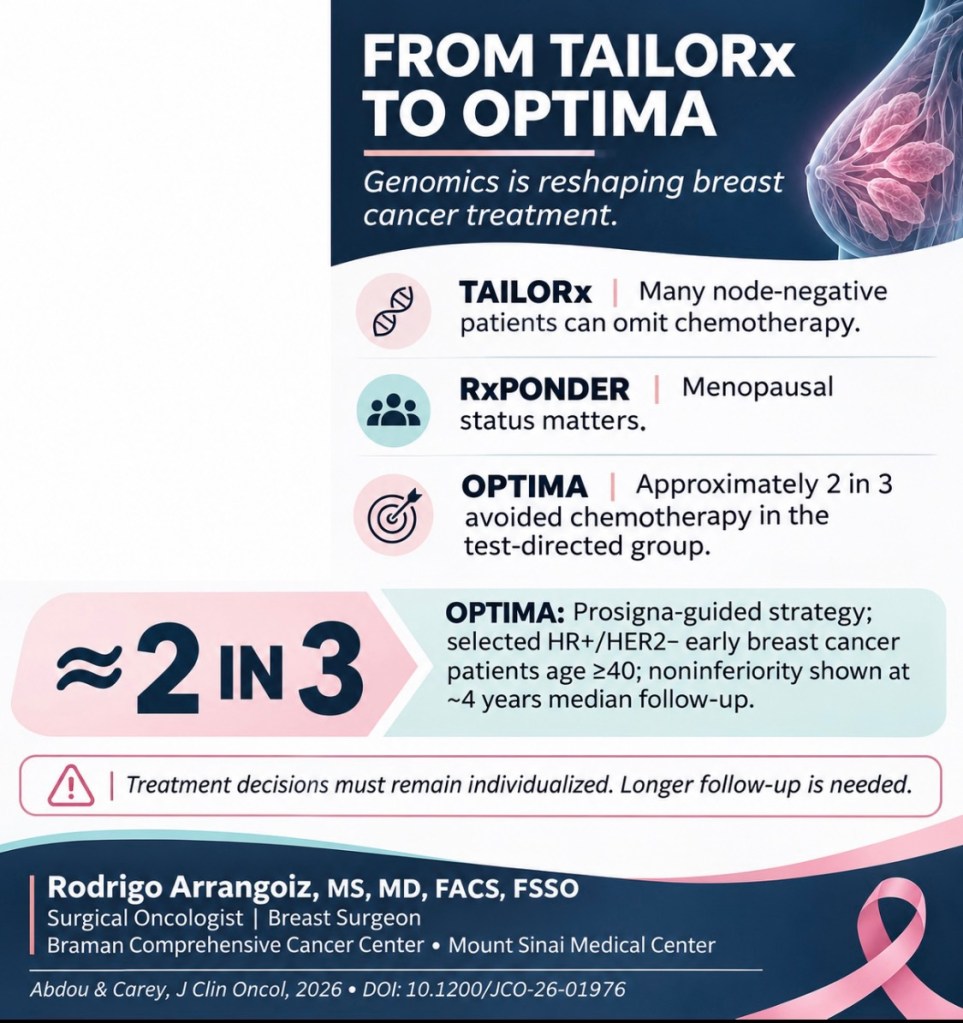
🧬 FROM TAILORx TO OPTIMA: A NEW ERA OF PERSONALIZED BREAST CANCER TREATMENT
Can we safely avoid chemotherapy in more patients with early-stage breast cancer?
An important commentary published on October 30, 2026, in the Journal of Clinical Oncology by Drs. Yara Abdou and Lisa Carey highlights how genomic testing continues to transform treatment decisions for hormone receptor–positive (HR+), HER2-negative breast cancer.
🔬 Four landmark clinical trials have shaped this evolution:
✅ MINDACT: Demonstrated that favorable tumor biology can help identify patients who may safely avoid chemotherapy despite clinically high-risk features.
✅ TAILORx: Established that many women with node-negative disease and intermediate Oncotype DX recurrence scores can safely receive endocrine therapy without chemotherapy.
✅ RxPONDER: Demonstrated that menopausal status matters. Many postmenopausal women with 1–3 positive lymph nodes and low recurrence scores can avoid chemotherapy, while premenopausal women demonstrated additional benefit.
✅ OPTIMA (2026): Extended genomic-guided treatment selection to a higher-risk population, including selected patients with up to nine positive lymph nodes.
Using the Prosigna (PAM50) genomic assay, approximately two-thirds of patients in the test-directed group avoided chemotherapy, with the genomic-guided strategy demonstrating noninferior outcomes compared with standard chemoendocrine therapy at approximately four years of median follow-up.
What does this mean for our patients?
We are moving beyond tumor size and lymph node involvement alone toward treatment decisions based on tumor biology, genomic risk, menopausal status, and individual patient characteristics.
Important questions remain, particularly for younger women, patients with greater nodal involvement, and the long-term durability of chemotherapy omission.
As a surgical oncologist and breast surgeon, I believe these findings reinforce the importance of multidisciplinary, personalized breast cancer care.
The goal is not simply to give less treatment. It is to deliver the right treatment to the right patient—avoiding unnecessary toxicity without compromising cancer outcomes.
📖 Abdou Y, Carey LA. From TAILORx to OPTIMA. Journal of Clinical Oncology. October 30, 2026.