Blog

Treatment of the Primary Site of a Squamous Cell Carcinoma of the Tongue

  • Resection of the tumor:
    • With a 1 cm margin in three dimensions:
      • Should be conducted if surgery is the treatment of choice
  • The use of ultrasonography :
    • To aid in assessment of surgical clearance had been advocated by some:
      • Particularly for the deep margin
  • Frozen section:
    • Can be used (its my practice) but some centers do not routinely used it:
      • Even with apparently adequate margins during surgery:
        • 10% of resections may demonstrate histologically positive margins
  • The aim of reconstruction of the oral tongue following resection:
    • Is to ensure maximum function of the residual tongue tissue:
      • Since the complex function of the tongue cannot be replicated with current reconstructive techniques
    • Preservation of the tip of the tongue:
      • While maintaining oncologically sound resection margins:
        • Helps maximize postoperative function
  • The use of monopolar electrocautery:
    • Cutting through mucosa changing to coagulation when in muscle, or the harmonic scalpel:
      • Helps reduce bleeding during the resection:
        • However this is at the cost of lack of feel afforded by the use of scalpel or scissors
  • If both lingual vessels are resected:
    • Then the viability of the tip of tongue remnant should be carefully assessed:
      • Sacrifice of both hypoglossal nerves results in a nonfunctioning tongue tip
  • Small lesions may be removed with a laser and allowed to heal by secondary intention
  • T1 and small T2 primary tumors:
    • May be excised with a vertical wedge and the defect closed primarily:
      • If the defect does not extend to significantly to include the floor of mouth
    • Many larger lesions benefit from free flap reconstruction of the defect:
      • Usually with a radial free forearm flap:
        • Although the anterolateral thigh free flap is being used more frequently
      • The skin paddle of the chosen free flap:
        • Should be fashioned so as not to restrict residual tongue function and should hopefully augment swallowing
      • Typically, the reconstruction should be of the same size, or slightly smaller than the defect created by the resection
      • Care should be taken in the design of the flap:
        • When the defect extends to include adjacent sites:
          • Such as the soft palate or floor of mouth
      • The mobile tongue and floor of mouth:
        • Should be ‘separated’ in the reconstruction:
          • To minimize restriction of movement of the residual tongue
      • Thin radial free flaps may have their bulk increased by extending fascial flaps beyond the skin island:
        • The fascial flaps then being folded and buried underneath the epithelial reconstruction
    • Reconstruction of large resections:
      • May be accompanied by measures aimed to improve postoperative function:
        • Such as static laryngeal suspension to the mandible and cricopharyngeal myotomy
    • Once the specimen is removed, it is examined for clearance and orientated for the pathologist:
      • A digital photograph being useful
  • Radiotherapy as the primary treatment modality can be used in certain situations:
    • Has been advocated since it conserves tongue volume and morphology:
      • Brachytherapy being considered preferable to external beam radiotherapy:
        • Osteoradionecrosis of the mandible is a recognized complication of brachytherapy of the tongue:
          • Up to 9% developing some form of osseous complication
        • The use of brachytherapy to the primary site:
          • Requires either surgery or external beam radiotherapy to the neck in an elective or therapeutic manner:
          • When surgery is not conducted as the primary treatment:
            • Valuable prognostic information is lost:
              • Since the primary tumor is not examined histologically:
                • This makes the decision as to whether to conduct an END more difficult
          • It has been suggested that surgery is superior to brachytherapy in the management of stage I / II tongue cancer:
            • By conducting surgery as the primary treatment modality, radiotherapy is kept in reserve for either poor prognostic indicators of the resected specimen, for management of recurrence or management of second primaries which commonly occur at a later date
#Arrangoiz #HeadandNeckSurgeon #CancerSurgeon #MountSinaiMedicalCenter #MSMC #SurgicalOncologist

Treatment of Floor of the Mouth Squamous Cell Carcinomas

  • Primary Site:
    • The need for aggressive treatment of floor of mouth carcinomas:
      • Is well recognized
    • Surgical resection with a 1 cm margin should be achieved:
      • If surgery is the preferred treatment modality
    • Even in the best surgeon’s hands:
      • Positive or close margins may be seen in up to 47% of resections:
        • Despite the use of intra-operative frozen section:
          • Many floor of mouth tumors are infiltrative with indistinct edges:
            • Possibly explaining the high incidence of positive margins
        • Further resection is advocated if margins are positive
      • Although 1 cm margins are considered by most surgeons to be adequate:
        • Extended 2 cm margins have been advocated by some
    • The early extension of floor of mouth tumors into the tongue or mandible:
      • Is demonstrated by the fact that many patients require marginal (rim) or segmental resection of the mandible
    • Surgical resection of the floor of mouth in the majority of circumstances:
      • Will involve resection of part of the submandibular ducts:
        • Typically, the ducts will be resected at the resection margin, well away from their orifice:
          • However in smaller resections at least 3 mm length of duct proximal to the orifice:
            • Should be taken to ensure surgical clearance of carcinoma or dysplasia that may extend along the duct
          • Management of the submandibular ducts is of great importance if a neck dissection is not being conducted with consequent removal of the submandibular gland:
            • Stricture of the duct in the presence of a functioning gland:
              • May give rise to obstructive symptoms of the gland and difficulty in differentiating the potential submandibular gland swelling from cervical disease
        • The ducts should be transected obliquely to minimize stricture formation and repositioned at the margin of resection, ideally being stented
        • Alternatively, the ducts may be found proximal to the resection margin:
          • A longitudinal incision made and the duct marsupialized’ to the floor of mouth mucosa:
            • Uninvolved branches of the lingual nerve should be identified and preserved
    • Small resections:
      • May be left to heal by secondary intention or a split thickness skin graft applied
    • A more substantial reconstruction may be achieved using local nasolabial or facial artery musculomucosal flaps:
      • However an edentulous segment is required when using both of these flaps to accommodate their pedicle
    • If a neck dissection is required and surgical facilities allow;
      • Microvascular reconstruction provides a far more flexible reconstructive option, without necessarily prolonging operative time if a two team approach is adopted
Reconstruction with split skin graft
  • The radial free forearm flap is an ideal reconstructive option for floor of mouth defects:
    • Easily being converted to a composite flap if segmental resection of an edentulous mandible is required
  • Prefabricated fasciomucosal free flaps have been described in oral reconstruction:
    • However their role in oncological reconstruction is questioned
  • The fibula osteocutaneous flap provides superior reconstruction if a segmental resection is anticipated in a dentate patient:
    • Although like the composite radial free flap:
      • Flexibility of the skin paddle is limited
  • The scapula osteocutaneous flap:
    • With two skin paddles, or one skin paddle and muscle left to mucosalize:
      • Provides an excellent reconstruction of large defects involving mucosa, bone and external skin
  • Radiotherapy techniques (brachytherapy or external beam):
    • For T1 / T2 primaries have been shown to provide results similar to surgery
    • The proximity of the floor of the mouth to the mandible:
      • Is of concern when using brachytherapy:
        • Since up to 8.5% of patients treated with this modality require segmental resection of the mandible:
          • Due to osteoradionecrosis within 10 years
    • Several units have described a change in practice from brachytherapy to surgery:
      • As the primary treatment modality due to the risk of complications
    • T3 / T4 lesions:
      • Are best treated with surgery and postoperative radiotherapy
  • Management of the Neck in Floor of the Mouth SCC:
    • Regional spread of disease in floor of mouth carcinomas is usually to the ipsilateral level I to III lymph nodes:
      • Involvement of multiple levels not being unusual
    • Lesions towards the midline:
      • May spread to both sides of the neck:
        • Hence bilateral neck dissections should be considered
    • The presence of lingual lymph nodes:
      • Has raised the concept of in-continuity neck dissection in an attempt to reduce local recurrence and improve survival:
        • Resection of the tumor accompanied with the complete clearance of the floor of the mouth, preserving mylohyoid, hyoglossus and genioglossus if possible, so clearing the lingual lymph nodes would seem an acceptable method of managing lingual lymph nodes
    • The decision to conduct an elective neck dissection has been related to tumor size or depth of invasion:
      • Lesions that are T2 or greater:
        • Should have an elective I to III / IV selective neck dissection:
          • Although elective neck dissections have been advocated for T1 lesions
    • Tumor thickness of 4 mm is often used as a ‘generic’ critical thickness, greater than which an elective neck dissection is indicated:
      • Since the risk of occult metastasis is greater than 20%:
        • It has been demonstrated that the risk of cervical metastasis of floor of mouth tumors exceeds 20% in tumors as thin as 1.5 mm to 2 mm:
          • Using a thickness of 1.5 mm may result in up to 32% of patients requiring END based on thickness criteria
  • The indications for postoperative radiotherapy to the loco-regional area are similar to other sites:
    • Notably two or more involved nodes in the neck
    • Extracapsular spread
    • Positive margins
    • Stage III / IV disease
  • Postoperative radiation therapy (PORT):
    • The beneficial role of PORT in selected patients with floor of mouth carcinoma has been demonstrated
  • Recurrence:
    • Recurrence rates for floor of mouth carcinoma are 26% to 55%:
      • Usually within the first two years
    • Factors that influence recurrence include:
      • Tumor size
      • Margin status
      • Tumor thickness
      • Advanced nodal disease
  • Prognosis
    • Overall five-year survival for floor of mouth carcinoma:
      • Is 52% to 76%
    • Factors that potentially influence survival include:
      • Nodal status
      • Thickness
      • Margin status
      • Recurrence
#Arrangoiz #CancerSurgeon #HeadandNeckSurgeon #SurgicalOncologist #Miami #Mexico #MountSianiMedicalCenter #MSMC

Clinical Presentation of Floor of the Mouth Tumors

  • Since the floor of mouth is a relatively small anatomical area:
    • Tumors frequently extend into adjacent sites notably the tongue or mandible
  • Patients may present with a:
    • Sore lesion
    • Ulceration
    • Obstructive submandibular gland symptoms
  • Leukoplakia of the floor of mouth:
    • May be considered a pre-malignant condition with an annual transformation rate of 1% to 2.9%:
      • The demonstration of carcinoma within an excised leukoplakia not being uncommon
  • Stage at presentation varies considerably between institutions:
    • Although approximately 50% present with advanced disease
  • Cervical lymphadenopathy is present in 17% to 45% of patients on presentation:
    • Up to 22% of those clinically N0 at presentation having occult metastasis
    • Depending on the location of the tumor:
      • Up to 28.6% of patients may have bilateral nodal involvement
  • Many tumors of the floor of mouth are well or moderately differentiated
#Arrangoiz #MountSinaiMedicalCenter #CancerSurgeon #SurgicalOncologist #HeadandNeckSurgeon #Miami #Mexico

Floor of the Mount Carcinoma Epidemiology

  • The floor of mouth:
    • Is a common site for oral cancer:
      • 18% to 33 of oral cancers developing at this site
  • It is thought that the high incidence of cancer at this site may be due to pooling of saliva with dissolved carcinogens or lack of keratinized epithelium
  • Within the anatomical site:
    • Tumors are more likely to occur anteriorly
  • Floor of mouth carcinoma:
    • Occurs more frequently in men:
      • The age at diagnosis usually being in the sixth to seventh decade
  • Floor of mouth cancer, as does oral cancer at all sites:
    • Has a strong association with smoking and the consumption of alcohol
#Arrangoiz #HeadandNeckCancer #CancerSurgeon #SurgicalOncologist #HeadandNeckSurgeon #MountSinaiMedicalCenter #MSMC #Miami #Mexico

Floor of the Mount Surgical Anatomy

  • Surgical anatomy:
    • The floor of mouth:
      • Is the mucosal lining of the anterior and lateral floor of the mouth
    • The area is bound anteriorly and laterally:
      • By the attached mucoperiosteum of the mandibular alveolus
    • The lateral floor of mouth is bound posteriorly:
      • By the anterior tonsillar pillars
    • Medially, the floor of mouth:
      • Merges with the ventral and lateral aspects of the tongue
  • The floor of mouth is lined by:
    • Nonkeratinizing stratified squamous epithelium similar to the buccal mucosa:
      • But with a less dense submucosa
    • Underlying the mucosa:
      • Lie minor salivary glands, the sublingual glands, submandibular ducts, hypoglossal nerves, lingual nerves and genioglossus muscles:
        • These structures are located in an area bound by the mylohyoid muscle laterally and hypoglossal muscle medially
    • The submandibular ducts:
      • Enter the mouth anteriorly either side of the lingual frenum
  • Sensory innervation to the area is by the:
    • Lingual branch of the mandibular division of the trigeminal nerve
  • Lymphatic drainage of the lateral floor of the mouth is via:
    • The ipsilateral submandibular nodes to the deep cervical chain
  • Lymphatic drainage of the anterior floor of mouth is via:
    • The submental nodes to both the left and right deep cervical chains
  • Lingual lymph nodes in the floor of mouth:
    • Above the mylohyoid, may have implications regarding the management of tumors of the floor of mouth
#Arrangoiz #CancerSurgeon #HeadandNeckSurgeon #SurgicalOncologist #MountSinaiMedicalCenter #MSMC #Miami #Mexico

Management of High Risk Basal Cell Carcinoma (BCC)

  • Options for high-risk BCC lesions include:
    • Standard excision using wider margins with linear or delayed repair with standard reexcision
    • Mohs Mircrographic surgery (MMS)
    • Resection with complete circumferential peripheral and deep margen assessment (CCPDMA)
    • RT for nonsurgical candidates
    • Patients treated with MMS or resection with CCPDMA should receive adjuvant radiation if clear margins cannot be achieved
  • Recommended adjuvant therapy options include:
    • Radiation and/or multidisciplinary consultation:
      • To consider systemic therapy with a hedgehog pathway inhibitor or involvement in a clinical trial:
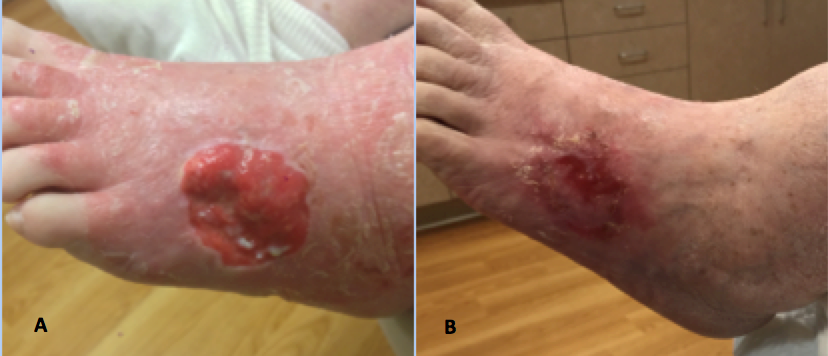
        • In select cases, hedgehog inhibitors can be considered in a neoadjuvant fashion if there is a potential benefit of decreasing the lesion to spare surgical morbidity, as demonstrated here
    • Adjuvant RT is recommended for patients with negative margins after surgery:
      • But with large nerve or extensive perineural involvement
Figure 4
Basal cell carcinoma before (a) and after (b) treatment with the neoadjuvant hedgehog inhibitor

Treatment Of Low Risk Basal Cell Carcinoma (BCC)

  • Primary treatment options for low-risk BCC include:
    • Curettage and electrodesiccation:
      • In areas without hair growth:
        • Provided that the treatment be changed to excision if the adipose is reached
    • Standard excision:
      • With 4 mm clinical margins
    • RT for nonsurgical candidates:
      • If margins are positive after excision:
        • Patients should receive adjuvant therapy
    • Mohs micrographic surgery (MMS)
    • Resection with complete circumferential peripheral and deep margin assessment (CCPDMA) with frozen or permanent section
    • Standard reexcision for area L regions (trunk, extremities):
      • Is recommended:
        • Whereas radiation may be administered to nonsurgical candidates
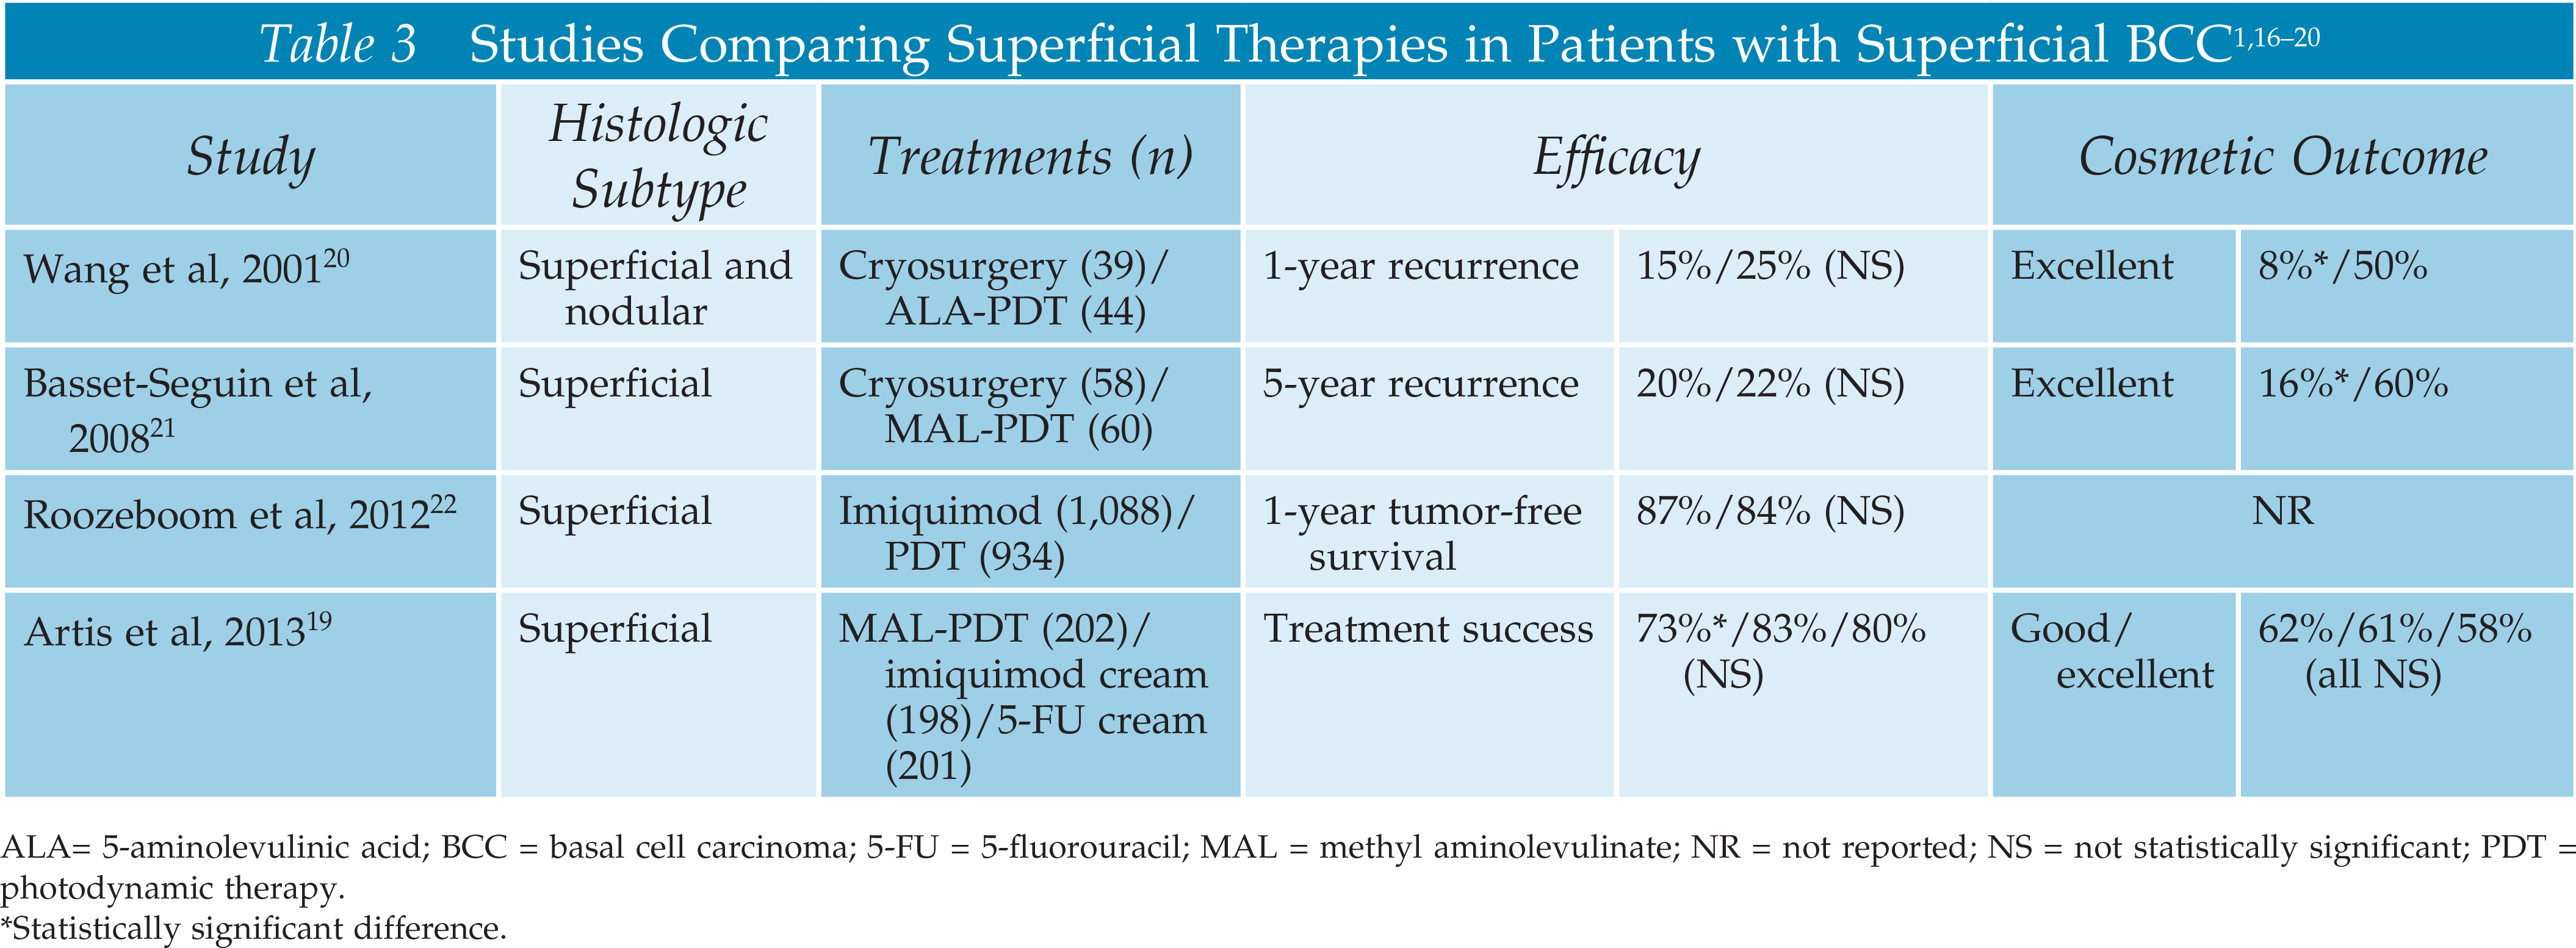
Table 3
  • Several randomized studies and meta-analyses have compared superficial therapies for low-risk BCC, including:
    • Topical therapies such as imiquimod or 5-fluorouracil (5-FU)
    • Photodynamic therapy (PDT) with methyl aminolevulinate (MAL) or 5-aminolevulinic acid (ALA),
    • Cryotherapy
  • 5-FU:
    • Is an antineoplastic antimetabolite
  • Imiquimod:
    • Is a synthetic immune response modifier:
      • That enhances cell-mediated immune response via the induction of proinflammatory cytokines
  • For the treatment of superficial BCC:
    • 5-FU can be applied daily to the tumor and several millimeters of surrounding skin for a period of at least 4 weeks:
      • After a 2- to 3-week interval:
        • The area is then evaluated, often by biopsy, to ensure adequate therapy
  • PDT:
    • Involves the application of a photosensitizing agent on the skin, followed by irradiation with a light source
  • Cryosurgery:
    • Destroys tumor cells by freeze-thaw cycles, but a key limitation is poorer cosmetic outcomes compared with other treatment options
    • Contraindications to cryosurgery for BCC include:
      • Indistinct borders
      • Recurrent tumor
      • Certain tumor location overlying nerves
      • Size greater than 1 cm on the face
      • Certain pathologic features of:
        • Morpheaform, sclerosing, infiltrative, or perineural invasion
      • Patient characteristics, including:
        • Dark skin type
        • Cosmetically sensitive patient
        • Previous poor response to cryotherapy
        • Raynaud phenomenon
    • Imiquimod and 5-FU:
      • Have been found to be effective in treating superficial BCC in randomized studies:
        • The efficacy and cosmetic results of some of these comparison studies are demonstrated in the table
        • One study indicates that PDT has similar efficacy as cryotherapy but better cosmetic outcomes
        • Another study demonstrates that PDT, imiquimod, and 5-FU have similar efficacy and cosmetic outcomes:
          • Although the risk of recurrence may be somewhat higher with PDT versus imiquimod
        • The National Comprehensive Cancer Network panel agrees that these superficial therapies:
          • May be effective for anatomically challenging locations where surgery or radiation is contraindicated or impractical:
            • But the cure rates of these approaches are lower compared with surgery
#Arrangoiz #CancerSurgeon #SurgicalOncologist #HeadandNeckSurgeon #MountSinaiMedicalCenter #MSMC #Miami #Mexico
  • SENTINA Trial:
    • Was a 4-arm, prospective, multicenter cohort study:
      • Of 1,737 patients:
        • That evaluated the role of sentinel lymph node biopsy (SLNB) in patients who had undergone neoadjuvant chemotherapy (NAC) for invasive breast cancer
      • Clinical node status:
        • Was determined by palpation and ultrasound in all patients
      • Ultrasound guided fine-needle aspiration or core biopsy:
        • Was recommended but not mandatory
      • Patients with clinically node-negative (cN-) disease:
        • Underwent SLNB before NAC (Arm A)
      • If the sentinel node (SN) was positive:
        • A second SLNB and axillary lymph node dissection (ALND) was performed after NAC (Arm B)
      • Women who were clinically node positive (cN+) underwent NAC, and those who converted to being cN- also had SLNB and axillary lymph node dissection (Arm C)
      • Only patients whose clinical nodal status remained positive (ycN1) underwent axillary dissection without sentinel lymph node biopsy (arm D)
  • When SLNB was done before NAC:
    • No difference in the detection rate was found between the combined (radiocolloid and blue dye) and single agent (radiocolloid alone) detection techniques:
      • 99.5% vs. 98.8%
  • However, when SLNB was done after NAC:
    • The addition of blue dye increased the detection rate and the number of nodes retrieved
    • Dual tracer detection rate was:
      • 76% after chemotherapy in patients who also had SLNB prior to chemotherapy and 88% in those who converted from cN+ to cN- with NAC and had only one SLNB
  • For patients who were confirmed node positive by SLNB biopsy prior to NAC:
    • The FNR of repeat SLNB after NAC was 51.6%
  • For patients who converted from cN+ to cN- with NAC:
    • FNR of SLNB after NAC was 14.2%:
      • However, in the cN+ to cN- group:
        • The FNR was below 10%, for patients who had 3 or more lymph nodes removed and if both blue dye and radiocolloid were used
          • In these cases, the FNR was 8.6%
  • References
    • Kuehn T, Bauerfeind I, Fehm T, Fleige B, Hausschild M, Helms G, et al. Sentinel-lymph-node biopsy in patients with breast cancer before and after neoadjuvant chemotherapy (SENTINA): a prospective, multicentre cohort study. Lancet Oncol.2013;14(7):609-618.
    • Schwentner L, Helms G, Nekljudova V, Ataseven B, Bauerfeind I, Ditsch N, et al. Using ultrasound and palpation for predicting axillary lymph node status following neoadjuvant chemotherapy – Results from the multi-center SENTINA trial. Breast. 2017;31:202-207.
#Arrangoiz #CancerSurgeon #BreastSurgeon #MSMC #MountSiniaMedicalCenter #Miami #Mexico

NSABP B-27 Trial

  • In the NSABP B-27 trial:
    • 2,411 women with operable breast cancer were randomly assigned to receive:
      • Preoperative AC followed by surgery
      • Preoperative AC followed by docetaxel then surgery
      • AC followed by surgery and then docetaxel
        • Tamoxifen was initiated concurrently with chemotherapy
    • The addition of docetaxel, preoperatively or postoperatively:
      • Did not significantly improve OS or DFS
    • The sample size of the study:
      • Was deemed insufficient to yield significance for the moderate improved DFS:
        • However, in the subset of patients with a clinical partial response to AC:
          • The addition of preoperative docetaxel (but not postoperative docetaxel):
            • Resulted in a significant increase in DFS compared with AC alone:
              • Hazard ratio, 0.71; 95% confidence interval, 0.55–0.91; P=.007
    • There was a significant decrease in the cumulative incidence of all local recurrence as first events:
      • In the two groups treated with docetaxel:
        • Approximately half of which was accounted for by ipsilateral breast tumor recurrences in women treated with breast-conserving therapy

References

1. Bear HD, Anderson S, Smith RE, Geyer Jr CE, Mamounas EP, Fisher B, et al. Sequential preoperative or postoperative docetaxel added to preoperative doxorubicin plus cyclophosphamide for operable breast cancer: National Surgical Adjuvant Breast and Bowel Project Protocol B-27. J Clin Oncol. 2006;24(13):2019-2027.

2. NSABP clinical trials overview. Protocol B-27. A randomized trial comparing preoperative doxorubicin (adriamycin) cyclophosphamide (AC) to preoperative AC followed by preoperative docetaxel (taxotere) and to preoperative ac followed by postoperative docetaxel in patients with operable carcinoma of the breast. National Surgical Adjuvant Breast and Bowel Project website. http://www.nsabp.pitt.edu/B-27.asp. Accessed May 15, 2020.

#Arrangoiz #CancerSurgeon #BreastSurgeon #SurgicalOncologist #BreastCancer #MountSinaiMedicalCenter #MSMC Miami #Mexico

NSABP B-51 / RTOG 1304 Trial

  • The NSABP B-51 / RTOG 1304 trial:
    • Is a phase 3 randomized clinical trial currently accruing patients:
      • The trial is designed to evaluate the role of regional nodal radiotherapy (RT) in patients who had documented positive axillary lymph nodes prior to undergoing NAC who subsequently convert to pathologically negative axillary nodes after the administration of NAC
    • The primary endpoint:
      • Is to determine if regional nodal RT significantly reduces the rate of in-breast cancer recurrence free interval
    • Node positivity:
      • Will be documented by either FNA or core needle biopsy prior to the administration of NAC
    • Patients will undergo standard NAC with the addition of anti-HER2 therapy for patients with HER2-positive tumors
    • Patients can have either mastectomy or breast-conserving therapy:
      • Mastectomy patients will be randomized to either no RT or regional nodal RT and chest wall RT
      • Breast conservation patients will be randomized to either whole-breast RT or whole-breast RT plus regional nodal RT
  • A companion trial is being undertaken by The Alliance for Clinical Trials in Oncology:
    • The A11202 trial is enrolling patients that were axillary node positive prior to NAC, have a normal axilla on physical exam after NAC, but have microscopic disease on sentinel lymph node biopsy:
      • This trial randomizes patients to completion axillary node dissection or sentinel lymph node biopsy only in addition to radiation therapy for both arms

References

1. NSABP clinical trials overview. Protocol B-27. A randomized trial comparing preoperative doxorubicin (adriamycin) cyclophosphamide (ac) to preoperative ac followed by preoperative docetaxel (taxotere) and to preoperative ac followed by postoperative docetaxel in patients with operable carcinoma of the breast. National Surgical Adjuvant Breast and Bowel Project website. http://www.nsabp.pitt.edu/b-51.asp. Accessed May 15, 2020.

2. NRG-alias protocol information. https://www.nrgoncology.org/Clinical-Trials/Protocol/nsabp-b-51-rtog-1304?filter=nsabp-b-51-rtog-1304. Accessed September 11, 2020.

3. Comparison of axillary lymph node dissection with axillary radiation for patients with node-positive breast cancer treated with chemotherapy. NIH ClinicalTrials.gov website. https://clinicaltrials.gov/ct2/show/NCT01901094. Accessed May 15, 2020.

#Arrangoiz #CancerSurgeon #SurgicalOncology #BreastSurgeon #BreastCancer #Miami #Mexico #MountSinaiMedicalCenter #MSMC