Blog

  • To investigate the risk of ipsilateral breast events (IBEs):
    • In patients with DCIS treated with local excision without radiation:
      • The Eastern Cooperative Oncology Group (ECOG) and North Central Cancer Treatment Group:
        • Conducted a prospective trial between 1997 and 2002 known as the E5194 study:
          • Patients were stratified into two groups based on grade:
            • Low- and intermediate-grade DCIS measuring 2.5 cm or smaller, and high-grade DCIS measuring 1 cm or smaller
            • Margin widths of 3 mm or wider were required along with no residual calcifications on postoperative mammograms
          • The low- and intermediate-grade DCIS group:
            • Had a 12-year IBE rate of 14.4%
          • The high-grade group:
            • Had a 12-year IBE rate of 24.6% (p=0.003)
          • Larger tumor size was also found to be statistically significantly associated with developing an IBE (P = .01)
          • The risks of developing an IBE for either DCIS or invasive cancer:
            • Increased over time through 12 years of follow-up, without plateau
  • Current literature reports a 50% decrease in local recurrence with radiotherapy after surgical excision of DCIS:
    • However, we continue to look for low risk subsets of patients with DCIS in whom the absolute benefit of radiation therapy of lumpectomy may be small
  • The DCIS score (12-gene signature) was developed from tissue samples from the E5194 study:
    • With the goal of identifying low and high-risk subsets of patients with DCIS following lumpectomy alone
    • This assay utilized quantitative reverse transcriptase-polymerase chain reaction (RT-PCR) from tumor specimens from 327 patients with DCIS treated with surgical excision without radiation from the E5194 study:
      • The DCIS score of 0 to 100 (low less than 39, intermediate 39 to 54, high ≥ 55) was then designed to predict the recurrence of IBE overall, as well as DCIS or invasive cancer recurrence:
        • The DCIS score correlated with 10-year IBE risk of:
          • 10.6% in the low-risk group
          • 26.7% in the intermediate-risk group
          • 25.9% in the high-risk group
        • Young age and larger tumor size:
          • Also were found to be independent predictors of recurrence:
            • So, this test may be most beneficial in postmenopausal women with small tumors

References

1. Solin LJ, Gray R, Hughes LL, Wood WC, Lowen MA, Badve SS, et al. Surgical excision without radiation for ductal carcinoma in situ of the breast: 12-year results from the ECOG-ACRIN E5194 Study. J Clin Oncol. 2015;33(33):3938-3944.

2. Solin LJ, Gray R, Baehner FL, Butler SM, Hughes LL, Yoshizawa C, et al. A multigene expression assay to predict local recurrence risk for ductal carcinoma in situ of the breast. J Natl Cancer Inst. 2013;105(10):701-710.

#Arrangoiz #BreastSurgeon #CancerSurgeon #SurgicalOncologist #MountSinaiMedicalCenter #MSMC #Miami #Mexico #BreastCancer #DCIS

Excision Lesions on the Nose and Reconstruction of Surgical Defects Part 1

  • The basic principles of reconstruction of cutaneous defects on the nose:
    • Require a thorough understanding of the anatomy of the nasal aesthetic subunits:
      • To facilitate appropriate excision and reconstruction
  • The cutaneous surface of the nose:
    • Is divided into several aesthetic subunits, shown in Figure:
      • The most cephalad part of the nose:
        • Also called the root of the nose:
          • Encompasses a subunit extending from the medial aspect of the eyebrow from one side to the other
      • The middle third of the nose is divided into:
        • The dorsum and lateral walls
      • The lower third of the nose is divided into:
        • The tip of the nose, the alar subunit, and the columella
  • Excision of any lesion involving any part of the cutaneous surface of the nose:
    • Therefore should include consideration of these subunits:
      • In planning not only the excision but also repair or reconstruction:
        • If the nasal aesthetic subunits are not considered in treatment planning:
          • The aesthetic result is not optimal
Aesthetic Subunits of the Nose
#Arrangoiz #SurgicalOncologist #CancerSurgeon #HeadandNeckSurgeon #ThyroidSurgeon #ParathyroidSurgeon #AestheticUnitsoftheNose #SkinCancer #MountSinaiMedicalCenter #MSMC #Miami Mexico

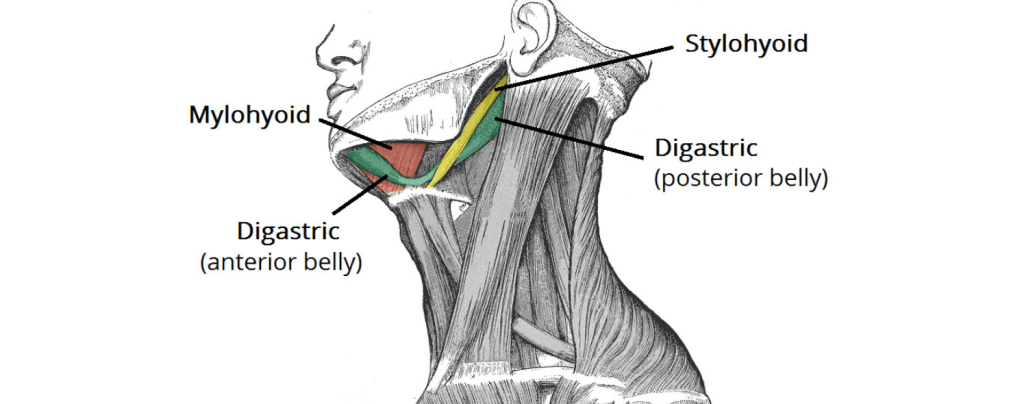
Suprahyoid Muscles

  • The suprahyoid muscles are a group of four muscles:
    • Located superior to the hyoid bone of the neck
  • They all act to elevate the hyoid bone:
    • An action involved in swallowing
  • The arterial supply to these muscles:
    • Is via branches of the facial artery, occipital artery, and lingual artery
  • Stylohyoid muscle:
    • Is a thin muscular strip:
      • Which is located superiorly to the posterior belly of the digastric muscle
    • Attachments: 
      • Arises from the styloid process of the temporal bone
      • Attaches to the lateral aspect of the hyoid bone
    • Actions:
      • Initiates a swallowing action:
        • By pulling the hyoid bone in a posterior and superior direction
    • Innervation:
      • Stylohyoid branch of the facial nerve (CN VII)
        • This arises proximally to the parotid gland
  • The digastric muscle:
    • Is comprised of two muscular bellies:
      • Which are connected by a tendon:
        • In some cadaveric specimens, this tendon can be seen to pierce the stylohyoid muscle
    • Attachments: 
      • The anterior belly arises from the digastric fossa of the mandible
      • The posterior belly arises from the mastoid process of the temporal bone
    • The two bellies are connected by an intermediate tendon:
      • Which is attached to the hyoid bone via a fibrous sling
    • Actions:
      • Depresses the mandible and elevates the hyoid bone
    • Innervation:
      • The anterior belly is innervated by the inferior alveolar nerve:
        • A branch of the mandibular nerve:
          • Which is derived from the trigeminal nerve, CN V
      • The posterior belly:
        • Is innervated by the digastric branch of the facial nerve
  • Mylohyoid muscle:
    • Is a broad, triangular shaped muscle
    • It forms the floor of the oral cavity and supports the floor of the mouth
    • Attachments:
      • Originates from the mylohyoid line of the mandible
      • Attaches onto the hyoid bone
    • Actions:
      • Elevates the hyoid bone and the floor of the mouth
    • Innervation:
      • Inferior alveolar nerve:
        • A branch of the mandibular nerve:
          • Which is derived from the trigeminal nerve
  • Geniohyoid muscle:
    • Is located either side of the midline of the neck:
      • Deep to the mylohyoid muscle
    • Attachments:
      • Arises from the inferior mental spine of the mandible
      • It then travels inferiorly and posteriorly to attach to the hyoid bone
    • Actions:
      • Depresses the mandible and elevates the hyoid bone
    • Innervation:
      • C1 nerve roots that run within the hypoglossal nerve
#Arrangoiz #HeadandNeckSurgeon #CancerSurgeon #ThyroidSurgeon #ParathyroidSurgeon #MountSinaiMedicalCenter #MSMC #Miami #Mexico

Posterior Belly of the Diagastric Muscle

  • The posterior belly, longer than the anterior belly, arises from the mastoid notch which is on the inferior surface of the skull, medial to the mastoid process of the temporal bone. It lies posterior to the parotid gland and the facial nerve. The mastoid notch is a deep groove between the mastoid process and the styloid process. The mastoid notch is also referred to as the digastric groove or the digastric fossa.
  • The posterior belly is supplied by the digastric branch of facial nerve.
  • The digastric muscle stretches between the mastoid process of the cranium to the mandible at the chin, and part-way between, it becomes a tendon which passes through a tendinous pulley attached to the hyoid bone. It originates from the second pharyngeal arch
  • “The resident’s friend”: Few qualms are as useful as the posterior belly of the digastric muscle.

It helps us to recognize…

  • Nerves: its cranial border is related to the facial nerve (VII PC), its caudal border to the spinal nerve or accessory (XI PC). 
  • Vessels: on its ventral face rests the facial vein (posterior) or the retromandibular vein, on its dorsal face the facial artery.

They constitute, together with the omohyoid muscle (also morphologically digastric), the “protectors” of the internal jugular vein. Both muscles stand in the way of the surgeon’s scalpel to the junction of the vascular axis of the neck (the posterior belly does so at level IIa, the intermediate tendon of the omohyoid at the boundary between III-IV).

Precancerous Oral Lesions

  • Diagnosis of precancerous lesions or early cancer can be difficult]
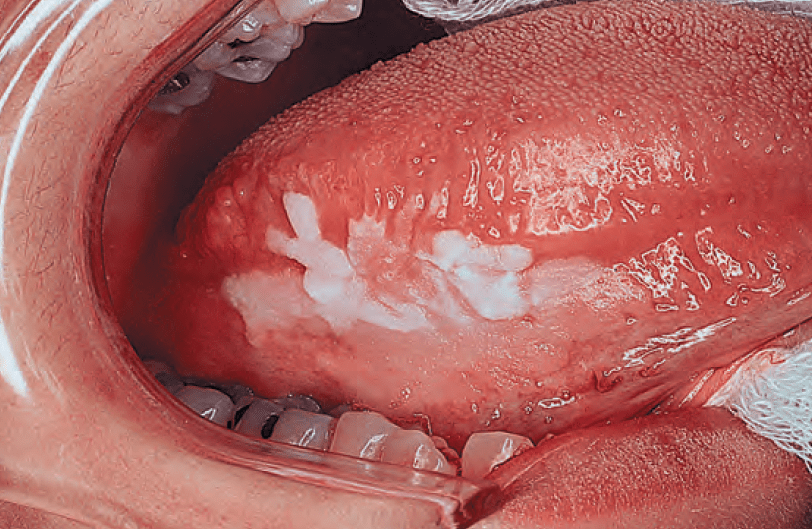
  • Leukoplakia and erythroplakia:
    • Are precancerous lesions that have a varying risk of progression to malignancy
    • Conversion from leukoplakia to carcinoma:
      • Is reported in up to 5% to 7% of patients observed over several years
    • Leukoplakia develops as a result of:
      • Chronic irritation of the mucous membranes by carcinogens:
        • This irritation stimulates proliferation of epithelial and connective tissue
      • Histopathologic examination reveals:
        • Underlying hyperkeratosis associated with epithelial hyperplasia
    • In the absence of underlying dysplasia:
      • Leukoplakia rarely (less than 5 % to 7%) is associated with progression to malignancy
    • Keratoses of a variety of degrees:
      • Manifest as leukoplakia
Leukoplakia (hyperkeratosis) of the oral tongue
Discoid leukoplakia with hyperkeratosis of the undersurface
of the tongue
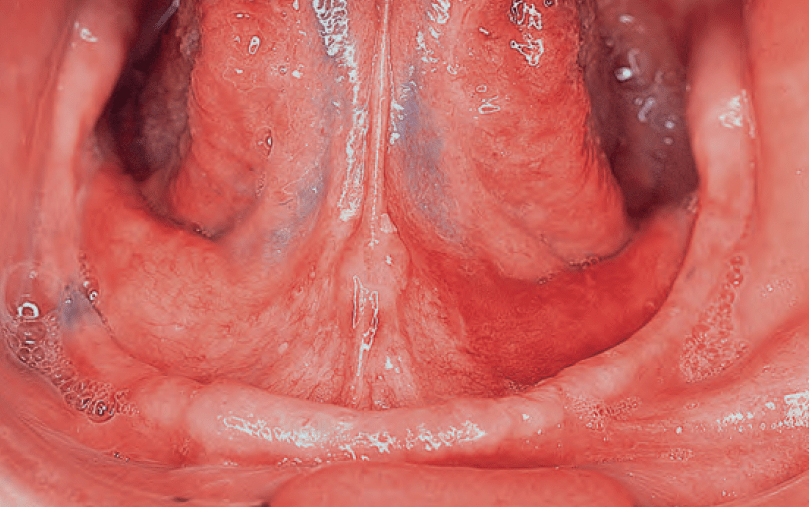
  • Red spots, friable adjacent normal mucosa, characterize erythroplakia:
    • It is associated with underlying epithelial dysplasia:
      • Has a much greater potential for malignancy than leukoplakia:
        • Carcinoma is found in nearly 30% to 40 % of cases of erythroplakia
    • Erythroplakia usually manifests as a pinkish, velvety flat
Erythroplakia of the left floor of the mouth
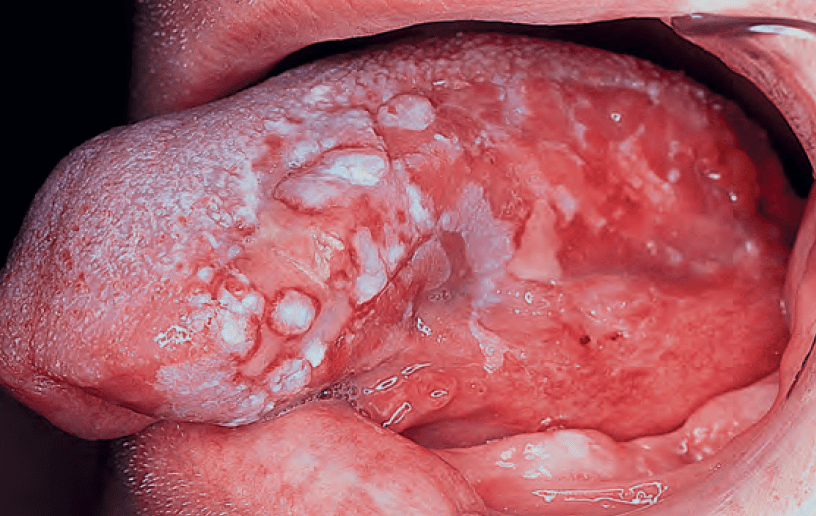
  • Speckled leukoplakia:
    • Has a particularly high incidence of malignant transformation:
      • Similar to erythroplakia
Speckled leukoplakia of the oral tongue

#Arrangoiz #CancerSurgeon #HeadandNeckSurgeon #SurgicalOncologist #ThyroidSurgeon #ParathyroidSurgeon #MountSinaiMedicalCenter #MSMC #Miami #Mexico

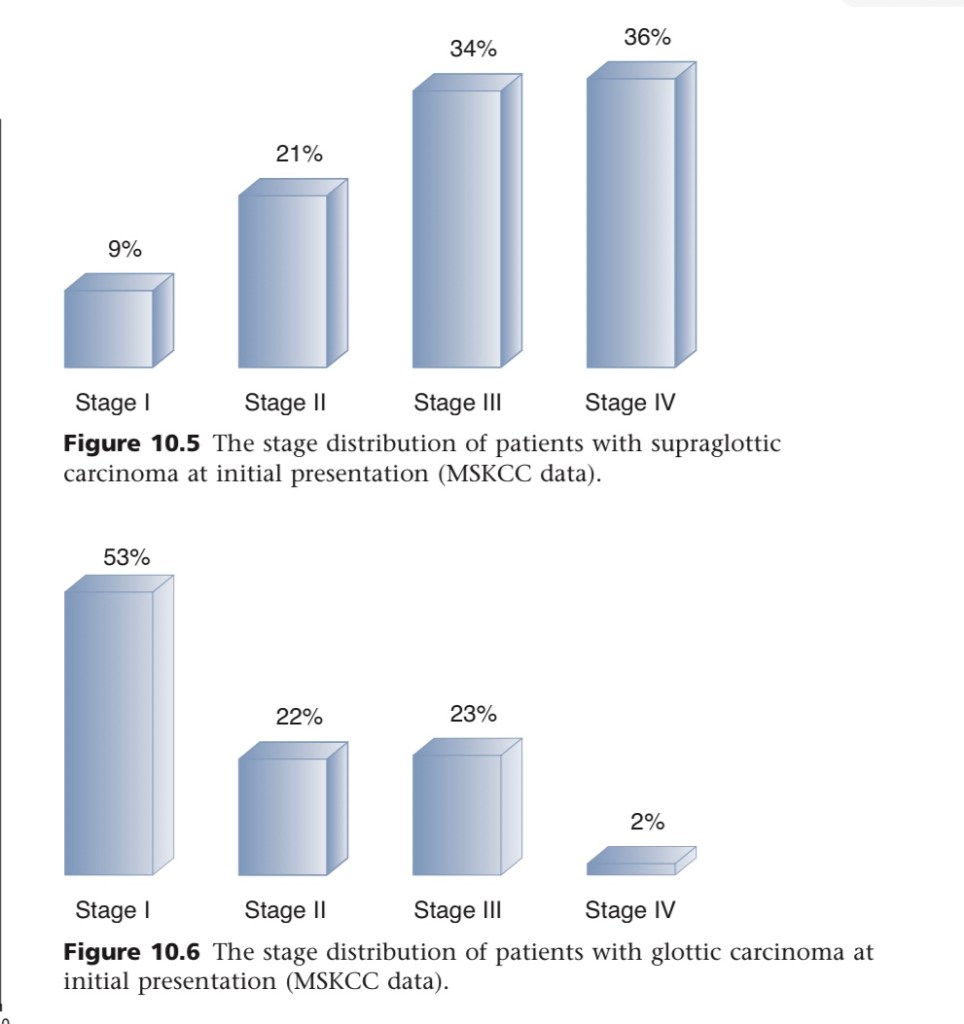
Stage distribution of patients with supraglottic carcinoma and glottic carcinoma

  • The glottic region is by far the most common site for primary malignant tumors in the larynx.
  • The stage distribution of patients with supraglottic carcinoma and glottic carcinoma at the time of presentation at Memorial Sloan Kettering Cancer Center is shown in the figures.
  • 75% of patients with glottic carcinoma have localized disease at the time of diagnosis, in contrast to nearly 70% of patients with supraglottic carcinoma who have advanced disease at presentation.

Tongue Anatomy

  • Musculature of the Tongue:

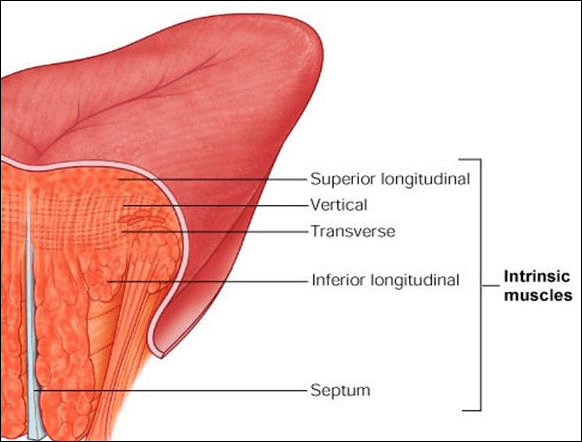
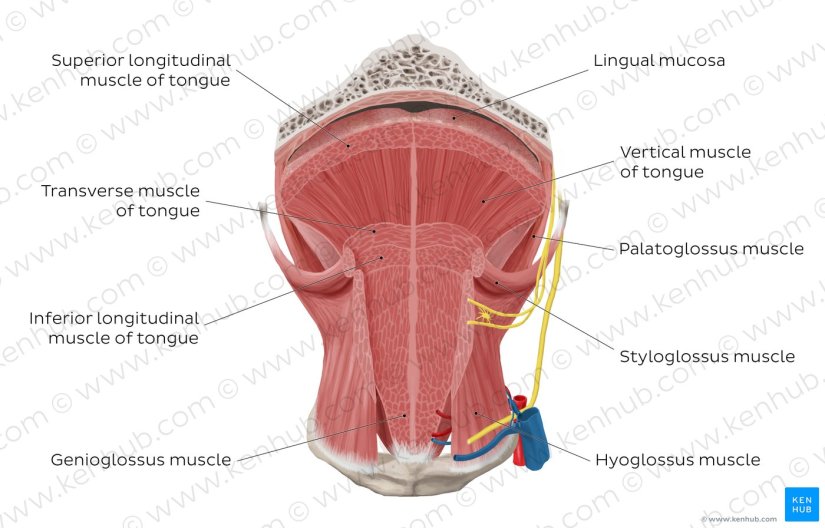
    • The intrinsic muscles (bilateral superior and inferior longitudinal, transverse, and vertical muscles) interdigitate and have no tissue spaces, which allows invasive cancers to spread easily.

ce507-fig04-intrinsic-tongue-muscles

H8rDTg2yQrkuDKTAMNqhg_the-muscles-of-the-tongue_english

  • On the other hand, infiltration of the extrinsic muscles of the tongue (genioglossus, hyoglossus, styloglossus, and palatoglossus) is a feature of locally advanced cancer.

extrinsic

  • The arterial supply to the tongue and floor of the mouth is from the:.

    • Dorsal lingual, sublingual, and deep lingual branches of the lingual artery.

  • The venous drainage of the tongue is into the lingual veins:

    • Which drain into the facial and retromandibular veins:

      • Which join to form the common facial vein.

    • Vasculature Tongue:

      • Similar to most of the head and neck region, the tongue derives its arterial blood supply from the external carotid artery.

      • The lingual artery branches off the external carotid artery deep to the stylohyoid muscle:

        • At first, it travels superomedially; after a short distance, it changes direction and moves anteroinferiorly.

        • The hypoglossal nerve (cranial nerve XII) crosses over it laterally before it enters the tongue deep in the hyoglossus muscle.

      • Within the tongue, the lingual artery gives rise to its three main branches:

        • The dorsal lingual artery:

          • The dorsal lingual artery supplies the base of the tongue

        • The deep lingual artery:

          • The deep lingual artery travels on the lower surface of the tongue to the tip.

        • The sublingual artery:

          • A branch to the sublingual gland and the floor of the mouth is known as the sublingual artery.

Blood-supply-of-tongue

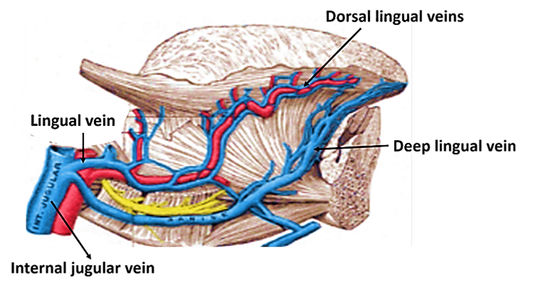
  • The veins of the tongue parallel the lingual artery branches:

    • The deep lingual vein begins at the tip of the tongue and travels posteriorly to join the sublingual vein:

      • This veins drains into the dorsal lingual vein, which accompanies the lingual artery.

    • The dorsal lingual vein drains into the lingual veins:

      • Which drain into the facial and retromandibular veins, which join to form the common facial vein:

        • Directly or indirectly, this vein empties into the internal jugular vein.

veins-of-tongue

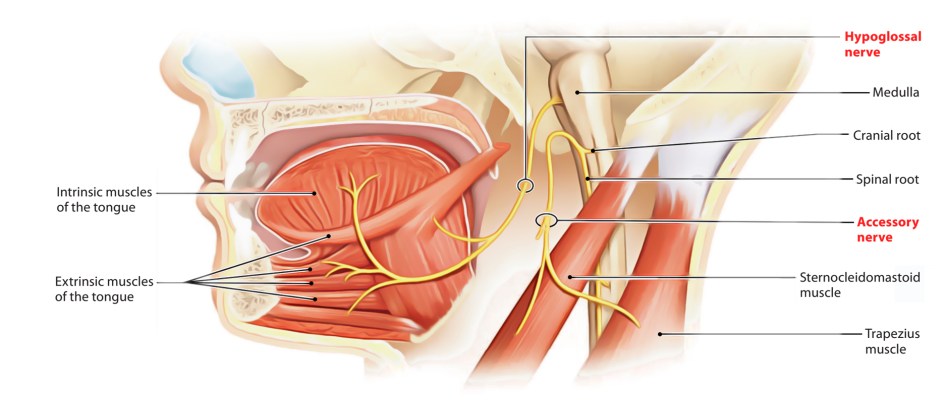
  • The hypoglossal nerve provides motor innervations to all muscles of the tongue except the palatoglossus:

    • Which is supplied by the pharyngeal plexus.

  • The lingual nerve is the sensory nerve to the anterior two thirds of the tongue, the floor of the mouth, and the lower gum, while taste sensation is carried along the chorda tympani branch of the facial nerve.

Hypoglossal-and-accessory-nerve-1

Rodrigo Arrangoiz MS, MD, FACS a head and neck surgeon and is a member of Mount Sinai Medical Center.

prof_739_20190417135234

He is first author on some publications on oral cavity cancer:

Training:

• General surgery:

• Michigan State University:

• 2004 al 2010

• Surgical Oncology / Head and Neck Surgery / Endocrine Surgery:

• Fox Chase Cancer Center (Filadelfia):

• 2010 al 2012

• Masters in Science (Clinical research for health professionals):

• Drexel University (Filadelfia):

• 2010 al 2012

• Surgical Oncology / Head and Neck Surgery / Endocrine Surgery:

• IFHNOS / Memorial Sloan Kettering Cancer Center:

• 2014 al 2016

image-42


#Arrangoiz

#Teacher

#Surgeon

#Cirujano

#ThyroidExpert

#ThyroidSurgeon

#CirujanodeTiroides

#ExpertoenTiroides

#ExpertoenParatiroides

#Paratiroides

#Hiperparatiroidismo

#CancerdeTiroides

#ThyroidCancer

#PapillaryThyroidCancer

#SurgicalOncologist

#CirujanoOncologo

Gra#CancerSurgeon

#CirujanodeCancer

#HeadandNeckSurgeon

#CirugiaEndocrina

#CirujanodeTumoresdeCabezayCuello

#OralCavityCancer

#Melanoma

 #MountSinaiMedicalCenter


Clinicopathologic Staging of Patients with Thyroid Cancer

  • Clinicopathologic staging of patients with thyroid cancer is valuable for many reasons, including the following:
    • To estimate risk of recurrence and disease-specific mortality for an individual patient
    • To tailor decisions regarding postoperative adjunctive therapy to the patient’s risk for disease recurrence and mortality:
      • Such as the need for radioiodine [RAI] ablation and degree of thyroid-stimulating hormone [TSH] suppression:
    • To make decisions regarding the frequency, modality, and intensity of follow-up:
      • Based upon an individual patient’s risk of recurrence and mortality
    • To enable accurate communication regarding a patient among health care professionals
    • To allow evaluation of differing therapeutic strategies applied to comparable groups of patients in clinical studies
    • To provide a method of conveying clinical experience to others without ambiguity
#Arrangoiz #HeadandNeckSurgeon #ThyroidSurgeon #ParathyroidSurgeon #CancerSurgeon #HeadandNeckCancer #ThyroidCancer #Miami #Mexico #MountSinaiMedicalCenter #MSMC #HeadandNeckAwarenessMonths

Parotid Surgery Complications

  • Knowledge of anatomy allows us to infer probable complications of parotidectomies.
  • Facial nerve motor weakness is a complication inherent to the extent of the operation, the extent of the tumor and technique used (less common in extracapsular dissections and partial parotidectomies, more common in superficial, deep-lobe or total parotidectomies).
  • The rates of transient injury in the literature are highly variable and there are large biases.
  • The lack of sensation or pre auricular and auricular paraesthesia will depend on the preservation of the posterior branch of the greater auricular nerve (at 24 months: 31% vs. 71%, with and without preservation respectively).
  • Frey’s syndrome (also called “gustatory sweating” syndrome) and First Bite Syndrome are more common in parotidectomies that include the deep lobe of the gland.
  • Frey’s has been linked to disruption of the secretagogue [parasympathetic] innervation of the gland (mediated through the auriculotemporal nerve).
  • The First Bite Syndrome occurs more frequently after surgeries for tumors located in the retromandibular prolongation of the gland, or in the pre-styloid space (parapharyngeal), which sometimes force to ligate the external carotid artery causing disruption of the sympathetic innervation.