Advancements in the Treatment of Differentiated Thyroid Cancer (DTC)

Radioiodine Ablation

  • The American Thyroid Association (ATA) recommends radioiodine (RAI) adjuvant therapy for:
    • High risk DTC patients after total thyroidectomy
  • Prior to RAI therapy:
    • Serum TSH, thyroglobulin (Tg), and anti-Tg antibody measurements should be obtained
  • Patients should be instructed to:
    • Maintain a low iodine diet (50 mg / day) for 1 to 2 weeks
    • And undergo thyroid hormone withdrawal
  • Levothyroxine (LT4):
    • Should be discontinued 3 to 4 weeks prior to RAI, and
  • Liothyronine (LT3):
    • Should be discontinued 2 weeks prior to therapy
  • ATA low and intermediate risk DTC patients and patients with contraindications to a hypothyroid state:
    • May undergo recombinant human TSH stimulation instead of thyroid hormone withdrawal
  • The 5-year follow-up results of the ESTIMABL1 trial:
    • A randomized control trial investigating rhTSH versus thyroid hormone withdrawal and low activity (1.1 GBq) versus high activity (3.7GBq) RAI in patients with low-risk DTC:
      • Showed no evidence of disease regardless of preparation method or radioiodine dose used, providing further support for the use of rhTSH and 1.1 GBq radioactive iodine in these patients
  • For advanced DTC:
    • Dosimetry might be appropriate to quantify RAI uptake and determine dosing given the variability from person to person, and within cells of the same tissue
  • The goals of RAI therapy include:
    • Destroying occult disease foci
    • Eliminating residual healthy tissue that may serve as a locus for neoplastic transformation
    • Improving the specificity of Tg as a tumor marker, and of whole body RAI scans during long-term surveillance
  • A dose of 30mCi is recommended over higher doses in lower-risk patients, but high-risk patients may require 100 to 200 mCi
  • During RAI ablation, 131I is taken up by follicular thyroid cells, where the molecules accumulate and undergo beta decay:
    • This process is optimized by functional sodium iodide symporter expression (NIS):
      • Dedifferentiating tumors lose NIS expression and become fluorodeoxyglucose (FDG) avid as they lose RAI avidity:
      • For this reason, FDG-PET (positron emission tomography) positive tumors:
        • Tend to be more aggressive and unlikely to respond to RAI
  • Age greater than 40 years, large tumor burden, and Hürthle cell histology:
    • Are also indicators of poor response
  • MAPK and PI3K / AKT activation:
    • Is thought to decrease NIS activity
  • Tumors with RAS mutations may be more likely to be RAI avid than those with BRAF and TERTmutations
  • Side effects of RAI therapy include:
    • Nausea
    • Temporary or permanent salivary gland and lacrimal duct dysfunction
    • Sialadenitis
    • Parotitis
    • Thyroiditis
    • Bone marrow and gonadal dysfunction
      • Adequate hydration might help alleviate symptoms
    • There is also a risk of second primary cancer of:
      • Soft tissue, salivary gland, colon, and blood, associated with higher cumulative doses
  • Less than 10% of DTC patients will develop metastatic disease
    • Of these, approximately one in three experience complete remission after RAI therapy
  • The ATA recommends a whole body scan with or without single photon emission computed tomography (SPECT) / computed tomography (CT) to determine RAI avidity for residual structural disease after therapy

#Arrangoiz #ThyroidSurgeon #ThyroidCancer #ThyroidExpert #CancerSurgeon #HeadandNeckSurgeon #EndocrineSurgery #MountSinaiMedicalCenter #MSMC #Miami #Mexico #RAI #RadioActiveIodine


Rodrigo Arrangóiz MS, MD, FACS, FSSO

  • Mount Sinai Medical Center (Main Campus)4306 Alton Road, 2nd Floor, Miami Beach, FL 33140
  • Mount Sinai Emergency Center and Primary & Specialty Care Hialeah6050 West 20th Ave., Hialeah, FL 33016

Rodrigo Arrangóiz MS, MD, FACS, FSSO

My Locations

  • Mount Sinai Medical Center (Main Campus)4306 Alton Road, 2nd Floor, Miami Beach, FL 33140
  • Mount Sinai Emergency Center and Primary & Specialty Care Hialeah6050 West 20th Ave., Hialeah, FL 33016

Papillary Thyroid Carcinoma in a Thyroglossal Duct

  • Thyroglossal duct remnants are commonly seen:
    • Comprising more than:
      • 75% of midline neck tumors in children 
      • 7% in adults
  • Finding a cancer within one of these cysts is rare:
    • One large study reported a prevalence of cancer:
      • In 1.3% of remnants
    • PTC is the most common tumor (90%):
      • Most are less than 1 cm
      • They are typically confined to the cyst
  • Because so few cases have been reported,:
    • No consensus exists about the optimal management
  • Most agree that a Sistrunk procedure is the best way to excise a thyroglossal duct cancer:
    • The necessity for total thyroidectomy is controversial:
      • As only 25% to 56% of patients have concomitant malignancy in the thyroid
    • A retrospective analysis of 18 patients treated at one institution found that:
      • 75% had lateral with or without central lymph node metastases 
      • 56% were found to have tumor foci in the thyroid
      • Twelve patients were given radioiodine
      • With a median follow-up of 12 years (range 1 to 22 years), 11 patients had stimulated thyroglobulin levels available; 10 were undetectable, the other was 2 ng/mL, and all had a negative neck ultrasound
    • Other studies have reported similarly encouraging results with follow-up, regardless of the treatment

#Arrangoiz #ThyroidSurgeon #CancerSurgeon #SurgicalOncologist #HeadandNeckSurgeon #EndocrineSurgery #ThyroidCancer #ThyroglossalDuctCystCancer #PapillaryThyroidCancer #Miami #Mexico #MountSinaiMedicalCenter

Thyroid surgery for differentiated thyroid cancer — recent advances and future

Thyroid surgery for differentiated thyroid cancer — recent advances and future directions

Tracy S. Wang & Julie Ann Sosa

Nature Reviews Endocrinology volume 14, pages670–683 (2018)

Key points

The incidence of thyroid cancer is increasing; this includes thyroid cancers of all tumour sizes and stages.

Molecular testing for indeterminate thyroid nodules continues to evolve and guide recommendations for the extent of thyroid surgery.

Appropriate extent of thyroidectomy for patients with low-risk thyroid cancer remains dynamic and might include active surveillance, thyroid lobectomy or total thyroidectomy.

Given the excellent outcomes for most patients with differentiated thyroid cancer, patient preference and a robust discussion regarding options for the extent of surgery and long-term surveillance are critical.

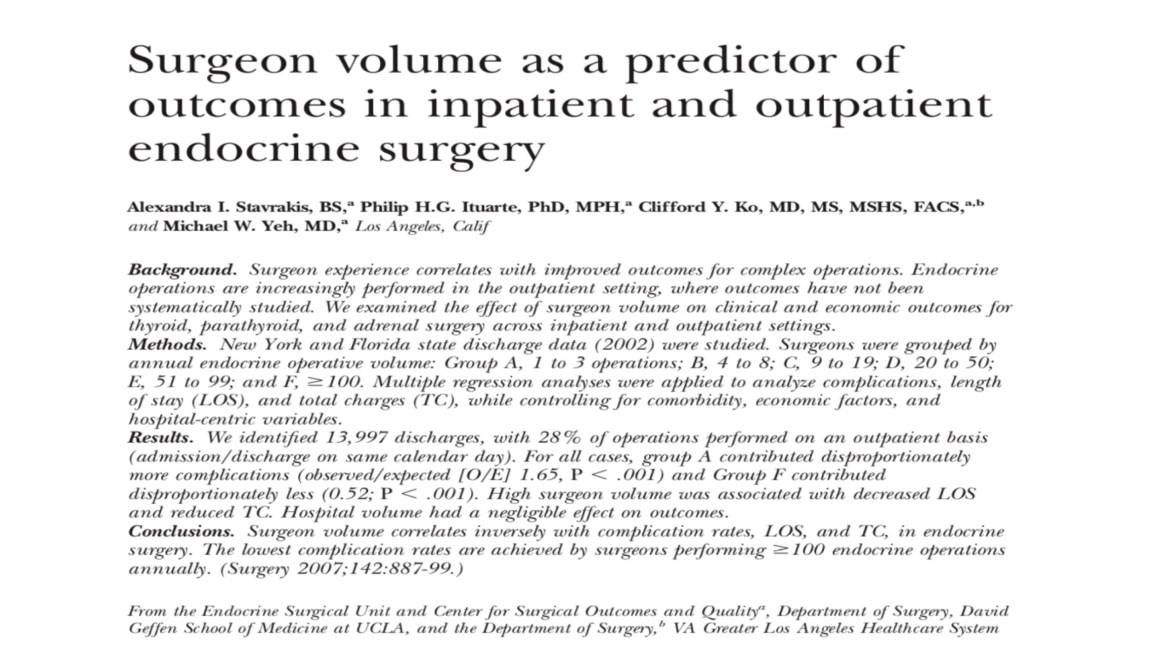
A strong association exists between surgeon volume and patient outcomes; surgeons’ awareness of their own outcomes is critical.

Referring providers, payers and policymakers should be aware of the implications of the association between surgeon volume and patient outcomes so that patient access to experienced thyroid surgeons can be optimized.

  • El entrenamiento y el volumen del cirujano son factores críticos para obtener el mejor resultado con las menores complicaciones en la cirugía de tiroides.

Presentation1


  • Ashok Shaha MD, FACScirujano de cabeza y cuello de Memorial Sloan Kettering Cancer Center experto en tiroides durante su plática inaugural de la American Head and Neck Society nos habla de quien debe estar realizando cirugía de tiroides.

REPORT THIS AD


Rodrigo Arrangoiz MS, MD, FACS cirujano de tumores de cabeza y cuello y cirugía endocrina de Mount Sinai Medical Center cumple con los requisitos determinados por el Dr. Saha para realizar cirugía de tiroides.

Su entrenamiento fue el siguiente:

• Cirugia general y gastrointestinal
• Michigan State University:
• 2004 al 2010image-48• Cirugia oncológica / tumores de cabeza y cuello / cirugia endocrina:
• Fox Chase Cancer Center (Filadelfia):
• 2010 al 2012image-39• Maestria en ciencias (Clinical research for healthprofessionals):
• Drexel University (Filadelfia):
• 2010 al 2012image-50• Cirugia de tumores de cabeza y cuello / cirugiaendocrina
• IFHNOS / Memorial Sloan Kettering Cancer Center:
• 2014 al 2016image-51

#Arrangoiz

#CirugiadeTumoresdeCabezayCuello

#CirugiaEndocrina

#CirugiaOncologica

#HeadandNeckSurgery

#EndocrineSurgery

#SurgicalOncology

#MountSinaiMedicalCenter

#Miami #Mexico

Adjuvant Chemotherapy for Triple Negative Breast Cancer (TNBC)

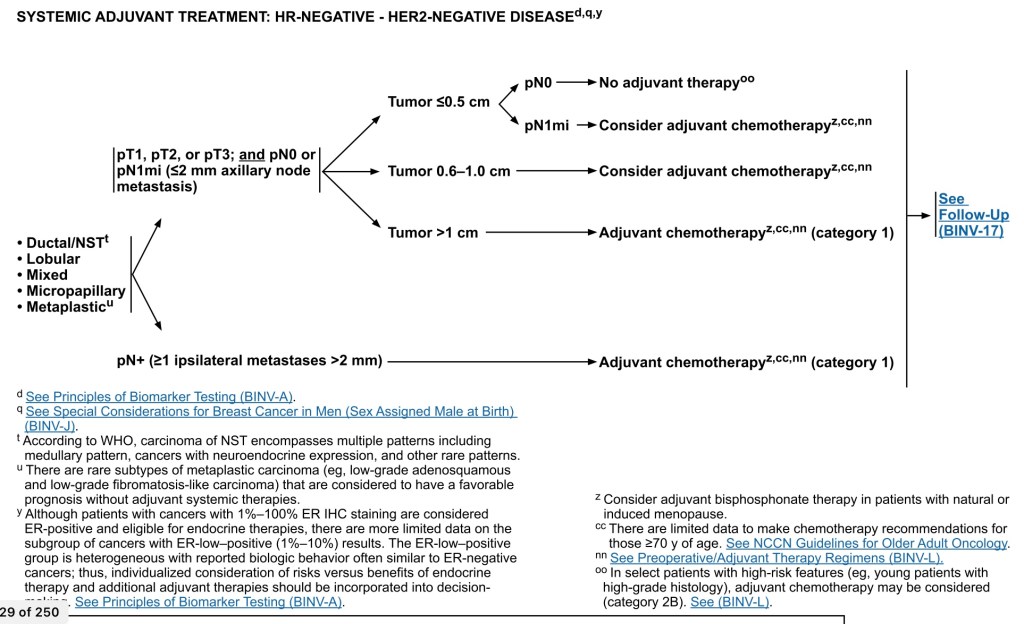
  • Algorithm for Adjuvant Therapy (AC) in TNBC:
    • For histologic types:
      • Ductal
      • Lobular
      • Mixed
      • Metaplastic
    • For pT1, T2, or T3 and pN0 or pN1mi (≤ 2 mm axillary nodal metastasis), adjuvant systemic treatment depends on tumor size:
      • For T1a (T ≤ 0.5 cm including microinvasive) and pN0:
        • NO adjuvant therapy, however, if pN1mi:
          • Adjuvant therapy should be considered
      • For T1b (T > 0.5 cm and ≤ 1.0 cm), pN0 or pN1mi:
        • Adjuvant therapy should be considered
      • For tumors greater than 1 cm, N0 or N1mi:
        • Chemotherapy should be given
      • For node-positive disease (one or more metastases ≥ 2 mm) to one or more axillary lymph nodes:
        • AC should be given
  • Standard Adjuvant Systemic Chemotherapy for TNBC:
    • Current AC for TNBC does not differ according to subtype
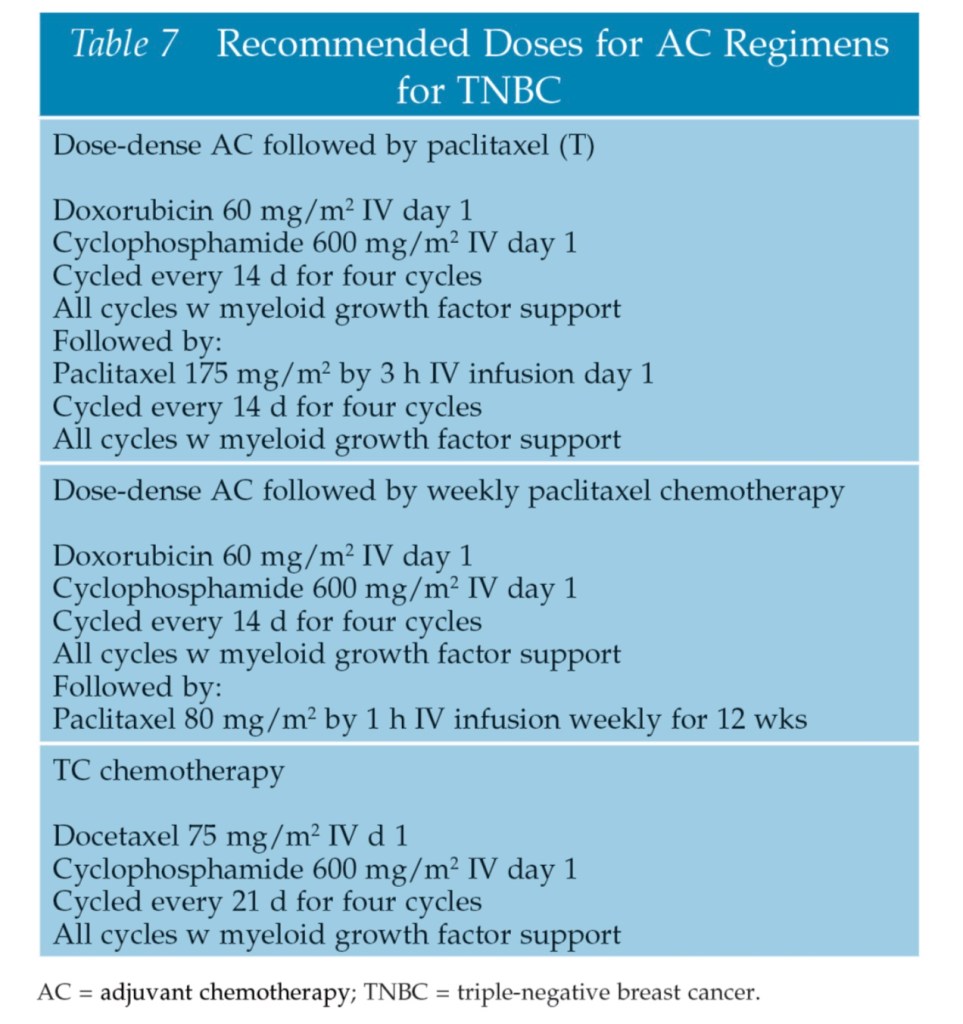
  • Preferred regimens are:
    • Dose-dense AC (doxorubicin / cyclophosphamide) followed by paclitaxel every 2 weeks
    • Dose-dense AC followed by weekly paclitaxel
    • TC (docetaxel and cyclophosphamide)
  • Other acceptable adjuvant therapy regimens as per NCCN guidelines are:
    • Dose-dense AC (doxorubicin / cyclophosphamide)
    • AC (doxorubicin / cyclophosphamide) every 3 weeks
    • Cyclophosphamide / methotrexate / fluorouracil
    • AC followed by docetaxel every 3 weeks
    • AC followed by weekly paclitaxel
    • Epirubicin / cyclophosphamide
    • TAC (docetaxel / doxorubicin / cyclophosphamide)
  • High-risk triple-negative patients are, in general:
    • Treated with an anthracycline and a taxane-containing regimen
  • Emerging concepts in systemic therapy for TNBC – Precision Medicine:
    • The considerable overlap of the BRCA1 tumor phenotype and TNBC:
      • Has led investigators to take advantage of TNBC BRCA-ness when considering chemotherapy regimens
    • The DNA repair defects characteristic of BRCA1-deficient cells:
      • Confer sensitivity to poly (adenosine diphosphate ribose) polymerase 1 (PARP) inhibition
      • Platinum salts:
        • Such as carboplatin and cisplatin:
          • Cause DNA cross-link strand breaks and thus should be effective in BRCA-mutated calls and TNBC:
            • Which are deficient in homologous DNA repair mechanisms
  • Consideration should be given for neoadyuvant chemotherapy (NAC) for:
    • Stages IIA, IIB, and IIIA and if the patient fulfills criteria for breast-conserving surgery apart from tumor size
  • The NCCN guidelines recommend:
    • The same NAC regimens for TNBC as for adjuvant treatment
  • Pathologic complete response (pCR) rates:
    • For TNBC are higher (22% to 44%) than for non-TNBC (6% to 11%)
  • Residual disease following NAC:
    • Portends a worse prognosis than a pCR
  • Response to neoadjuvant therapy (adriamycin-, cytoxan-, taxol-containing regimens) differs according to intrinsic subtype:
    • Masuda and colleagues noted a pCR of 28% overall:
      • However, when looked at by subtype:
        • BL1 subtype has a pCR of 52% versus:
          • BL2 0%
          • LAR 10%
          • MSL (23%)
  • TNBC subtype is an independent predictor of pCR following NAC:
  • Tsai and colleagues determined that residual nodal disease post-NAC for TNBC was associated with an unfavorable outcome:
    • They calculated the lymph node ratio (LNR) and the proportion of positive nodes over the number excised, following NAC according to molecular subtype:
      • Patients with a low LNR (≤ 0.2) had a prolonged DFS compared with those with a high (> 0.65) LNR
  • Patients with TNBC:
    • Have higher pCR rates in the axilla following NAC than patients with hormone receptor-positive cancers:
      • 49.4% versus 21.1%
  • Further, a pCR determined by the sentinel node biopsy in the axilla may reduce the need for full axillary dissection in selected patients who achieve the pCR:
    • Axillary downstaging to reduce the extent of axillary node dissection with NAC is an emerging paradigm
  • Despite the relative chemosensitivity of TNBC:
    • Early relapse is common:
      • Leading to the term:
        • Triple-negative paradox
    • TNBC tumors show increased rates of pCR to NAC:
      • But have lower DFS and overall survival (OS) compared with other subtypes
  • It has been postulated that the triple-negative paradox:
    • Is due to differing pCR rates and higher likelihood of relapse in patients who do not achieve pCR
  • Swisher and colleagues found that failure to achieve a pCR (in both the breast and axilla) following NAC:
    • Was a significant adverse feature for patients with TNBC tumors
    • With a median follow-up of 4.6 years:
      • Those with a pCR the locoregional recurrence-free survival was:
        • 98.6% versus 89.9% for those who did not achieve pCR (p = .007)
  • For TNBC patients having residual disease following NAC:
    • The use of AC following surgery has been associated with an improvement in survival
  • The CREATE-X (Capecitabine for Residual Cancer as Adjuvant Therapy) trial:
    • Was designed to study the effect of adjuvant capecitabine on patients with TNBC who did not achieve pCR following NAC
    • Women in the capecitabine group:
      • Had better 2-year:
        • DFS:
          • 82.8% versus 74.0%
        • OS:
          • 94% versus 89.2%
  • In an ongoing clinical trial (SWOG 1418):
    • The role of pembrolizumab (an immune checkpoint inhibitor) in patients with residual disease after NAC is being investigated
  • Two landmark trials have shown the efficacy of platinum salts when added to NAC regimens for TNBC:
    • The GeparSixto trial:
      • Compared paclitaxel, doxorubicin, and bevacizumab (Avastin) with or without carboplatin
      • In the TNBC subset:
        • pCR improved from 37.9% to 58.7% with the addition of carboplatin
    • In the Cancer and Leukemia Group B 40603 trial:
      • Patients received paclitaxel 80 mg/m2 once per week for 12 weeks followed by doxorubicin plus cyclophosphamide once every 2 weeks for four cycles, and were randomly assigned to concurrent carboplatin (area under curve 6) once every 3 weeks for four cycles and / or bevacizumab 10 mg/kg once every 2 weeks for nine cycles
      • The addition of either carboplatin (60% versus 44%; p = .0018) or bevacizumab (59% versus 48%; p = .0089) significantly increased pCR in the breast:
      • Whereas only carboplatin (54% versus 41%; p = .0029) significantly raised pCR in both and axilla
  • In a meta-analysis of eight platinum-based therapy trials for TNBC:
    • Tian and colleagues concluded that both pCR and overall response rate:
      • Were significantly higher for platinum-based regimens
  • In the I-SPY 2 trial:
    • A phase 2, multicenter, adaptively randomized trial:
      • Multiple experimental regimens in combination with standard NAC were screened
    • Seventy-two patients with TNBC were randomly assigned to receive veliparib (a PARP inhibitor), carboplatin, and standard therapy, and 44 patients were concurrently assigned to receive control therapy
    • The investigators found the estimated rates of pathologic complete response in the triple-negative population at the completion of chemotherapy were:
      • 51% in the veliparib-carboplatin group versus 26% in the control group
      • They concluded that veliparib-carboplatin had an 88% predicted probability of success in a phase 3 trial for TNBC

#Arrangoiz #CancerSurgeon #BreastSurgeon #SurgicalOncologist #ComplexSurgicalOncology #BreastCancer #TripleNegativeBreastCancer #TNBC #Miami #Mexico #Teacher #Surgeon #MountSinaiMedicalCenter #MSMC

Metastatic Triple Negative Breast Cancer (TNBC)

  • All patients with TNBC:
    • Should be considered for a clinical trial
  • Taxanes, carboplatin, eribulin, and capecitabine:
    • Are some of the commonly used standard chemotherapeutic drugs
  • In general, medical oncologists recommend single-agent sequential therapy
  • Combination regimens:
    • Have not shown an improvement in DFS or OS
  • If the patient has a BRCA mutation:
    • He / she could be considered for a PARP inhibitor trial
  • Based on the Olympiad trial:
    • The PARP inhibitor olaparib:
      • Has shown improvement in progression-free survival
    • Several other PARP inhibitors such as niraparib and veliparib are being investigated in clinical trials:
  • An ongoing SWOG trial (SWOG 1416):
    • Is looking at the role of veliparib in mTNBC patients treated with cisplatin
  • If the patient has a mismatch repair–deficient tumor or a tumor with microsatellite instability:
    • He or she could be considered for pembrolizumab based on recent FDA approval of pembrolizumab in the tumor agnostic setting
  • In about 10% of patients, next-generation sequencing may also give a genomically driven clinical trial option

#Arrangoiz #CancerSurgeon #BreastSurgeon #SurgicalOncologist #ComplexSurgicalOncology #BreastCancer #TripleNegativeBreastCancer #TNBC #Miami #Mexico #Teacher #Surgeon #MountSinaiMedicalCenter #MSMC

Differentiated Thyroid cancer: Radioiodine Treatment

Introduction

• Radioiodine therapy:

• Has been used in the management of patients with well-differentiated (papillary or follicular) thyroid cancer since the 1940s

• Thyroid tissue has a unique ability to take up iodine from blood:

• Like iodine, radioiodine is taken up and concentrated in thyroid follicular cells:

• Because they have a membrane sodium-iodide transporter

• Compared with normal thyroid follicular cells:

• Thyroid cancer cells have reduced expression of the transporter:

• Which may account for the low iodine-131 (131-I) uptake in thyroid cancer tissue

• 131-I:

• Causes acute thyroid cell death by:

• Emission of short path-length (1 to 2 mm) beta particles

• The uptake of 131-I by thyroid tissue:

• Can be visualized by scanning to detect the gamma radiation that is also emitted by the isotope

• 131-I must be taken up by thyroid tissue to be effective:

• As a result, it is of no value in patients whose thyroid cancers do not concentrate iodide:

• Patients with medullary cancer, lymphoma, or anaplastic cancer

Goals of Radioactive Iodine Treatment

• In an effort to standardize terminology:

• An inter-societal working group with representatives from the American Thyroid Association (ATA), the European Thyroid Association, the European Association of Nuclear Medicine, and the Society of Nuclear Medicine and Molecular Imaging reached the following consensus regarding the goals of iodine-131 (131-I) therapy in differentiated thyroid cancer:

• Remnant ablation:

• The primary goal of remnant ablation is:

• Destruction of presumably benign thyroid tissue after total thyroidectomy:

• To facilitate initial staging and follow-up studies. This will, in turn:

• Improve the specificity of measurements of serum thyroglobulin (Tg) as a tumor marker

• Increase the specificity of 131-I scanning for detection of recurrent or metastatic disease:

• By eliminating uptake by residual normal tissue

• Adjuvant treatment:

• The primary goal of adjuvant treatment is destruction of subclinical tumor deposits:

• That may or may not be present after surgical resection of all known primary tumor tissue and metastatic foci

• Since adjuvant treatment is given based on the risk of having persistent / recurrent disease without definitive evidence of biochemical or structural evidence of disease:

• It is accepted that some patients selected for adjuvant treatment might already have been treated sufficiently by their primary surgery

• Thus, the decision to recommend adjuvant treatment requires:

• Balancing oncological risk (risk of persistent / recurrent disease and disease-specific mortality) and the risks associated with adjuvant treatment (short- and long-term risks of 131-I):

• With the potential benefit of adjuvant treatment (potential to decrease recurrence, improve progression-free survival, and/or improve disease-specific mortality)

• Thus, in properly selected patients, the potential benefits of 131-I adjuvant treatment could include:

• Destruction of subclinical, microscopic foci of disease remaining after surgery

• Decreased risk of recurrence

• Improved disease-specific survival

• Improved progression-free survival

• Treatment of known disease:

• The primary goal in the treatment of known disease is:

• Destruction of clinically apparent macroscopic disease (evidenced by either abnormal thyroglobulin values or structural findings) that is not amenable to surgical therapy

• Radioiodine treatment of residual disease and metastatic disease:

• May reduce the risk of recurrence and mortality:

• Especially in small-volume disease that is radioiodine avid

#Arrangoiz #ThyroidSurgeon #CancerSurgeon #HeadandNeckSurgeon #ThryoidExpert #ThyroidCancer #RadioactiveIodine #Teacher #Miami #MountSinaiMedicalCenter

Surgical Management of Triple Negative Breast Cancer

  • Surgical management of TNBC consists of the standard options of:
    • Breast-conserving treatment versus mastectomy
  • TNBC should not be treated differently from the surgical standpoint
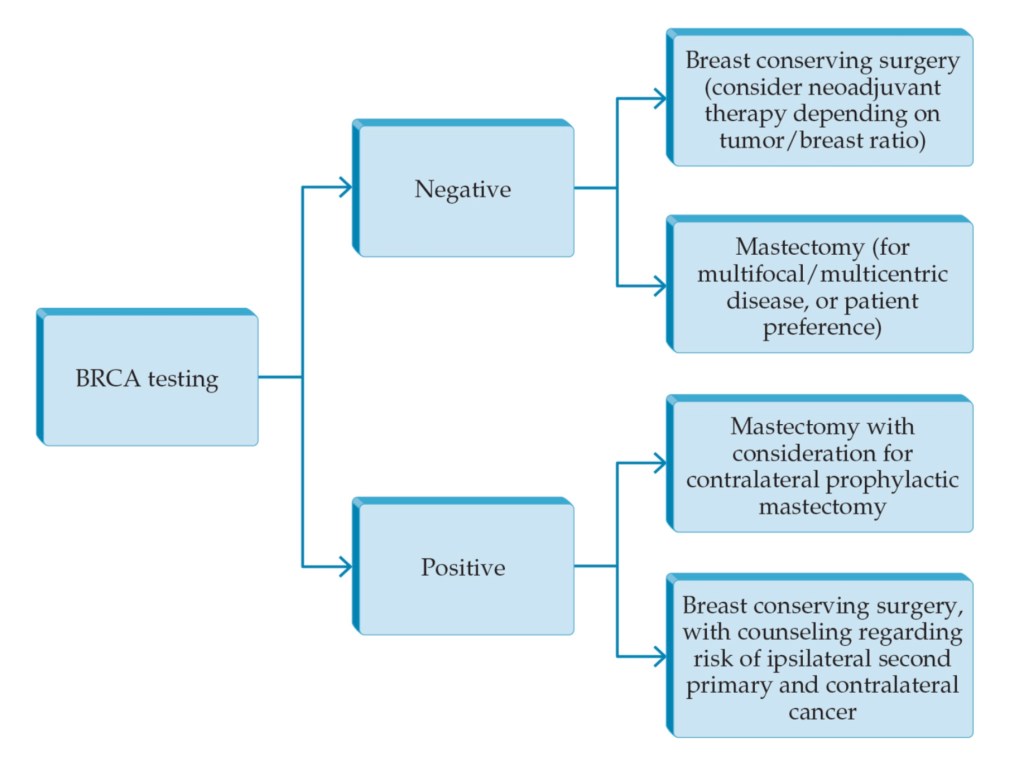
  • Genetic testing and BRCA 1/ BRCA 2 status guide surgical choices as per the algorithm are shown in Figure
  • NCCN guidelines recommend:
    • Discussion of the option of risk-reducing mastectomy
Algorithm for surgical choices in TNBC based on genetic testing and BRCA1 / BRCA 2 status

#Arrangoiz #CancerSurgeon #BreastSurgeon #SurgicalOncologist #ComplexSurgicalOncology #BreastCancer #TripleNegativeBreastCancer #TNBC #Miami #Mexico #Teacher #Surgeon #MountSinaiMedicalCenter #MSMC

Clinical Features and Presentation of Triple Negative Breast Cancers

  • The majority of TNBCs are detected clinically as a:
    • Mass, either by the patient or examining clinician
  • Other possible presenting symptoms include:
    • Breast pain
    • Bloody nipple discharge
  • In the institutional review by Krizmanich-Conniff and colleagues, when compared with non-TNBCs:
    • TNBCs were more likely to present clinically:
      • 68% versus 48%
    • The remaining 32% of TNBCs were found on screening mammography:
      • Whereas 52% of non-TNBCs were found by screening
  • More than one-third of patients whose TNBC was detected clinically had no prior mammography:
    • Of those detected by mammography:
      • One-third had developed within 12 months of the last mammography:
        • The high incidence of interval cancers is attributed to the aggressive growth rate of TNBC
  • Imaging:
    • Mammographic characteristics of TNBC included:
      • A round mass (59.3%) or an oval or lobulated mass (65%), with circumscribed (15%), microlobulated (12.5%), or indistinct margins (55%)
      • Spiculated margins were much less common (15%)
  • On mammography, TNBCs are most likely seen as:
    • A noncalcified mass:
      • 58%
  • Dogan and Turnbull caution that TNBC may lack the typical mammographic features of breast cancer, and although ultrasonography adds to the sensitivity of diagnosis:
    • 21% to 41% of TNBCs can have benign characteristics on breast imaging
  • On MRI, the most common enhancement pattern seen with TNBC is rim enhancement:
    • MRI findings following neoadjuvant chemotherapy (NAC):
      • Correlate well with the extent of residual tumor
    • MRI provides a reliable baseline prior to NAC and can predict response more sensitively than other imaging methods

#Arrangoiz #CancerSurgeon #BreastSurgeon #SurgicalOncologist #ComplexSurgicalOncology #BreastCancer #TripleNegativeBreastCancer #TNBC #Miami #Mexico #Teacher #Surgeon #MountSinaiMedicalCenter #MSMC