
Accelerated Partial Breast Irradiation (APBI)

The use of catheter-based, accelerated partial-breast irradiation (APBI) offers many potential advantages over routine whole-breast radiation therapy, including decreased treatment time and decreased radiation dose delivered to uninvolved portions of the breast and adjacent organs. This has resulted in significant interest in APBI, with more than 32,000 women in the United States having had treatment with a breast brachytherapy catheter.

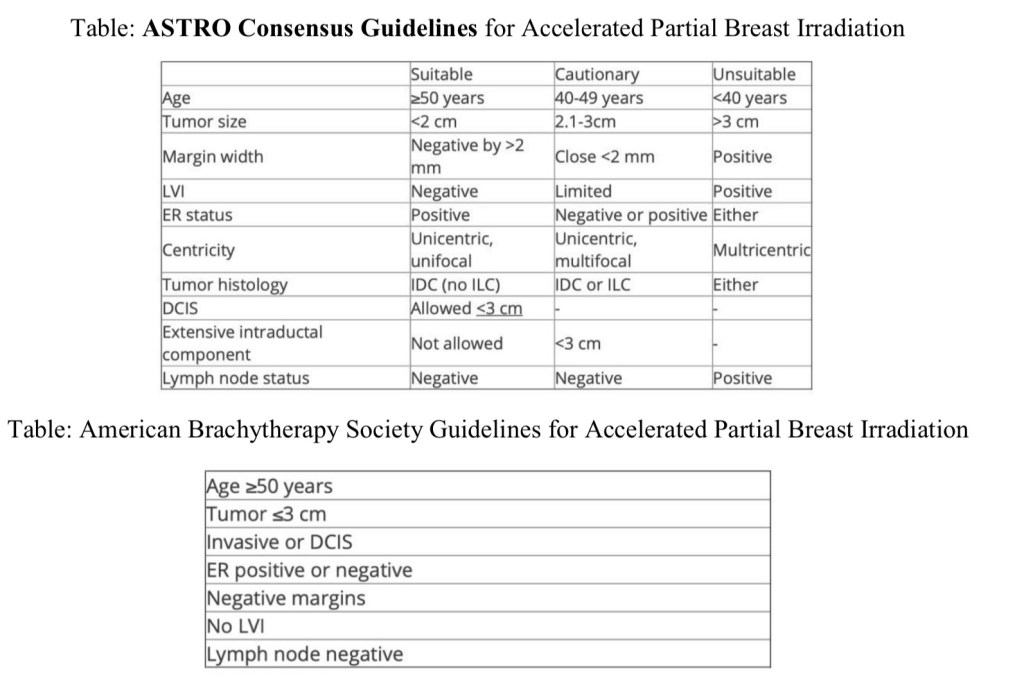
However, randomized clinical trials comparing APBI with conventional whole-breast radiation therapy have yet to be completed. In light of this, the American Society for Radiation Oncology (ASTRO) has issued a consensus statement regarding the appropriate use of APBI, categorizing potential patients for APBI into three groups: suitable, cautionary, and unsuitable. A similar, but somewhat more liberal guideline was put forth by The American Brachytherapy Society.

Accelerated partial breast irradiation includes multiple techniques such as: interstitial brachytherapy, applicator brachytherapy, external beam radiation therapy.

The Groupe Européen de Curie thérapie of European Society for Radiotherapy and Oncology (GEC-ESTRO) trial randomized 1184 patients with low-risk invasive carcinoma or ductal carcinoma in situ (DCIS) treated with breast-conserving surgery to either whole-breast irradiation (WBI) or APBI using multi catheter brachytherapy. The cumulative incidence of local recurrence at 5 years was 1.44% with APBI and 0.92% with WBI.

The Florence trial randomized 520 patients to either WBI or APBI with intensity-modulated radiation therapy, with a mean follow-up of 5 years. The rate of local recurrence was 1.5% in both arms.

The American Society of Breast Surgeons’ Mammo Site Registry found 5-year rates of local recurrence were less than 4%.

An older randomized trial from Hungary using interstitial APBI and electrons found that the 5-year local recurrence rate of 4.7%.


It is important to recognize that these outcomes are likely due to the highly selected, low-risk patient populations included in many of the APBI trials as evidenced by the tables / guidelines: patients tend to be postmenopausal, tumors less than 3 cm, without DCIS, node negative, ER-positive.


Arthur D W, Vicini F A, Kuske RR, Wazer DE, American Brachytherapy Society. Accelerated partial breast irradiation: an updated report from the American Brachytherapy Society. Brachytherapy. 2003;2:124-130.

Hughes KS, Schnaper LA, Berry D, et al. Cancer and Leukemia Group B; Radiation Therapy Oncology Group; Eastern Cooperative Oncology Group. Lumpectomy plus tamoxifen with or without irradiation in women 70 years of age or older with early breast cancer. N Engl J Med. 2004;351:971-977.

National Comprehensive Cancer Network. NCCN Clinical Practice Guidelines in Oncology. Breast Cancer. Available at http://www.nccn.org.

Smith BD, Arthur DW, Buchholz TA, et al. Accelerated partial breast irradiation consensus statement from the American Society for Radiation Oncology (ASTRO). J Am Coll Surg. 2009;209:269-277.

Giuliano AE, Ballman KV, McCall L, et al. Effect of Axillary Dissection vs No Axillary Dissection on 10-Year Overall Survival Among Women With Invasive Breast Cancer and Sentinel Node Metastasis: The ACOSOG Z0011 (Alliance) Randomized Clinical Trial. JAMA. 2017; 318(10): 918-926. doi: 10.1001/jama.2017.11470.

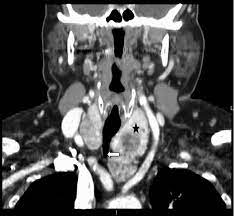
Goiter

  • The term goiter refers to:
    • An abnormal growth of the thyroid gland
  • Depending on the etiology goiters can be:
    • Diffuse
    • Nodular
  • May be associated with:
    • Normal thyroid hormone production
    • Decreased thyroid hormone production
    • Increased thyroid hormone production
  • The clinical manifestations vary with:
    • Thyroid function and with the size and location of the goiter
  • Anatomical Relationships:
    • In healthy adults without iodine deficiency:
      • A normal thyroid gland is approximately:
        • 4.0 cm to 4.8 cm x 1.0 cm to 1.8 cm x 0.8 cm to 1.6 cm in size
      • Mean sonographic volume of:
        • 7 mL to 10 mL:
          • Thyroid volume measured by ultrasonography:
            • Is slightly greater in men than women
            • Increases with age and body weight
            • Decreases with increasing iodine intake
  • Weight of the thyroid gland:
    • 10 grams to 20 grams:
      • As high as 30 grams is considered normal
  • The normal thyroid gland:
    • Is immediately caudal to the larynx and encircles the anterolateral portion of the trachea
  • The thyroid gland is bordered by:
    • The trachea and esophagus posteriorly
    • The carotid sheath laterally
  • Enlarging thyroid lobes:
    • Usually grow outward:
      • Because of their location in the anterior neck in front of the trachea:
        • Covered only by the thin strap muscles, subcutaneous tissue, and skin
    • As a result of this outward growth:
      • Even very large goiters:
        • May not compress the trachea or impinge on the great vessels lateral to the lobes:
          • However, in patients with substantial enlargement of one lobe or asymmetric enlargement of both lobes:
            • The trachea, esophagus, or blood vessels:
              • May be displaced or, less often, compressed
          • Bilateral lobar enlargement:
            • Especially if the goiter extends posterior to the trachea:
              • May cause either:
                • Compression or concentric narrowing of the trachea
                • Compression of the esophagus
                • Compression of the jugular veins
  • The thoracic inlet:
    • Is an ovoid area that measures approximately 5 cm x 10 cm:
      • Boundaries:
        • The sternum anteriorly
        • The first thoracic vertebral body posteriorly
        • The first ribs laterally
    • The inlet is traversed by the:
      • Trachea
      • Esophagus
      • Blood vessels
      • Nerves
    • The inferior pole of each thyroid lobe:
      • Normally lies above the thoracic inlet:
        • However, with some goiters, there is growth of one or both lobes through the inlet into the thoracic cavity:
          • Which can result in obstruction of any of the structures in the inlet:
            • Such goiters are called substernal:
              • Although retrosternal is probably a more precise term
  • Most substernal goiters are in the:
    • Anterolateral mediastinum:
      • But approximately 10%:
        • Are located primarily in the posterior mediastinum
  • The prevalence of substernal goiter as a percentage of thyroidectomies:
    • Ranges from 2% to 19%

#Arrangoiz #ThyroidSurgeon #HeadandNeckSurgeon #CancerSurgeon #MSMC #MountSinaiMedicalCenter #Miami #Mexico #Goiter #SubsternalGoiter

Lobular Carcinoma and MRI Use

The data for preoperative MRI in the setting of either lobular or ductal carcinoma is controversial.

Routine preoperative MRI is not mandatory for either entity and is not anticipated to change the rate of repeat excision for positive margins or recurrence. It should be used on a case-by-case basis, taking into account other factors, such as breast density and additional risk factors.

Invasive lobular carcinoma is described pathologically as small cells that infiltrate the mammary stroma and adipose tissue in a single file pattern due to a lack of E-cadherin. The cells induce minimal reaction in the surrounding tissue, making them insidious both radiographically and pathologically. Classic-type invasive lobular carcinoma is usually positive for estrogen receptor and negative for HER2, but this is not universally true, as HER2 subtypes do exist. Lobular cancers respond less well to neoadjuvant chemotherapy than their ductal counterparts.

Orvieto E, Maiorano E, Bottiglieri L, et al. Clinicopathologic characteristics of invasive lobular carcinoma of the breast: results of an analysis of 530 cases from a single institution. Cancer. 2008;113:1511-1520.

Purushotham A, Pinder S, Cariati M, Harries M, Goldhirsch A. Neoadjuvant chemotherapy: not the best option in estrogen receptor-positive, HER2-negative, invasive classical lobular carcinoma of the breast? J Clin Oncol. 2010;28:3552-3554.

Turnbull L, Brown S, Harvey I, et al. Comparative effectiveness of MRI in breast cancer (COMICE) trial: a randomized controlled trial. Lancet. 2010;375:563-571.

Inflammatory Breast Cancer (IBC)

Inflammatory breast cancer (IBC) is a clinical diagnosis made on the basis of a breast that rapidly enlarges; that is red, firm, and has skin edema (peau d’orange); and that involves 30% of the breast or more with a palpable border.

On evaluation of a specimen obtained by skin punch biopsy, the hallmark of this disease is dermal lymphatic invasion by tumor cells, but this pathologic finding is not necessary to make the diagnosis.

Nearly all women with IBC have lymph node involvement at the time of diagnosis, and sentinel lymph node biopsy has been shown to have a high false-negative rate in these patients. Hence, sentinel node biopsy is not indicated.

Approximately 30% of women with IBC will have distant metastatic disease; thus, all women with IBC should have a thorough staging work-up at the time of diagnosis.

As IBC has an American Joint Committee on Cancer (AJCC) stage of IIIb or higher (owing to its designation of T4d, N0-3, M0-1), neoadjuvant chemotherapy is the recommended first course of treatment.

Skin-sparing mastectomy is contraindicated.

Because the degree of pathologic response to neoadjuvant chemotherapy predicts prognosis, and the intensity of preoperative therapy predicts response, all chemotherapy up front instead of a so-called sandwich approach of chemotherapy/surgery/chemotherapy is preferred.

Surgery is indicated if disease responds well, as this gives the best chance for disease-free survival.

Post-mastectomy radiation therapy is required to reduce the risk of chest wall recurrence in these patients.

Cristofanilli M, Gonzalez-Angulo AM, Buzdar AU, Kau SW, Frye DK, Hortobagyi GN. Paclitaxel improves the prognosis in estrogen receptor negative inflammatory breast cancer: the M.D. Anderson Cancer Center experience. Clin Breast Cancer. 2004;4:415-419.

Dawood S, Cristofanilli M. What progress have we made in managing Inflammatory breast cancer? Oncology (Williston Park). 2007;21:673-687.

National Comprehensive Cancer Network. NCCN Clinical Practice Guidelines in Oncology. Breast Cancer. Available at http://www.nccn.org.

Panades M, Olivotto IA, Speers CH, et al. Evolving treatment strategies for inflammatory breast cancer: a population-based survival analysis. J Clin Oncol. 2005;23:1941-1950.

Breast Cancer in Pregnancy

Breast cancer associated with pregnancy occurs anywhere in the first postpartum year, during pregnancy, or anytime during lactation.

Management of pregnant women newly diagnosed with breast cancer can be complex and depends on the trimester of pregnancy and desires for breast conservation.

Most obstetricians will recommend to deliver the baby at the earliest at 34 weeks to avoid morbidity of prematurity and treatment for the breast cancer should not be delayed until delivery. Studies have shown worse survival in those patients who delayed treatment 3 to 6 months.

It is safe to administer chemotherapy during pregnancy, but the risk of congenital malformations in the first trimester can be as high as 20% so it is generally recommended to start chemotherapy in the second or third trimester. The only agents that are contraindicated are taxanes and trastuzumab.

A study published in 2006 did not show any significant short term complications for children that were exposed to fluorouracil, doxorubicin, cyclophosphamide (FAC) chemotherapy in utero. It is not safe however to administer radiation or hormone therapy during pregnancy because of risks to the fetus.

Surgery is safe in the second and third trimester and is generally avoided in the first trimester due to risk of spontaneous abortion.

Surgical options include mastectomy and breast conservation, if applicable. If a patient has lumpectomy, radiation therapy must wait until after delivery. Sentinel node biopsy has been shown to be safe during pregnancy followed by axillary node dissection if the sentinel node is tumor positive. It is generally felt that preoperative lymphoscintigraphy is safe during pregnancy, although only a few small studies have examined sentinel node biopsy in pregnant patients. Injection of blue dye to identify a sentinel node is not recommended because of the small risk of allergic reaction and uncertain affects on the fetus.

Therapeutic abortion is no longer necessary or recommended.

Barnes DM, Newman LA. Pregnancy-associated breast cancer: a literature review. Surg Clin North Am. 2007:87:417-430.

Berry DL, Theriault RL, Holmes FA, et al. Management of breast cancer during pregnancy using a standardized protocol. J Clin Oncol. 1999;17:855-861.

Hahn KME, Johnson PH, Gordon N, et al. Treatment of pregnant breast cancer patients and outcomes of children exposed to chemotherapy in utero. Cancer. 2006;107:1219-1226.

Khera SY, Kiluk JV, Hasson DM, et al. Pregnancy-associated breast cancer patients can safely undergo lymphatic mapping. Breast J. 2008;14:250-254.

Mondi MM, Cuenca RE, Ollila DW, Stewart JH 4th, Levine EA. Sentinel lymph node biopsy during pregnancy: initial clinical experience. Ann Surg Oncol. 2007;14:218-221.

The National Surgical Adjuvant Breast and Bowel Project (NSABP) B-18 trial compared the strategy of four cycles of chemotherapy followed by surgery (neoadjuvant) to the strategy of surgery followed by four cycles of the same chemotherapy (adjuvant).

While the former was associated with a higher rate of breast conservation, there was no difference in survival between the two arms.

Patients who achieve a pathologic complete response after neoadjuvant chemotherapy have an improved prognosis; therefore, many clinical trials use the neoadjuvant setting, where response to novel therapies can be monitored in vivo.

Untch M, Konecny GE, Paepke S, von Minckwitz G. Current and future role of neoadjuvant therapy for breast cancer. Breast. 2014; 23:526-537.

Wang-Lopez Q, Chalabi N, Abrial C, et al. Can pathologic complete response (pCR) be used as a surrogate marker of survival after neoadjuvant therapy for breast cancer? Crit Rev Oncol Hematol. 2015;95:88-105.

Wolmark N, Wang J, Mamounas E, Bryant J, Fisher B. Preoperative chemotherapy in patients with operable breast cancer: nine year results for National Breast and Bowel Project B-18. J Natl Cancer Inst Monogr. 2001;30:96-102

Who Should Get Metastatic Work-Up in Operable Breast Cancer Patients

Patients presenting with potentially operable breast cancer should be evaluated for occult metastatic disease if they have clinical stage III disease, per American Society of Clinical Oncology (ASCO) guidelines.

Patients with stage II disease have a low rate of finding distant metastases, and, therefore, such a work-up is not indicated.

While young age and triple-negative phenotype are poor prognostic factors, they do not influence whether patients should have a metastatic work-up independent of clinical stage.

Brennan ME, Houssami N. Evaluation of the evidence on staging imaging for detection of asymptomatic distant metastases in newly diagnosed breast cancer. Breast. 2012;21:112-123.

Kim H, Han W, Moon HG, et al. The value of preoperative staging chest computed tomography to detect asymptomatic lung and liver metastasis in patients with primary breast carcinoma. Breast Cancer Res Treat. 2011;126:637-641.

Myers RE, Johnston M, Pritchard K, et al. Baseline staging tests in primary breast cancer: A practice guideline. CMAJ. 2001;164:1439-1444.

Schnipper LE, Smith TJ, Raghavan D, et al. American Society of Clinical Oncology identifies five key opportunities to improve care and reduce costs: the top five list for oncology. J Clin Oncol. 2012;30:1715-1724.

Paget Disease of the Breast

Paget’s disease of the breast, which is completely unrelated to Paget’s disease of bone, accounts for 1% to 3% of all breast cancers. Paget’s disease may be either ductal carcinoma in situ (DCIS) or invasive breast cancer, although in situ lesions predominate.

Paget cells are large eosinophilic cells with pale cytoplasm and large atypical nuclei; these should be distinguished from Toker cells, which tend to be small bland cells that can be found in 10% of normal nipples.

Although most series have included small cohorts, mammographically occult underlying cancers have been found in 29% to 100% of cases of Paget’s disease. Preoperative imaging is critical, particularly if breast conservation is desired. If mammography is negative, breast MRI should be considered. However, if biopsy of the nipple demonstrates invasion and mastectomy is the chosen procedure, the findings on breast MRI would unlikely change management.

Breast conservation was previously thought to be contraindicated because of the need to remove the nipple-areolar complex. However, as with other breast cancers, lumpectomy (to include the nipple-areolar complex) is oncologically safe provided negative margins are obtained even if an underlying invasive cancer is present. The patient should be counseled, however, about the resulting cosmetic deformity. Radiotherapy alone is insufficient treatment and has not been evaluated for this disease.

Evaluation of the nodes with use of sentinel lymph node biopsy is indicated in standard fashion if invasive cancer is present, or if the patient opts for a mastectomy and has DCIS.

Bijker N, Rutgers EJ, Duchateau L, et al. Breast-conserving therapy for Paget disease of the nipple: a prospective European Organization for Research and Treatment of Cancer study of 61 patients. Cancer. 2001;91:472-477.

Dalberg K, Hellborg H, Warnberg F. Paget’s disease of the nipple in a population based cohort. Breast Cancer Res Treat. 2008;111:313-319.

Echevarria JJ, Lopez-Ruiz JA, Martin D, Imaz I, Martin M. Usefulness of MRI in detecting occult breast cancer associated with Paget’s disease of the nipple-areolar complex. Br J Radiol. 2004;77:1036-1039.

Ikeda DM, Helvie MA, Frank TS, Chapel KL, Andersson IT. Paget disease of the nipple: radiologic-pathologic correlation. Radiology. 1993;189:89-94.

HER2-Targeted Agents In Breast Cancer

HER2-targeted agents are highly effective in improving survival in HER2-positive patients.

Therefore, trastuzumab (+/- pertuzumab), both of which target HER2, are part of every regimen endorsed by NCCN for HER2-positive disease.

These are often combined with standard chemotherapy, composed of anthracyclines (such as doxorubicin) and/or taxanes (such as docetaxel and paclitaxel).

National Comprehensive Cancer Network. NCCN Clinical Practice Guidelines in Oncology. Breast Cancer. Available at http://www.nccn.org.

Slamon D, Eiermann W, Robert N, et al. Adjuvant trastuzumab in her2 positive breast cancer. N Engl J Med. 2011;365:1273-1283.

HR+, HER2+ Early-Stage Disease: Interpreting Results From ADAPT and NSABP B52

We have two trials out there looking at anti-HER2 therapy plus/minus endocrine therapy in the setting. One trial is the ADAPT Trial looking at hormone receptor-positive, HER2-positive disease at 12 weeks of T-DM1 (ado-trastuzumab) plus/minus endocrine therapy, where there was no difference in the pCR (pathologic complete response) rate but a substantial pCR of 41% with 12 weeks of TDM1 alone.

The second trial is the NSABP B-52 trial, a phase III trial that looked at TCHP (docetaxel, carboplatin, trastuzumab, and pertuzumab) plus/minus endocrine therapy.

Both trials involved pre- and postmenopausal patients. And again, the NSABP B-52 trial did not show an improvement of the pCR in hormone receptor-positive HER2-positive disease by adding endocrine therapy to anti-HER2 therapy.

What does that mean for clinical practice?

It means, first of all, the endocrine therapy did not negatively impact the pCR rate. So it’s safe to use endocrine therapy plus anti-HER2 therapy in the postoperative setting, but there is no need, so far, to combine it with the anti-HER2 therapy with a chemotherapy backbone in the neoadjuvant setting. We don’t know why that is; it may be that the times used in the studies were not long enough and endocrine therapy added to anti-HER2 therapy needs a longer time. But I think for the time being, we should not combine endocrine therapy plus chemotherapy and anti-HER2 therapy in the neoadjuvant setting.
