Blog

High-Risk Assessment of Early Breast Cancer II

  • Although women with at least one first-degree relative with a history of breast cancer have a two- to three fold excess risk of developing the disease, only 5% to 10% have an identifiable hereditary predisposition
  • On average, women with a germline BRCA1 mutation have a 72% risk of developing breast cancer by age 80 years
  • For those with a germline BRCA2 mutation, the risk is 69%
  • The highest rates of BRCA1 mutations occur among Ashkenazi Jewish women
  • Because of the high lifetime risk for breast cancer in germline BRCA mutation carriers, both American and European guidelines recommend considering prophylactic surgery, such as double mastectomy
  • Other women at high risk of developing breast cancer because of a hereditary predisposition may opt for frequent imaging
  • Breast cancers that develop in germline BRCA1 mutation carriers are more likely to be high-grade, as well as triple-negative or basal-like subtype, whereas those with BRCA2 mutations are more likely to develop a high-grade, hormone receptor–positive/HER2-negative tumor

#Arrangoiz #BreastSurgeon #CancerSurgeon #SurgicalOncologist #MountSinaiMedicalCenter #MSMC #Miami #Mexico #BreastCancer

Breast Cancer Subtypes

  • One of the most important factors to be considered with breast cancer diagnosis is breast cancer subtype
  • There are three major breast cancer subtypes: luminal-like, HER2-positive, and triple-negative, which are identified by the expression of hormone receptors and HER2 by breast cancer cells
  • Of note, these subtypes have different biologic features, prognosis, and response to treatment
  • Although all breast cancers may recur despite treatment, those defined as triple-negative breast cancer (TNBC), which lack specific targets for effective treatments, are considered high risk
  • Hence, up to 40% of early-stage breast cancer patients will experience recurrence after standard treatment
  • Tumors expressing hormone receptors (ie, estrogen and progesterone receptors) are defined as luminal-like, are typically less aggressive, and have a good prognosis
  • HER2-positive breast tumors are biologically aggressive tumors, but the outcome has dramatically improved with anti-HER2 targeted therapies
#Arrangoiz #BreastSurgeon #CancerSurgeon #SurgicalOncologist #MountSinaiMedicalCenter #MSMC #Miami #Mexico #BreastCancer

Adjuvant Endocrine Therapy for Breast Cancer

  • Several trials showed that extended adjuvant endocrine therapy beyond 5 years provides additional benefit in terms of reduction of disease recurrence
  • According to ASCO guidelines, all patients with node-positive disease should be offered 10 years of adjuvant ET
  • Guidelines from the European Society for Medical Oncology (ESMO) also note that 10 years of treatment is advantageous. Moreover, women with node-negative breast cancer may be offered extended adjuvant endocrine therapy for up to 10 years, on the basis of considerations of recurrence risk using established prognostic factors
  • Conversely, women with low-risk, node-negative tumors should notroutinely be offered extended therapy because the absolute reduction of recurrence risk is likely to be small in this category of patients
  • The ESMO notes that extended therapy should not be offered to those with a very low risk of relapse
  • Similarly, 5 years of ovarian function suppression with either tamoxifen or an aromatase inhibitor provides an additional benefit for this patient population. However, there is no evidence that continuing ovarian function suppression alone beyond 5 years provides additional benefit

Red Flags for Breast Cancer

  • Although most breast cancers do not present with any symptom and are diagnosed through screening mammograms, breast cancer may present with different signs and symptoms, including breast lumps, nipple inversion and discharge, and peau d’orange
  • Signs in palpable lumps that should raise concern include focal nodularity, hardness, irregularity, and asymmetry with the other breast
#Arrangoiz #BreastSurgeon #CancerSurgeon #SurgicalOncologist #Miami #Mexico #BreastCancer #MountSinaiMedicalCenter #MSMC #Doctor

Treatment of Early Stage Hormone Receptor Positive Breast Cancer

  • Treatment strategies for early-stage hormone receptor positive / human epidermal receptor 2 negative (HR+/HER2-) breast cancer comprise definitive local therapy (primary surgical management of the breast and axilla with or without adjuvant radiation), and adjuvant endocrine therapy with or without chemotherapy
  • Nearly all patients with early-stage, HR+ breast cancers should be considered as candidates for adjuvant endocrine therapy
  • Conversely, adjuvant chemotherapy is considered only in a subgroup of patients with HR+/HER2- early breast cancer, based on the predicted risk for recurrence; the expected benefit from chemotherapy; and patient-specific factors, such as comorbidities.
  • In very select cases, neoadjuvant endocrine therapy or chemotherapy may be an option for patients with early-stage HR+ disease prior to surgery.

Breast Cancer

  • Approximately 70% to 80% of all breast cancers are hormone receptor–positive (HR+), with tumor cells expressing either the estrogen receptor (ER), progesterone receptor (PR), or both.
  • Testing for human epidermal growth receptor 2 (HER2) protein overexpression and / or HER2 gene amplification is undertaken at diagnosis to guide treatment decisions
  • More than 80% of HR+ tumors are HER2-negative (HER2-) so that HR+/HER2- breast cancer is the most common subtype of invasive breast cancer
  • Adjuvant therapy for breast cancer aims to treat micrometastatic disease
  • A cornerstone of treatment for HR+/HER2- breast cancer is adjuvant endocrine therapy (eg, aromatase inhibitors and/or tamoxifen with or without ovarian suppression).
##Arrangoiz #BreastSurgeon

Cyclin Dependent Kinase 4/6 Inhibitors in Early Breast Cancer

  • Cyclin-dependent kinase 4 / 6 (CDK4/6) inhibitors have become integral to the treatment of HR+ / HER2- breast cancer
  • Approved in 2015 for use in the metastatic setting and most recently in the adjuvant setting, CDK 4 / 6 inhibitors have revolutionized treatment in both endocrine-sensitive and endocrine-resistant settings and in premenopausal and postmenopausal women
  • Many questions remain regarding the optimal use of these medications in clinical practice.
  • The three main studies that looked at the role of adjuvant CDK 4 / 6 inhibitors, including the PALLAS and PENELOPE-B trials, in which palbociclib showed no benefit in invasive disease-free survival
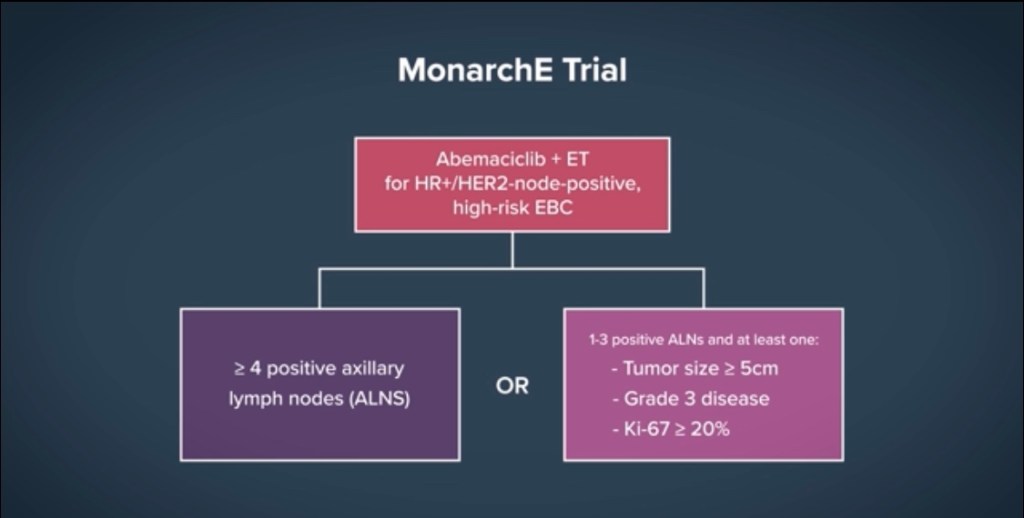
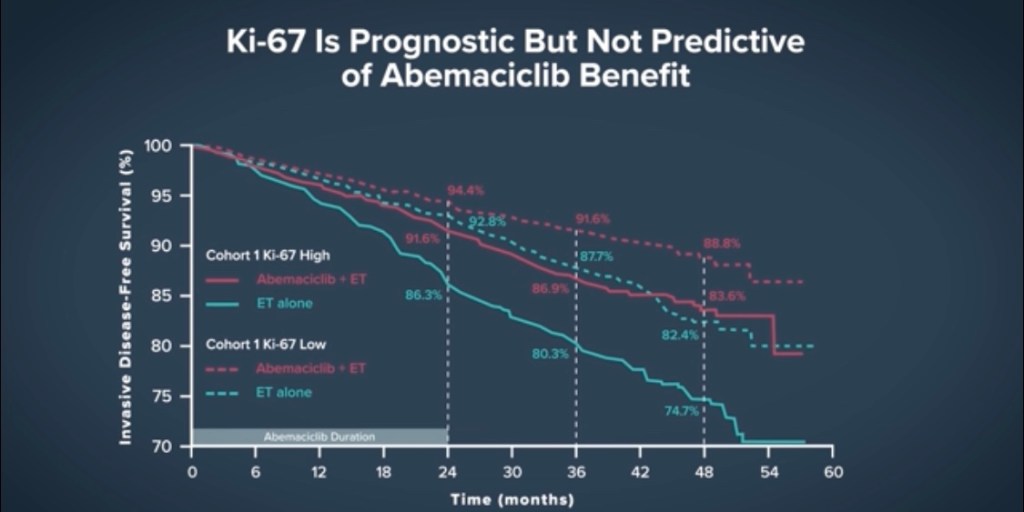
  • In contrast, in the monarchE trial, abemaciclib showed a robust benefit in preventing recurrence, which was sustained after longer follow-up, as reported at the San Antonio Breast Cancer Symposium 2022
Breast Cancer Risk Assessment and Screening
Key Takeaways in Early Breast Cancer From AACR 2023
Metastatic Breast Cancer: A Review of 3 Cases and Palliative Care

Treatment of Non Metastatic Triple Negative Breast Cancer (TNBC) Equal or Greater Than 0.5 cm in Size

  • The neoadjuvant or adjuvant chemotherapy options for patients with TNBC:
    • Are similar to the approaches used in other breast cancer phenotypes
    • The principles for the surgical management of and radiation therapy options for breast cancer are also applied in a similar way across breast cancer subtypes
  • Tumors equal or greater than 0.5 cm:
    • Chemotherapy:
      • Chemotherapy is recommended for women with:
        • TNBC equal or greater than 0.5 cm or with node-positive TNBC (regardless of tumor size):
          • These patients have a higher risk of relapse compared with other breast cancer phenotypes and are not candidates for other forms of targeted therapy (ie, HER2-directed treatment or endocrine therapy)
    • Neoadjuvant versus adjuvant administration:
      • Neoadjuvant chemotherapy (NACT) is the preferable approach in patients with:
        • Locally advanced breast cancer or for those who are not candidates for or unlikely to have a good cosmetic outcome with breast conservation
      • For patients receiving NACT:
        • Pathologic complete response:
          • Is associated with improvement in disease-free survival (DFS)
      • Additionally, patients with smaller (eg, T1c) TNBCs:
        • May be offered neoadjuvant therapy:
          • Particularly if they might be candidates for additional treatments in the adjuvant setting if residual disease is identified
      • Benefits:
        • Stage for stage, there is a larger absolute benefit to adjuvant chemotherapy among patients with TNBC compared with those with hormone-positive diseas:
          • In an analysis of three randomized trials that involved a total of 6644 women with node-positive breast cancer, compared with those with ER-positive breast cancer, patients with ER-negative breast cancer:
            • Had the following significant outcomes at five years following adjuvant chemotherapy:
              • A larger reduction in the risk of recurrence:
                • 55% versus 26%:
                  • This translated into a higher absolute improvement in DFS:
                    • 23% versus 7%
              • A larger reduction in the risk of death:
                • 55% versus 23%:
                  • This translated into a higher absolute improvement in overall survival (OS):
                    • 17% vs 4%
                • These data emphasize the importance of neoadjuvant chemotherapy for women with TNBC:
                  • Who (unlike those with ER-positive or HER2-positive breast cancer) are not eligible for targeted therapies
  • Choice of regimen:
    • Preferred regimen:
      • Anthracycline-, alkylator-, and taxane-based chemotherapy regimens remain the standard regimens for TNBC:
        • For example, dose-dense doxorubicin and cyclophosphamide followed by paclitaxel (AC-T)
      • Taxanes have significant activity in the treatment of TNBC:
        • There are no meaningful data regarding regimens lacking alkylator-based therapy:
          • As an example of the benefits of a taxane:
            • In the GEICAM 9906 trial of adjuvant fluorouracil, epirubicin and cyclophosphamide (FEC) versus FEC followed by paclitaxel:
              • The addition of paclitaxel was associated with an improvement in DFS at seven years:
                • 74% vs 56%
          • The ABC trials:
            • Tested anthracycline / taxane-based regimens versus docetaxel and cyclophosphamide (TC) given for the same duration:
              • Finding a benefit overall for incorporation of the anthracycline:
                • Particularly in TNBC in subset analysis:
                  • However, the absolute benefit in node-negative TNBC appears modest
  • Non-anthracycline-based regimens:
    • Are an appropriate alternative for patients with lower-risk TNBC:
      • Node-negative
      • Less than 1 cm
      • Those with cardiac risk factors
      • Those who prefer to avoid the risks associated with anthracyclines
    • TC:
      • Is an alternative in low-risk disease
        • For example, in a randomized trial of nearly 650 patients with operable TNBC:
          • Those assigned to six cycles of adjuvant paclitaxel and carboplatin (administered on days 1, 8, and 15 every 28 days):
            • Had a longer DFS relative to those assigned to an anthracycline and taxane based regimen:
              • Five-year DFS 87% vs 80%:
                • With similar OS
    • Is there a role for an antimetabolite agent?
      • For patients with stage II or III TNBC, neoadjuvant regimens such as AC-T or TC are standard:
        • Followed by capecitabine for those with residual disease:
          • Given results of a randomized trial showing an OS benefit with the adjuvant addition of capecitabine when residual disease is present:
            • However, for patients with stage I disease, adjuvant rather than neoadjuvant treatment is appropriate:
              • Using standard regimens such as AC-T or TC
      • In general, for patients who have not received neoadjuvant chemotherapy:
        • Adding antimetabolite agents such as capecitabine or gemcitabine to adjuvant chemotherapy:
          • Has not improved OS outcomes in TNBC
            • A Chinese trial demonstrated improvement in DFS, but not OS, with capecitabine following standard adjuvant regimens:
              • Among 434 women with early-stage TNBC who received standard adjuvant treatment (94% of whom had not received neoadjuvant therapy):
                • Low-dose capecitabine maintenance therapy for one year improved five-year DFS compared with observation only:
                  • 83% versus 73%; hazard ratio [HR] 0.64, 95% CI 0.42-0.95)
                • The five-year OS was similar between the groups:
                  • 86% vs 81%:
                    • With and without capecitabine, respectively; HR 0.75, 95% CI 0.47-1.19)
                • The trial had important limitations; notably, there was an imbalance in randomization, with a higher proportion of older women assigned to placebo, which could have favored the capecitabine group
      • In a separate phase III trial of 876 women with early-stage TNBC who had received standard adjuvant chemotherapy:
        • Subsequent treatment with capecitabine versus placebo resulted in numerically:
          • But not statistically, improved five-year DFS and OS (DFS, 80% versus 77%, HR 0.79, 95% CI 0.61-1.03; OS, 86.2% versus 85.9% , HR 0.92, 95% CI 0.66-1.28)
        • Similarly, trials looking at adjuvant gemcitabine have proven negative.
    • Given the sum of data, most medical oncologist opt for standard anthracycline- and/or taxane-based chemotherapy regimens as adjuvant therapy in patients with TNBC who have not received neoadjuvant treatment:
      • As discussed, in practice, only lower-risk patients (ie, stage I TNBC) are treated with adjuvant rather than neoadjuvant chemotherapy:
        • As most patients with higher-risk disease receive neoadjuvant therapy
  • Is there a role for platinums?
    • There is controversy as to whether adding platinum-based chemotherapy should be “standard” in stage II or III TNBC:
      • Trials have shown that adding platinum-based chemotherapy to neoadjuvant regimens can improve the rate of complete pathologic response:
        • However, to date, this has not improved OS in women also receiving anthracycline-, alkylator-, and taxane-based treatment
  • PARP inhibitors for BRCA carriers:
    • The poly(ADP-ribose) polymerase (PARP) inhibitor olaparib:
      • Has regulatory approval by the US Food and Drug Administration for the adjuvant treatment of adult patients with deleterious or suspected deleterious germline breast cancer susceptibility gene (BRCA)-mutated, HER2-negative, high-risk early breast cancer:
        • Who have been treated with neoadjuvant or adjuvant chemotherapy
  • Is there a role for immunotherapy?
    • Pembrolizumab has regulatory approval with chemotherapy for the neoadjuvant treatment of patients with high-risk, early-stage TNBC
#Arrangoiz #BreastSurgeon #CancerSurgeon #SurgicalOncologist #MountSinaiMedical #MSMC #Miami #Mexico #BreastCancer #TripleNegativeBreastCancer

Diagnosis and Staging of Triple Negative Breast Cancer (TNBC)

  • Diagnosis:
    • Triple-negative means cancers that have less than 1 percent expression of ER and PR as determined by immunohistochemistry (IHC), and that are either 0 to 1+ by IHC, or IHC 2+ and fluorescence in situ hybridization (FISH)-negative (not amplified):
      • According to American Society of Clinical Oncology / College of American Pathologists (ASCO/CAP) guidelines
  • Receptor testing and the cut-offs used to determine ER, PR, and HER2 statuses:
    • Were developed to determine the odds of response to endocrine and HER2-directed therapy, respectively:
      • They were not developed to distinguish a distinct biologic subtype of breast cancer:
        • Such as the “triple-negative” phenotype
  • In support of this definition of ER and PR receptor-negative status:
    • An analysis of cooperative group studies with centrally determined ER, PR, and molecular subtype suggests that this group is molecularly heterogeneous, including both luminal and nonluminal subtypes
  • Staging:
    • The clinical staging of breast cancer is identical across breast cancer subtypes using the American Joint Committee on Cancer and the International Union for Cancer Control (AJCC-UICC) Tumor, Node, Metastasis (TNM) breast cancer staging system
#Arrangoiz #BreastSurgeon #CancerSurgeon #SurgicalOncologist #MountSinaiMedical #MSMC #Miami #Mexico #BreastCancer #TripleNegativeBreastCancer