Blog

Oral Paclitaxel, Carboplatin, and Dostarlimab Demonstrates Efficacy With Manageable Safety in Triple-Negative Breast Cancer

  • The phase 2 I-SPY2 trial:
    • Is the first to study combination therapy with:
      • Oral paclitaxel, carboplatin, and the PD-1 inhibitor dostarlimab in early triple-negative breast cancer
    • Among 56 patients with triple-negative breast cancer:
      • This combination therapy was found to be safe and moderately effective:
        • Demonstrating an estimated pathologic complete response rate of 48%
    • Results are preliminary:
      • Further investigation is needed before implementing in clinical practice
  • The phase 2 I-SPY2 trial found that patients with triple-negative breast cancer:
    • Who received the novel combination of oral paclitaxel, carboplatin, and the PD-1 inhibitor dostarlimab:
      • Demonstrated a higher predicted pathologic complete response (pCR) than control participants
      • Furthermore, drug-related adverse events from the novel combination treatment were manageable
      • I-SPY2 is the first trial to study combination therapy with oral paclitaxel, carboplatin, and the PD-1 inhibitor dostarlimab in early triple-negative breast cancer
  • The findings show that oral paclitaxel, carboplatin, and dostarlimab:
    • Can be effective in triple-negative breast cancer:
      • Although the estimated pCR rate of 48% is not as high as we anticipated for a triplet-therapy combination that includes a taxane, platinum chemotherapy, and an immune checkpoint inhibitor in this subgroup:
        • It may not be ideal to use these as a combination in this setting until further investigation into a larger cohort of patients
  • Optimizing Oral Chemotherap:
    • Intravenous (IV) taxane therapy, including with paclitaxel:
      • Is highly effective in high-risk breast cancer
    • To date, oral paclitaxel in combination with other treatments, such as immunotherapy:
      • Has yet to demonstrate similar benefits as the IV formulation but could represent a desirable treatment option that allows patients to use at-home administration and avoid needle sticks:
      • There are also some favorable side-effect profiles of oral paclitaxel compared to IV paclitaxel:
        • Less peripheral neuropathy and alopecia:
          • Which can impact quality of life
  • Findings from a recent phase 3, head-to-head comparison of oral paclitaxel with IV paclitaxel have opened the door to new questions about whether an oral formulation can be optimized in combination with other treatments:
    • In that study, investigators observed a higher confirmed tumor response with oral paclitaxel and a numerically (although not statistically) higher progression-free and overall survival than with IV paclitaxel
    • In the phase 3 trial that compared oral paclitaxel to IV paclitaxel:
      • The overall risk–benefit ratio of oral paclitaxel over IV paclitaxel was questionable:
        • The U.S. Food and Drug Administration [FDA] did not approve oral paclitaxel due to concerns regarding 19-week objective response rate per blinded independent central review, where a reread of data may have brought on unmeasured bias
        • In addition, FDA cited febrile neutropenia as a safety concern
  • In the I-SPY2 study, compared with IV paclitaxel:
    • Oral paclitaxel caused less peripheral neuropathy;
      • But led to increased rates of nausea, diarrhea, neutropenia, anemia, and urinary tract infections
  • In an effort to identify optimal treatment options, the ongoing I-SPY2 trial is investigating the efficacy of several experimental therapies for early-stage breast cancer with a high risk of recurrence, including a combination treatment featuring oral paclitaxel
  • Multiple investigational arms are assessed in parallel, using neoadjuvant chemotherapy plus an investigational drug (the treatment arm) versus neoadjuvant chemotherapy alone (the control arm):
    • The primary endpoint is pCR
  • Biomarker assessments performed at baseline are used to classify patients into 1 of 10 predefined signature subtypes:
    • Based on hormone receptor (HR), erbB-2 receptor, and MammaPrint status
    • Adaptative randomization in I-SPY2 preferentially assigns patients to new or standard regimens based on Bayesian predictive probabilities of rates of pCR for each subtype
    • Regimens that demonstrate a high predictive probability of being statistically superior to standard treatment in at least 1 of 10 predefined signatures in a hypothetical phase 3 confirmatory trial “graduate” from the study
  • In the analysis women with early-stage breast cancer:
    • Considered high risk based on HR, erbB-2 receptor, and MammaPrint status were randomly assigned to the control group or experimental treatment
    • The experimental arm received oral paclitaxel plus encequidar (which is required for the body to absorb oral paclitaxel) followed by carboplatin and dostarlimab and then chemotherapy with doxorubicin / cyclophosphamide
    • The control arm received paclitaxel plus doxorubicin /cyclophosphamide
    • Patients with HER2-positive disease also received trastuzumab during the first 12 weeks of the study
    • In the 106 randomly assigned patients, 44 had HR-positive/HER2-negative disease, 56 had triple-negative breast cancer, and 6 had HER2-positive breast cancer
    • Among the 10 predefined biomarker signatures in which the treatment regimen was assessed, it was most successful in the triple-negative signature:
      • In this group, the treatment had a predicted pCR of 48% versus 29% in the control arm, causing the experimental treatment to “graduate” from the study:
        • This is the first study to combine an oral taxane with an immune checkpoint inhibitor
        • It demonstrated that the combination of oral chemotherapy and dostarlimab is safe and feasible
        • The combination of chemotherapy and dostarlimab can be potentially effective in triple-negative breast cancer
        • The effectiveness of oral paclitaxel plus encequidar was comparable to that of IV paclitaxel and with lower rates of neuropathy and alopecia than with the IV treatment:
          • Suggesting this oral agent may be an attractive alternative to IV paclitaxel to be used as single agent
#Arrangoiz #BreastSurgeon #CancerSurgeon #SurgicalOncologist #MountSinaiMedicalCenter #MSMC #Miami #Mexico

Comparison of TPF Induction and CCRT with CCRT alone

  • Several phase 3 trials were conducted between 2015 and 2017:
    • Which directly compared taxane-based induction chemotherapy (IC) with concurrent chemoradiation (CCRT):
      • On groups of unselected locally advanced head and neck cancer (LAHNC):
        • Most of IC protocols were followed by CCRT:
          • But one trial had RT combined by targeted therapy
  • The first of this list includes the multi-center PARADIGM trial:
    • That considered high-risk patients with high nodal load
    • A hundred and forty-five patients were randomized to either be treated with CCRT with 2 cycles of 100 mg/m2 cisplatin or 3 cycles of TPF followed by CCRT with weekly carboplatin for good responders or weekly docetaxel for the rest
    • No significant differences in progression free survival (PFS) or overall survival (OS) were detected between groups
    • Unexpectedly, both groups were advantaged with good survival results:
      • 3 year overall survival (OS) 73% (95% CI 60–86) in IC, vs. 78% (66−86) in CCRT (Haddad et al., 2013)
  • A second trial, DeCide:
    • Used CCRT in both arms with 2 cycles of induction with TPF in the experimental arm
    • Here, 285 patients were recruited and randomized
    • Cancer deaths and distant metastases were reduced with induction:
      • But serious adverse events and non-cancer related deaths increased
    • As well, none of the survival measures improved with IC
    • Similar to the PARADIGM trial:
      • Mean OS was higher than predicted in both groups, and patients were prescribed with an unconventional regimen (including fluorouracil, docetaxel, and hydroxyurea)
    • Moreover, both mentioned trials were disadvantaged for being underpowered:
      • 200 were planned for PARADIGM and 400 for DeCide (Cohen et al., 2014)
  • The 3-armed Spanish TTCC trial:
    • Was the first well-designed study to compare:
      • TPF-CCRT, PF-CCRT, and CCRT, with standard high-dose cisplatin combined with RT
    • The trial reached its accrual goals and 439 patients were analyzed
    • The results did show a trend of higher PFS, in favor of induction over CCRT:
      • But only as a result of per-protocol analysis:
        • In fact 27% of patients in the TPF arm did not receive the treatment as scheduled:
          • Likewise, intention to treat analysis showed no PFS advantage in any group (logrank P = 0.56) (Hitt et al., 2014)
          • Moreover, in a follow-up study, OS, PFS, and TTF were neither significantly different when intention to treat analysis compared TPF followed by CCRT with CCRT alone (Hitt et al., 2021 Apr)
  • The GORTEC 2007–02 trial:
    • Examined TPF induction followed by cetuximab with RT in comparison to CCRT with 3 cycles of carboplatin and fluorouracil on 370 LAHNC patients
    • Similar to DeCide, there was a decrease in distant metastases in the TPF arm:
      • Though the documented response rate was poor (45%), and both PFS and OS were almost identical in the two groups
    • Nevertheless, the concerning effect was that the rate of early deaths was as high as 6.6% (Geoffrois et al., 2016)
  • The Italian GSTTC:
    • A primarily phase 2 (and 3) study with a 2 × 2 factorial design:
      • Evaluated CCRT with cisplatin (cumulative dose of 160 mg/m2) and 5-FU (800 mg/m2/ 96 h) or cetuximab with or without a modified TPF (docetaxel 75 and cisplatin 80 mg/m2 day 1 and 5-fluorouracil 800 mg/m2/day 96-h) induction
      • Among 414 patents over half were oropharyngeal cases, and most patients had excellent performances (79% ECOG 0 and the rest 1)
      • Outcomes were far better with IC with a median OS of 54.7 vs. 31.7 months in favor of IC and a significantly higher PFS (median 29.7 months vs. 18.5, HR 0.72; 95% CI 0.56–0.93; p = 0.013) and OS (HR 0.74; 95% CI 0.56–0.97; p = 0.031)
      • The results of TPF followed by CCRT versus CCRT alone:
        • Was not significantly different:
          • While the comparison of TPF followed by cetuximab and RT showed to be superior to cetuximab and RT alone
      • Furthermore, compliance with IC was high, as 93% of patients were able to receive the planned 3 cycles of TPF, and early deaths were 1%
      • This was a unique trial that showed OS benefit for IC but likely because of the good prognose of the subjects
#Arrangoiz #HeadandNeckSurgeon #CancerSurgeon #SurgicalOncologist #MountSinaiMedicalCenter #MSCM #Miami #Mexico #HeadandNeckCancer

Inflammatory Breast Cancer

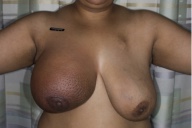
  • Inflammatory breast cancer (IBC):
    • Is a clinical diagnosis defined by the American Joint Committee on Cancer as a:
      • Diffuse erythema and edema involving approximately a third or more of the skin of the breast:
        • It is staged cT4d
    • A punch biopsy of the skin:
      • Demonstrates tumor emboli within dermal lymphatics:
        • Approximately 75% of the time
      • A negative skin biopsy does NOT preclude the diagnosis:
        • As it is clinical
    • The appearance may lead to misdiagnosis of mastitis or breast cellulitis
    • The rapid evolution of symptoms (within 3 to 6 months):
      • Distinguishes IBC from a locally advanced breast cancer with associated edema
  • IBC is rare:
    • Present in 2% to 4% of breast cancer patients:
      • Although the reported annual incidence has been increasing
    • The tumor biology is disproportionately ER negative and HER2 amplified, compared with non-IBC
  • Patients should be evaluated in a multidisciplinary setting for trimodal therapy:
    • Treatment should be initiated with neoadjuvant chemotherapy:
      • Followed by aggressive local therapy
    • The majority of patients with IBC:
      • Present with clinical lymph node involvement
    • Sentinel lymph node biopsy is not reliable in IBC:
      • Due to blockage of dermal lymphatics:
        • Thus axillary dissection should be performed
    • Following neoadjuvant chemotherapy:
      • Modified radical mastectomy is the appropriate surgery:
        • Skin should not be spared:
          • So as not to leave behind residual disease:
            • Immediate reconstruction should be avoided
      • Patients should receive post-mastectomy radiation to the skin, chest wall, and regional lymph nodes following surgery to optimize local control
  • Survival in IBC has improved with trimodal therapy:
    • A recent analysis of Surveillance, Epidemiology, and End Results data:
      • Evaluated 10,197 patients with non-metastatic IBC between 1998 and 2010
      • Patients who underwent trimodal therapy had improved 5- and 10-year survival:
        • 55.4% and 37.3% over those that did not receive all 3 modalities
      • Survival was lowest at 10 years (16.5%) for patients who underwent surgery alone
  • References
    • Amin MB, Edge S, Greene F, et al., eds. AJCC Cancer Staging Manual. 8th ed. New York, NY: Springer; 2017
    • Hance KW, Anderson WF, Devesa SS, Young HA, Levine PH. Trends in inflammatory breast carcinoma incidence and survival: the surveillance, epidemiology, and end results program at the National Cancer Institute. J Natl Cancer Inst 2005;97(13):966-975.
    • NCCN clinical practice guidelines in oncology. National Comprehensive Cancer Network. www.nccn.org/professionals/physician_gls/f_guidelines.asp. Accessed August 25, 2019.
    • Menta A, Fouad TM, Lucci A, et al. Inflammatory breast cancer: what to know about this unique, aggressive breast cancer. Surg Clin North Am. 2018;98(4):787-800.
    • Rueth NM, Lin HY, Bedrosian I, et al: Underuse of trimodality treatment affects survival for patients with inflammatory breast cancer: an analysis of treatment and survival trends from the National Cancer Database. J Clin Oncol. 2014;32(19):2018-2024.
#Arrangoiz #BreastCancer #BreastSurgeon #SurgicalOncologist #MountSinaiMedicalCenter #MSMC #Miami #Mexico #InflammatoryBreastCancer

The Meta-Analysis of Chemotherapy in Head and Neck Cancer (MACH-NC) Study

  • The Meta-Analysis of Chemotherapy in Head and Neck Cancer (MACH-NC):
    • Is an individual patient data analysis intended to evaluate the role of chemotherapy in head and neck cancers
    • It is known for its rigorous process for quality data collection and its large ongoing data- base
    • Results of indirect comparisons were not limited to evaluation of survival advantage:
      • But an estimate of the interaction between the treatment effects and the timing of chemotherapy as adjuvant, concurrent, neoadjuvant, or induction was made possible (Pignon and Bourhis, 1995 Oct)
    • Since the first reports of MACH-NC:
      • Results demonstrated an:
        • 8.6% benefit of cause-specific survival (CSS) at 5 years, hazard ratio, 0.81; 95% CI, 0.78–0.86; P = 0.001):
          • For concurrent chemoradiation (CCRT):
            • While systemic chemotherapy in the setting of induction or adjuvant did not show OS advantage
        • Nevertheless, the magnitude of the overall response rate of induction chemotherapy (IC) with the PF regimen (cisplatin 100 mg/m2 on day 1 and 5-fluorouracil 1000 mg/m2 daily for 5 days):
          • Was high and ranged from 57% to 80%, with a complete response rate of 19% to 48%
        • Analyses on the subset of 15 trials who received PF:
          • Showed a modest improvement in OS compared to CCRT (HR, 0.90; 95% CI, 0.82–0.99):
            • Which is a survival gain equal to 5% at 5 years
        • In the MACH-NC a subset analysis of 16 IC trials with non-PF combinations:
          • Did not show survival benefit with these IC regimens:
            • Which is attributed to the low dose of ineffective regimens that were administered for a duration not long enough:
              • Here, PF showed more adequate responses in comparison with non-PF trials:
                • Which reflects the nature of PF as a more potent drug combination for the most common administered schedules (Pignon et al., 2009; Monnerat et al., 2002):
                  • So, in particular PF became the dominant induction regimen for years
#Arrangoiz #HeadandNeckSurgeon #CancerSurgeon #SurgicalOncologist #MountSinaiMedicalCenter #MSCM #Miami #Mexico #HeadandNeckCancer

Surgical Management of the Axillary in Breast Cancer Patients Over 70 Years of Age

  • The standard of care with respect to surgical management of early stage breast cancer with a clinically negative axilla:
    • Is to undergo axillary staging with sentinel lymph node biopsy (SLNB)
  • In patients who are clinically node negative undergoing lumpectomy with SLNM and SLNB:
    • A completion axillary lymph node dissection (ALND) is not required if one or two lymph nodes are positive:
      • These patients should go on to receive adjuvant therapy:
        • Omission of ALND does not lead to a difference in 10-year locoregional recurrence or overall survival
    • There is, however, a role for omission of axillary staging in elderly women:
      • Who are clinically node negative with ER+ tumors:
        • Particularly if co-morbidities are present
    • The Cancer and Leukemia Group B (CALBG) 9343 study:
      • Evaluated women ≥ 70 years of age who underwent lumpectomy:
        • For clinical T1, N0, ER+ breast cancer +/- adjuvant radiation (RT):
          • With tamoxifen (Tam) recommended for all patients
      • Of the 636 participants:
        • 404 (64%) did not undergo any initial axillary surgery
      • At 12-year follow-up:
        • There were no axillary recurrences among women who underwent initial axillary dissection
        • Among those who did not undergo axillary dissection:
          • There were no axillary recurrences:
            • In the Tam + RT group
          • Six of 200 in the Tam group (3%) had axillary recurrences
    • The International Breast Cancer Study Group Trial 10-93:
      • Evaluated 473 patients with early stage breast cancer who were clinically node negative
      • Patients had a mean age of 74
      • The majority of patients were ER+, and patients were randomized to breast surgery +/- axillary dissection followed by endocrine therapy
      • Overall, 2% of patients had an axillary recurrence (1% of those with axillary surgery vs. 3% in patients without axillary surgery):
        • With no difference in disease-free and overall survival.
  • Results from these and other studies recently led the Society of Surgical Oncology to release the Choosing Wisely guidelines:
    • Recommending against routine use of SLNB in clinically node-negative women ≥70 years of age with hormone positive cancer:
    • Hormonal therapy is typically recommended for patients with hormone receptor positive disease
    • Omission of SLNB in clinically node-negative women ≥70 years of age treated with hormonal therapy does not result in a significantly increased rate of locoregional recurrence and does not impact breast cancer mortality:
      • Thus, although axillary staging with SLNB continues to be the standard of care:
        • Omission of axillary staging can be considered in some patients ≥70 years of age with:
          • Early stage, clinically node-negative, hormone receptor positive breast cancer
  • References
    • Giuliano AE, Ballman K, McCall L, et al. Locoregional recurrence after sentinel lymph node dissection with or without axillary dissection in patients with sentinel lymph node metastases: long-term follow-up from the American College of Surgeons Oncology Group (Alliance) ACOSOG Z0011 randomized trial. Ann Surg. 2016;264(3):413-420.
    • Giuliano AE, Ballman KV, McCall L, et al. Effect of axillary dissection vs no axillary dissection on 10-year overall survival among women with invasive breast cancer and sentinel node metastasis: the ACOSOG Z0011 (Alliance) Randomized Clinical Trial. JAMA. 2017;318(10):918-926.
    • Hughes KS, Schnaper LA, Bellon JR, et al. Lumpectomy plus tamoxifen with or without irradiation in women age 70 years or older with early breast cancer: long-term follow-up of CALGB 9343. J Clin Oncol. 2013;31(19):2382-2387.
    • International Breast Cancer Study Group: Randomized trial comparing axillary clearance versus no axillary clearance in older patients with breast cancer: first results of International Breast Cancer Study Group Trial 10-93. J Clin Oncol.2006;24(3):337-344.
    • Society of Surgical Oncology. Five things physicians and patients should question. Choosing Wisely website. Released July 12, 2016; updated June 20, 2019. http://www.choosingwisely.org/societies/society-of-surgical-oncology. Accessed August 25, 2019.
#Arrangoiz #BreastSurgeon #CancerSurgeon #SurgicalOncologist #MountSinaiMedicalCenter #MSCM #Miami #Mexico #BreastCancer

Adverse Events in the OlympiA Trial

  • The most common advérese events (AE) observed in the olaparib arm during the OlympiA trial were:
    • Nausea, fatigue, anemia, and vomiting:
      • Most of which were of grade 1 or 2
  • At the updated analysis, no new safety signals were detected (including no new cases of acute myeloid leukemia or myelodysplastic syndrome)
#Arrangoiz #BreastSurgeon #CancerSurgeon #SurgicalOncologist #MountSinaiMedicalCenter #MSCM #Miami #Mexico #BreastCancer

CDK 4/6 Inhibitors in Metastatic Breast Cancer

  • Hormone receptor–positive, HER2 negative:
    • Is the most common breast cancer subtype
  • Endocrine therapy (used alone or in combination):
    • Has been a longstanding standard of care for hormone receptor–positive breast cancer:
      • In both the early and advanced stages
  • In more recent years, endocrine therapy combined with a CDK4/6 inhibitor:
    • Has become the first-line standard of care for most women with hormone receptor–positive, HER2 negative metastatic breast cancer (MBC)
  • Use of first-line endocrine therapy plus a CDK4/6 inhibitor is based on positive results from several clinical trials:
    • The hazard ratios for progression-free survival (PFS) were very similar in these trials
  • Recently, statistically significant improvements in overall survival were reported in multiple phase 3 studies of ribociclib plus endocrine therapy:
    • For example, the secondary end point of overall survival (OS) was met in the MONALEESA-2 study of ribociclib plus an aromatase inhibitor
    • Of note, at the second interim analysis of data from the phase 3 MONARCH-3 clinical trial of abemaciclib plus endocrine therapy, OS data remained immature (HR, 0.754; 95% CI, 0.584-0.974; P = 0.03)
    • The addition of palbociclib to letrozole in the PALOMA-2 study of did not yield a statistically significant benefit in terms of OS (HR, 0.956; 95% CI, 0.777–1.177):
      • PALOMA-2 study investigators noted that final OS data were missing for 13% in the experimental arm vs 21% in the control arm
#Arrangoiz #BreastSurgeon #CancerSurgeon #SurgicalOncologist #MountSinaiMedicalCenter #MSCM #Miami #Mexico #BreastCancer

MonarchE Trial In High Risk Early Breast Cancer III

  • At updated analysis, the safety findings were consistent with what had been reported previously:
    • Adverse events (AEs) associated with adjuvant abemaciclib are considered manageable and acceptable in this patient population
  • The most common AEs reported (≥ 20%) in the abemaciclib plus endocrine therapy arm and at least 2% higher than in the endocrine therapy–alone arm were:
    • Diarrhea, infections, neutropenia, fatigue, leukopenia, nausea, anemia, and headache
    • The most frequently reported (≥ 5%) grade 3 or 4 AEs were:
      • Neutropenia, leukopenia, diarrhea, and lymphopenia
    • Clinicians should be aware of the potential for certain rare, but serious, toxicities:
      • Venous thromboembolism
      • Interstitial lung disease / pneumonitis
#Arrangoiz #BreastSurgeon #CancerSurgeon #SurgicalOncologist #MountSinaiMedicalCenter #MSCM #Miami #Mexico #BreastCancer

Oncotype Dx Recurrence Score

  • For patients with early-stage breast cancer, gene expression assays can be used to determine the likelihood of recurrence and the potential benefit of adjuvant chemotherapy
  • For example, the Oncotype Dx assay, which is based on the expression profile of 21 genes, provides a score (ie, recurrence score) that is both prognostic and predictive of chemotherapy benefit
  • Node-negative tumors with a recurrence score of 0 to 10 have a very good prognosis, with a low rate of distant recurrence at 10 years
  • Conversely, tumors with a high recurrence score (> 25) have higher risk for recurrence and have been shown to benefit from chemotherapy in retrospective studies
  • In the TAILORx studies, postmenopausal patients with node-negative, HR+ early breast cancer and intermediate recurrence score (11 to 25) did not derive a significant benefit from chemotherapy, which is thus not recommended for this subgroup of patients
#Arrangoiz #BreastSurgeon #CancerSurgeon #SurgicalOncologist #Miami #Mexico #BreastCancer #MountSinaiMedicalCenter

Monarch E Trial In High Risk Early Breast Cancer

  • The addition of abemaciclib to adjuvant endocrine therapy:
    • Was evaluated in the phase 3 monarchE trial:
      • That enrolled patients with high-risk, early-stage breast cancer:
        • With high risk defined as:
          • ≥ 4 axillary nodes or
          • 1 to 3 axillary nodes with:
            • Grade 3 histology
            • A large primary tumor (equal or greater than 5 cm)
            • High Ki67 score:
              • Defined as ≥ 20%
      • At a median 27 months of follow up:
        • The addition of abemaciclib led to statistically significant improvements in:
          • Invasive disease-free survival (IDFS) (HR, 0.70; 95% CI, 0.59-0.82; nominal P < 0.0001)
          • Distant relapse-free survival (DRFS) (HR, 0.69; 95% CI, 0.57-0.83; nominal P < 0.0001)
        • These findings were consistent with those from earlier data analyses
        • A low Ki-67 level was prognostic of better outcome:
          • However, it was not predictive of benefit from abemaciclib in this study
      • Results from a prespecified overall survival (OS) interim analysis were presented at the 2022 San Antonio Breast Cancer Symposium:
        • All patients were no longer receiving abemaciclib at a median follow-up of 42 months
        • Invasive DFS and DRFS benefits were sustained beyond the treatment period
        • OS data remained immature at time of analysis (Table 1.1)

Table 1.1. Efficacy Results From the monarchE Study Presented at SABCS 2022

#Arrangoiz #BreastSurgeon #CancerSurgeon #SurgicalOncologist #MountSinaiMedicalCenter #MSCM #Miami #Mexico #BreastCancer