With HER2 negative breast cancer and residual disease after undergoing neoadjuvant chemotherapy:
To standard postsurgical treatment and capecitabine or placebo
The primary end point:
Was disease-free survival (DFS)
Secondary end points included:
Overall survival (OS)
DFS was longer in the capecitabine group than in the control group (placebo):
74.1% vs. 67.6% of the patients were alive and free from recurrence or second cancer at 5 years
Among patients with triple-negative disease:
DFS was 69.8% in the capecitabine group versus 56.1% in the control group
OS rate was 78.8% versus 70.3%
There is no role for tamoxifen or anastrozole in triple negative breast cancer
Residual disease after completion of neoadjuvant chemotherapy:
Is associated with worse outcomes
References
1. Masuda N, Lee SJ, Ohtani S, Im YH, Lee ES, Yokota I, et al. Adjuvant capecitabine for breast cancer after preoperative chemotherapy. N Eng J Med. 2017;376(22):2147-2159.
2. Symmans WF, Wei C, Gould R, Yu X, Zhang Y, Liu M, et al. Long-term prognostic risk after neoadjuvant chemotherapy associated with residual cancer burden and breast cancer subtype. J Clin Oncol. 2017;35(10):1049-1060.
The omission of adjuvant regional nodal irradiation did not appear to increase the risk for recurrence or death among patients with breast cancer whose disease converted from lymph node-positive to lymph node-negative after neoadjuvant chemotherapy, according to research presented at the 2023 San Antonio Breast Cancer Symposium
There is no standard of care in place for patients with breast cancer for whom neoadjuvant chemotherapy has eliminated lymph node involvement, the researchers explained
The researchers performed a phase 3 clinical trial of 1,641 patients with lymph-node positive, nonmetastatic breast cancer who were found to have no lymph node involvement after neoadjuvant chemotherapy and surgery
They randomly assigned patients to two different regimens:
One group was assigned to skip regional nodal irradiation after undergoing mastectomy or whole breast irradiation and breast-conserving surgery
The other group was assigned to continue with chest wall irradiation and regional nodal irradiation following mastectomy or whole-breast irradiation plus regional nodal irradiation and breast-conserving surgery
Median follow-up was 59.5 months, and patients were a median of 52 years old
Seventy-eight percent had experienced a complete breast pathological response
In the “no regional nodal irradiation group,” 91.8% of patients were invasive breast cancer-recurrence free at 5 years compared with 92.7% of those who did undergo regional nodal irradiation
In both groups, 93.4% of patients were reported to be distant-recurrence free at 5 years
Overall survival was 94% in patients who were assigned to skip regional nodal irradiation and 93.6% in those who did not skip the therapy, according to the researchers
The researchers are planning a longer-term follow-up to further examine their findings, and a 10-year analysis time point was reached this past year
There findings suggest that downstaging cancer-positive regional lymph nodes with neoadjuvant chemotherapy can allow some patients to skip adjuvant regional nodal irradiation without adversely affecting oncologic outcomes
Follow-up of patients for long-term outcomes continues
Reference:
Mamounas, E. Loco-regional irradiation in patients with biopsy-proven axillary node involvement at presentation who become pathologically node-negative after neoadjuvant chemotherapy: Primary outcomes of NRG Oncology/NSABP B-51/RTOG 1304. Abstract GS02-07. SABCS 2023
In women with hormone receptor positive (HR+), HER2-negative early breast cancer, the 21-gene signature score:
Provides prognostic information that is independent of clinicopathological features
A high score (on a scale of 0 to 100) indicates:
A higher rate of distant recurrence and is predictive of chemotherapy benefit
The prospective Trial Assigning Individualized Options for Treatment (TAILORx);
Showed that endocrine therapy alone was noninferior to adjuvant chemotherapy plus endocrine (chemoendocrine) therapy:
In women with HR+, HER2-negative, axillary node-negative breast cancer and a 21-gene recurrence score of 11 to 25
An exploratory analysis indicated some benefit of chemotherapy:
In women 50 years of age or younger who had a recurrence score of 16 to 25
In this analysis there was a small (~1.6%) chemotherapy benefit in distant disease-free survival for patients with recurrence score results from 16 to 20, and a modest (~6.5%) chemotherapy benefit for patients with recurrence score results from 21 to 25
References
1. Sparano JA, Gray RJ, Ravdin PM, Makower DF, Pritchard KI, Albain KS, et al. Clinical and genomic risk to guide the use of adjuvant therapy for breast cancer. New Engl J Med. 2019;380(25):2395-2405.
2. Sparano JA, Gray RJ, Makower DF, Pritchard KI, Albain KS, Hayes DF, et al. Adjuvant chemotherapy guided by a 21-gene expression assay in breast cancer. New Engl J Med. 2018;379(2):111-121.
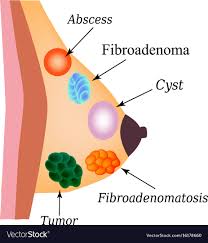
Fibroadenomas:Are benign, solid neoplasms of the breast:Consisting of fibroepithelial elements
Their size is hormonally influenced:As evidenced byfluctuation in size with the menstrual cycle and regression in postmenopausal women
Fibroadenomas are often solitary masses:But in approximately 25% of patients present with multiple lesion’s
They have a characteristic clinical presentation: Rubbery, mobile, and firm:Despite this, previous reports have indicated that diagnosis by clinical examination:Is accurate in only 50% to 75% of patient’s
One of the clinical dilemmas facing both surgeons and patients is the concern that the mass is something more ominous than a fibroadenoma:Both benign and malignant phylloides tumors may mimic fibroadenomas
Additionally, published reports have described adenocarcinoma and ductal carcinoma in situ:Arising within fibroadenomas or misdiagnosed as fibroadenomas
Because of the potential for more aggressive pathology masquerading as fibroadenomas:Management has been debated and recommendations changed several times in recent decades:Until the mid-1980s:Standard practice was excision of all fibroadenomas
Subsequent studies in the 1980s and 1990s:Demonstrated the safety of observing the presumed fibroadenomas:In women under age 35:Who had a fine-needle aspirate biopsy that did not contain malignant or suspicious cells
More recently, the question has been asked whether biopsy is even necessary:Smith and Burrows concluded:That patients under the age of 25 with benign ultrasound findings:Could be safely observed without a biopsy
Criteria for excision of suspected fibroadenomas of the breast: Patients with an age greater than 35 years
Immobile or poorly circumscribed mass
Size greater than 2.5 cm
Biopsy not definitive for fibroadenoma
Fibroadenomas:Son neoplasias benignas y sólidas de la mama que consisten en elementos fibroepiteliales.
Su tamaño está influenciado hormonalmente: Como lo demuestra la fluctuación en el tamaño con el ciclo menstrual y regresión en mujeres posmenopáusicas.
Los fibroadenomas son a menudo tumores solitarios: Pero en aproximadamente el 25% de los pacientes presentan lesiones múltiples
Tienen una presentación clínica característica: Gomoso, móvil y firme: A pesar de esto, informes anteriores han indicado que el diagnóstico mediante examen clínico: Es preciso en solo 50% a 75% de los pacientes
Uno de los dilemas clínicos que enfrentan los cirujanos y los pacientes es la preocupación de que la tumoración sea algo más siniestra que un fibroadenoma: Los tumores filoides benignos y malignos pueden simular fibroadenomas:Además, los informes publicados han descrito el adenocarcinoma y el carcinoma ductal in situ: Surgen dentro de fibroadenomas o se diagnostican erróneamente como fibroadenomas.
Debido al potencial de una patología más agresiva disfrazada de fibroadenomas: El manejo ha sido debatida y las recomendaciones cambiaron varias veces en las últimas décadas:Hasta mediados de la década de 1980: La práctica estándar fue la escisión de todos los fibroadenomas.
Estudios posteriores en las décadas de 1980 y 1990: Demostró la seguridad de observar los presuntos fibroadenomas: En mujeres menores de 35 años que tuvieron una biopsia por aspiración con aguja fina que no contenía células malignas o sospechosas
Más recientemente, se ha preguntado si la biopsia es necesaria: Smith y Burrows concluyeron: Que los pacientes menores de 25 años con hallazgos benignos de ultrasonido: Podría observarse con seguridad sin una biopsia.
In women with hormone receptor positive (HR+), HER2–negative early breast cancer:
A 21-gene signature assay provides prognostic information that is independent of clinicopathological features
A high score (on a scale of 0 to 100):
Indicates a higher rate of distant recurrence and is predictive of chemotherapy benefit
The prospective Trial Assigning Individualized Options for Treatment (TAILORx):
Showed that endocrine therapy alone was noninferior to adjuvant chemotherapy plus endocrine (chemoendocrine) therapy:
In women with HR+, HER2-negative, axillary node–negative breast cancer and a 21-gene recurrence score of 11 to 25
An exploratory analysis indicated:
Some benefit of chemotherapy in women 50 years of age or younger who had a recurrence score of 16 to 25
In this analysis there was a small (~1.6%) chemotherapy benefit in distant disease-free survival for patients with recurrence score results from 16 to 20, and a modest (~6.5%) chemotherapy benefit for patients with recurrence score results from 21 to 25
The TAILORx study:
This study showed a recurrence score between 11 to 25 predicts lack of benefit with adjuvant chemotherapy in women over 50 years of age
The level of clinical risk does not appear to predict benefit of chemotherapy
References
1. Sparano JA, Gray RJ, Ravdin PM, Makower DF, Pritchard KI, Albain KS, et al. Clinical and genomic risk to guide the use of adjuvant therapy for breast cancer. New Engl J Med. 2019;380(25):2395-2405.
2. Sparano JA, Gray RJ, Makower DF, Pritchard KI, Albain KS, Hayes DF, et al. Adjuvant chemotherapy guided by a 21-gene expression assay in breast cancer. New Engl J Med. 2018;379(2):111-121.
There are two main groups of diffuse breast cancers:
That present as large areas of architectural distortion on the mammogram:
One is neoductgenesis
The other is a diffusely infiltrating carcinoma:
Which makes up approximately 5% of all breast cancers
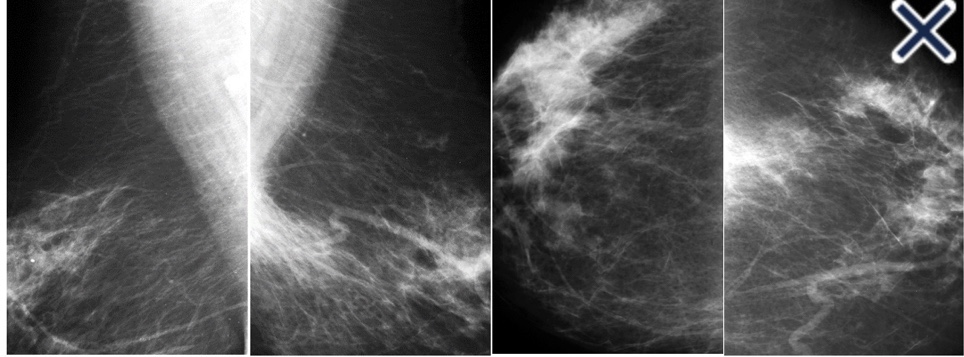
Bilateral diagnostic mammogram images
When the tumor is e-cadherin negative:
It is usually called invasive “lobular” carcinoma
When it is e-cadherin positive:
It is called infiltrating “ductal” carcinoma:
The designation based on e-cadherin staining is arbitrary:
Because the behavior of diffusely invasive carcinoma is the same regardless of the staining
Lacking calcifications and a central tumor mass:
These cancers are notoriously difficult to perceive on mammogram:
Even when they are large and palpable or when they occur in fatty involuted breasts:
However, the associated connective tissue response:
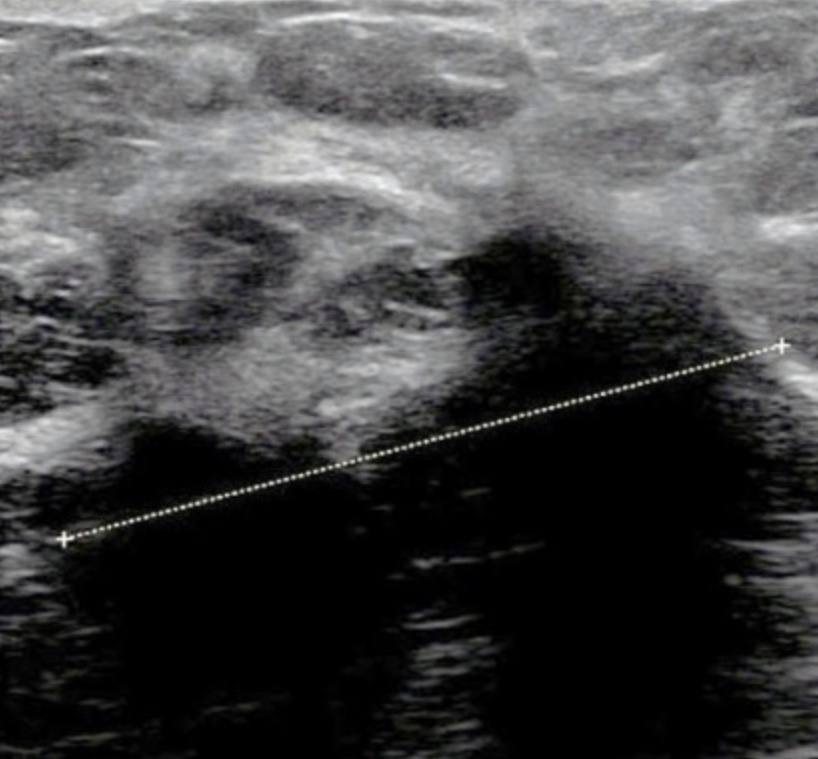
Makes this type of cancer quite visible with ultrasound
Hand-held ultrasound image
In contrast to diffusely infiltrating cancers:
Circular (Image) and spiculated (Image) tumors arising in the terminal ductal lobular units (TDLU):
Have bulging, convex contours protruding into the adipose tissue
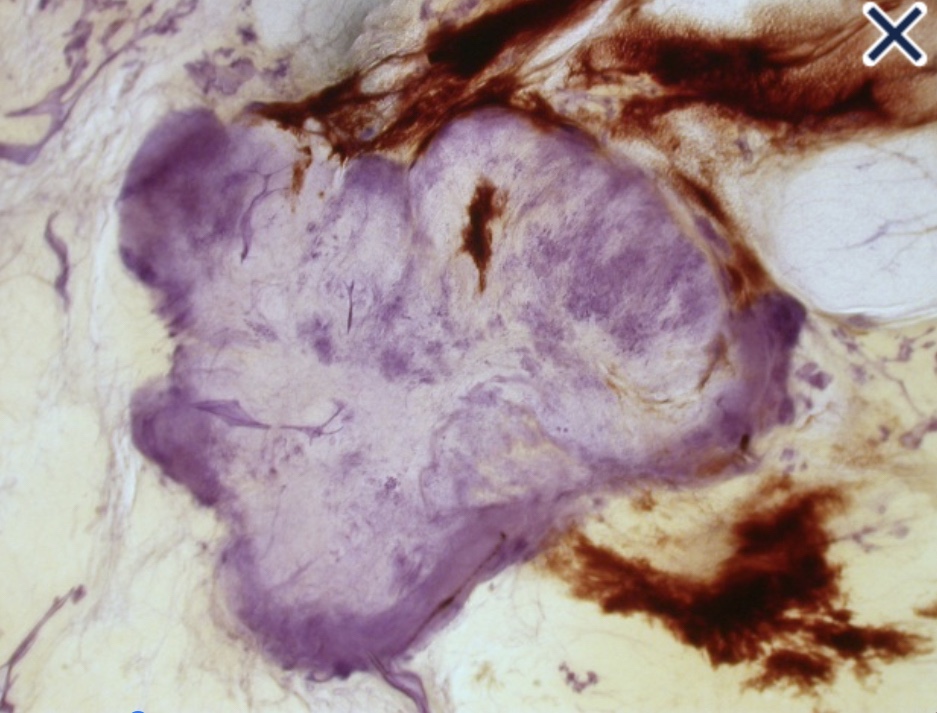
Lobulated spherical tumor massMultifocal stellate invasive breast cancer
The solid variety of infiltrating lobular carcinoma:
Most probably arises within the TDLU and has a circular / oval shape on breast imaging
There are two other variants of invasive lobular carcinoma that arise in the TDLUs:
The tubulolobular variant:
Is either a unifocal or multifocal spiculated lesion on the mammogram (Image)
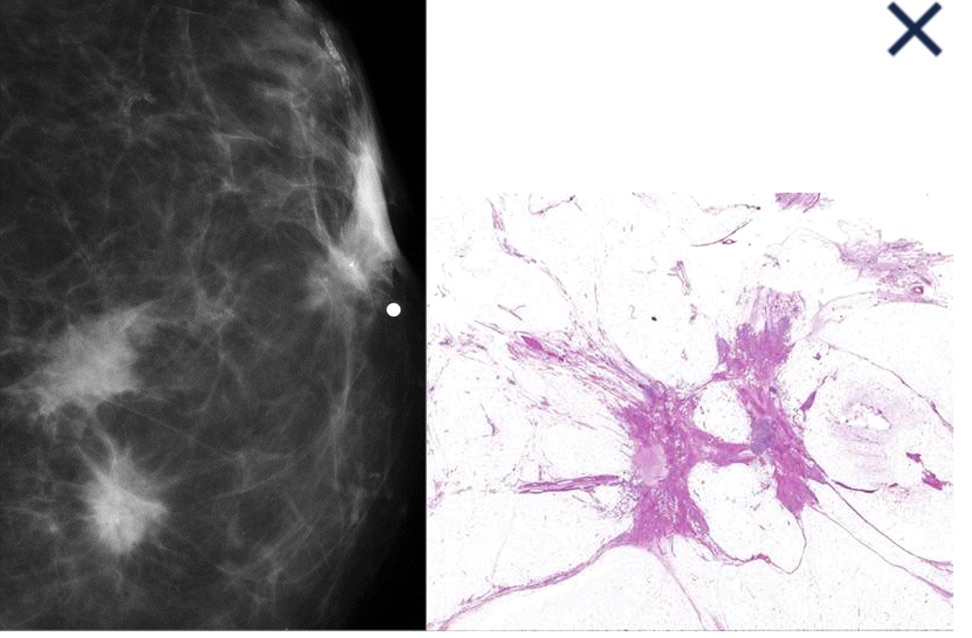
The alveolar type of invasive lobular carcinoma:
Is usually mammographically occult, or it can be seen as a subtle, asymmetric density (Image)
Multifocal spiculated lesion on the mammogramMammogram (a) and large format histology (b) alveolar type invasive lobular carcinoma
The various forms of invasive lobular carcinoma that develop in the TDLUs and present as localized lesions:
Have a significantly better prognosis than the diffusely infiltrating type breast cancer
Complex sclerosing lesions:
Present mammographically as nonpalpable architectural distortion with no central tumor mass and lucent radiating structures, the so called “black star”:
As opposed to cancers originating from the TDLU:
Which have a dense central tumor mass surrounded by radiopaque spiculation, giving the impression of looking at a “white star”
Malignant phyllodes tumors:
Present as large, high density masses:
The borders may be circumscribed or ill defined
Fat necrosis:
Also presents as a hypoechoic, high-density mass
References:
Tot T. Diffuse invasive breast carcinoma of no special type. Virchows Arch. 2016;468(2):199-206.
Tabár L, Dean PB. Teaching Atlas of Mammography. New York, NY: Thieme; 2011.
Is frequently associated with early recurrence and high mortality
Neoadjuvant chemotherapy:
Is the preferred treatment approach
In addition to potentially increasing the likelihood of tumor resectability and breast conservation:
Patients who have a pathological complete response after neoadjuvant therapy:
Have longer event-free survival:
Defined as the time from randomization to the date of disease progression that precluded definitive surgery, the date of local or distant recurrence or the occurrence of a second primary tumor, or the date of death from any cause
Have longer overall survival:
Accordingly, regulatory guidance supports the use of the pathological complete response as an end point for clinical testing of neoadjuvant treatment in patients with early triple-negative breast cancer
Pembrolizumab (Keytruda, Merck Sharp & Dohme):
An anti–programmed death 1 (PD-1) monoclonal antibody:
Has been shown to have antitumor activity and a range of mainly low-grade toxic effects in patients with metastatic triple-negative breast cancer, especially when used as first-line treatment
Immune checkpoint inhibition:
May enhance endogenous anticancer immunity:
After increased release of tumor-specific antigens with chemotherapy
Preliminary results from the phase 1b KEYNOTE-173 trial:
Showed that pembrolizumab plus neoadjuvant chemotherapy, with or without carboplatin:
Had promising antitumor activity:
Without a major increase in serious toxic effects in patients with locally advanced triple-negative breast cancer
In the phase 2 I-SPY2 trial:
The estimated percentage of patients with human epidermal growth factor receptor 2 (HER2)–negative breast cancers:
Who had a pathological complete response was:
Higher among those who received pembrolizumab combined with neoadjuvant chemotherapy than among those who received neoadjuvant chemotherapy alone
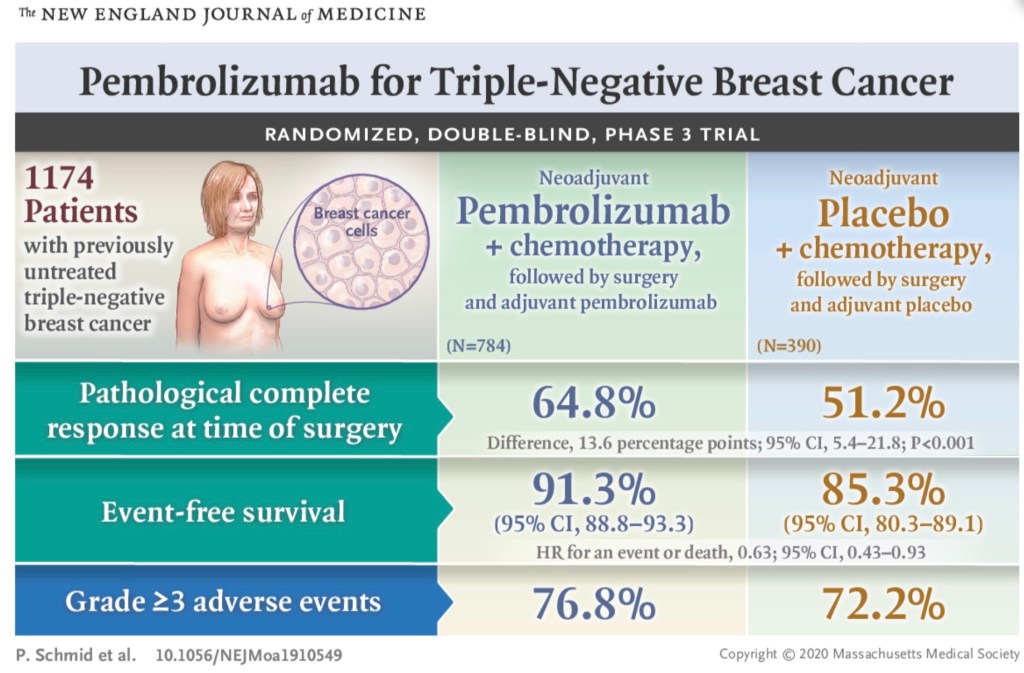
The phase 3 KEYNOTE-522 trial:
Evaluated the efficacy and safety of neoadjuvant pembrolizumab–chemotherapy as compared with neoadjuvant placebo–chemotherapy, followed by adjuvant pembrolizumab or placebo in patients with early triple-negative breast cancer
Methods of the Keynote 522 trial:
In this phase 3 trial, they randomly assigned (in a 2:1 ratio) patients with previously untreated stage II or stage III triple-negative breast cancer:
To receive neoadjuvant therapy with four cycles of pembrolizumab (at a dose of 200 mg) every 3 weeks plus paclitaxel and carboplatin (784 patients; the pembrolizumab–chemotherapy group) or placebo every 3 weeks plus paclitaxel and carboplatin (390 patients; the placebo–chemotherapy group)
The two groups then received an additional four cycles of pembrolizumab or placebo, and both groups received doxorubicin–cyclophosphamide or epirubicin–cyclophosphamide
After definitive surgery, the patients received adjuvant pembrolizumab or placebo every 3 weeks for up to nine cycles
The primary end points were a pathological complete response at the time of definitive surgery and event-free survival in the intention-to-treat population
Results of the Keynote 522 trial:
At the first interim analysis, among the first 602 patients who underwent randomization:
The percentage of patients with a pathological complete response was 64.8% (95% confidence interval [CI], 59.9 to 69.5) in the pembrolizumab–chemotherapy group and 51.2% (95% CI, 44.1 to 58.3) in the placebo–chemotherapy group (estimated treatment difference, 13.6 percentage points; 95% CI, 5.4 to 21.8; P<0.001)
After a median follow-up of 15.5 months (range, 2.7 to 25.0), 58 of 784 patients (7.4%) in the pembrolizumab–chemotherapy group and 46 of 390 patients (11.8%) in the placebo chemotherapy group had disease progression that precluded definitive surgery, had local or distant recurrence or a second primary tumor, or died from any cause (hazard ratio, 0.63; 95% CI, 0.43 to 0.93)
Across all treatment phases, the incidence of treatment-related adverse events of grade 3 or higher was 78.0% in the pembrolizumab–chemotherapy group and 73.0% in the placebo–chemotherapy group, including death in 0.4% (3 patients) and 0.3% (1 patient), respectively
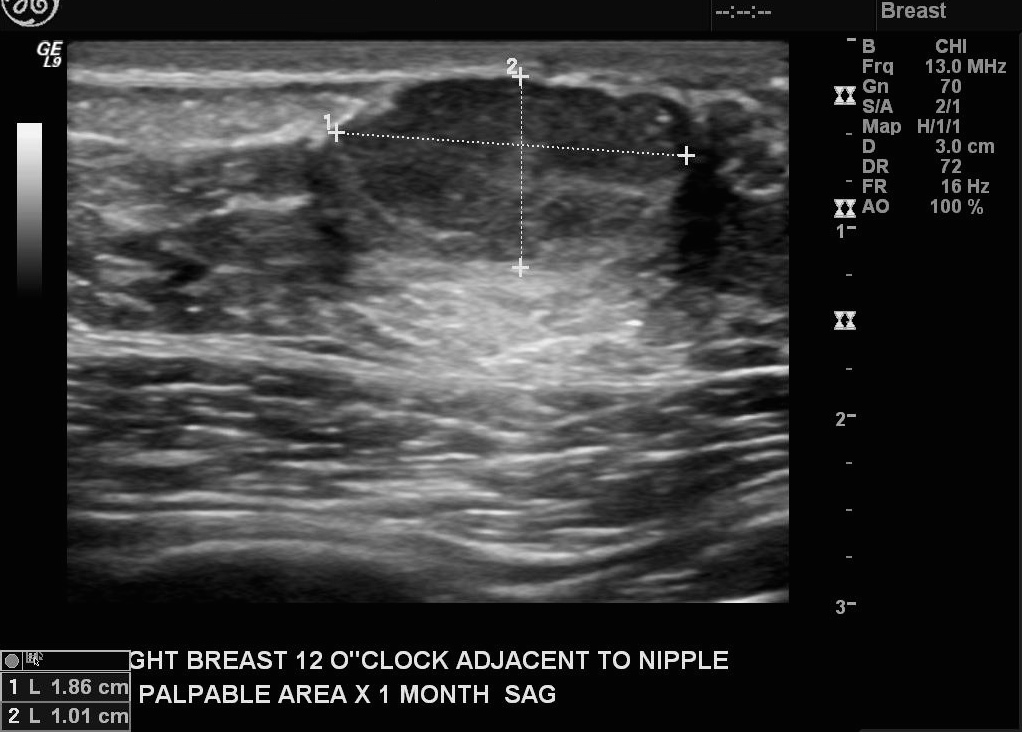
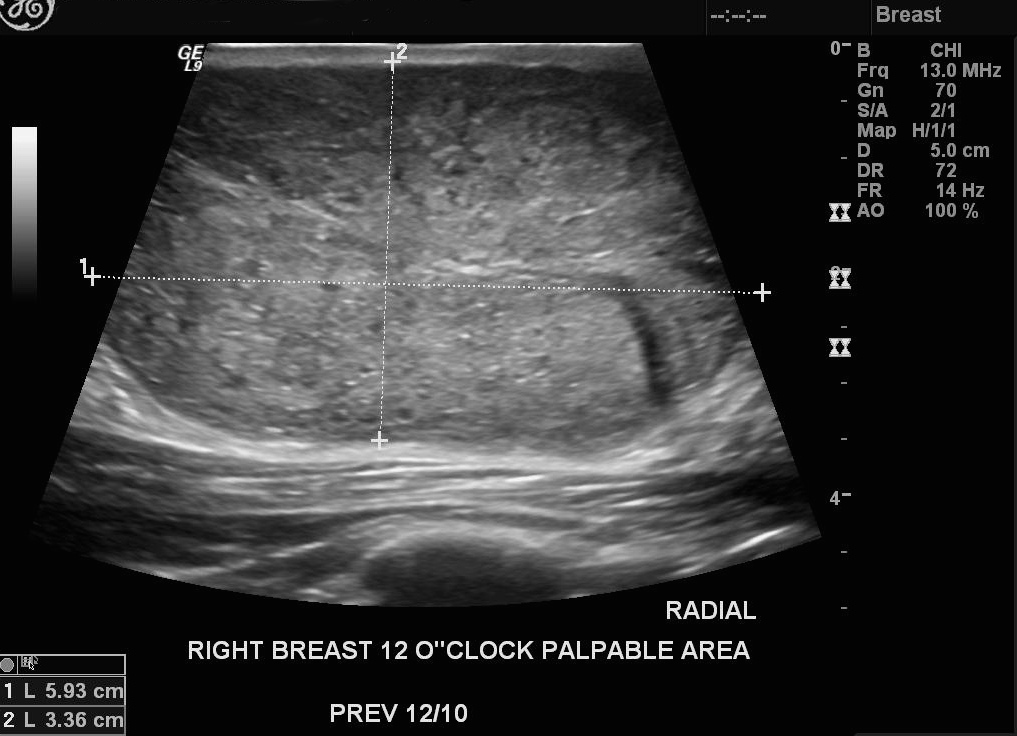
Rapid growth of breast lesions like the one seen above suggests that it is a phyllodes tumor:
Although a giant fibroadenoma is another possibility
The ultrasound image shows:
An isoechoic, heterogeneous mass that contains cystic, fluid filled spaces, and is vascular on Doppler examination
In most cases, benign phyllodes tumors have margins that are well-circumscribed, and a thin, echogenic capsule is demonstrable
The doubling time for a benign phyllodes tumor:
Is about four months
The doubling time for a malignant phyllodes tumor:
Is a little over a month
Rapidly growing phyllodes tumors:
Whether benign or malignant:
Often cause prominent veins on the skin from the developing vascularity
Phyllodes tumors are more common:
In women of Mexican descent:
Latin American women with phyllodes tumors tend to be diagnosed at an earlier age than other women
A core needle biopsy:
Cannot reliably distinguish phyllodes tumors from fibroadenomas:
Is therefore not sufficient for a definitive diagnosis
The correct management is excision:
With or without a pre-operative core biopsy, with care to completely excise the tumor
Phyllodes tumors can also be difficult to distinguish from giant juvenile fibroadenomas:
But they should also be treated by surgical excision
References:
Guillot E, Couturaud B, Reyal F, Curnier A, Ravinet J, Lae M, et al. Management of phyllodes breast tumors. Breast J. 2011;17(2):129-137.
Plaza MJ, Swintelski C, Yaziji H, Torres-Salichs M, Esserman LE. Phyllodes tumor: review of key imaging characteristics. Breast Dis. 2015;35(2):79-86.
Rajan PB, Cranor ML, Rosen PP. Cystosarcoma phyllodes in adolescent girls and young women: a study of 45 patients. Am J Surg Pathol. 1998;22(1):64-69.
Sosin M, Pulcrano M, Feldman ED, Patel KM, Nahabedian MY, Weissler JM, et al. Giant juvenile fibroadenoma: a systematic review with diagnostic and treatment recommendations. Gland Surg. 2015;4(4):312-321.
Stavros AT. Atypical, high-risk, premalignant, and locally aggressive lesions. In: Stavros AT. Breast Ultrasound. Philadelphia, PA: Lippincott