Blog

July – Parathyroid Awareness Month

    July is Parathyroid Awareness month! Join Dr. Rodrigo ARRANGOIZ member of Sociedad Quirurgica SC and expert in parathyroid surgery in the #CheckYourCalcium challenge.
    • Share this post and then post a selfie with your calcium result on your page to raise awareness. #JAM2019 #JulyHPT #CheckYourCalcium.
  • #Arrangoiz

    #ParathyroidExpert

    #ParathyroidSurgeon

    #Hyperparathyroidism

    #Hypercalcemia

    #CheckYourCalcium

    #HeadandNeckSurgeon

    #EndocrineSurgeon

    Thyroid Articles

    Check out these Thyroid-related articles published online or in print this past week!

    Surgical management of the compromised recurrent laryngeal nerve in thyroid cancer. Russell MD, Kamani D, Randolph GW. Best Pract Res Clin Endocrinol Metab. 2019 Jun 4. https://www.ncbi.nlm.nih.gov/pubmed/31230919

    Intraoperative nerve monitoring during thyroidectomy: evaluation of signal loss, prognostic value and surgical strategy. Gür EO, Haciyanli M, Karaisli S, Haciyanli S, Kamer E, Acar T, Kumkumoglu Y. Ann R Coll Surg Engl. 2019 Jun 20:1-10. https://www.ncbi.nlm.nih.gov/pubmed/31219340

    Stimulating and dissecting instrument for transoral endoscopic thyroidectomy: proof of concept investigation. Zhang D, Li S, Dionigi G, Zhang J, Wang T, Zhao Y, Xue G, Sun H.

    Surg Endosc. 2019 Jun 19. https://www.ncbi.nlm.nih.gov/pubmed/31218426

    Case report of a neuroendocrine tumor of the thyroid gland with limited calcitonin expression: a diagnostic challenge. Sukpanich R, Khanafshar E, Suh I, Gosnell J.

    AME Case Rep. 2019 May 14;3:12. https://www.ncbi.nlm.nih.gov/pubmed/31231713

    Hyperparathyroidism / Hiperparatiroidismo Articles / Artículos

    Check out these parathyroid-related articles published online or in print this week!

    Correlation between iPTH Levels on the First Postoperative Day After Total Thyroidectomy and Permanent Hypoparathyroidism: Our Experience. Canu GL, Medas F, Longheu A, Boi F, Docimo G, Erdas E, Calò PG. Open Med (Wars). 2019 Jun 7;14:437-442. https://www.ncbi.nlm.nih.gov/pubmed/31231683

    Can Met-PET/CT Predict Sporadic Multiglandular Hyperparathyroidism? Report of a Case and Review of the Literature. Hillenbrand A, Lemke J, Henne-Bruns D, Beer AJ, Prasad V.

    Case Rep Endocrinol. 2019 May 15;2019:1791740. https://www.ncbi.nlm.nih.gov/pubmed/31223506

    Surgical Treatment of Hyperparathyroidism After Kidney Transplant. Kovács DÁ, Fedor R, Asztalos L, Andrási M, Szabó RP, Kanyári Z, Barna S, Nemes B, Győry F. Transplant Proc. 2019 May;51(4):1244-1247. PMID: 31101206 https://www.ncbi.nlm.nih.gov/pubmed/31101206

    #Arrangoiz

    #HeadandNeckSurgeon

    #ParathyroidSurgeon

    #ParathyroidExpert

    #Hyperparathyroidism

    #EndocrineSurgery

    #ExpertoenParatiroides

    #CirujanodeParatiroides

    #Hiperparatiroidism

    #CirujanodeTumoresdeCabezayCuello

    #CirugiaEndocrina

    http://www.hiperparatiroidismo.info

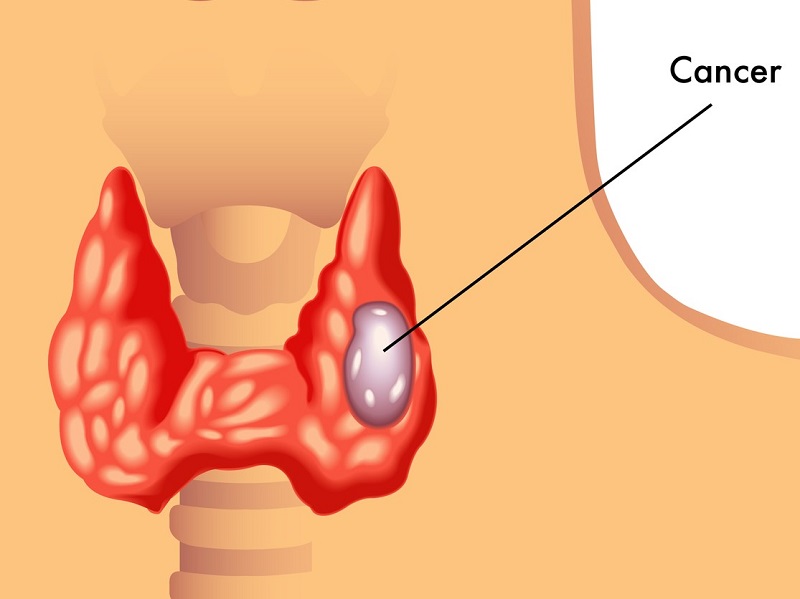
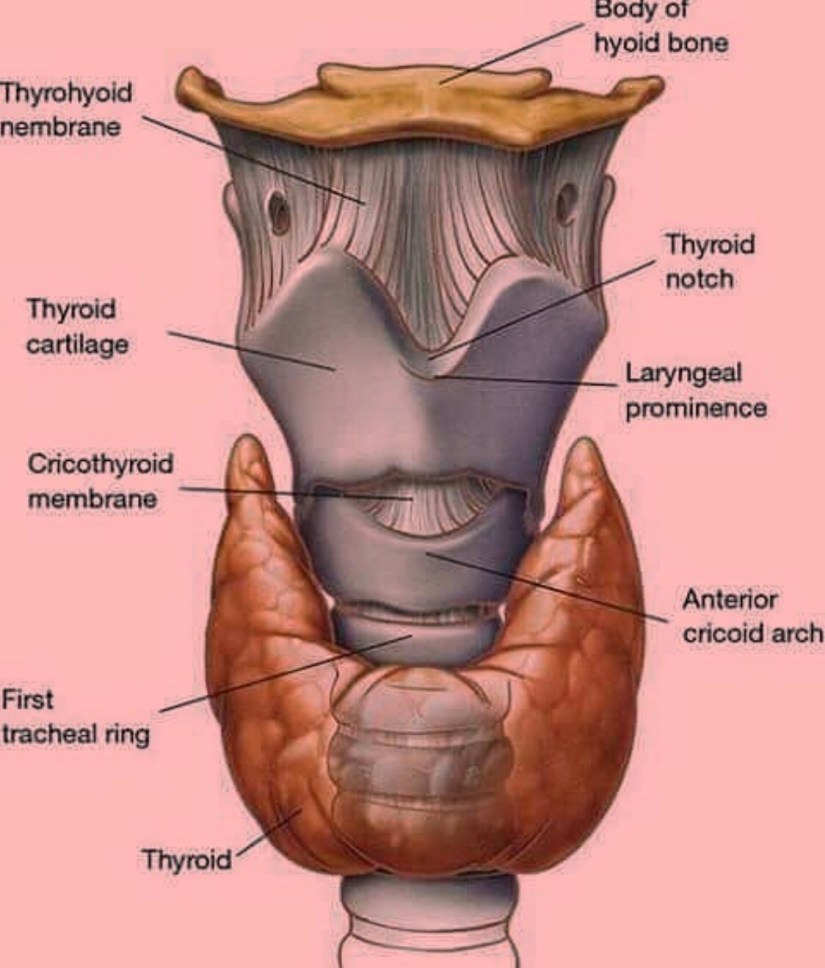
    Nódulo Tiroideo

    thyroid-cancer-shown-1

    • Un nódulo tiroideo es una lesión discreta dentro de la glándula tiroides que es radiológicamente diferente que el resto del parénquima tiroideo:
      • Algunas lesiones palpables del cuello pueden no corresponder ha alteraciones radiológicas:
        • Estas anomalías no cumplen con la definición estricta de nódulos tiroideos
    • Los nódulos tiroides no palpables detectados por otros estudios de imagen se denominan nódulos descubiertos incidentalmente o “incidentalomas”:
      • Los nódulos no palpables tienen el mismo riesgo de malignidad que los nódulos palpables confirmados por ultrasonido del mismo tamaño
    • En general:

      • Solo se deben evaluar los nódulos mayores 1 cm:

        • Ya que tienen un mayor potencial de ser cánceres clínicamente significativos.

    • En ocasiones,:
      • Puede haber nódulos menores de 1 cm que requieren una evaluación adicional debido a:
        • Los síntomas clínicos del paciente:
          • Dolor en el cuello
          • Dificultad or dolor al deglutir
          • Cambios de voz
          • Dificultad para respirar
        • Adenopatía linfática asociada
        • Historia familiar de primario grado de cancer de tiroides
        • Historia de radiación a la región de la cabeza y cuello


    #Arrangoiz

    #Teacher

    #Surgeon

    #Cirujano

    #ThyroidExpert

    #ThyroidSurgeon

    #CirujanodeTiroides

    #ExpertoenTiroides

    #ExpertoenParatiroides

    #Paratiroides

    #Hiperparatiroidismo

    #CancerdeTiroides

    #ThyroidCancer

    #PapillaryThyroidCancer

    #SurgicalOncologist

    #CirujanoOncologo

    #CancerSurgeon

    #CirujanodeCancer

    #HeadandNeckSurgeon

    #CirugiaEndocrina

    http://www.cirugiatiroides.com

    Thyroid Nodules Epidemiology

    images

    • Palpable thyroid nodules:
      • Occur in 5% of women and 1% of men in iodine-sufficient areas.
    • Thyroid nodule prevalence varies with detection mode and increases with age:
      • 2% to 6% prevalence by palpation
      • 19% to 68% prevalence by ultrasound
    • Among all thyroid nodules:
      • 7% to 15% are malignant:
        • The proportion varies with:
          • Age
          • Gender
          • Radiation exposure
          • Family history
          • Other factors
    • At least 94% of thyroid carcinomas are:
      • Differentiated thyroid cancer (DTC):
        • Primarily papillary thyroid carcinoma (PTC), and follicular thyroid carcinoma
    • The annual incidence of thyroid cancer per 100 000 person has increased from:
      • 4.6 in 1974 to 1977 to 14.4 in 2010-2013
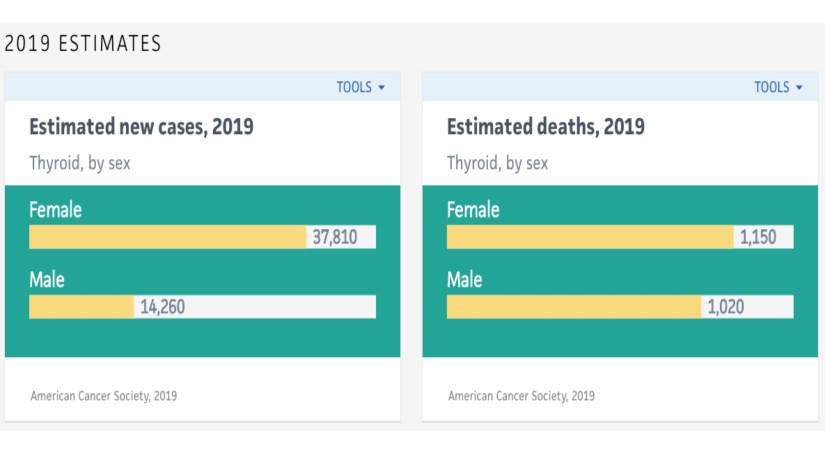
    • In the United States in 2019:
      • 52,070 new cases of thyroid cancer are estimated to be diagnosed :
        • 14,260 in men
        • 37,810 in women
          • This figure is largely attributable to:
            • Incidentally detected subclinical disease:
      • Approximately 2,170 deaths from thyroid cancer are estimated:
        • 1,020 men
        • 1,150 women

    thyroid 2thyroid 1

    #Arrangoiz

    #Teacher

    #Surgeon

    #Cirujano

    #ThyroidExpert

    #ThyroidSurgeon

    #CirujanodeTiroides

    #ExpertoenTiroides

    #ExpertoenParatiroides

    #Paratiroides

    #Hiperparatiroidismo

    #CancerdeTiroides

    #ThyroidCancer

    #PapillaryThyroidCancer

    #SurgicalOncologist

    #CirujanoOncologo

    #CancerSurgeon

    #CirujanodeCancer

    #HeadandNeckSurgeon

    #CirugiaEndocrina

    http://www.cirugiatiroides.com

    Thyroid related Articles

    Check out these Thyroid-related articles published online or in print this past week! American Thyroid Association THYCA American Association of Clinical Endocrinologists Endocrine Society American College of Surgeons

    Efficacy of indocyanine green fluorescence in predicting parathyroid vascularization during thyroid surgery. Razavi AC, Ibraheem K, Haddad A, Saparova L, Shalaby H, Abdelgawad M, Kandil E. Head Neck. 2019 Jun 17. https://www.ncbi.nlm.nih.gov/pubmed/31206817

    Risk-oriented concept of treatment for intrathyroid papillary thyroid cancer. Hartl DM, Hadoux J, Guerlain J, Breuskin I, Haroun F, Bidault S, Leboulleux S, Lamartina L. Best Pract Res Clin Endocrinol Metab. 2019 Jun 4. https://www.ncbi.nlm.nih.gov/pubmed/31208873

    Thyroid core needle biopsy: patients’ pain and satisfaction compared to fine needle aspiration. Jin Kim H, Koon Kim Y, Hoon Moon J, Young Choi J, Il Choi S.

    Endocrine. 2019 Jun 15. https://www.ncbi.nlm.nih.gov/pubmed/31203562

    Deciphering novel biomarkers of lymph node metastasis of thyroid papillary microcarcinoma using proteomic analysis of ultrasound-guided fine-needle aspiration biopsy samples. Lin P, Yao Z, Sun Y, Li W, Liu Y, Liang K, Liu Y, Qin J, Hou X, Chen L. J Proteomics. 2019 Jun 10;204:103414. https://www.ncbi.nlm.nih.gov/pubmed/31195151

    Axillary Radiation (AR) Instead of Undergoing an Axillary Dissection (ALND)?

    shutterstock_113090875

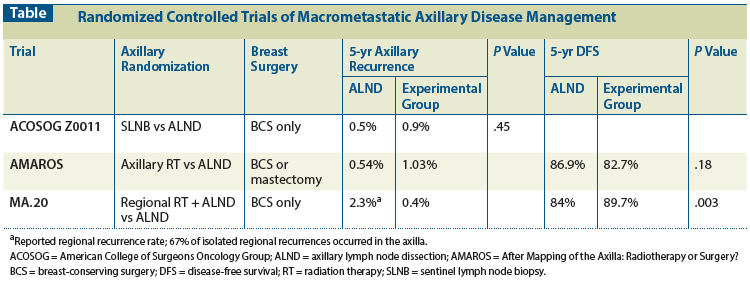
    • The European Organisation for Research and Treatment of Cancer (EORTC) 10981 After Mapping of the Axilla, Radiation or Surgery? (AMAROS) trial:
      • Randomized 4806:
        • Clinically node-negative
        • T1 to T2 tumors:
          • To completion axillary lymph node dissection (ALND) or axillary radiation (AR):
            • If they had positive nodes
        • Of the 1425 patients with positive sentinel nodes:
          • 744 had been randomly assigned to ALND
          • 681 to AR
        • Initially:
          • Patients with tumors 3 cm or smaller were eligible:
            • But the protocol was later modified to include:
              • Tumors up to 5 cm, multifocal tumors, or both
        • In the AR arm 21% of patients had T2 lesions
        • There were no age limits for eligibility:
          • Patients ranged from age 48 to 64 years
        • In the AR arm:
          • 42% of women were premenopausal
        • Patients who had either partial or total mastectomy were enrolled in the trial:
          • 18% of women had mastectomy
        • There was no limit on the number of positive nodes for the radiation arm:
          • But the majority of patients had 1 or 2 positive nodes
        • Crossover was allowed:
          • For patients with extensive axillary disease:
            • From the radiation arm to the dissection arm
          • Patients in the dissection arm who had 4 or more positive nodes:
            • Where allowed to have axillary radiation
            • Four percent of patients who stayed in the radiation arm had 3 positive nodes, and 1% had 4 or more positive nodes.
        • Importantly:
          • In the axillary dissection arm:
            • 25% of patients had an additional 1 to 3 positive nodes (in addition to the positive sentinel nodes) at dissection
            • 8% had 4 or more additional positive nodes
          • Since it was a randomized trial:
            • We can assume the same numbers were present in the radiation arm:
              • So these patients did not necessarily have low-volume axillary disease.
        • Axillary radiotherapy (RT) included:
          • The contents of all 3 levels of the axilla and the medial part of the supraclavicular fossa
          • The prescribed dose was 25 fractions of 2 Gy each
          • For patients in the AR arm who had mastectomy:
            • Radiation to the chest wall in addition to the axilla was optional but not mandatory
        • There were no significant differences:
          • In 5-year overall survival or disease-free survival between the two arms:
            • At 6.1 years of follow-up:
              • There was no significant difference:
                • In the rate of axillary failure:
                  • 0.43% ALND vs 1.19% RT
            • At 5-year follow-up there was a significant difference:
              • In clinical signs of lymphedema between the groups:
                • 23% in ALND vs. 11% in AR:
                  • There was greater than a 10% difference in arm size compared to the contralateral arm:
                    • In 13% of the ALND arm and 5% of the AR arm
    • The AMAROS study findings would suggest that axillary RT is an appropriate alternative to ALND in patients with a positive sentinel node:
      • However, the clinical characteristics of the AMAROS cohort are remarkably similar to the American College of Surgeons Oncology Group (ACOSOG) Z0011 cohort:
        • With 80% of AMAROS patients having:
          • A tumor less than 2 cm
        • 90% patients:
          • Receiving any systemic therapy
        • 95% of patients:
          • Having only 1 to 2 positive sentinel nodes
      • Patients in ACOSOG Z0011 treated with sentinel lymph node biopsy only demonstrated:
        • Similar 5-year rates of regional recurrence as the AMAROS patients receiving axillary RT:
          • 0.9% [ACOSOG Z0011] vs 1.2% [EORTC 10981 AMAROS axillary RT]):
            • Thus, while AMAROS indicates that sentinel node biopsy and nodal RT is an alternative to ALND:
              • It does not demonstrate that RT is necessary in all patients with a positive sentinel node:
                • Particularly in those treated with breast-conserving surgery
      • The decision to include axillary RT in patients with 1 to 2 positive sentinel nodes:
        • Should be tailored to the individual:
          • Taking into account other clinical factors which may place the patient at higher risk for locoregional recurrence

    0405MorrowTable

    img_0832-2img_0833-2img_0834-2img_0835-2img_0836-2img_0837-2

    #Arrangoiz

    #Teacher

    #Surgeon

    #Cirujano

    #SurgicalOncologist

    #CirujanoOncologo

    #CancerSurgeon

    #CirujanodeCancer

    #BreastSurgeon

    #BreastCancer

    #CancerdeMama

    #CirujanodeMama

    Following Breast Conserving Surgery -What Subgroup of Patients Can Have Omission of Adjuvant Irradiation?

    • Multiple groups have attempted to define a favorable subgroup of women in whom the omission of adjuvant irradiation following a partial mastectomy is reasonable:The CALGB 9343 trial:Randomized women:Ages 70 years and older
          • With clinical stage I (T1,N0,M0) disease:To tamoxifen for 5 years versus tamoxifen plus whole-breast irradiationPatients with estrogen receptor-negative tumors were excluded
            • Most tumors were 2 cm or less
            • Surgical margins were required to be negative:Defined as the absence of tumor at the inked margin
        • Adjuvant whole-breast irradiation:Significantly reduced the risk of local or regional failure:From 10% to 2% at 10 yearsThere were no significant differences in:Distant disease-free survival or overall survival between the groups
      • The PRIME II trial:Enrolled 1326 patients:Ages 65 years and older
          • T1 to T2
          • Node-negative tumors
          • Clear margins
        • Following breast-conserving surgery:Patients received endocrine therapyAnd were randomized to adjuvant radiation therapy or no further treatment
        • At 5 years:Those undergoing radiation:Demonstrated a reduction in local recurrence:4.1% vs 1.3%
            • With no difference in survival
    • Typical breast tangents:Without targeted nodal irradiation:Would be appropriate for a patient with pN0 disease
    • Adjuvant irradiation reduces the risk of ipsilateral breast tumor recurrence regardless of whether the margins are positive:A positive margin:Significantly increases the risk of local failure despite irradiation


    img_0832-2img_0833-2img_0834-2img_0835-2img_0836-2img_0837-2


    #Arrangoiz

    #Teacher

    #Surgeon

    #Cirujano

    #SurgicalOncologist

    #CirujanoOncologo

    #CancerSurgeon

    #CirujanodeCancer

    #BreastSurgeon

    #BreastCancer

    #CancerdeMama

    #CirujanodeMama

    Who Should Receive Radiation Therapy Following Breast Cancer Surgery

    shutterstock_113090875

    • Following breast-conserving surgery (partial mastectomy, lumpectomy):
      • Adjuvant radiotherapy is recommended due to benefits in:
        • Local control
        • Potentially breast cancer mortality.
    • The Early Breast Cancer Trialists’ Collaborative Group (EBCTCG) meta-analysis:
      • Found that for patients undergoing breast-conserving surgery that are N0:
        • Radiation reduced:
          • The risk of any recurrence:
            • From 31% to 16%
          • Reduced breast cancer mortality:
            • From 21% to 17%
      • The EBCTCG also found that for patients undergoing mastectomy with 1 to 3 positive nodes:
        • Radiotherapy was associated with a:
          • Reduction in locoregional recurrence (LRR):
            • From 20% to 4%
          • Reduction in breast cancer mortality:
            • From 50% to 42%
      • Although many have interpreted the EBCTCG findings to mean:
        • All postmastectomy patients with 1 to 3 positive nodes should have postmastectomy radiation therapy (PMRT):
          • The patients enrolled in the trials in that meta-analysis were from a different era:
            • Making it difficult to know how relevant the findings are to patients who are diagnosed and treated by current standards:
              • The patients were enrolled between 1964 and 1986
              • Many of them did not receive systemic therapy:
                • The 64% who received chemotherapy were treated with:
                  • Cyclophosphamide, methotrexate, and fluorouracil:
                    • Which is inferior to modern regimens
              • Only 24% of patients were treated with tamoxifen
              • No patients received an aromatase inhibitor.
        • The benefit of PMRT diminishes:
          • As the risk of LRR diminishes
        • Patients with 1 to 3 positive nodes in the meta-analysis who were not treated with PMRT:
          • Had a 20% rate of LRR (vs. 4%):
            • But recurrence is significantly lower with modern systemic treatment:
              • Sharma et al. retrospectively reviewed patients:
                • Who had mastectomies between 1997 and 2002 and did not receive PMRT:
                  • The 10-year rate of LRR in patients with 1 to 3 positive nodes:
                    • Was only 4.3%:
                      • Compared to 20% in the EBCTCG meta-analysis
              • Another study of patients with 1 to 3 positive nodes:
                • Compared the risk of LRR:
                  • Between two different eras, before and after the routine use of sentinel node biopsy, taxane therapy, and aromatase inhibitors:
                    • Use of PMRT reduced the 15-year rate of LRR in the first era:
                      • From 14.5% to 6.1%
                    • PMRT did not appear to benefit patients treated in the second era:
                      • With 5-year LRR rates of:
                        • 2.8% without PMRT
                        • 4.2% with PMRT
              • The NSABP B-28 study:
                • Randomized node-positive patients to:
                  • Doxorubicin and cyclophosphamide versus doxorubicin and cyclophosphamide plus paclitaxel
                • Use of PMRT was not allowed in patients who were treated with mastectomy:
                  • So the trial gives a good view of the risk of LRR for node-positive patients who are treated with mastectomy and relatively modern systemic therapy.
                • For patients with 1 to 3 positive nodes:
                  • LRR at 10 years was:
                    • 6% for patients with high-risk oncotype DX recurrence scores
                    • 4.1% with intermediate-risk oncotype DX recurrence scores
                    • 2.4% with low-risk oncotype DX recurrence scores
              • Lai et al. recently reviewed 293 mastectomy patients with T1 to T2 breast cancer and 1 to 3 positive lymph nodes:
                • All received anthracycline or taxane based chemotherapy and none received PMRT.
                • After stratifying patients according to:
                  • Luminal A and B, luminal HER2, HER2, and triple-negative subtypes:
                    • They found patients with triple-negative breast cancer to have the highest 5-year LRR when compared to all other subtypes:
                      • 10.6% vs 4.2%:
                        • P=0.05
                  • Multivariate analysis found that the following factors significantly increased the risk of LRR:
                    • Patients younger than age 40 years
                    • Tumors larger than 3 cm
                    • The presence of extensive intraductal components .
                  • The authors concluded that:
                    • Administering modern systemic therapy to early breast cancer patients not receiving PMRT:
                      • Significantly reduces the rate of LRR.
            • In view of the fact that PMRT significantly increased overall mortality in node-negative patients in the EBCTCG (47.6% vs 41.6%; rate ratio 1.23):
              • Caution should be taken in extrapolating the results to all patients with 1 to 3 positive nodes in the modern era.
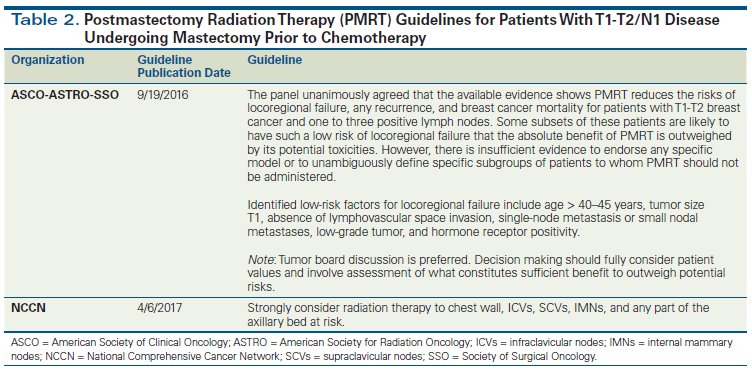
        • The American Society of Clinical Oncology, the American Society for Radiation Oncology, and the Society of Surgical Oncology:
          • Recently released an updated consensus statement regarding the role of PMRT in women with 1 to 3 positive lymph nodes:
            • The consensus panel unanimously agreed that PMRT in this subset of patients (with T1 to T2 breast cancer with 1 to 3 positive lymph nodes):
              • Reduces local-regional failure
              • Any recurrence
              • Breast cancer mortality in patients.
            • They agreed that the decision for PMRT:
              • Should be made in a multidisciplinary setting
              • With the involvement of the patient and her wishes after she is presented with all available data.
            • The panel went on to acknowledge that in some subsets of patients:
              • The risk of local-regional failure may be so low that the:
                • Absolute benefit of PMRT is outweighed by its toxicities.
            • Further, even if axillary lymph node dissection is omitted in the setting of a positive lymph node:
              • PMRT should only be used if there is already significant evidence justifying the benefit of PMRT without knowing the status of any additional axillary nodes.
            • When given:
              • PMRT should include the:
                • Internal mammary, supraclavicular, and apical axillary nodes and the chest wall or reconstructed breast.
            • All patients with a positive axillary node after receipt of neoadjuvant chemotherapy should receive PMRT

    1806sharma-table2

    img_0832-1img_0833-1img_0834-1img_0835-1img_0836-1img_0837-1


    #Arrangoiz

    #Teacher

    #Surgeon

    #Cirujano

    #SurgicalOncologist

    #CirujanoOncologo

    #CancerSurgeon

    #CirujanodeCancer

    #BreastSurgeon

    #BreastCancer

    #CancerdeMama

    #CirujanodeMama