Occult Breast Cancer

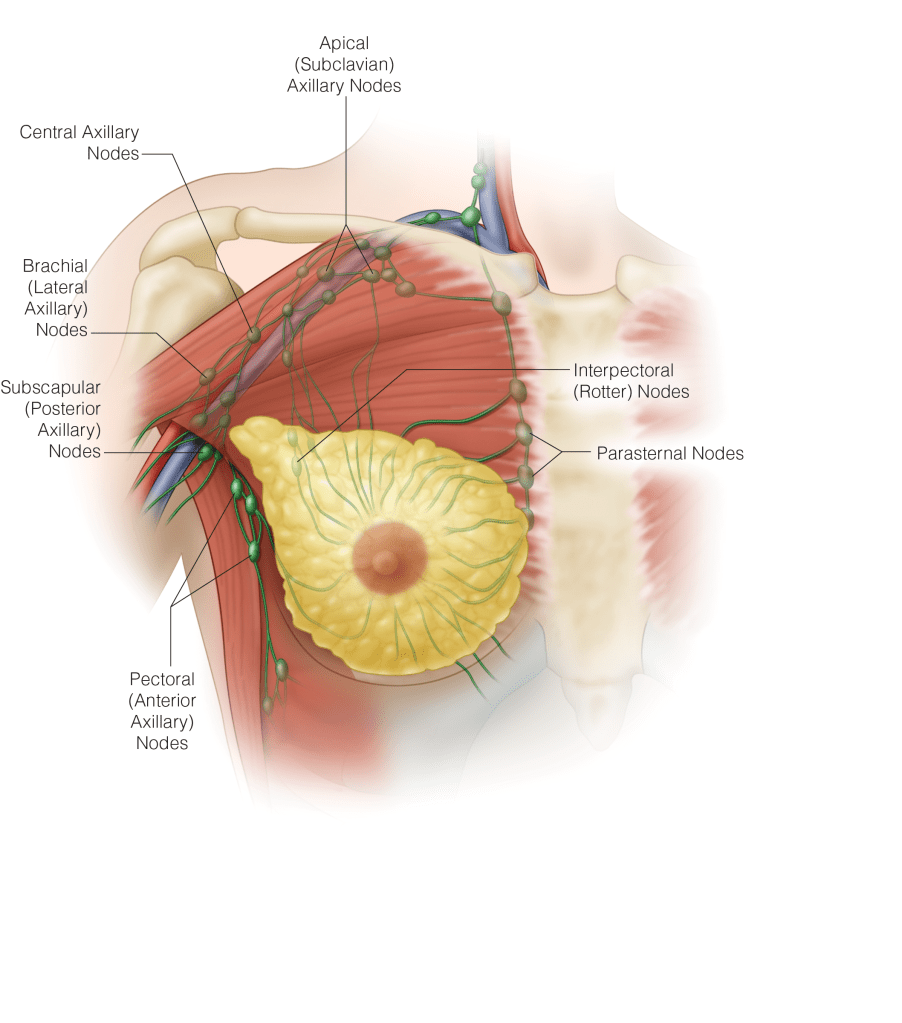
  • Occult breast cancer:
    • Which manifests as axillary lymph node metastasis:
      • Without the evidence of a primary breast tumor on clinical examination or mammography
    • It accounts for 0.3% to 1.0% of all breast cancers
  • The American College of Radiology:
    • Recommends the use of MRI for occult breast cancer patients:
      • Who do not have evidence of a breast primary on traditional radiological examination (mammogram and ultrasound) and clinical examination
    • Level I evidence has shown MRI is significantly more sensitive in detecting a primary lesion than mammography or ultrasound:
      • Identifying a primary tumor in 72% of cases that were originally deemed occult
  • Patients with occult breast cancer who have abnormalities demonstrated on MRI should then undergo evaluation with:
    • Targeted ultrasound plus ultrasound-guided needle biopsy or MRI-guided needle biopsy and receive treatment according to the clinical stage of the breast cancer
  • Treatment recommendations for those with negative MRI results and occult breast cancer presenting as isolated axillary metastases:
    • Are based on nodal status and breast cancer subtype
  • Most patients with axillary metastasis from an unknown breast primary:
    • Are candidates for neoadjuvant therapy
  • A meta-analysis reported outcomes for occult breast cancer in patients undergoing axillary lymph node dissection (ALND) (with or without radiation therapy [RT]) versus mastectomy:
    • It included 7 international studies, with 241 patients presenting between 1973 and 2011
    • The mean follow up was 62 months
    • There was no difference in survival, locoregional recurrence rate, or distant metastatic rate between those occult breast cancer patients who underwent mastectomy versus those who underwent ALND + breast RT (without breast surgery)
    • Radiotherapy improves locoregional recurrence and possibly mortality rates of patients undergoing ALND
    • Based on this meta-analysis, combined ALND and RT is an acceptable approach
  • The current National Comprehensive Cancer Network guidelines:
    • Recommend that patients with negative MRI results should be treated with mastectomy plus axillary lymph node dissection (modified radical mastectomy) OR ALND plus whole-breast irradiation
  • Approximately 40% of patients undergoing neoadjuvant chemotherapy for clinically node-positive disease:
    • Are successfully down staged in the axilla, and may be able to avoid ALND
    • Although this may prove to be safe for patients with primary occult breast cancer, there are no studies that have specifically addressed the safety of sentinel lymph node biopsy with targeted axillary dissection in this highly select subset
  • Treatment gold standard for occult breast cancer presenting with axillary metastases which remain clinically positive after neoadjvuant chemotherapy, remains ALND
  • References
    1. Ge L-P, Liu X-Y, Xiao Y, et al. Clinicopathological characteristics and treatment outcomes of occult breast cancer: a SEER population-based study. Cancer Manag Res. 2018;10:4381-4391. doi: 10.2147/CMAR.S169019
    2. Ofri A, Moore K. Occult breast cancer: where are we at? Breast. 2020;54:211-215. doi: 10.1016/j.breast.2020.10.012
    3. American College of Radiology. ACR practice parameter for the performance of contrast-enhanced magnetic resonance imaging (MRI) of the breast. Accessed April 7, 2023. https://www.acr.org/-/media/ACR/Files/Practice-Parameters/MR-Contrast-Breast.pdf?la1⁄4en.
    4. de Bresser J, de Vos B, van der Ent F, Hulsewé K. Breast MRI in clinically and mammographically occult breast cancer presenting with an axillary metastasis: a systematic review. Eur J Surg Oncol. 2010;36(2):114-119. doi: 10.1016/j.ejso.2009.09.007
    5. Macedo FIB, Eid JJ, Flynn J, Jacobs MJ, Mittal VK. Optimal surgical management for occult breast carcinoma: a meta-analysis. Ann Surg Oncol. 2016;23(6):1838-1844. doi: 10.1245/s10434-016-5104-8
    6. National Comprehensive Cancer Network. Breast Cancer. Version: 3.2023. Accessed April 7, 2023. https://www.nccn.org/professionals/physician_gls/pdf/breast.pdf
    7. American Society of Breast Surgeons. Consensus Statement on Axillary Management for Patients With In-Situ and Invasive Breast Cancer: a concise overview. Accessed April 17, 2023. https://www.breastsurgeons.org/docs/statements/management-of-the-axilla.pdf

Lateral Mandibulotomy

👉A lateral mandibulotomy has several disadvantages:

  • First, the muscular pull on the two segments of the mandible is unequal:
    • Putting the mandibulotomy site under significant stress and causing a delay in healing:
      • For this reason, intermaxillary fixation may be required
  • Second, the ability to gain access to the suture line to maintain cleanliness following surgery in the oral cavity is hampered as a result of intermaxillary fixation:
    • Leading to poor oral hygiene and the potential risk for sepsis of the suture line
  • In addition, a lateral mandibulotomy poses several anatomic disadvantages:
    • Leading to denervation of the teeth distal to the mandibulotomy site and the skin of the chin:
      • As a result of transection of the inferior alveolar nerve
  • A lateral mandibulotomy also causes devascularization of the distal teeth and the distal segment of the mandible:
    • From its endosteal blood supply
  • The exposure provided by a lateral mandibulotomy is:
    • Limited
  • If the patient needs postoperative radiation therapy:
    • The mandibulotomy site is directly within the lateral portal of radiation therapy:
      • Leading to delayed healing and complications at the site of the mandibulotomy

👉For these reasons, a lateral mandibulotomy is not recommended

#Arrangoiz #Doctor #Surgeon #Teacher #HeadandNeckSurgeon #CancerSurgeon #SurgicalOncologist #OralCancer #PharyngealCancer #MountSinaiMedicalCenter #MSMC #BramanComprehensiveCancerCenter #BCCC #Miami #Mexico

Techniques for Guiding Excision of Non Palpable Breast Lesions

  • Currently, wire localization (WL):
    • Is the most commonly used technique for guiding excision of nonpalpable lesions in the breast
    • Disadvantages of WL include:
      • Coordination of scheduling in the operating room and radiology
      • Patient discomfort
      • Potential for dislodgement or malpositioning
  • Localization devices that do not require wires are increasing in popularity to overcome some of these issues:
    • Commonly used devices include:
      • Radioactive seeds
      • Radar reflectors
      • Magnetic seeds
        • They can be implanted prior to surgery via mammographic or sonographic guidance
        • These can be placed in patients undergoing surgery upfront or after completion of neoadjuvant chemotherapy
  • Studies comparing the various techniques to WL:
    • Have demonstrated similar rates of positive margins, specimen volumes, and need for re-excision
  • While removal of the lesion can be determined simply by confirming signal within the specimen:
    • Specimen radiograph is still essential to document retrieval of the clip and/or targeted lesion.4Radioactive seed placement has not been shown to interfere with the isotope utilized in sentinel node mapping. Although initially used mostly for non-palpable breast lesions, use of these techniques is increasing in localization of lymph nodes, especially after neoadjuvant chemotherapy.5
  • References
  • 1. Lovrics PJ, Goldsmith CH, Hodgson N, et al. A multicentered, randomized, controlled trial comparing radioguided seed localization to standard wire localization for nonpalpable, invasive and in situ breast carcinomas. Ann Surg Oncol. 2011;18(12):3407-3414.
  • 2. Patel SN, Mango VL, Jadeja P, et al. Reflector-guided breast tumor localization for lumpectomies: a comparison of surgical outcomes. Clin Imaging. 2018;47:14-17.
  • 3. Harvey JR, Lim Y, Murphy J, et al. Safety and feasibility of breast lesion localization using magnetic seeds (Magseed): a multi-centre, open-label cohort study. Breast Cancer Res Treat. 2018;169(3):531-536.
  • 4. American Society of Breast Surgeons: Performance and Practice Guidelines for Breast-Conserving Surgery/Partial Mastectomy, v.2015. https://www.breastsurgeons.org/statements/guidelines/PerformancePracticeGuidelines_Breast-ConservingSurgery-PartialMastectomy.pdf. Accessed February 15, 2019.
  • 5. Caudle AS, Yang WT, Mittendorf EA et al. Selective surgical localization of axillary lymph nodes containing metastases in patients with breast cancer: a prospective feasibility trial. JAMA Surg. 2015;150(2):137-143.

Atypical Ductal Hyperplasia (ADH)

  • Atypical ductal hyperplasia (ADH):
    • Is a benign proliferative breast lesion:
      • Characterized by filling and distention of ducts by dysplastic monotonous epithelial cells:
        • Forming architecturally complex patterns, including:
          • Cribriform-like secondary lumens or micropapillary formations
    • It is found in approximately 10% of benign breast biopsies
    • It confers a four-fold increased risk of subsequent breast cancer:
      • With a cumulative incidence approaching 30% at 25 years
  • Definition and Histopathology:
    • ADH is defined by cytologic and architectural features:
      • Established by Page and colleagues in 1985
    • The lesion shows:
      • Proliferation of dysplastic, monotonous epithelial cells:
        • With architectural complexity and nuclear hyperchromasia
    • The key distinction from ductal carcinoma in situ (DCIS) is quantitative rather than qualitative:
      • ADH shares histologic features with low-grade DCIS but is less extensive
      • If the lesion meets criteria for DCIS in terms of quality but involves fewer than two ducts or measures less than 2 mm:
        • It is classified as ADH
    • This places ADH in a transitional zone between benign and malignant disease:
      • Making it a premalignant lesion
  • Epidemiology:
    • ADH:
      • Is found in approximately 10% of core needle biopsy specimens with benign findings
    • Both atypical ductal and atypical lobular hyperplasia:
      • Occur with equal frequency and confer similar breast cancer risks
    • The lesion is typically discovered incidentally on screening mammography:
      • In asymptomatic women
  • Risk Factors and Modifiers:
    • Younger age at diagnosis:
      • Is associated with higher subsequent breast cancer risk
    • Family history of breast cancer:
      • May increase risk, though data are conflicting
    • Number of atypical foci significantly impacts risk:
      • Women with ≥ 3 foci have a standardized incidence ratio (SIR) of 5.29 compared to 3.11 for a single focus
    • Dense breasts:
      • Increase risk compared to fatty breasts
  • Imaging Characteristics:
    • ADH:
      • Has no pathognomonic imaging appearance and typically mimics findings seen in small cancers
    • Mammographic Features:
      • Clustered microcalcifications:
        • Are the most common finding directly correlated with ADH:
          • Present in 64% to 82% of cases
        • Calcifications of intermediate concern or higher probability of malignancy:
          • Are more frequent when ADH is associated with malignancy
      • May also present as masses, asymmetric densities, or architectural distortion
      • Direct mammographic-histologic correlation:
        • Occurs in approximately 41% of cases
    • Ultrasound Features:
      • Most lesions appear as hypoechoic masses (64%)
      • Irregular shape (51%) and microlobulated margins (49%)
      • No specific posterior acoustic features (53%)
      • Parallel orientation (57%)
      • Presence of calcifications on ultrasound is significantly associated with upgrade to malignancy
    • ADH lesions are typically assigned BI-RADS category 4 (suspicious abnormality):
      • Warranting tissue sampling by core needle biopsy
  • Management:
    • Surgical Excision:
      • Surgical excision remains the standard of care for ADH diagnosed on core needle biopsy:
        • Due to upgrade rates of 15% to 30% to DCIS or invasive cancer
      • A 2020 meta-analysis of 6,458 lesions:
        • Found a 29% upgrade rate for surgically excised ADH
      • The Society of Surgical Oncology recommends routine excision:
        • Noting an upgrade rate of at least 20%
    • Emerging Evidence for Selective Observation:
      • Recent literature suggests that select low-risk ADH lesions may be candidates for observation rather than routine excision:
        • Lesions that appear completely removed at biopsy
        • Limited foci:
          • Fewer than 2 to 3 foci
        • No necrosis or significant atypia on pathology
        • Small groups of mammographic calcifications
        • No enhancement on MRI
        • No underlying risk factors:
          • No history of breast cancer
          • No genetic mutation
          • No concurrent high-risk lesions
    • A 2022 study found that selected women with ADH who met predetermined low-risk criteria and were managed nonoperatively:
      • Had a 1.2% index site cancer rate at median 5.2-year follow-up:
        • Comparable to the 1.5% rate in those who underwent surgery
    • A 2025 study applying COMET trial criteria:
      • Found only a 3.43% upgrade to invasive disease in low-risk patients
  • Post-Diagnosis Management:
    • For women with confirmed ADH on excisional biopsy:
      • Enhanced surveillance:
        • Annual mammography plus breast MRI screening
      • Risk-reducing medications:
        • Endocrine therapy (tamoxifen or aromatase inhibitors) is strongly recommended by NCCN guidelines:
        • With an 86% risk reduction for women with atypical hyperplasia
      • Lifestyle modifications:
        • Counseling on healthy lifestyle factors
    • Prognosis:
      • ADH confers a relative risk of approximately 4 for future breast cancer compared to women without the diagnosis
      • The absolute risk is substantial and sustained over time:
        • Cumulative Breast Cancer Incidence:
          • 5 years: 6.6% (95% CI 4.4-9.7%)
          • 10 years: 13.9% (95% CI 7.8-23.6%)
          • 25 years: 30% (either DCIS or invasive cancer)
        • The 10-year cumulative incidence is approximately 14.6%:
          • Representing about 1% per year
        • Risk increases with the number of atypical foci present:
          • Women with ≥ 3 foci have nearly double the risk of those with a single focus
      • Important Prognostic Considerations:
        • Risk affects both the ipsilateral and contralateral breast:
          • Though ipsilateral risk may be slightly higher
        • The risk does not plateau but continues to increase linearly over decades
        • Approximately half of subsequent breast cancers:
          • Occur within the first 5 years after ADH diagnosis
        • Both DCIS and invasive cancer contribute to subsequent events
        • The NCCN Breast Cancer Risk Reduction guidelines:
          • Classify women with atypical hyperplasia as high-risk and recommend risk-reducing endocrine therapy for those with life expectancy ≥ 10 years, given the substantial and sustained elevation in breast cancer risk
  • References:
    • Atypical Hyperplasia of the Breast — Risk Assessment and Management Options. Hartmann LC, Degnim AC, Santen RJ, Dupont WD, Ghosh K. The New England Journal of Medicine. 2015;372(1):78-89. doi:10.1056/NEJMsr1407164.
    • Updates on Management of Atypical Hyperplasia of the Breast. Klassen CL, Fraker JL, Pruthi S. Mayo Clinic Proceedings. 2025;100(6):1051-1057. doi:10.1016/j.mayocp.2025.01.029.
    • Subsequent Breast Cancer Risk Following Diagnosis of Atypical Ductal Hyperplasia on Needle Biopsy. Menes TS, Kerlikowske K, Lange J, et al. JAMA Oncology. 2017;3(1):36-41. doi:10.1001/jamaoncol.2016.3022.
    • Benign Breast Disease and Breast Cancer Risk in the Percutaneous Biopsy Era. Sherman ME, Vierkant RA, Winham SJ, et al. JAMA Surgery. 2024;159(2):193-201. doi:10.1001/jamasurg.2023.6382.
    • Atypical Hyperplasia of the Breast: Mammographic Appearance and Histologic Correlation. Helvie MA, Hessler C, Frank TS, Ikeda DM. Radiology. 1991;179(3):759-64. doi:10.1148/radiology.179.3.2027988.
    • Imaging Characteristics of and Multidisciplinary Management Considerations for Atypical Ductal Hyperplasia and Flat Epithelial Atypia: Review of Current Literature. Harper LK, Carnahan MB, Bhatt AA, et al. Radiographics : A Review Publication of the Radiological Society of North America, Inc. 2023;43(10):e230016. doi:10.1148/rg.230016.
    • Atypical Ductal Hyperplasia Diagnosed at Sonographically Guided Core Needle Biopsy: Frequency, Final Surgical Outcome, and Factors Associated With Underestimation. Mesurolle B, Perez JC, Azzumea F, et al. AJR. American Journal of Roentgenology. 2014;202(6):1389-94. doi:10.2214/AJR.13.10864.
    • Mucocele-Like Tumors of the Breast as Cystic Lesions: Sonographic-Pathologic Correlation. Kim SM, Kim HH, Kang DK, et al. AJR. American Journal of Roentgenology. 2011;196(6):1424-30. doi:10.2214/AJR.10.5028.
    • Diagnosis of Columnar Cell Lesions and Atypical Ductal Hyperplasia by Ultrasound-Guided Core Biopsy: Findings Associated With Underestimation of Breast Carcinoma. Ahn HS, Jang M, Kim SM, et al. Ultrasound in Medicine & Biology. 2016;42(7):1457-63. doi:10.1016/j.ultrasmedbio.2016.02.009.
    • Society of surgical oncology medical student & trainee primer for breast surgical oncology. Marissa K. Boyle, Julia M. Selfridge, Rachel E. Sargent, et al.
      Upgrade Rate of Percutaneously Diagnosed Pure Atypical Ductal Hyperplasia: Systematic Review and Meta-Analysis of 6458 Lesions. Schiaffino S, Calabrese M, Melani EF, et al. Radiology. 2020;294(1):76-86. doi:10.1148/radiol.2019190748.
    • Risk of Breast Cancer in Selected Women With Atypical Ductal Hyperplasia Who Do Not Undergo Surgical Excision. Kilgore LJ, Yi M, Bevers T, et al. Annals of Surgery. 2022;276(6):e932-e936. doi:10.1097/SLA.0000000000004849.
    • Implications of the COMET Trial for the Management of Atypical Ductal Hyperplasia. Zaveri S, Sun SX, Bevers TB, Albarracin CT, Bedrosian I. Annals of Surgical Oncology. 2025;:10.1245/s10434-025-18236-2. doi:10.1245/s10434-025-18236-2.
    • Atypical Hyperplasia of the Breast: Clinical Cases and Management Strategies. Vegunta S, Mussallem DM, Kaur AS, Pruthi S, Klassen CL. Cleveland Clinic Journal of Medicine. 2023;90(7):423-431. doi:10.3949/ccjm.90a.22098.
      Breast Cancer Risk Reduction. National Comprehensive Cancer Network. Updated 2025-08-29.
    • Use of Endocrine Therapy for Breast Cancer Risk Reduction: ASCO Clinical Practice Guideline Update. Visvanathan K, Fabian CJ, Bantug E, et al. Journal of Clinical Oncology : Official Journal of the American Society of Clinical Oncology. 2019;37(33):3152-3165. doi:10.1200/JCO.19.01472.
      Practice Bulletin Number 179: Breast Cancer Risk Assessment and Screening in Average-Risk Women. Obstetrics and Gynecology. 2017;130(1):e1-e16. doi:10.1097/AOG.0000000000002158.
    • Atypical Ductal or Lobular Hyperplasia, Lobular Carcinoma in-Situ, Flat Epithelial Atypia, and Future Risk of Developing Breast Cancer: Systematic Review and Meta-Analysis. Baker J, Noguchi N, Marinovich ML, et al. Breast (Edinburgh, Scotland). 2024;78:103807. doi:10.1016/j.breast.2024.103807.
    • Trajectory of Subsequent Breast Cancer Diagnoses in a Diverse Patient Cohort With Breast Atypia. Limberg JN, Thomas SM, Dalton JC, et al. Annals of Surgical Oncology. 2024;31(11):7550-7558. doi:10.1245/s10434-024-15788-7.

Types of Breast Surgery

👉A mastectomy is an operation to remove all of the breast tissue from a breast as a way to treat or prevent cancer.

👉Mastectomy can be a treatment option for many types of cancer:

  • Ductal carcinoma in situ or non-invasive breast cancer
  • Stage I and II (early stage) breast cancer
  • Stage III (locally advanced) breast cancer, after chemotherapy
  • Inflammatory breast cancer, after chemotherapy
  • Paget’s disease of the breast
  • Locally recurring breast cancer

👉Breast-conserving surgery (partial mastectomy/ lumpectomy), in which only the tumor is removed with negative margins, may be another option.

👉Newer mastectomy techniques can preserve the skin of the breast and allow it to have a more natural appearance – Skin sparing mastectomy

👉Newer mastectomy techniques can preserve the nipple areolar complex of the breast allowing it to have a more natural appearance – Nipple sparing mastectomy

👉Surgery to restore the shape of the breast, called breast reconstruction, can be done at the same time as the mastectomy or during a second operation.

#Arrangoiz #BreastSurgeon #BreastCancer #CancerSurgeon

High Risk Breast Lesion – Atypical Ductal Hyperplasia (ADH)

  • Surgical excision of an area of atypical duct hyperplasia (ADH) found on core needle biopsy:
    • Is recommended to rule out underlying occult breast cancer:
      • Which can be found in 15% to 30% of patients
  • Studies consistently show higher rates of upgrade to DCIS (2/3 of the cases) compared to invasive carcinoma (1/3 of the cases)
  • A multivariable model assessing predictors for risk of upgrade at the time of excision of ADH found that:
    • Lesions that were less than 50% removed by core biopsy, compared to those with greater than 90% removed:
      • Had a significantly higher risk of upgrade (OR 3.8)
    • Similarly, ADH with individual cell necrosis (OR 4.3) and with multiple foci of atypia on core biopsy (OR 2-3 foci 2.1; OR >3 foci 3.6 compared to 1 foci) were more likely to have a subsequent upgrade
  • ADH is associated with an increased risk of future development of breast cancer when identified on a core needle biopsy or at time of surgery:
    • With a relative risk of approximately 4
  • Increasing number of foci of atypia:
    • Has also been reported to be associated with increasing future breast cancer risk
  • A study by Degnim and colleagues combined outcomes for women with a history of atypical hyperplasia from the Mayo Clinic and the Nashville Cohort:
    • In the combined analysis, among women with ADH, the relative risk of breast cancer was 2.65 with 1 foci, 5.19 with 2 foci, and 8.94 with >3 foci, p<.001
  • As the vast majority of subsequent cancers in this population are estrogen positive:
    • Patients with ADH may benefit from chemoprevention as demonstrated in the NSABP P-1 study:
      • Which demonstrated a 49% reduction in the development of invasive breast cancer in high-risk patients with the use of tamoxifen compared to placebo (p<0.00001), with the greatest benefit seen in women with atypical hyperplasia or lobular carcinoma in situ:
        • However, tamoxifen did not effect overall survival
  • References
    • Mooney K, Bassett LW, Apple SK. Upgrade rates of high-risk breast lesions diagnosed on core needle biopsy: a single-institution and literature review. Modern Pathol. 2016;29(12):1471-1484.
    • Pena A, Shah SS, Fazzio RT, Hoskin TL, Brahmbhatt RD1, Hieken TJ, at al. Multivariate model to identify women at low risk of cancer upgrade after a core needle biopsy diagnosis of atypical ductal hyperplasia. Breast Cancer Res Treat.2017;164(2):295-304.
    • Hartmann LC, Degnim AC, Santen RJ, Dupont WD, Ghosh K. Atypical hyperplasia of the breast – risk assessment and management options. NEJM. 2015;372(1):78-89.
    • Degnim AC, Dupont WD, Radisky DC, et al. Extent of atypical hyperplasia stratifies breast cancer risk in 2 independent cohorts of women. Cancer. 2016;122(19):2971-2978.
#Arrangoiz #Doctor #Surgeon #CancerSurgeon #SurgicalOncologist #BreastSurgeon #MountSiniaMedicalCenter #MSMC #Miami #Mexico #BreastCancer

Local Breast Cancer Recurrence

Local recurrence in the breast may be accompanied by distant recurrence. Therefore, all patients who are diagnosed with a local or regional recurrence should have staging scans to rule out distant disease. If these scans are negative, surgical intervention is recommended if the tumor is operable.

In patients who develop an ipsilateral breast recurrence or new primary tumor following prior history of breast conservation with whole breast radiation therapy, further radiation is generally contraindicated. Therefore, the standard surgical treatment of the breast is mastectomy. While there have been case reports of repeat lumpectomy followed by accelerated partial-breast radiation therapy, there are insufficient data to support the long-term safety of this approach. If the tumor is not operable by mastectomy at presentation, neoadjuvant therapy with chemotherapy or hormone therapy may be considered as an initial step.

The approach to the axillary lymph nodes has been an area of debate since the era of SLNB. Nodal staging provides valuable prognostic information, even in the case of a local recurrence. If a patient is clinically node-negative at the time she presents with a local recurrence in the breast, SLNB may be attempted. There is a small body of literature supporting the use of reoperative SLNB in clinically node-negative patients who have an ipsilateral recurrence or new primary following prior breast conservation with SLNB. These studies have found that successful lymphatic mapping is more likely to occur when fewer nodes were removed at the time of the treatment for the index cancer. While lymphoscintography is not strictly required, it may help to identify sites of extra-axillary drainage due to alternate drainage pathways. In patients who have had prior completion axillary lymph node dissection, reoperative SLNB is possible, but less likely to be associated with successful lymphatic mapping. In these cases, axillary exploration is less likely to yield any additional lymph nodes.

Cardosa F, Fallowfield L, Costa A, et al; and ESMO Guidelines Working Group. Locally recurrent or metastatic breast cancer: ESMO Clinical Practice Guidelines for diagnosis, treatment and follow-up. Ann Oncol. 2011;22(Suppl 6):vi25-vi30.

Cox CE, Furman BT, Kiluk JV, et al. Use of reoperative sentinel lymph node biopsy in breast cancer patients. J Am Coll Surg. 2008;207:57-61.

Karam A, Stempel M, Cody HS III, Port ER. Reoperative sentinel lymph node biopsy after previous mastectomy. J Am Coll Surg. 2008;207:543-548.

Kaur P, Kiluk JV, Meade T, et al. Sentinel lymph node biopsy in patients with previous ipsilateral complete axillary lymph node dissection. Ann Surg Oncol. 2011;18:727-732.

Port E, Garcia-Etienne C, Park J, Fey J, Borgen PI, Cody HS 3rd. Reoperative sentinel lymph node biopsy: a new frontier in the management of ipsilateral breast tumor recurrence. Ann Surg Oncol. 2007;14:2209-2214.

Long-term outcomes of invasive ipsilateral breast tumor recurrences after lumpectomy in NSABP B-17 and B-24 randomized clinical trials for DCIS

  • Patients enrolled in the NSABP B-17 trial:
    • Were randomly assigned to receive:
      • Partial mastectomy only or partial mastectomy followed by lattice radiotherapy (LRT; a novel technique of delivering heterogeneous doses of radiation to voluminous tumors not amenable to surgery) for the treatment of localized DCIS
    • The trial showed a clear benefit for the addition of radiation
  • Patients enrolled in the NSABP B-24 trial:
    • Were randomly assigned to receive LRT or LRT plus tamoxifen (LRTT)
  • At 15-year follow-up:
    • The risk of death in these trials was low:
      • Ranging from 2.3% for patients who had LRTT to 4.7% for patients who had LRT
    • Ipsilateral breast tumor recurrence was:
      • 35% (19.6% invasive, 15.4% DCIS) in the lumpectomy only arm of B-17 and 19.8% (10.7% invasive, 9.0% DCIS) in the LRT arm
      • In B-24 IBRT was 16.6% (9.0 invasive, 7.6% DCIS) in the LRT arm and 13.2% (6.6% invasive, 6.7% DCIS) in the LRTT arm
    • The risk of contralateral new primary ranged from:
      • 4.9% (3.3% invasive, 1.6% DCIS) in the LRTT arm of B-24 to 9.3% (5.6% invasive, 3.7% DCIS) in the LRT arm of B-17
  • References:
    • Wapnir IL, Dignam JJ, Fisher B, Mamounas EP, Anderson SJ, Julian TB, et al. Long-term outcomes of invasive ipsilateral breast tumor recurrences after lumpectomy in NSABP B-17 and B-24 randomized clinical trials for DCIS. J Natl Cancer Inst. 2011;103(6):478-488.

#Arrangoiz #BreastSurgeon #BreastCancer #CancerSurgeon #Teacher #SurgicalOncologist #Miami #Mexico #DCIS

Safety of Omitting Radiotherapy After Lumpectomy in Early Breast Cancer — What the Randomized Evidence Says

Bottom line: In carefully selected patients (typically older, ER+/HER2–, node-negative, small tumors on endocrine therapy), skipping whole-breast radiotherapy (RT) raises local recurrence modestly but does not worsen overall survival in long-term randomized data. 

Key randomized signals (10-year):

• PRIME II (age ≥65, HR+, ≤3 cm, node-negative, endocrine therapy): local recurrence 9.5% without RT vs 0.9% with RT; no difference in distant recurrence or overall survival (~81% both arms). 

• CALGB 9343 (age ≥70, T1N0 ER+): local/regional control higher with RT (98% vs 90%) but no differences in time to mastectomy, distant metastasis, breast cancer-specific survival, or OS (67% vs 66%). 

Meta-analytic perspective: Syntheses focused on randomized trials consistently show RT substantially lowers local recurrence after breast-conserving surgery, with minimal or no OS impact in these low-risk cohorts—informing shared decisions when a patient prioritizes avoiding RT toxicity or logistics. 

Who may be appropriate to consider for omission?

• Age ≥65–70, ER+, HER2–, pT1, node-negative, clear margins, committed to endocrine therapy; ideally with a reassuring axillary assessment and low-risk biology. (Emerging prospective cohorts like LUMINA/IDEA support expanding biologic selection but are not RCTs.) 

Why this matters for patients:

• Fewer visits, less fatigue/dermatitis, and lower long-term toxicity burden—without sacrificing survival in the right subset. 

Practical takeaways for clinic:

Discuss omission for the classic low-risk profile above; quote absolute local-recurrence trade-offs (e.g., ~9–10% vs ~1% at 10 years in PRIME II).  If RT is preferred or biology is borderline, consider de-escalated RT (partial-breast or 5-fraction regimens) to cut burden while preserving control.  Use shared decision-making; align with patient goals, comorbidity, adherence to endocrine therapy, and imaging/pathology risk features. 

#BreastCancer #RadiationOncology #Deescalation #SharedDecisionMaking #Oncology

#Arrangoiz

SOUND Trial – Comprehensive Journal Club Q&A (Study Guide)

  • Framing the Question:
    • Clinical question:
      • In women with invasive breast cancer ≤ 2 cm, clinically node-negative and axillary ultrasound (AUS) negative:
        • Is omitting axillary surgery non-inferior to sentinel lymph node biopsy (SLNB):
          • For 5-year distant disease-free survival (DDFS)? JAMA Network
    • Why this matters now:
      • ACOSOG Z0011:
        • Showed no therapeutic benefit for ALND over less surgery (SLNB alone):
          • The next logical step tests whether staging itself (SLNB) can be omitted:
            • When it won’t change adjuvant plans:
              • Reducing morbidity without compromising oncologic safety JAMA Network
  • Study Design Essentials:
    • Design:
      • Prospective, multicenter, phase 3 non-inferiority RCT:
        • 1:1 randomization to:
          • No axillary surgery vs SLNB
      • Primary endpoint:
        • 5-yr distant disease free survival (DDFS) (ITT)
      • Secondary:
        • Disease free survival (DFS)
        • Overal survival (OS)
        • Cumulative incidence of distant and axillary recurrences, and adjuvant treatment recommendations JAMA Network
    • Setting and timeline:
      • 18 hospitals in:
        • Italy, Spain, Switzerland, and Chile
      • Enrollment Feb 2012 to Jun 2017
      • Analysis 2022 to 2023 JAMA Network
    • Eligibility (PICO):
      • Women of any age
      • Tumor ≤ 2 cm
      • cN0 by exam
      • Negative AUS:
        • Suspicious nodes required cytology to exclude metastasis
      • Breast-conserving surgery (BCS) common, with radiotherapy permitted:
        • Including partial breast and IORT
      • ITT N = 1,405:
        • SLNB 708
        • Omit 697
      • Median age 60
      • Median tumor 1.1 cm
      • ~ 88% ER+ / HER2 –  JAMA Network
    • AUS as a triage tool:
      • Despite variable sensitivity in literature:
        • Negative AUS in the SOUND trial effectively ruled out heavy nodal burden:
          • SLNB arm had 13.7% any nodal metastasis but only 0.6% had ≥ 4 positive nodes
          • Axillary recurrence 0.4% at 5 years in both arms JAMA Network
  • Statistics You Should Know:
    • Non-inferiority setup:
      • Primary analysis ITT:
        • NI margin 2.5% for 5-year DDFS; HR with 90% CI and one-sided NI P-value
        • Assumed 5-year DDFS ≈ 96.5%:
          • Observed outcomes were higher, increasing power to show NI if risks are truly similar JAMA Network
    • Follow-up:
      • Median follow-up for disease assessment 5.7 years in both arms JAMA Network
  • Results (with absolute numbers):
    • Primary endpoint (DDFS):
      • 5-year DDFS: 
        • 97.7% (SLNB) vs 98.0% (No surgery):
          • HR 0.84, 90% CI 0.45–1.54; P for non-inferiority = 0.02:
            • Two-arm difference not significant by log-rank (P=0.67) JAMA Network
    • Secondary endpoints:
      • 5-year DFS: 
        • 94.7% (SLNB) vs 93.9% (No surgery), P=0.30.
      • 5-year OS: 
      • Regional control (events are rare):
        • 5-year cumulative axillary recurrence = 0.4% in each arm (Gray P=0.91)
      • Locoregional relapse: 
      • Absolute event counts:
        • SLNB: 
          • 13 distant metastases (1.8%), 21 deaths (3.0%).
        • No surgery: 
          • 14 distant metastases (2.0%), 18 deaths (2.6%) JAMA Network
      • Adjuvant therapy impact:
        • No material differences in systemic therapy or RT use between arms:
          • Supporting that, in this AUS-negative group:
            • Pathologic nodal information didn’t drive adjuvant decisions JAMA Network
        • Radiotherapy details:
          • All RT options allowed, including partial breast / IORT
          • Notably, 114 patients (16.3%) in the no-surgery arm received ELIOT (full-dose or boost)
          • Despite this heterogeneity:
            • Axillary failures stayed 0.4% at 5 years in both arms JAMA Network
    • How often was SLNB positive?
      • 13.7% had any nodal metastasis in the SLNB arm (micro + macro metasteses)
      • Heavy burden (≥ 4 nodes) was 0.6% JAMA Network
  • Interpretation and External Context:
    • Plain-English bottom line:
      • For AUS-negative, ≤ 2 cm, cN0 tumors planned for BCS + RT:
        • Skipping SLNB is non-inferior for 5-yearr DDFS:
          • With no increase in axillary failures and no detectable survival trade-off – and you avoid the morbidity of axillary surgery JAMA Network
  • How does the SOUND trial line up with INSEMA trial (NEJM 2024/2025)?:
    • INSEMA broadened to T1 to T2 ≤ 5 cm BCT patients and used invasive DFS as the primary endpoint:
  • Generalizability – who are “SOUND-like” in clinic?
    • Mostly small (T1 / ≤ 2 cm), HR+ / HER2 –  tumors, negative AUS, upfront BCS + RT:
      • Adjuvant decisions unlikely to change with nodal micrometastatic information:
        • Authors estimate ~ 25% of all breast cancer (BC) cases may fit these criteria JAMA Network
  • Potential practice impact:
    • With ~ 2.3 M new BC cases / year, ~ 500,000 patients globally could avoid axillary surgery:
      • Improving early arm function and reducing lymphedema risk without oncologic compromise JAMA Network
  • Limitations and Caveats:
    • Low-risk enrichment:
      • Mostly small, ER+ / HER2- tumors:
        • Short-to-mid-term risk low:
    • Adjuvant therapy analysis not powered:
      • Differences in systemic / RT nuances might be too small to detect:
        • Adjuvant-recommendation analysis was secondary JAMA Network
    • Late trial registration noted:
      • Registered after enrollment began; protocol / statistical plan were peer-review-published, and authors state no interim looks occurred; still worth acknowledging JAMA Network
    • Radiation heterogeneity (including IORT):
      • Permissive RT techniques (e.g., ELIOT) could theoretically influence local / axillary outcomes:
        • Nonetheless axillary failure remained 0.4% in both arms JAMA Network
    • Not for neoadjuvant or mastectomy:
      • SOUND trial did not test patients planned for neoadjuvant systemic therapy or mastectomy without conventional whole-breast RT:
    • Young HR+ / HER2- patients (Rx-PONDER context):
      • In some premenopausal HR+ / HER2- patients:
        • Nodal positivity can still influence chemo or endocrine therapy type / duration:
          • If nodal information truly changes systemic therapy:
  • Apply in Clinic” Checklist (What to document):
    • Who qualifies for omission (SOUND-style)?
      • Tumor ≤ 2 cm
      • cN0 on exam
      • Negative AUS (suspicion cleared by cytology)
      • Upfront BCS + RT planned
      • Adjuvant plan won’t change with nodal micro-staging
      • Document shared decision-making:
    • Who should still get SLNB?
      • Neoadjuvant candidates (different evidence base)
      • Mastectomy without standard whole-breast RT
      • Cases where nodal status alters chemotherapy / Endocrine therapy decisions:
        • Younger HR+ / HER2-
      • AUS positive / suspicious nodes not cleared by cytology JAMA Network
    • How to counsel about risk:
      • Explain that with negative AUS, the chance of heavy nodal disease is very low (≥ 4 nodes 0.6% in SLNB arm), and axillary recurrence at 5 years ~ 0.4% without surgery – the same as with SLNB JAMA Network
    • Quick Numbers Box:
      • ITT N=1,405 (708 SLNB; 697 No surgery):
      • 5-yr DDFS: 
        • 97.7% vs 98.0% (HR 0.84; 90% CI 0.45–1.54; NI P=0.02) JAMA Network
      • 5-yr DFS: 
        • 94.7% vs 93.9% (P=0.30)
      • 5-yr OS: 98.2% vs 98.4% (P=0.72) JAMA Network
      • Axillary recurrence (5 yrs): 
        • 0.4% vs 0.4%
      • SLN+ (any):
        • 13.7%
      • ≥ 4 nodes:
      • RT nuance: 
        • 16.3% of omission arm received ELIOT (full-dose / boost) JAMA Network
  • Discussion Starters:
    • Endpoint choice: 
      • Was DDFS the best primary endpoint versus iDFS or regional failure:
        • SOUND chose DDFS to reflect oncologic safety independent of local RT nuances JAMA Network
    • Imaging vs surgery: 
      • Does negative AUS sufficiently replace pathologic staging in 2025 clinics, especially with modern systemic therapy selection? JAMA Network
    • RT heterogeneity: 
      • Could permissive RT (including IORT) have “rescued” regional control?
        • If so, why are axillary failures identically rare in both arms? JAMA Network
    • Younger HR+ / HER2- patients: 
      • Where do you draw the line for still doing SLNB given Rx-PONDER-type considerations? JAMA Network
    • Global impact: 
      • How would your clinic operationalize AUS-triaged omission (workflow, sonographer QA, documentation templates)? JAMA Network
    • How SOUND Aligns with INSEMA (one-paragraph takeaway):
      • INSEMA (NEJM 2024/2025) randomized cN0 BCT patients (T1 to T2 ≤ 5 cm) to omission vs SLNB:
        • Invasive DFS primary outcome was non-inferior, with less arm morbidity in the omission group
      • Together with SOUND (DDFS primary, ≤ 2 cm, AUS-negative), these trials support AUS-triaged omission of SLNB in carefully selected early breast cancers planned for BCS + RT New England Journal of Medicine+2PubMed+2