My name is Rodrigo Arrangoiz I am a breast surgeon/ thyroid surgeon / parathyroid surgeon / head and neck surgeon / surgical oncologist that works at Center for Advanced Surgical Oncology in Miami, Florida.
I was trained as a surgeon at Michigan State University from (2005 to 2010) where I was a chief resident in 2010. My surgical oncology and head and neck training was performed at the Fox Chase Cancer Center in Philadelphia from 2010 to 2012. At the same time I underwent a masters in science (Clinical research for health professionals) at the University of Drexel. Through the International Federation of Head and Neck Societies / Memorial Sloan Kettering Cancer Center I performed a two year head and neck surgery and oncology / endocrine fellowship that ended in 2016.
Mi nombre es Rodrigo Arrangoiz, soy cirujano oncólogo / cirujano de tumores de cabeza y cuello / cirujano endocrino que trabaja Center for Advanced Surgical Oncology en Miami, Florida.
Fui entrenado como cirujano en Michigan State University (2005 a 2010 ) donde fui jefe de residentes en 2010. Mi formación en oncología quirúrgica y e n tumores de cabeza y cuello se realizó en el Fox Chase Cancer Center en Filadelfia de 2010 a 2012. Al mismo tiempo, me sometí a una maestría en ciencias (investigación clínica para profesionales de la salud) en la Universidad de Drexel. A través de la Federación Internacional de Sociedades de Cabeza y Cuello / Memorial Sloan Kettering Cancer Center realicé una sub especialidad en cirugía de cabeza y cuello / cirugia endocrina de dos años que terminó en 2016.
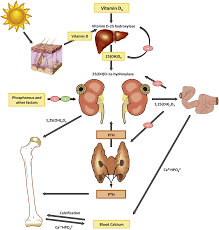
Parathyroid hormone (PTH) acts to raise blood calcium levels via its action on 3 organs. 1. The kidneys by Increased calcium reabsorption, Decreased phosphate reabsorption, Increased conversion of vitamin D to its final form – 1,25(OH) vitamin D; 2) Bones (increased resorption); 3) Intestines (increased absorption largely due to increased vitamin D in its final form).
Thyroid nodules are very common and frequently incidentally detected with the increasing use of imaging
The primary concern is how to identify those with suspicious features in order to avoid unnecessary diagnostic exams like fine-needle aspiration biopsy (FNAB) and overtreatment
Even though the Thyroid Imaging Reporting and Data System (TI-RADS):
Created by the American College of Radiologists:
Is widely accepted as an easy and useful tool to avoid unnecessary FNAB and close follow-up it still suffers from some biases, including experience and heterogeneity among sonographers
Contrast-enhanced ultrasound (CEUS) is a novel technology:
That can help differentiate between benign and malignant thyroid nodules
TI-RADS does not recommend FNAB for nodules up to 1 cm:
Even though such nodules have mild, moderate, or high (TI-RADS 3, 4, and 5, respectively) sonographic risk for malignancy
However, CEUS represents a new tool in the evaluation of thyroid nodules
The aim of this study was to compare the use of CEUS versus conventional ultrasound (as TI-RADS) in the risk stratification of thyroid nodules
Methods
In this study, 185 solid thyroid nodules between 0.5 and 1 cm in 154 patients were evaluated by conventional ultrasound and CEUS at the same time and by the same investigator
In conventional ultrasound, each target nodule was scored based on the components of:
Echogenicity, shape, edge, and strong echogenic focus, according to the 2017 edition of ACR TI-RADS in order to ascertain a TI-RADS classification
Qualitative indicators of CEUS analysis in the targeted thyroid nodules included:
Enhancement intensity, patterns of enhancement, internal homogeneity, the presence of perfusion defect, clearness of boundary, morphology, and size at enhance‐ ment peak
The CEUS characteristics of benign and malignant thyroid nodules with the significant differential diagnosis were scored, and the total scores of each thyroid nodule were calculated
Results
Of 185 thyroid nodules, the diagnosis was confirmed in 133 by surgical pathology, with 90 nodules (67.67%) showing papillary thyroid cancer (PTC) and 43 (32.33%) having benign results
In 52 thyroid nodules, cytology from the FNAB showed PTC in 11 nodules (21.15%) and nonmalignancy in 41 (78.85%)
Overall, there were 101 malignant thyroid nodules
When comparing the risk assessment scores:
CEUS outperformed TI-RADS using conventional ultrasound for benign diseases, but this was not the case in malignant nodules
Comparing the diagnostic performance between TI-RADS TR5 nodules and CEUS nodules that scored 5 points:
Sensitivity was 90.10% versus 86.13%, specificity 55.95% versus 89.29%, accuracy 74.59% versus 87.57%, positive predictive value 72.22% versus 90.63%, negative predictive value 82.46% versus 84.27%, and the area under the receiver-operating-characteristic curve 0.738 (95% CI, 0.663–0813) versus 0.916 (95% CI, 0.871– 0.961).
Conclusions
This study found that CEUS:
When evaluating small solid thyroid nodules, had higher diagnostic performance and a higher specificity than TI-RADS using conventional ultrasound
CEUS may be a valuable imaging tool to select patients with thyroid nodules for FNAB or surgery
Conventional ultrasound is currently the initial diagnostic tool for the risk stratification of thyroid nodules
To increase the diagnostic confidence and avoid unnecessary FNABs, many societies have proposed systems to stratify malignancy risks by ultrasound and guide physicians in when to perform FNAB:
One of the most popular and practical methods is TI-RADS
However, how to accurately differentiate malignant from benign nodules remains a significant challenge in many situations:
Since at least a half of all biopsied nodules are benign and up one third of FNABs are inconclusive
The new imaging method of CEUS can show tumor perfusion and vascular distribution after intravenous injection of a microbubble contrast agent:
Since vascular structures in the nodule differ from those of normal tissues
The specific characteristics of CEUS, like enhancement intensity, patterns of enhancement, and internal homogeneity, seem to be valuable in determining which nodules should undergo an FNAB and which may be kept under observation
In this study evaluating small nodules:
CEUS had significantly higher performance than TI-RADS in differentiating malignant from benign nodules:
Suggesting that CEUS qualitative analysis could be more effective in excluding malignant nodules and avoiding unnecessary biopsies
The use of CEUS in clinical practice has some crucial limitations, including the:
Cost of the exam, especially if the patient has more than one nodule to be analyzed:
Each nodule requires injection of a contrast agent
In addition, the small numbers of radiologists trained to perform this imaging study, as well as the absence of well-estab‐ lished criteria and consensus regarding the patterns of enhancement and classification of thyroid nodules, make its broad use in clinical practice controversial at present
Fine-needle aspiration (FNA) using the recently revised Bethesda System for Reporting Thyroid Cytopathology accurately discriminates benign from malignant thyroid nodules:
However, the risk of malignancy in each Bethesda category has been studied using inconsistent methods, and most studies focus on nodules with corresponding surgical histology, which introduces selection bias
The present study sought to determine the real-world risk of malignancy in each Bethesda category using data from a large retrospective cohort of thyroid nodules with a mixture of surgical and long-term population-based clinical follow-up
Methods
All thyroid FNAs from the University of California, San Francisco (UCSF) Pathology database (collected between January 1, 1997, and December 31, 2004) were reviewed and recoded using the 2017 Bethesda system reporting standard
If multiple nodules were biopsied and had different results, the highest-grade Bethesda category was used
Corresponding patients were matched to the UCSF cancer registry, along with the California Cancer Registry (CCR; a statewide, population-based registry)
Patients who were not detected in either registry were considered to be free of malignancy
Exclusion criteria included a prior diagnosis of thyroid cancer, prior thyroid surgery, or development of a cancer in the lobe con- tralateral to the biopsy site
The date of the original FNA was the time origin, and the interval time to repeat FNA, surgery, or final follow-up on July 10, 2015 (date of matching to the CCR), was recorded
Kaplan–Meier survival curves and Cox proportional hazards models were used to estimate incidence rates of malignancy for each category and the instantaneous risk of malignancy, respectively
Results
A total of 2233 patients with 2758 FNA reports were available:
26 were excluded, for a final count of 2207
The median age was 48 years (range, 7 to 92) and 1880 (85.2%) were female
Of the 2207 test results:
236 (10.7%) were determined to be nondi- agnostic
1575 (71.4%) benign
57 (2.58%) atypia of undetermined significance (AUS)
78 (3.53%) follicular lesion of undetermined significance (FLUS)
107 (4.85%) follicular neoplasm or Hürthle-cell neoplasm
20 (0.9%) suspicious for malignancy
134 (6.07%) malignant
Median follow-up after the initial FNA was 13.9 years (range, 10.5 to 18.4):
279 (12.6%) patients were diagnosed with thyroid malignancy during that period
Compared to the benign reference group, hazard ratios were:
2.09 (95% CI, 1.2–3.7) for a nondiagnostic read
8.8 (95% CI, 5.7–13.6) for AUS / FLUS
10.9 (95% CI, 7.0–17.0) for follicular neoplasm
49.1 (95% CI, 27.1–88.9) for suspicious for malignancy
201 (95% CI, 138–293) for a malignant read
When AUS and FLUS were split into separate categories:
AUS had a higher hazard ratio (13.0; 95% CI, 7.7–22.0)
Malignancy rates per 1000 person-years were:
4.82 (95% CI, 3.0–7.9) for a nondiagnostic read
2.42 (95% CI, 1.9–3.2) for a benign read
22.4 (95% CI, 16.0–31.6) for AUS / FLUS
29.1 (95% CI, 20.4–41.3) for follicular neoplasm
183 (95% CI, 108–310) for suspicious for malignancy, and 980 (CI) for a malignant read
A total of 52 (3.2%) of 1575 were false-negative results:
29 (1.7%) of which were papillary thyroid microcarcinomas
A total of 15 patients died from thyroid cancer:
None of them had an initial benign FNA
Conclusions
FNA and the Bethesda System for Reporting Thyroid Cytopathology are highly accurate in detecting thyroid malignancy
Long-term combined clinical and histopathologic follow-up reveal a low false-negative rate, low rates of malignancy in nondiagnostic specimens, and extremely low rates of mortality, especially in benign and nondiagnostic categories
Thyroid nodules are common:
5% to 15% of them are malignant:
The majority of which are well-differentiated thyroid cancers with a good prognosis
The Bethesda system has standardized reporting of thyroid nodule cytopathology:
Thereby facilitating efficient and precise communication, research, and articulation of evidence-based management guidelines:
However, even the most robust classification systems meet with variable adoption and implementation in the real-world clinical setting, and generalizability depends on validation in diverse popula- tions of patients and care systems
The present study sought to address two limitations in estimating risk of malignancy in validation studies:
Use of surgical histopathology as the gold standard:
Which leads to a higher estimated risk of malignancy in lower-risk nodules since they are less likely to undergo surgery
Inconsistent statistical handling of “indeterminate” categories:
Which have a wide range of preva- lence across institutions
Strengths of the study include:
A long duration of follow-up of a robust number of patients and use of an institutional and comprehensive population-based cancer registry to detect and provide a narrative summary of malignant cases and patient mortality
Limitations of the study include:
Its retrospective, single-institution design (which improves standardization at the cost of generalizability) and the assumption that patients without registry data did not develop malignancy, which misses patients who moved away or did not follow up, thereby underestimating the risk of malignancy
It is worth noting that even a median follow-up of 13.9 years is relatively short when dealing with an indolent disease, especially in light of long-term data showing minimal growth of biopsy-proven small papillary thyroid carcinomas
Given the marked indolence of most thyroid cancers, coupled with a high and rising incidence of small and incidental cancers:
Perhaps the most important task for clinicians is to avoid missing patients harboring clinically significant malignancy
The most notable aspect of this study is:
The confirmation that the false-negative rate for benign FNA was low, at 3.2%:
More than half of which were innocent papillary microcarcinomas), and that no patients with a false-negative FNA died of thyroid cancer
While risk of malignancy of nondiagnostic specimens was roughly double that of benign ones:
It was still relatively low, and the long-term outcomes for patients were similar
It is not surprising that thyroid cancer– related mortality was low (0.7%) across all categories during the follow-up period
Lastly, it was interesting that the AUS category had a higher risk of malignancy than FLUS:
When they were separated on the basis of nuclear (AUS) and architectural (FLUS) atypia:
While the Bethesda system designates AUS/ FLUS as a single category:
The current study corroborates others showing that subcategorization, while controversial, is worthy of discussion
Additional studies with large data sets and long-term follow-up are needed
Ultimately, while thoughtful management and longitudinal surveillance of patients with thyroid nodules requires integration of cytopathology with clinical and sonographic risk assessment:
It is reassuring to see confirmation that most patients with thyroid cancer do well, and that our standard-of- care approach of using FNA and Bethesda system reporting standards is accurate and rarely misses malignancy
Disease-specific survival for differentiated thyroid cancer (DTC) is lengthy and most profoundly impacted by:
Patient age (55 years)
Distant metastases
Extent of gross extrathyroidal extension (ETE)
Nodal status
Microscopic margin positivity (R1 margin):
Has shown no impact on local recurrence, but it has not been studied as:
A marker of completeness of resection
This National Cancer Database (NCDB) study evaluated the impact of R1 margin on overall survival in DTC to determine the presence of modifiable factors such as institutional annual thyroidectomy volume and hospital setting of thyroidectomy
Methods
The NCDB was queried for adults (ages 18 to 90) who underwent surgery from 2004 to 2016 for treatment of well- and moderately-differentiated thyroid carcinoma with a primary tumor size of 1 to 4 cm
Patients with histologically aggressive variants were excluded
Patients with gross ETE into the strap muscles (T3b); subcutaneous soft tissues, larynx, trachea, esophagus, or recurrent laryngeal nerve (T4a); or invading prevertebral fascia, encasing carotid or mediastinal vessels (T4b), or nodal disease were included if primary tumor size was less than 4 cm
Binary logistic-regression analyses evaluated factors affecting margin positivity after adjusting for confounders including age, gender, comorbidity score (modified Charlson–Deyo), extent of thyroid operation (lobectomy or total), margin status, lymphovascular invasion, multifocality, institutional annual case volume for thyroidectomy, and institu- tion type (community, comprehensive community, academic, or integrated network
Results
This study included 14,471 patients with DTC (median age, 47.52 years [range, 18–90]; 74.7% female)
After correcting for confounders, disease-specific (nonmodifiable) factors impacting survival included:
ETE:
25.2% of patients; OR, 1.47; P = 0.001), lateral neck nodal disease (12.6%; OR, 1.73; P = 0.001
Lymphovascular invasion:
15.7%; OR, 1.32; P = 0.044
R1 margin:
15.3%; OR, 1.46; P = 0.038
Modifiable factors impacting survival included:
Institutional case volume and type of facility:
Overall, institutions had a mean case volume of 30.3 thyroidectomies per year (range, 4 to 485):
When evaluating R1 margin status as a modifiable risk factor for survival:
Treatment in academic / research facilities (OR, 0.623; 95% CI, 0.527–0.738; P<0.001), integrated networks (OR, 0.782; 95% CI, 0.654–0.934; P = 0.009), or facilities with higher case volumes (OR, 0.979; 95% CI, 0.978–0.982; P = 0.004):
Was associated with lower odds of R1 margin
This study was sufficiently powered to detect a small impact of R1 margin on 8-year survival:
OR, 1.464; 95% CI, 1.039–2.121; P = 0.038
Conclusions
In this large database study:
R1 margin in DTC impacted overall survival
Modifiable risk factors associated with decreased risk of R1 margin were:
Treatment in an academic / research facility or integrated network and higher institutional annual case volume
As the thyroid gland has an incomplete capsule:
Interpreting an R1 margin as a prognostic indicator in DTC has been the source of some confusion
A meta-analysis of patients with DTC:
Found no association between R1 margin and local recurrence
This study aimed to evaluate the impact of negative versus R1 margins in a more homogeneous population of patients with smaller DTCs
The major modifiable factor in this study was care setting:
Higher-volume thyroid surgeons are more likely to operate in academic settings
Worldwide, higher individual surgeon volume for thyroidectomy (30 to 100 cases / year) is protective against complications and yields better oncologic outcomes
A similar NCDB study with a more heteroge- neous thyroid cancer population confirmed that treatment in an academic center was associated with a lower probability of R1 margin and higher overall survival
Rather than contradicting prior studies about the seeming irrelevance of R1 margin in DTC:
This study highlights how R1 margin may be a marker of incomplete resection when thyroidectomy is performed in low-volume centers
When I receive pathologic “positive margins,”assuming no ETE was present intraoperatively:
I generally reassure the patient that all tumor was appropriately resected:
However, this study raises important questions about how to interpret pathology reports documenting R1 margin from lower-volume centers
In contrast to this study’s findings of improvement in mean overall survival with negative margins:
Prior retrospective studies have not found that R1 margin impacts overall survival
Although this study corrected for confounders:
ETE was the variable most strongly correlated with an R1 margin (OR, 2.8):
ETE decreases survival in thyroid cancer, and it makes sense that ETE would be a natural continuation of R1 margins
However, further research is needed to determine the prognostic significance of thyroid cancers with positive inked margins without a finding of gross ETE
The past 10 to 15 years have seen two related paradigm shifts in the care of patients with papillary thyroid cancer:
Risk-stratification systems:
Have been developed and validated, which have allowed clinicians to recognize patients with an excellent prognosis
Treatment guidelines:
Have also undergone rapid change, particularly for patients with lower-risk cancers
These changes, which have led to a trend of less aggressive treatment of low-risk patients:
Have been controversial
One area of extreme controversy has been when to use postoperative radioactive iodine ablation
There are important reasons why the conser‐ vative use of radioactive iodine is ideal:
In the face of an excellent prognosis, salivary and lacrimal treatment-related adverse events, or even the potential of an increase in the rate of second cancers, become important:
However, proponents for the increased use of radioactive iodine point to:
Its usefulness in completing risk stratification
This study was a retrospective analysis of patient outcomes from a single Italian center (Sapienza University of Rome) before and after a policy change for the use of postoperative radioactive iodine
Prior to 2011 at this institution, most patients with papillary thyroid cancer had received radioactive iodine following total thyroidectomy as a standard procedure
In 2011, the default position changed for patients in whom the estimated risk of recur‐ rence was ≤ 8% and decision-making was deferred for approximately 12 months:
In this later group, delayed radioactive iodine ablation was recommended if:
The serum thyroglobulin concentration was ≥ 1 ng/mL
There is imaging evidence of persistent disease or
At the patients request
Methods
Patients initially treated between 2005 and June 2011 were managed in the more aggressive radioactive iodine era (cohort 1; 116 patients)
Cohort 2 included 156 patients initially treated from July 2011 to December 2018
Follow-up was performed 3 months after surgery and then at least yearly, with analysis performed at 12 months, 3 years after surgery, and at last contact
Outcomes were classified according to dynamic risk-stratification criteria validated for patients undergoing total thyroidectomy followed by radioactive iodine, as stratified by:
Excellent response:
No clinical, biochemical, or structural evidence of disease with a very sensitive cutpoint for serum thyroglobulin of ≤ 0.2 ng/ml)
Indeterminate response:
Detectable but low serum thyroglobulin levels, positive thyroglobulin antibodies, or abnormal but nonspecific imaging findings
Biochemical incomplete response:
Abnormal serum thyroglobulin levels or rising thyroglobulin antibodies
Structural incomplete response:
Identifiable locoregional or distant metastatic disease
Analyses were performed by comparing numbers of patients with structural incomplete response with those with other outcomes, and “gray-zone” responses (indeterminate or biochemical incomplete response) with “black-or-white” responses (excellent or structural incomplete responses)
Modeling approaches attempted to account for potential confounding
Results
In cohort 1, of the 116 patients, 90 (plus one additional patient during a median follow-up of 8 years) received postoperative radioactive iodine ablation
In cohort 2, of the 156 patients, 10 (plus three additional patients during a median follow-up of 4 years) received postoperative radioactive iodine
Apart from follow-up time, the only key tumor feature that differed between cohorts was a smaller median tumor size in the group from the later period (10 mm vs. 7 mm; range, 1–45 and 1–60 respectively)
Structurally incomplete responses were very rare in both cohorts and at all time points analyzed (1% to 3%, P=not significant)
Significantly higher proportion of gray-zone responses was apparent at 1 year of follow-up in cohort 2, driven mostly by the presence of more indeterminate responses due to serum thyroglobulin antibody positivity in that group (8.6% in cohort 1 vs. 18.6% in cohort 2)
While these statistically significant differences did not persist at final follow-up, gray-zone responses were very common and remained numerically higher in cohort 2 (30% in cohort 1 and 44% in cohort 2, from a combination of detectable serum thyroglobulin levels, persistent positive serum thyroglobulin antibodies, and non‐specific imaging findings
Conclusions
In this longitudinal cohort study, structural incomplete responses were rare in lower-risk papillary thyroid cancer patients, whether or not they received radioactive iodine ablation:
However, less use of postoperative radioactive iodine does lead to a higher rate of “uncertain” disease response status, at least initially
This study supports the success of modern risk-stratification systems in identifying patients with very low risk of structurally persistent or recurrent differentiated thyroid cancer:
Whether or not postoperative radioactive iodine ablation is given
It builds on previous work showing low rates of recurrence in appropriately selected patients treated with surgery alone and should not surprise those familiar with the literature
Clinicians can be reassured that withholding radioactive iodine in lower-risk patientsrarely results in the development of clinically significant recurrent disease:
Acknowledging that most patients treated in this study had small, localized tumors and that follow-up was relatively short
The other key message of the study is the trade-offs that occur between a more aggressive and a more conservative approach to radioactive iodine pre‐ scription:
At least in the short term, not administering postoperative radioactive iodine led to a lower chance of “certainty” in the success of the treatment response:
This gray-zone outcome was due to a combination of:
Nonspecific imaging findings being more common in patients not receiving radioactive iodine
Without a considered response, higher rates of gray-zone outcomes could lead to increased patient (and physician) anxiety and / or an increase in diagnostic procedures associated with hunting for low-volume structural recurrence
Limiting these possibilities (and the side effects of overtreatment with radioactive iodine) requires attention to the biology of each patient’s thyroid cancer, a care team working together with consistent communication, careful discus‐ sion with patients about how common gray-zone responses are and relating that the majority do not represent recurrent disease, and assessment of the trends in each patient’s biochemical and imaging response over time
Consultations take longer, and depending on a clinic’s imaging protocols, may result in an increase in ultrasound use to follow up on nonspecific imaging findings
Flexibility is also required, particularly in recognizing that some patients’ anxiety can be reduced only by radioactive ablation and that the rare requirement for delayed radioactive iodine administration is not necessarily a treatment failure
This study, therefore, adds a valuable contribution to the literature, in highlighting the issues of certainty trade-offs that occur with current trends toward less aggressive treatment of lower-risk differentiated thyroid cancers
The Union for International Cancer Control (UICC) and the American Joint Committee on Cancer (AJCC) tumor, node, metastasis (TNM) staging system:
Is designed to predict disease-specific survival
Differentiated thyroid cancer (DTC) is the only malignancy that includes an age cutoff in determining stage within this system
The previous AJCC 7th edition used an age cutoff of 45 years:
In which patients under the age of 45 could not be staged higher than stage II
While the updated 8th edition now uses 55 years:
As this threshold for both papillary thyroid cancer (PTC) and follicular thyroid cancer (FTC)
Multiple studies have shown age 55 years to be superior to 45 years as a cutoff for DTC, but questions remain on other potential age cutoffs for DTC
PTC and FTC are staged together as DTC, given their similar disease-specific survival:
Yet it has not been established whether PTC and FTC should have the same age cutoff, given that they can have different clinical courses:
PTC is more likely to have regional lymph node metastasis and FTC to have distant metastasis
The present study aims to investigate the optimal cutoff for the TNM staging the system for DTC, using the histopathologic criteria of the 8th edition, and also to examine optimal age cutoffs for both PTC and FTC
Methods
The current study is a retrospective analysis of two well-established databases from The Netherlands and Germany
Patients were age 18 years and above who were treated for either PTC or FTC between 2002 and 2016 (Erasmus Medical Center database) or between 1980 and 2015 (University of Würzburg database)
All patients underwent thyroid surgery and were treated according to standards at the time
Demographic, disease, treatment, and mortality data were obtained
Patients were reclassified using the histopathologic criteria from the TNM 8th edition with different age cutoffs
Age cutoffs were analyzed at 5-year increments from 20 up to 85 years and by 1-year increments between 35 and 55 years
Analysis was done for the combined DTC patient population and separately for PTC and FTC
Disease-specific survival was analyzed using the Kaplan–Meier method and compared across stages using the log-rank test
The concordance index (Harrell’s C-index), Akaike information criterion (AIC), and Bayesian information criterion (BIC) were used to assess the statistical model performance at different age cutoffs
The model with the highest C-index and lowest AIC and BIC was considered to be the best
Results
A total of 3074 patients were included (820 from Erasmus Medical Center and 2254 from University of Würzburg)
Of these patients, 2355 (77%) had PTC and 719 (23%) had FTC, with a median follow-up of 84 months
The mean age was 48.7 years, and 69.5% were female
Overall, 23.1% had lymph node metastasis and 8.8% had distant metastasis
When compared to patients with PTC, patients with FTC:
Were older (54.2 years vs. 47.1 years; P<0.001), more likely to be male (37.1% vs. 28.5%; P<0.001), less likely to have lymph node metastasis (9.2% vs. 27.3%; P<0.001), and more likely to have distant metastasis (18.2% vs. 6.0%; P<0.001)
Using the 8th edition’s age cutoff of 55 years, 2430 patients (79%) were classified as stage I, 384 (13%) as stage II, 88 (3%) as stage III, and 172 (6%) as stage IV
Lowering the age cutoff :
Lowered the number of patients in stage I
Increasing the age cutoff:
Increased the number of patients in stage
The 10-year disease-specific survival for DTC was 94.7% and was significantly higher for patients with PTC than for those with FTC (96.5% vs. 89.5%; P<0.001)
For DTC, PTC, and FTC, the majority of age cutoffs performed better in the statistical model than did no age cutoff
Using 5-year increments for the age cutoffs:
DTC and PTC had the best performance, with an age cutoff of 50 years
While FTC was 40 years
Using 1-year increments:
DTC performed best, at an age cutoff of 50 years, PTC at 48 years, and FTC at 41 years
Conclusions
When using the histopathologic criteria of the 8th edition TNM system:
The optimal age cutoff for DTC to predict disease-specific survival is 50 years, rather than 55 years as is currently in use
The optimal age cutoff for PTC is also 50 years
While the age cutoff for FTC should be 40 years:
Signifying that the age cutoffs for PTC and FTC should be different
In patients with American Thyroid Association (ATA) low-risk and ATA intermediate- risk DTC without extensive lymph node involvement (i.e., pT1 to pT3, cN0 / cNx/ pN1a, M0) in whom radioactive iodine (RAI) remnant ablation or adjuvant therapy is planned:
Preparation with rhTSH stimulation:
Is an acceptable alternative to thyroid hormone withdrawal for achieving remnant ablation:
Based on evidence of superior short-term quality of life, noninferiority of remnant ablation efficacy, and multiple consistent observations suggesting no significant difference in long-term outcomes
In patients with ATA intermediate-risk DTC who have extensive lymph node disease (multiple clinically involved LN) in the absence of distant metastases:
Preparation with rhTSH stimulation may be considered as an alternative to thyroid hormone withdrawal prior to adjuvant RAI treatment
In patients with ATA high-risk DTC with attendant higher risks of disease-related mortality and morbidity:
More controlled data from long-term outcome studies are needed before rhTSH preparation for RAI adjuvant treatment can be recommended
In patients with DTC of any risk level with significant comorbidity that may preclude thyroid hormone withdrawal prior to iodine RAI administration:
rhTSH preparation should be considered
Significant comorbidity may include:
A significant medical or psychiatric condition that could be acutely exacerbated with hypothyroidism, leading to a serious adverse event
Inability to mount an adequate endogenous TSH response with thyroid hormone withdrawal
If thyroid hormone withdrawal is planned prior to radioactive iodine (RAI) therapy or diagnostic testing:
Levothyroxine (LT4) should be withdrawn for 3 to 4 weeks
Liothyronine (LT3) may be substituted for LT4 in the initial weeks if LT4 is withdrawn for 4 or more weeks:
In such circumstances, LT3 should be withdrawn for at least 2 weeks
Serum thyroid stimulating hormone (TSH) should be measured prior to radioisotope administration to evaluate the degree of TSH elevation:
A goal TSH of greater than 30 mIU/L has been generally adopted in preparation for RAI therapy or diagnostic testing:
But there is uncertainty relating to the optimum TSH level associated with improvement in long-term outcomes
Thyrotropin stimulation before RAI remnant ablation / therapy or scanning has been a long-established standard of care because early observational research suggested that:
A TSH greater than 30 mIU/L was required for incompletely resected thyroid tumors to significantly concentrate 131I
There have been two RCTs comparing various thyroid hormone withdrawal protocols prior to therapeutic or diagnostic iodine radioisotope administration:
Lee et al. reported on an open-label, single-center study, in which 291 patients with well-differentiated thyroid cancer (TNM stage T1 to T3, N0 / N1a, M0) were randomized to either with- drawal LT4 for 4 weeks (n = 89), or withdrawal of LT4 for 4 weeks with substitution of LT3 for the first 2 weeks (n = 133), or recombinant human TSH (rhTSH; with withdrawal of LT4 for a few days from the time of the first rhTSH injection to radioisotope administration) (n = 69):
In this trial, all patients received 30 mCi of 131I for remnant ablation and were prescribed a 2-week low-iodine diet (LID) pre-ablation
Although the randomization method was unclear, the baseline characteristics (including pre-ablation urinary iodine measurements) were well balanced among groups
Furthermore, the pre-ablation TSH was greater than 30 in all patients in all groups in this trial, with no significant difference in mean pre- ablation TSH levels
Moreover, the primary outcome, which was the rate of successful remnant ablation at 12 months:
Was not significantly different among groups:
Range 91.0% to 91.7% among groups
Upon administration of questionnaires in a double-blind fashion, there was no significant difference in quality of life during preparation for RAI ablation, between the LT4 withdrawal group and the LT4 withdrawal with LT3 substitution group:
However, quality of life in both withdrawal groups prior to remnant ablation was significantly worse than after rhTSH preparation
Long-term outcome data from this trial were not reported
In a single-center trial, Leboeuf et al. randomized 20 individuals with well-differentiated thyroid cancer awaiting RAI remnant ablation or diagnostic scanning to:
LT4 withdrawal and either substitution of LT3 for 21 days, followed by 2 weeks off LT3, or identical-appearing placebo for LT3 for 21 days
In both groups, either the LT3 or placebo was withdrawn for another 2 weeks, and weekly measurements were performed for serum TSH, free thyroxine, and free triiodothy- ronine
The primary outcome was the hypothyroidism symptom score (Billewicz scale), which was ascertained in a double-blind fashion at time of LT4 withdrawal and every 2 weeks until the end of the study
The randomization method was a computer-generated number sequence; the LT3 group was significantly older than the placebo group (mean age 64 compared to 46), suggesting imbalance in the randomization
Disease stage of participants was not reported
Approximately 15% of participants withdrew from this trial
Leboeuf et al. reported no significant differences between the two thyroid hormone withdrawal protocol groups for hypothyroid symptom scores at any time point in the trial in a protocol-based analysis
At the time of ablation or whole-body scanning, the mean TSH was not significantly different between groups
In summary, available evidence from recent RCTs suggests that either direct LT4 withdrawal or LT4 withdrawal with substitution of LT3 in initial weeks is associated with similar short-term quality of life and hypothyroidism symptom scores; moreover, the remnant abla- tion success rate appears comparable
There is some conflicting observational evidence on whether any specific pre-RAI administration TSH level is associated with success of remnant ablation:
For example, in a secondary analysis of a RAI remnant ablation activity RCT, Fallahi et al:
Reported that a pre-RAI TSH of greater than 25 following (LT4 and LT3) thyroid hormone withdrawal was significantly associated with increased likelihood of successful remnant ablation (odds ratio 2.36, [95% CI 1.28–4.35], p=0.006), after adjustment for RAI activity, baseline serum Tg, on-LT4 TSH level, sex, age, histology, baseline RAI up-take, and extent of surgery
In two retrospective studies, each including several hundred DTC patients who underwent thyroid hormone withdrawal, no significant association was observed between pre-RAI TSH and rate of successful remnant ablation, in respective multivariable analyses adjusted for relevant variables such as disease extent, 131I activity, and gender:
However, results of these two studies may not necessarily be extrapolated to TSH levels below 30 mU/L, given that patients with such TSH thresholds were not generally considered eligible for RAI ablation in these studies
Pre–RAI ablation TSH was not a significant predictor of becoming disease free without further treatment in a secondary subgroup analysis of 50 patients who underwent thyroid hormone with- drawal, but the small number of patients in this subgroup may have limited the statistical power for a multivariate analysis
In summary, there is some uncertainty on the optimal level pre–RAI treatment TSH following thyroid hormone withdrawal in considering long-term outcome effect
Depending on the postoperative risk stratification of the individual patient:
The primary goal of postoperative administration of RAI after total thyroidectomy may include:
RAI remnant ablation:
To facilitate detection of recurrent disease and initial staging by tests such as Tg measurements or whole-body RAI scans)
RAI adjuvant therapy:
Intended to improve disease-free survival by theoretically destroying suspected, but unproven residual disease, es- pecially in patients at increased risk of disease recurrence)
RAI therapy:
Intended to improve disease-specific and disease-free survival by treating persistent disease in higher risk patients)
Additional considerations in RAI decision-making may include:
Patient comorbidities (and the potential impact of therapeutic doses of RAI or preparation for the procedure)
Feasible or preferred disease surveillance procedures
Patient preferences:
The latter being particularly important when clear data on therapeutic efficacy are lacking), or others