Blog

Primary Hyperparathyroidism (PHPT)

Introduction

  • Primary hyperparathyroidism (PHPT) is caused by increased secretion of parathyroid hormone (PTH) by the parathyroid gland(s):
    • Which leads to an elevated serum calcium level.
  • Single gland disease:
    • Caused by a single, enlarged, overactive gland:
      • Is found in over 85% to 90% of the cases.
    • Multiple gland disease occurs in 10% to 15% of cases:
      • Multiple gland disease may consist of:
        • Double adenomas:
          • 6% to 9% of the cases
        • Four-gland hyperplasia
          • 3% of the cases
        • Three enlarged and one normal appearing gland:
          • 0.3% of the cases.
      • Because asymmetric hyperplasia is common:
        • It is difficult to distinguish between multiple adenomas and hyperplasia and the term multiple gland disease is preferred.
  • PHPT in the United States usually presents quite early:
    • Often when hypercalcemia is noted during routine laboratory testing and the patients has minimal symptoms.
  • Signs may include:
    • Nephrolithiasis (kidney stones)
    • Decreased bone density (osteopenia or osteoporosis)
    • Fragility fractures
    • Subjective symptoms may include:
      • Fatigue, cognitive changes, depression, emotional lability, anxiety, irritability, decrease social interaction, constipation and other gastrointestinal complaints (abdominal pain, nausea, anorexia, GERD), musculoskeletal pain, point pain, bone pain nocturia, muscle weakness and rarely pruritus.
    • Most patients will be symptomatic if a detailed history is performed.
  • A family history of endocrine disorders should be investigated, as hyperparathyroidism alone can be familial or can present as a component of multiple endocrine neoplasia (MEN) types 1 and 2A.

Diagnostic Evaluation 

  • A biochemistry panel consisting of:
    • Serum total calcium, PTH level, creatinine, and 25-OH vitamin D should be obtained.
  • An inappropriately elevated PTH level is the disease hallmark on laboratory examination.
  • Calcium and PTH are tightly regulated and need to be evaluated concurrently when considering hyperparathyroidism
PHPT
Regulation of calcium homeostasis
  • In a patient with hypercalcemia:
    • A PTH level at the upper normal range is inappropriately elevated and indicative of PHPT.
  • Normocalcemic PHPT is a condition characterized by a:
    • Normal total and ionized calcium level
    • Elevated PTH
    • No other etiology for secondary hyperparathyroidism:
      • Chronic kidney disease
      • Vitamin D deficiency
      • Medications
      • Renal hypercalciuria
      • Malabsorption syndromes
    • The natural history of this variant includes:
      • Stability or progression toward hypercalcemia.
  • Uncommonly, patients with PHPT can present with hypercalcemic crisis:
    • Which occurs when the serum calcium level is markedly elevated and often presents with symptoms of mental status changes.
    • Treatment starts with:
      • IV hydration with or without forced diuresis
      • Followed by bisphosphonates.
      • Some patients may require calcitonin, glucocorticoids, or even dialysis.
  • 25-OH vitamin D level should be measured:
    • Vitamina D deficiency is a common occurrence in classic PHTP (elevated calcium and elevated PTH).
    • In patients with posible normocalcemic PHPT and a low 25 OH vitamin D level:
      • Secondary hyperparathyroidism due to vitamin D deficiency should be rule out.
    • Other laboratory values that could also be measured include:
      • A serum phosphorus level,:
        • Which is low or low normal in PHPT
      • Alkaline phosphatase activity:
        • Which when elevated, is an indication of more active bone disease.
      • A 24-hour urine for calcium and creatinine is obtained:
        • To rule out familial hypocalciuric hypercalcemia and assess for the presence of high urinary calcium excretion:
          • If elevated, a stone risk profile is recommended.
    • A bone density study may be useful in helping to determine the need for surgery.
    • An abdominal film, CT, and MRI may identify asymptomatic nephrolithiasis but are not a routine part of the work-up.
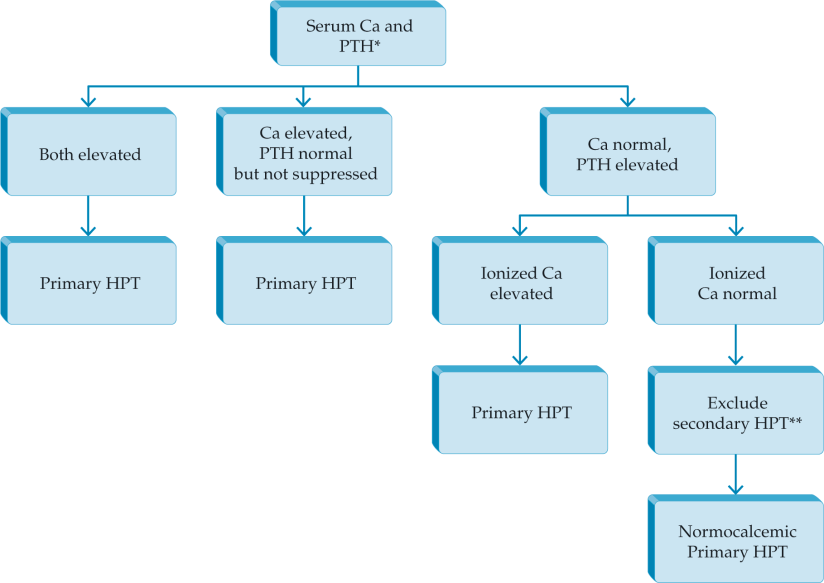
PHPT
Algorithm for the Diagnosis of PHPT 
  • Sestamibi:
    • The most widely used imaging study is the sestamibi scan:
      • Identifies an abnormal parathyroid gland 60% to 90% of the time.
    • The radioisotope is taken up by the thyroid and parathyroid glands and over time (45 to 90 minutes) washes out of the thyroid gland, leaving uptake in the enlarged parathyroid gland(s)
    • Variations of the technique include:
      • SPECT
      • Subtraction using 99Tc pertechnetate thyroid scan
      • SPECT-CT fusion:
        • The study is useful in detecting mediastinal adenomas (the chest should always be imaged) and can obviate a neck exploration in small number of patients with mediastinal adenomas.
  • Limitations of sestamibi include:
    • Low sensitivity for small adenomas and multiple gland disease.
    • The addition of SPECT and SPECT-CT adds to anatomic definition.

PHPT
Localization of abnormal parathyroid on imaging.
  • Ultrasound:
    • Neck ultrasonography is a complementary imaging study.
    • The sensitivity ranges from 60% to 80% and provides more detailed anatomic information for operative planning.
    • Ultrasonography also identifies concomitant thyroid pathology:
      • Present in 30% to 50%:
        • Which could be simultaneously addressed if necessary during parathyroidectomy.
  • 4D CT scan:
    • Four-dimensional CT is a highly accurate and anatomically specific method of localizing parathyroid adenomas and may be superior to ultrasonography and sestamibi in detecting multiple gland disease.
    • It captures images of the neck before, during, and after contrast infusion:
      • Can distinguish between lymph nodes and abnormal parathyroid glands
    • It subjects the patient to significant radiation exposure and contrast dye load.
    • It is very useful in reoperative parathyroid surgery and has largely replaced selective venous sampling for localization in these difficult cases.

Rodrigo Arrangoiz MS, MD, FACS cirujano de tumores de cabeza y cuello / cirugía endocrina / cirugía oncológica miembro de Sociedad Quirúrgica S.C. experto en el manejo del hiperparatiroidismo:

Rodrigo Arrangoiz MS, MD, FACS es miembro de la American Thyroid Association:

2019 membership certificate arrangoiz, rodrigo

Publicaciones sobre el hiperparatiroidismo:


Rodrigo Arrangoiz MS, MD, FACS cirujano de tumores de cabeza y cuello / cirugía endocrina / cirugía oncológica miembro de Sociedad Quirúrgica S.C. pionero en México de la paratiroidectomia radioguiada mínimamente invasiva:


Entrenamiento:

  • Cirugia general y gastrointestinal:

• Michigan State University: 2004- 2010


image-48

• Cirugia oncológica / tumores de cabeza y cuello / cirugia endocrina:

• Fox Chase Cancer Center (Filadelfia):

• 2010 al 2012
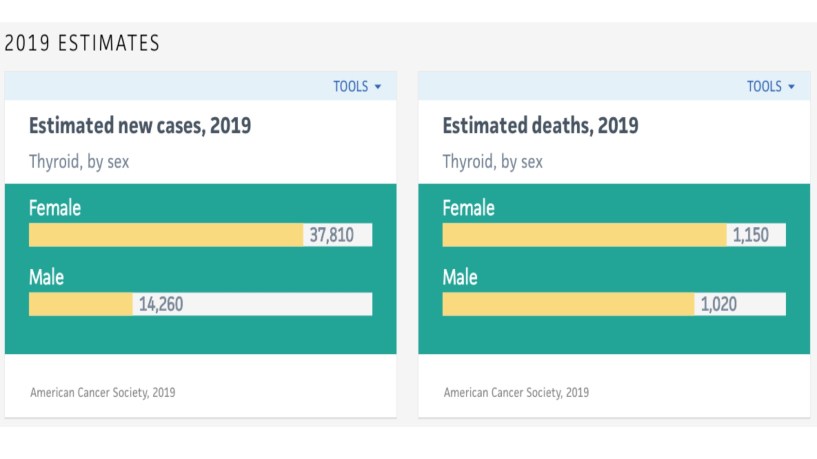
image-39

• Maestria en ciencias (Clinical research for healthprofessionals):

• Drexel University (Filadelfia):

• 2010 al 2012
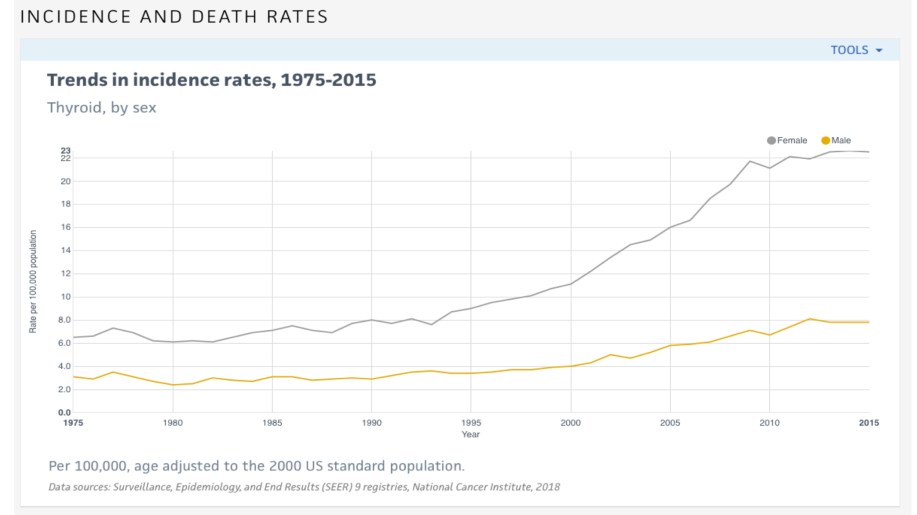
image-50

• Cirugia de tumores de cabeza y cuello / cirugiaendocrina

• IFHNOS / Memorial Sloan Kettering Cancer Center:

• 2014 al 2016

image-51

http://www.sociedadquirurgica.com

http://www.hiperparatiroidismo.info

http://www.cirugiatiroides.com

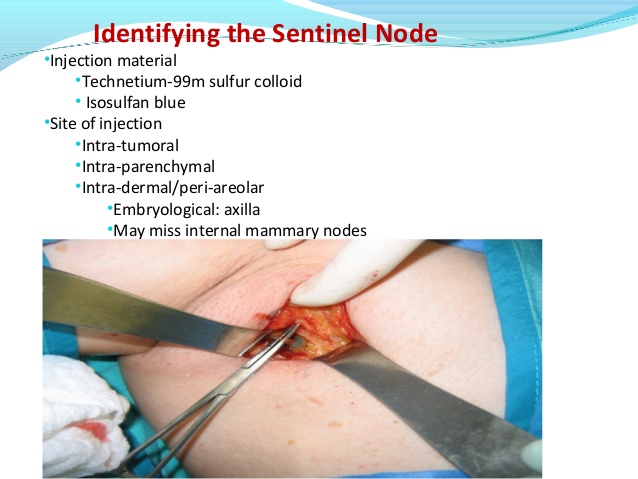
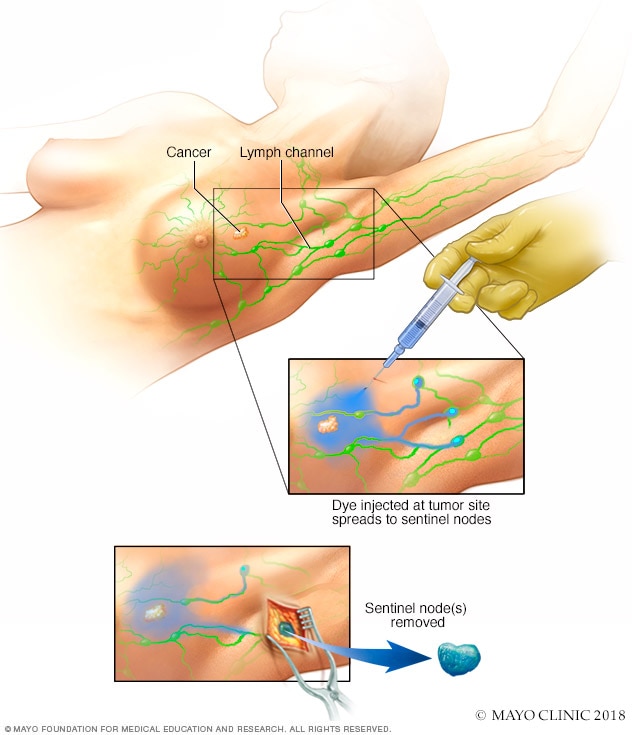
Can you perform a Sentinel Lymph Node Mapping and Biospy (SLNM and SLNB) after Breast or Axillary Surgery?

breast-cancer-14-638

  • In 2014, The American Society of Clinical Oncology (ASCO) Guidelines were updated and published on the use of SLNB for early-stage breast cancer:
    • A strong recommendation was made for re-operative SLNM and SLNB in women who have undergone prior breast or axillary surgery.
  • There are now multiple reports of successful second SLNM and SLNB in patients with a local breast cancer recurrence following a previous SLNB or even axillary lymph node dissection (ALND):
    • In a recent systematic review and meta-analysis of studies on repeat SLNB in locally recurrent breast cancer found that sentinel node identification was successful in 452 of the 692 patients (65.3%):
      • This percentage was significantly higher in patients who had undergone previous SLNB compared to previous ALND:
        • 81.0% vs 52.2%.
      • In most of these studies, a dual tracer technique, with use of blue dye and radiocolloid, was performed.
      • Aberrant drainage pathways were demonstrated in 43% of patients:
        • More frequently after previous ALND than after previous SLNB:
          • 69.2% vs 17.4%.
        • Lymphoscintigraphy, including examination of the contralateral axilla:
          • Should be performed if repeat SLNB is planned:
            • Given that these patients often have alternate drainage patterns.

sentinel-lymph-node-concept-in-early-breast-cancer-by-prof-r-wasike-19-638bc-3650984-001-8colbreast-cancer

REFERENCES

  • Lyman GH, Temin S, Edge SB, et al. Sentinel lymph node biopsy for patients with early-stage breast cancer: American Society of Clinical Oncology Clinical Practice Guideline update. J Clin Oncol. 2014; 32:1365-1383.
  • Maaskant-Braat AJ, Voogd AC, Roumen RM, et al. Repeat sentinel node biopsy in patients with locally recurrent breast cancer: a systematic review and meta-analysis of the literature. Breast Cancer Res Treat. 2013;138:13-20.

Rodrigo Arrangoiz MS, MD, FACS a surgical oncologist and is a member of Sociedad Quirúrgica S.C at the America British Cowdray Medical Center in Mexico City:

  • He is an expert in the management of breast cancer.

    • If you have any questions about SLNM and SLNB is recurrent breast cancer please fill free to contact Dr. Arrangoiz.

Training:

• General surgery:

• Michigan State University:

• 2004 al 2010
• Surgical Oncology / Head and Neck Surgery / Endocrine Surgery:

• Fox Chase Cancer Center (Filadelfia):

• 2010 al 2012
• Masters in Science (Clinical research for health professionals):

• Drexel University (Filadelfia):

• 2010 al 2012
• Surgical Oncology / Head and Neck Surgery / Endocrine Surgery:

• IFHNOS / Memorial Sloan Kettering Cancer Center:

• 2014 al 2016

#Arrangoiz

#Surgeon

#Cirujano

#SurgicalOncologist

#CirujanoOncologo

#BreastSurgeon

#CirujanodeMama

#CancerSurgeon

#CirujanodeCancer

http://www.sociedadquirurigca.com


img_0832-2img_0833-2img_0834-2img_0835-2img_0836-2img_0837-2

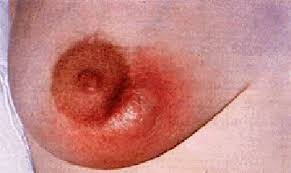
Peripartum or Lactational Mastitis


mastitis

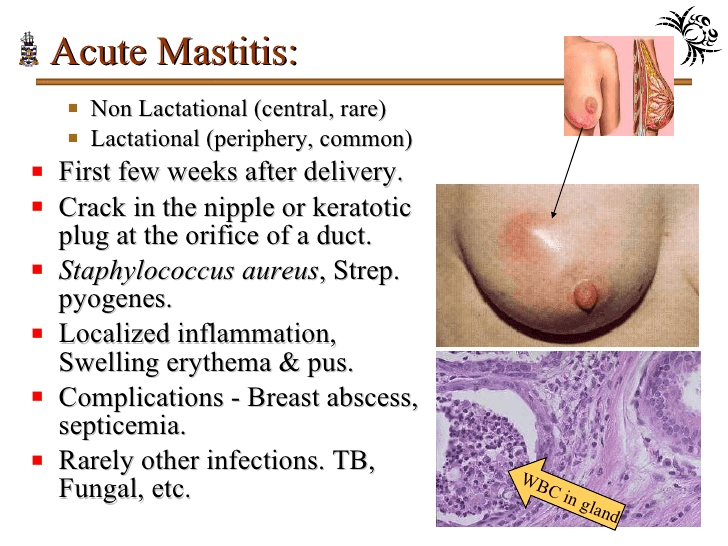
  • Peripartum or lactational mastitis and abscess formation is an uncommon occurrence affecting less than 10% of lactating mothers:
    • In the past, incision and drainage with prolonged packing and cessation of breastfeeding has been the primary method of treatment.

unknownimages

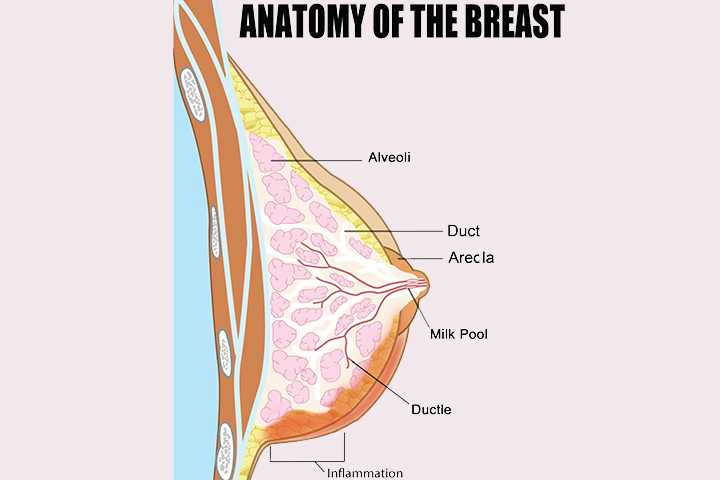
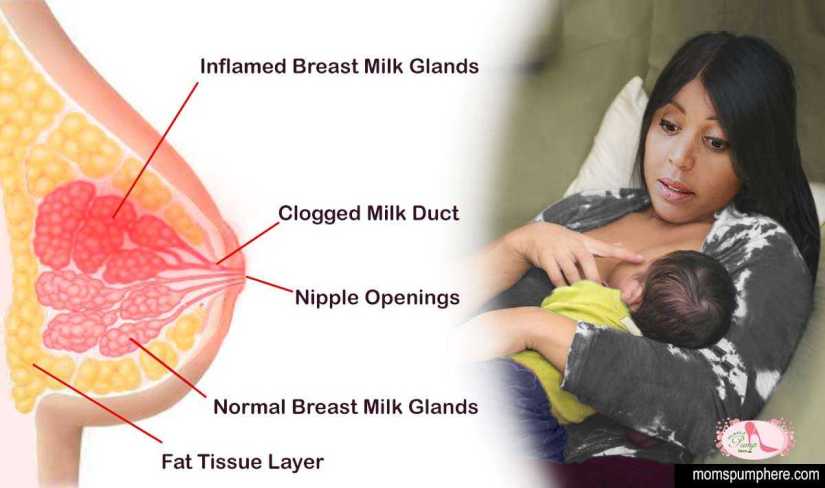
  • The etiology of lactational abscess results from milk duct blockage with resultant milk stasis and superimposed bacterial infection from the skin or mouth flora of the nursing infant:
    • Microbiology often reveals staphylococcal organisms.

mastitis-breastfeeding-diagram

  • A modern series report of multidisciplinary management with serial aspiration and appropriate antibiotics suggests a more conservative treatment is appropriate:
    • This study reviewed 41 abscesses of which 22 were treated with aspiration alone and 19 required aspiration and incision and drainage:
      • The primary reason for incision and drainage was lack of improvement or recurrence (N=12) or presence of a fistula (N=3).

mastistis

REFERENCES

  • Giess CS, Golshan M, Flaherty K, et al. Clinical experience with aspiration of breast abscesses based on size and etiology at an academic medical center. J Clin Ultrasound. 2014: 42:513-521.
  • Meguid MM, Kort KC, Numann PJ, et al. Subareolar breast abscess: the penultimate stage of the mammary duct-associated inflammatory disease sequence. In: Bland KI, Copeland EM III, eds. The Breast: Comprehensive Management of Benign and Malignant Disorders. 4th ed. Philadelphia (PA): Saunders Elsevier; 2009:107-144.
  • Trop I, Dugas A, David J, et al. Breast abscesses: evidence-based algorithms for diagnosis, management, and follow-up. Radiographics. 2011;31:1683-1699.


Rodrigo Arrangoiz MS, MD, FACS a surgical oncologist and is a member of Sociedad Quirúrgica S.C at the America British Cowdray Medical Center in Mexico City:

  • He is an expert in the management of breast cancer.

    • If you have any questions about lactational mastitis please fill free to contact Dr. Arrangoiz.

Training:

• General surgery:

• Michigan State University:

• 2004 al 2010

• Surgical Oncology / Head and Neck Surgery / Endocrine Surgery:

• Fox Chase Cancer Center (Filadelfia):

• 2010 al 2012

• Masters in Science (Clinical research for health professionals):

• Drexel University (Filadelfia):

• 2010 al 2012

• Surgical Oncology / Head and Neck Surgery / Endocrine Surgery:

• IFHNOS / Memorial Sloan Kettering Cancer Center:

• 2014 al 2016

#Arrangoiz

#Surgeon

#Cirujano

#SurgicalOncologist

#CirujanoOncologo

#BreastSurgeon

#CirujanodeMama

#CancerSurgeon

#CirujanodeCancer

http://www.sociedadquirurigca.com

img_0832-2img_0833-2img_0834-2img_0835-2img_0836-2img_0837-2

Angiosarcoma (AS) of the Breast

  • Angiosarcoma (AS) of the breast is rare:
    • Accounting for far less than 1% of all soft tissue breast tumors.
  • It presents as a primary tumor of the breast or as a secondary lesion most commonly associated with previous radiotherapy:
    • Primary AS has been observed in women ages 30 to 50 years presenting with poorly defined masses.
    • It accounts for less than 0.04% of malignant neoplasms.
    • Typically arises in the parenchyma of the breast, and has occasional skin involvement.
    • Women with primary AS usually present with a palpable mass, fullness or swelling in the breast:
      • Which at times can be rapidly growing.
  • In contrast, secondary AS presents in older women (median age 67 to 71 years) following a median of 10.5 years after radiotherapy for breast cancer:
    • The median latency to presentation after radiotherapy in 7 series ranges from 5 to 10 years.
    • Although a causal relationship between radiation exposure and AS has not been established, multiple case reports support the increased risk for AS following adjuvant radiotherapy:
      • It has been proposed that at radiation doses greater than 50 Gy, apoptosis occurs while at less than 50 Gy DNA damage and instability result.
    • Sarcomas frequently occur at the edge of radiation fields where doses and tumor necrosis may be heterogeneous.
    • When associated with chronic lymphedema and located outside a radiated field:
      • AS in an edematous limb after mastectomy and radiotherapy is referred to as Stewart–Treves syndrome.
    • Secondary AS presents as painless bruising that is frequently multifocal but can present with a mass:
      • It is often neglected because of its seemingly innocent appearance.
      • There are other varied descriptions of the presenting signs including :
        • Purplish discoloration, eczematous rash, hematoma-like swelling, and diffuse breast swelling.

4.31.1.item

  • Kasabach–Merritt syndrome, also known as hemangioma with thrombocytopenia, is a rare disease in which vascular tumors lead to platelet sequestration and hemorrhage:
    • Although it occurs primarily in infants with hemangioma, rarely has it been reported in angiosarcomas.
  • On histopathological analysis the lesions are notable for irregular vascular formations with hyperchromatic and irregular nuclei (Figure ):

4.31.1.critique

  • The diagnosis can be clarified by immunohistologic staining for the endothelial marker CD31 as in this case which determines the tumor is of endothelial origin:
    • CD31 is the most sensitive and specific indicator of angiogenic proliferation; however, the lesions will also stain positive for the vascular markers:
      • Factor VIII, and Fli1, and will usually at least be weakly positive for CD34.


Rodrigo Arrangoiz MS, MD, FACS a surgical oncologist and is a member of Sociedad Quirúrgica S.C at the America British Cowdray Medical Center in Mexico City:

  • He is an expert in the management of breast cancer.

    • If you have any questions about angiosarcoma of the breast cancer  please fill free to contact Dr. Arrangoiz.

Training:

• General surgery:

• Michigan State University:

• 2004 al 2010

• Surgical Oncology / Head and Neck Surgery / Endocrine Surgery:

• Fox Chase Cancer Center (Filadelfia):

• 2010 al 2012

• Masters in Science (Clinical research for health professionals):

• Drexel University (Filadelfia):

• 2010 al 2012

• Surgical Oncology / Head and Neck Surgery / Endocrine Surgery:

• IFHNOS / Memorial Sloan Kettering Cancer Center:

• 2014 al 2016

#Arrangoiz

#Surgeon

#Cirujano

#SurgicalOncologist

#CirujanoOncologo

#BreastSurgeon

#CirujanodeMama

#CancerSurgeon

#CirujanodeCancer

http://www.sociedadquirurigca.com


img_0832-2img_0833-2img_0834-2img_0835-2img_0836-2img_0837-2

Human Epidermal Growth Factor Receptors

  • Human epidermal growth factor receptors (HER/ErbB) include 4 cell-surface membrane tyrosine kinase receptors:

    • That transmit signals overseeing normal cell growth and differentiation:

      • HER receptors occur as both monomers and dimers:

        • Homodimers

        • Heterodimers

  • HER2 oncogene is a member of the human epidermal growth factor receptor family located on chromosome 17q12:

    • All 4 HER receptors are transmembrane single subunit glycoproteins:

      • That have an:

        • Extracellular ligand-binding domain

        • A transmembrane domain

        • Intracellular tyrosine kinase catalytic domain.

    • On ligand activation, the receptors dimerize forming homodimers or heterodimers:

      • This is followed by transphosphorylation which activates several intracellular signaling pathways such as:

        • Ras/mitogen-activated protein kinase pathway

        • The phosphatidylinositol 3 kinase (PI3K)/Akt pathway

        • The Janus kinase/signal transducer and activator of transcription pathway

        • The phospholipase C pathway:

          • All of this pathways ultimately affects cell proliferation, survival, motility, and adhesion.

  • Ligand binding to HER1, HER3, or HER4 results in receptor dimerization:

    • Primarily with HER2 as the dimer partner.

  • HER2-containing heterodimers produce stronger intracellular signals than other HER combinations:

    • Normal cells have few HER2 receptors at the cell surface leading to very few heterodimers and thus weak and easily controlled intracellular signals.

    • HER2 overexpression results in increased HER2 receptors, increased opportunity for HER2 heterodimers, stronger intracellular signals, and malignant growth.

    • There is no known ligand for HER2 receptors to form homodimers.

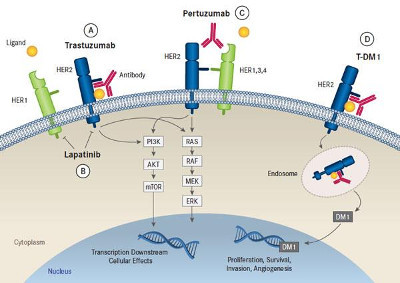
    • HER receptors and known HER2 antibodies are listed in Figure below:4.28.1.critique

  • HER2 amplification is the primary pathway of HER2-receptor overexpression and is a major driver of tumor development and progression in about 15% to 20% of breast cancers.

    • The overexpressed HER2 receptor is a valuable therapeutic target.

      • The 2013 ASCO CAP guidelines mandate that HER2 should be evaluated in every invasive breast cancer, whether primary or recurrence, to guide therapy.

Rodrigo Arrangoiz MS, MD, FACS a surgical oncologist and is a member of Sociedad Quirúrgica S.C at the America British Cowdray Medical Center in Mexico City:

  • He is an expert in the management of breast cancer.

    • If you have any questions about HER2 positive breast cancer  please fill free to contact Dr. Arrangoiz.

Training:

• General surgery:

• Michigan State University:

• 2004 al 2010

• Surgical Oncology / Head and Neck Surgery / Endocrine Surgery:

• Fox Chase Cancer Center (Filadelfia):

• 2010 al 2012

• Masters in Science (Clinical research for health professionals):

• Drexel University (Filadelfia):

• 2010 al 2012

• Surgical Oncology / Head and Neck Surgery / Endocrine Surgery:

• IFHNOS / Memorial Sloan Kettering Cancer Center:

• 2014 al 2016

#Arrangoiz

#Surgeon

#Cirujano

#SurgicalOncologist

#CirujanoOncologo

#BreastSurgeon

#CirujanodeMama

#CancerSurgeon

#CirujanodeCancer

http://www.sociedadquirurigca.com


img_0832-2img_0833-2img_0834-2img_0835-2img_0836-2img_0837-2

January Thyroid Awareness Month

images-1imagesimagesPaginas de internet para información sobre enfermedades de la glándula tiroides:

20d943b1-6f20-49c3-9754-2f3756051c9312fc1993-1232-40ac-91a0-f394c7a8de2e2131cd57-aa86-4187-801d-bb4d2ab2d6ef5b081828-c940-488d-bd45-21f33bd5f84f

Rodrigo Arrangoiz MS, MD, FACS cirujano de tumores de cabeza y cuello / cirugía endocrina / cirugía oncológica miembro de Sociedad Quirúrgica S.C. experto en el manejo del cáncer de tiroides:

  • Cumple con los requisitos determinados por el Dr. Ashok Saha para realizar cirugía de tiroides de manera efectiva y segura:

Rodrigo Arrangoiz MS, MD, FACS es miembro de la American Thyroid Association:

2019 membership certificate arrangoiz, rodrigo

Entrenamiento:

  • Cirugia general y gastrointestinal:

• Michigan State University:

• 2004 al 2010image-48

• Cirugia oncológica / tumores de cabeza y cuello / cirugia endocrina:

• Fox Chase Cancer Center (Filadelfia):

• 2010 al 2012

image-39

• Maestria en ciencias (Clinical research for healthprofessionals):

• Drexel University (Filadelfia):

• 2010 al 2012

image-50

• Cirugia de tumores de cabeza y cuello / cirugiaendocrina

• IFHNOS / Memorial Sloan Kettering Cancer Center:

• 2014 al 2016

image-51

http://www.sociedadquirurgica.com

http://www.hiperparatiroidismo.info

http://www.cirugiatiroides.com

Enero Mes de la Educación en Enfermedades de la Glándula Tiroides / January Thyroid Awareness Month

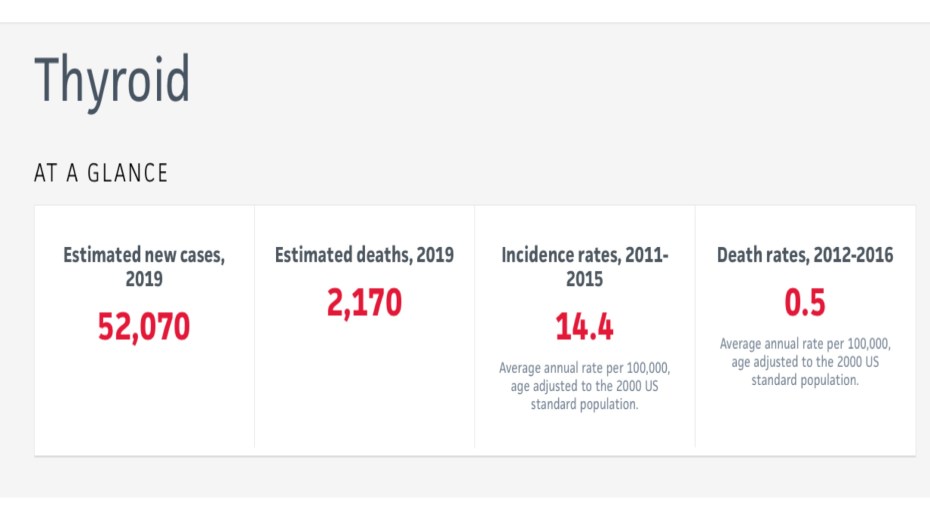
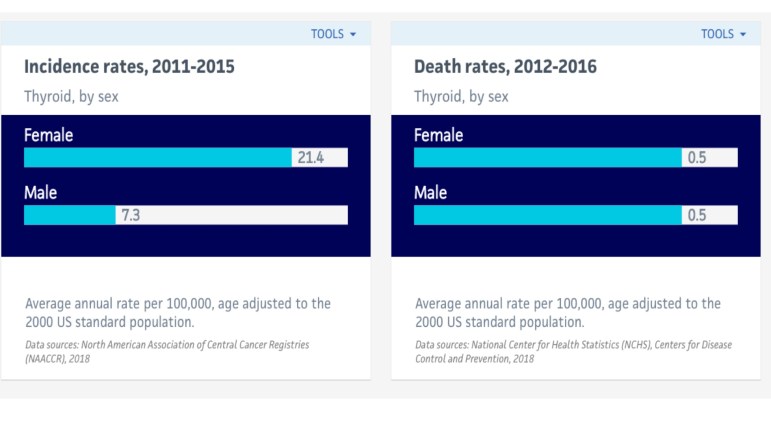
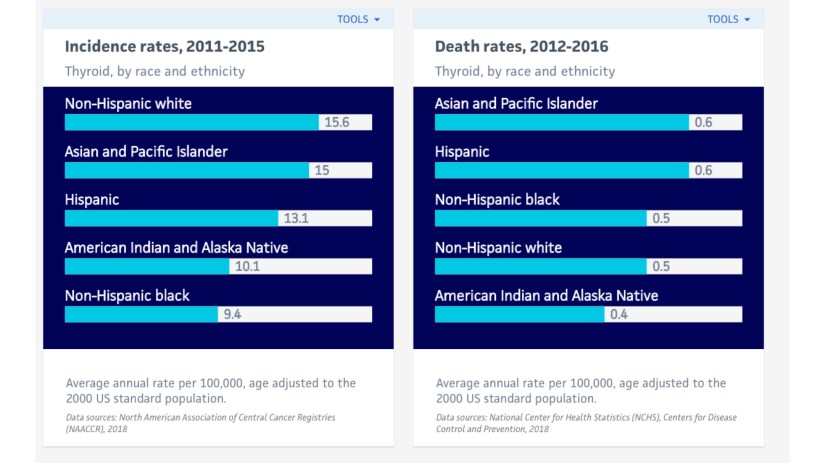
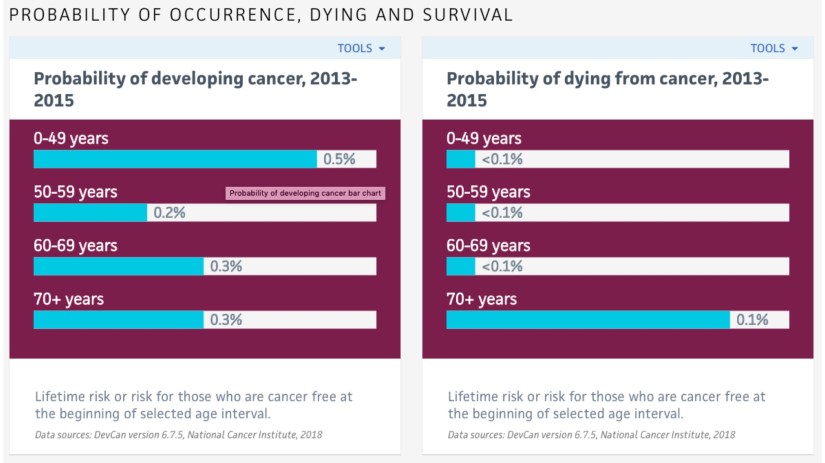
Epidemiología sobre el cáncer de tiroides / Thyroid cancer epidemiology:

thyroid 1thyroid 2thyroid 3thyroid 4thyroid 5thyroid 6

thyroid 7

Rodrigo Arrangoiz MS, MD, FACS cirujano de tumores de cabeza y cuello / cirugía endocrina / cirugía oncológica miembro de Sociedad Quirúrgica S.C. experto en el manejo del cáncer de tiroides:

  • Cumple con los requisitos determinados por el Dr. Ashok Saha para realizar cirugía de tiroides de manera efectiva y segura:

Rodrigo Arrangoiz MS, MD, FACS es miembro de la American Thyroid Association:

2019 membership certificate arrangoiz, rodrigo

Entrenamiento:

  • Cirugia general y gastrointestinal:

• Michigan State University:

• 2004 al 2010image-48

• Cirugia oncológica / tumores de cabeza y cuello / cirugia endocrina:

• Fox Chase Cancer Center (Filadelfia):

• 2010 al 2012

image-39

• Maestria en ciencias (Clinical research for healthprofessionals):

• Drexel University (Filadelfia):

• 2010 al 2012image-50

• Cirugia de tumores de cabeza y cuello / cirugiaendocrina

• IFHNOS / Memorial Sloan Kettering Cancer Center:

• 2014 al 2016

image-51

http://www.sociedadquirurgica.com

http://www.hiperparatiroidismo.info

http://www.cirugiatiroides.com


#Arrangoiz

#CirugiadeTumoresdeCabezayCuello

#CirugiaEndocrina

#CirugiaOncologica

#HeadandNeckSurgery

#EndocrineSurgery

#SurgicalOncology


Thyroid Awareness Month / Mes de Educación sobre Enfermedades Tiroideas

Rodrigo Arrangoiz MS, MD, FACS cirujano de tumores de cabeza y cuello / cirugía endocrina / cirujano oncólogo miembro de Sociedad Quirúrgica S.C. experto en el manejo del cáncer de tiroides:

Rodrigo Arrangoiz MS, MD, FACS es miembro de la American Thyroid Association.

Entrenamiento:

  • Cirugia general y gastrointestinal:

• Michigan State University:

• 2004 al 2010image-48

• Cirugia oncológica / tumores de cabeza y cuello / cirugia endocrina:

• Fox Chase Cancer Center (Filadelfia):

• 2010 al 2012

image-39

• Maestria en ciencias (Clinical research for healthprofessionals):

• Drexel University (Filadelfia):

• 2010 al 2012image-50

• Cirugia de tumores de cabeza y cuello / cirugiaendocrina

• IFHNOS / Memorial Sloan Kettering Cancer Center:

• 2014 al 2016

image-51

http://www.sociedadquirurgica.com

http://www.hiperparatiroidismo.info

http://www.cirugiatiroides.com


#Arrangoiz

#CirugiadeTumoresdeCabezayCuello

#CirugiaEndocrina

#CirugiaOncologica

#HeadandNeckSurgery

#EndocrineSurgery

#SurgicalOncology

January Thyroid Awareness Month / Mes de Educación sobre Tiroides

January Thyroid Awareness Month

Rodrigo Arrangoiz MS, MD, FACS cirujano de tumores de cabeza y cuello / cirugía endocrina / cirujano oncólogo miembro de Sociedad Quirúrgica S.C. experto en el manejo del cáncer de tiroides:

  • Cumple con los requisitos determinados por el Dr. Ashok Saha para realizar cirugía de tiroides de manera efectiva y segura:

Rodrigo Arrangoiz MS, MD, FACS es miembro de la American Thyroid Association:

2019 membership certificate arrangoiz, rodrigo

Entrenamiento:

  • Cirugia general y gastrointestinal:

• Michigan State University:

• 2004 al 2010image-48

• Cirugia oncológica / tumores de cabeza y cuello / cirugia endocrina:

• Fox Chase Cancer Center (Filadelfia):

• 2010 al 2012

image-39

• Maestria en ciencias (Clinical research for healthprofessionals):

• Drexel University (Filadelfia):

• 2010 al 2012image-50

• Cirugia de tumores de cabeza y cuello / cirugiaendocrina

• IFHNOS / Memorial Sloan Kettering Cancer Center:

• 2014 al 2016

image-51

http://www.sociedadquirurgica.com

http://www.hiperparatiroidismo.info

http://www.cirugiatiroides.com


#Arrangoiz

#CirugiadeTumoresdeCabezayCuello

#CirugiaEndocrina

#CirugiaOncologica

#HeadandNeckSurgery

#EndocrineSurgery

#SurgicalOncology


Breast Cancer Epidemiology

  • Breast cancer remains the most common cancer diagnosed and the second most common cause of cancer-related mortality among women in the United States (lung cancer is first):
    • The American Cancer Society estimated that in 2016, approximately 246,660 new cases of invasive breast cancer will be diagnosed and nearly 40,450 breast cancer related deaths will occur.
    • Estimated new cases and deaths from breast cancer (women only) in the United States in 2018:
      • New cases:
        • 268,670
      • Deaths from breast cancer:
        • 41,400
    • Breast cancer is the most common non-cutaneous cancer in U.S. women:
      • With an estimated 63,960 cases of in situ disease in 2018.
      • 266,120 cases of invasive disease in 2018:
        • Thus, fewer than one of six women diagnosed with breast cancer die of the disease:
          • By comparison, it is estimated that about 70,500 American women will die of lung cancer in 2018.3. Men account for 1% of breast cancer cases and breast cancer deaths.
    • Currently, the lifetime risk of breast cancer among women is 1 in 8 or 12% compared to 1 in 11 for women in the 1970s:
      • This increase in risk over the past four decades is attributed to:
        • Longer life expectancy
        • Changes in reproductive patterns
        • Hormone use
        • The rising prevalence of obesity
        • As well as increased detection through screening mammography
    • Although the incidence of breast cancer has risen:
      • Breast cancer mortality has decreased:
        • Breast cancer death rates have decreased 36% from 1989 to 2012, after slowly increasing (0.4% per year) since 1975:
          • This likely reflects the increased use of screening mammography beginning in the early 1980s leading to detection of earlier stage disease, as well as continued improvements in systemic adjuvant therapy.
  • Breast cancer incidence rates are highest in non-Hispanic white women, followed by African American women and are lowest among Asian/Pacific Islander women:
    • Contrastingly, breast cancer death rates are highest for African American women, followed by non-Hispanic white women, and are lowest for Asian/Pacific Islander women:
      • Furthermore, the difference in long-term breast cancer mortality by race/ethnicity persists and is increasing with breast cancer death rates 42% higher in African American than Caucasian women in 2012:
        • This disparity reflects a combination of factors, including differences in stage at diagnosis, obesity, comorbidities, tumor characteristics, screening, access, adherence, and response to treatment.

Rodrigo Arrangoiz MS, MD, FACS a surgical oncologist and is a member of Sociedad Quirúrgica S.C at the America British Cowdray Medical Center in Mexico City:

  • He is an expert in the management of breast cancer.

    • If you have any questions about breast cancer epidemiology please fill free to contact Dr. Arrangoiz.

Training:

• General surgery:

• Michigan State University:

• 2004 al 2010

• Surgical Oncology / Head and Neck Surgery / Endocrine Surgery:

• Fox Chase Cancer Center (Filadelfia):

• 2010 al 2012

• Masters in Science (Clinical research for health professionals):

• Drexel University (Filadelfia):

• 2010 al 2012

• Surgical Oncology / Head and Neck Surgery / Endocrine Surgery:

• IFHNOS / Memorial Sloan Kettering Cancer Center:

• 2014 al 2016


#Arrangoiz

#Surgeon

#Cirujano

#SurgicalOncologist

#CirujanoOncologo

#BreastSurgeon

#CirujanodeMama

#CancerSurgeon

#CirujanodeCancer

http://www.sociedadquirurigca.com

img_0832-2img_0833-2img_0834-2img_0836-2img_0835-2img_0837-2