
- Toxic Nodular Goiter (TNG):
- Generally causes milder symptoms than Graves’ disease
- In the absence of contraindications:
- Beta-blockers may be used for symptomatic relief:
- While awaiting results of definitive treatment
- Beta-blockers may also be appropriate for patients with:
- Atrial fibrillation and rapid ventricular response
- Propranolol has been widely used to block T4 to T3 conversion:
- A theoretic benefit
- A selective beta-blocker:
- Such as atenolol:
- May be used in patients who cannot tolerate propranolol
- Such as atenolol:
- If beta-blockers are contraindicated:
- A calcium channel blocker may be useful
- Beta-blockers may be used for symptomatic relief:
- Definitive Treatment:
- Toxic Nodular Goiter:
- RAI therapy (with 131I) and surgery:
- Are effective options for the definitive treatment for TNG
- The long-term use of thionamide antithyroid drugs (ATDs):
- Is not favored:
- Unless either 131I therapy or surgery is contraindicated
- Is not favored:
- Thionamides, however, may be used before surgery:
- Especially in older patients:
- Until euthyroidism is restored
- Especially in older patients:
- Radioactive iodine:
- The clinical utility of RAI therapy in the management of TNG:
- Is well established
- If radioactive iodine uptake (RAIU) is adequate and the patient is not a good surgical candidate:
- RAI is the treatment of choice
- Although the dose of 131I may be calculated on the basis of uptake determinations and gland weight:
- TNGs are relatively resistant to 131I:
- Because of their larger size and relatively lower uptake of iodine:
- For these reasons, some clinicians increase the standard dose:
- By 20% to 50%
- For these reasons, some clinicians increase the standard dose:
- Because of their larger size and relatively lower uptake of iodine:
- TNGs are relatively resistant to 131I:
- Frequently, RAI doses between:
- 15 and 50 mCi (555 and 1850 MBq) are administered
- In a report from Mayo Clinic, Jensen et al:
- Treated their patients with a mean dose of 37 mCi (1370 MBq) (range, 6.3 to 150 mCi [233 to 5550 MBq]):
- After 1 year of follow-up:
- 16% of patients were hypothyroid
- After 1 year of follow-up:
- Treated their patients with a mean dose of 37 mCi (1370 MBq) (range, 6.3 to 150 mCi [233 to 5550 MBq]):
- Danaci et al. treated TNGs with a fixed dose of 16.6 mCi (631 MBq) 131I and reported:
- A cumulative relapse rate of:
- 39% at 5 years
- Cumulative incidence of hypothyroidism of:
- 24% at 5 years
- A cumulative relapse rate of:
- In a large prospective study involving 130 consecutive patients with TNGs and a mean follow-up of 6 years:
- 92% of patients were cured after one or two treatments with 131I
- Thyroid volume was reduced by a mean of 43%, and adverse effects were few
- Patients were treated with a median dose of 10 mCi (370 MBq)
- The clinical utility of RAI therapy in the management of TNG:
- RAI therapy (with 131I) and surgery:
- Toxic Nodular Goiter:
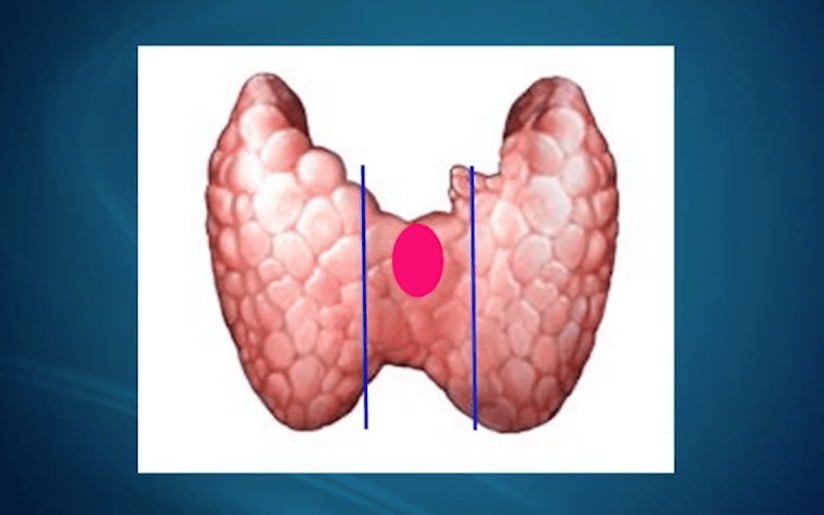
- Generally, after RAI most patients are euthyroid within 2 to 4 months:
- Although sometimes achieving euthyroidism may take longer
- Although most patients treated with RAI achieve long-term euthyroidism:
- 10% to 24% of these patients eventually become hypothyroid:
- Regardless of the dose used
- RAI is associated with a 20% chance of recurrence:
- In which case patients may receive a second dose of 131I or opt for thyroidectomy
- These patients should not be given iodide preoperatively:
- Because of the risk of exacerbating thyrotoxicosis
- 10% to 24% of these patients eventually become hypothyroid:
- Surgery:
- Total thyroidectomy:
- Is recommended for patients with:
- Large goiters causing obstructive symptoms such as:
- Choking
- Dyspnea
- Dysphagia:
- Hoarsness
- Large goiters causing obstructive symptoms such as:
- For those who refuse RAI therapy
- Surgery may also be indicated when a suspicious cold or growing nodule is identified in a TNG
- Surgery is an excellent option for patients who:
- Decline RAI therapy and also for pregnant women
- Is recommended for patients with:
- Two issues with the operation:
- The extent of thyroidectomy remains somewhat controversial
- In the past, some clinics have preferred subtotal thyroidectomy to minimize complications such as:
- Recurrent laryngeal nerve damage and hypoparathyroidism
- In current practice, most surgeons perform:
- A total thyroidectomy for bilateral benign nodular goiters:
- This is what I recommend
- A total thyroidectomy for bilateral benign nodular goiters:
- Also, the trend in recent decades:
- Suggests that RAI is being increasingly considered as:
- An attractive, effective alternative to surgery in TNG
- For example, a study from Mayo Clinic showed that between 1950 and 1974:
- 83% of patients had surgical treatment
- 17% had RAI treatment
- Between 1990 and 1999, the figures were:
- 53% for surgery and 47% for RAI
- Suggests that RAI is being increasingly considered as:
- Total thyroidectomy:
- Thionamide antithyroid drugs:
- Thionamide antithyroid drugs are the preferred transient treatment:
- During pregnancyuntil delivery
- They should also be considered for patients who are not candidates for or who decline definitive treatment
- Treatment is generally indefinite with thionamide ATDs:
- Generally because permanent remission is never achieved in TNG
- Thionamide antithyroid drugs are the preferred transient treatment:
- Graves’ Disease:
- In the management of Graves’ disease:
- Treatment preferences vary substantially by geographic region
- This was suggested by the outcome of an international survey of endocrinologists from the United States, Europe, and Japan:
- Among physicians in the United States:
- Thionamide ATDs were selected as the primary form of therapy for a “typical 43-year-old healthy woman” by only approximately 30%, whereas 69% chose RAI treatment and 1% opted for surgery
- By contrast, 77% of European physicians and 88% of Japanese physicians selected thionamide ATDs as the preferred primary treatment, with RAI therapy as the second choice.
- Among physicians in the United States:
- Thionamide antithyroid drugs:
- Thionamide ATDs inhibit biosynthesis of thyroid hormones:
- Biochemical euthyroidism is usually achieved within 6 to 8 weeks after initiation of therapy
- Currently, three thionamide ATDs are available:
- Methimazole
- Available in the United States
- Half-life of methimazole in plasma is:
- 3 to 5 hours
- Propylthiouracil
- Available in the United States
- Half-life of in plasma of propylthiouracil is 1 to 2 hours
- Carbimazole:
- Which is metabolized to methimazole:
- Is sometimes used in Europe and Asia
- Which is metabolized to methimazole:
- Methimazole
- Methimazole has a longer duration of action:
- Although both drugs are effective for more than 5 hours because they accumulate in thyroid cells
- Initial daily doses range from:
- 10 mg to 40 mg of methimazole usually once daily
- 100 to 150 mg of propylthiouracil every 6 to 8 hours daily
- 15 to 45 mg daily of carbimazole usually in one dose up to three divided doses
- The decision to use methimazole / carbimazole or propylthiouracil:
- Is a matter of physician preference:
- Because both agents are equally effective
- However, observations over several decadeshave shown that methimazole and its prodrug carbimazole are better than propylthiouracil in controlling more severe hyperthyroidism;
- But propylthiouracil should not be routinely used because of potential fatal hepatotoxicity
- Is a matter of physician preference:
- This has led to the recommendation that methimazole / carbimazole:
- Be the first-line drug when ATD therapy is initiated:
- Either for primary treatment or to prepare a patient for RAI therapy or surgery
- An exception to this rule has been pregnancy:
- During which propylthiouracil has been preferred:
- Because of rare reports of birth defects associated with methimazole
- Propylthiouracil has also been used in patients with:
- Minor reactions to methimazole but who, nonetheless, prefer to continue ATD therapy
- Propylthiouracil may also be preferable in patients with:
- Life-threatening thyrotoxicosis:
- Because of its additional inhibition of T4 to T3 conversion
- Life-threatening thyrotoxicosis:
- During which propylthiouracil has been preferred:
- Be the first-line drug when ATD therapy is initiated:
- It is crucial to evaluate patients clinically and biochemically (with serum T4 and TSH measurements) regularly:
- From 6 to 8 weeks after the initiation of ATD treatment:
- Until the patient is biochemically euthyroid and every 8 to 12 weeks thereafter
- Once the patient is euthyroid, the ATD dose may be reduced
- From 6 to 8 weeks after the initiation of ATD treatment:
- Some clinicians favor adding levothyroxine to the ATD regimen as part of a block-replacement regimen:
- Without reducing the original ATD dose:
- To minimize the number of patient visits and maintain a more normal stable TSH:
- This addition to the regimen causes no difference in the remission outcome compared with titration of ATD alone
- The concern about compliance and the advantages of ATD alone have ensured that combination treatment (thyroxine and ATD) has not been widely adopted
- To minimize the number of patient visits and maintain a more normal stable TSH:
- Without reducing the original ATD dose:
- It has been determined from various reports that treatment with thionamide ATDs for 12 to 18 months is optimal:
- Resulting in long-term remission in 40% to 60% of patients with Graves’ disease:
- With higher remission rates in women than in men
- The likelihood of sustained remission:
- Is greater in patients with:
- Mild hyperthyroidism
- Small goiter
- Low or undetectable TSHR-Ab titers:
- Than in those with moderate to severe hyperthyroidism or T3 toxicosis, large goiter, and high TSHR-Ab titers
- Is greater in patients with:
- If hyperthyroidism recurs:
- Other modes of therapy (RAI or surgery) are considered
- Most relapses following cessation of thionamide ATDs;
- Occur shortly after the ATDs are discontinued:
- Generally within the first few months:
- Although they may occur several years later:
- Therefore, clinical and biochemical evaluation is necessary 2 months after ATD withdrawal and periodically at regular intervals thereafter
- Although they may occur several years later:
- Generally within the first few months:
- Occur shortly after the ATDs are discontinued:
- Resulting in long-term remission in 40% to 60% of patients with Graves’ disease:
- As with all other drugs, thionamide ATDs may cause adverse effects:
- As early as 2 weeks after initiation of therapy or later in the course of therapy:
- It is essential to instruct patients on how to deal with these adverse reactions
- As early as 2 weeks after initiation of therapy or later in the course of therapy:
- The most serious and rare complication:
- Agranulocytosis:
- Should be ruled out:
- By obtaining white blood cell and differential counts:
- If fever and signs of infection such as sore throat occur while the patient is on thionamide ATD therapy
- By obtaining white blood cell and differential counts:
- Should be ruled out:
- Agranulocytosis:
- Thionamide ATDs inhibit biosynthesis of thyroid hormones:
- In the management of Graves’ disease:
| Adverse Effect | Propylthiouracil (100 to 150 mg/day) | Methimazole (10 to 40 mg/day) |
| Minor reactions | ||
| —Fever, rash, arthralgia | 5% to 20% | 5% to 20% (dose related) |
| Major reactions | ||
| —Agranulocytosis | 0.2%-0.5% (not clearly dose related) | 0.2%-0.5% (dose related) |
| —Hepatotoxicity (hepatitis) | 30% (< 1% severe) | Cholestatic (usually reversible, with few deaths reported) |
| —Vasculitis | ANCA + | Rare |
ANCA, antineutrophil cytoplasmic antibody |
- Inorganic Iodine:
- Iodine given in pharmacologic doses (as Lugol solution or as a saturated solution of potassium iodide):
- Inhibits the release of thyroid hormones for a few days or weeks:
- After which its antithyroid action is lost
- For this reason it is not used routinely:
- But short-term iodine therapy is useful in:
- The preparation of patients for surgery
- After RAI therapy to hasten the fall in serum T3 and T4 concentrations to normal:
- Although this is not a routine indication
- In the treatment of thyrotoxic crisis
- But short-term iodine therapy is useful in:
- The usual dose of Lugol solution (5% iodine and 10% potassium iodide in water) is:
- 0.1 to 0.3 mL three times daily
- The usual dose of potassium iodide is:
- 60 mg (1 drop) three times daily
- Inhibits the release of thyroid hormones for a few days or weeks:
- Iodine given in pharmacologic doses (as Lugol solution or as a saturated solution of potassium iodide):
- Radioactive iodine therapy:
- In use for more than 60 years:
- RAI therapy is established as an effective, relatively inexpensive, and safe treatment option for Graves’ disease
- The objective of RAI therapy is to:
- Destroy sufficient thyroid tissue to cure hyperthyroidism
- The goal of treatment is to:
- Render the patient either euthyroid or hypothyroid:
- Depending on the willingness of the physician to risk the possibility of persistent hyperthyroidism
- Render the patient either euthyroid or hypothyroid:
- Much attention has focused on achieving euthyroidism:
- By adjusting the RAI dose:
- But there is little consensus regarding the most appropriate dose schedule
- By adjusting the RAI dose:
- The regimens used include the traditional method of:
- Repeated low doses (2 mCi)
- Fixed doses
- Doses calculated on the basis of:
- The size of the thyroid
- The RAIU
- The turnover of 131I
- Because it has proved impossible to titrate doses for individual patients accurately to guarantee a euthyroid state:
- The majority of physicians in the United States:
- Prefer to administer a single, relatively large dose:
- 10 to 20 mCi initially with the intent of:
- Inducing thyroid ablation and the development of hypothyroidism
- 10 to 20 mCi initially with the intent of:
- Thyroid function is then assessed 6 to 8 weeks after RAI administration and possibly every month thereafter:
- To monitor the development of hypothyroidism:
- Especially during the first 6 months after RAI treatment
- To monitor the development of hypothyroidism:
- When hypothyroidism is detected by TSH elevations:
- Levothyroxine treatment should be initiated:
- To maintain the TSH level in the normal range (0.5 to 3 mIU/L)
- Levothyroxine treatment should be initiated:
- However, if hyperthyroidism persists:
- Another RAI dose may be delivered:
- But should not be given until at least 6 months after the first dose
- Another RAI dose may be delivered:
- Prefer to administer a single, relatively large dose:
- The majority of physicians in the United States:
- Before RAI treatment is started:
- Patients should be informed of the precautions needed after RAI
- Rarely patients may experience:
- Mild anterior neck pain after RAI
- A short-lived exacerbation of hyperthyroid symptoms:
- Caused by the leakage of preformed thyroid hormones from a damaged thyroid gland
- Worsening of Graves’ ophthalmopathy:
- Especially among smokers:
- May be observed after 131I treatment
- Risk is reduced by:
- Cessation of smoking and the administration of glucocorticoids, namely, prednisone:
- Different regimens are available, but most agree on the regimen of oral prednisone:
- Administration 1 to 3 days after RAI treatment at 0.3 to 0.5 mg/kg daily, and the dose is tapered until withdrawal about 3 months later
- Different regimens are available, but most agree on the regimen of oral prednisone:
- Cessation of smoking and the administration of glucocorticoids, namely, prednisone:
- Especially among smokers:
- Whether to pretreat patients with thionamide ATDs:
- Until they are euthyroid before 131I administration is a matter of debate:
- Retrospective studies have shown that the efficacy of treatment with 131I:
- Is decreased after propylthiouracil:
- It is best to discontinue ATDs a few days before RAI is given
- Is decreased after propylthiouracil:
- Retrospective studies have shown that the efficacy of treatment with 131I:
- Previously RAI was reserved for adults because of the lack of long-term data in children and adolescents:
- More recently, in properly administered doses, data have shown that RAI is the ideal form of therapy for Graves’ disease in children
- It remains absolutely contraindicated:
- During pregnancy and lactation
- Until they are euthyroid before 131I administration is a matter of debate:
- In use for more than 60 years:
- Surgery:
- Because of the higher relapse rates seen with subtotal thyroidectomy, or near-total thyroidectomy:
- Total thyroidectomy:
- Is the recommended surgical procedure for the treatment of Graves’ hyperthyroidism
- Total thyroidectomy:
- It usually results in postoperative hypothyroidism:
- Requiring lifelong levothyroxine replacement
- Thyroidectomy is preferred in patients with:
- Large goiters:
- Especially those with tracheoesophageal compression symptoms)
- Coincidental suspicious thyroid nodules
- Contraindications to 131I or ATDs
- In those who refuse RAI treatment or are pregnant when hyperthyroidism is difficult to control
- Large goiters:
- Surgical morbidity, including:
- Permanent hypoparathyroidism
- Vocal cord dysfunction caused by recurrent laryngeal nerve injury,
- Infection
- Hematoma
- Is low in experienced centers
- Any patient with hyperthyroidism scheduled to undergo surgery:
- Should be treated with thionamide ATDs:
- To restore euthyroidism
- Should be treated with thionamide ATDs:
- Alternative methods of preoperative therapy include:
- Thionamide ATDs combined with beta-blockers:
- Propranolol:
- 40 to 80 mg three times a day or
- A longer-acting beta-adrenergic antagonist:
- Atenolol, 50 mg/day
- Propranolol:
- Potassium iodide:
- 40 mg three times a day for 10 days
- Potassium iodide (several drops per day for 10 days) in combination with propranolol (40 to 120 mg per day):
- May be another alternative:
- Any of these regimens virtually eliminates the risk of postoperative thyrotoxic crisis
- May be another alternative:
- Thionamide ATDs combined with beta-blockers:
- Indefinite follow-up is essential after thyroidectomy:
- With an adequate replacement dose of levothyroxine that maintains TSH within the range of normal
- Because of the higher relapse rates seen with subtotal thyroidectomy, or near-total thyroidectomy:
- Pregnancy:
- Appropriate management of hyperthyroidism during pregnancy is important for the mother’s health and for the course of the pregnancy
- Moreover, the quality of management may have considerable impact on the progeny:
- Both in fetal and in neonatal life and on the long-term health of the child
- The most common form of hyperthyroidism during pregnancy:
- Is mostly the result of Graves’ disease:
- Its adequate control is essential
- Is mostly the result of Graves’ disease:
- Pregnant hyperthyroid women should be treated with:
- Thionamide ATDs:
- Most clinicians prefer propylthiouracil:
- Although both propylthiouracil and methimazole:
- Are shown to cross the placenta equally
- Although both propylthiouracil and methimazole:
- As noted previously, rare reports of birth defects associated with methimazole exist
- The minimum dose of ATD that keeps maternal thyroid function around or slightly above the upper limit of normal should be used:
- To avoid fetal hypothyroidism and fetal goiter:
- Therefore, frequent monitoring of the mother and the fetus is necessary
- To avoid fetal hypothyroidism and fetal goiter:
- Mothers may experience:
- Exacerbation of thyrotoxicosis after delivery
- Newborns may have:
- Transient thyroid dysfunction when exposed to ATDs or may develop transient neonatal hyperthyroidism resulting from the passage of TSHR antibodies through the placenta
- Most clinicians prefer propylthiouracil:
- Thionamide ATDs:
- Postpartum propylthiouracil:
- Is also preferred for nursing mothers:
- Because less drug appears in breast milk than with methimazole
- Is also preferred for nursing mothers:
- Surgical thyroidectomy:
- In the second trimester of a pregnant woman with Graves’ disease:
- Is performed only in the case of uncontrollable hyperthyroidism:
- That threatens the health of the woman or when ATDs are not tolerated
- Is performed only in the case of uncontrollable hyperthyroidism:
- If thyroidectomy is performed, this should be followed by a systematic and a careful follow-up evaluation of the thyroid state of the fetus
- In the second trimester of a pregnant woman with Graves’ disease:
#Arrangoiz #ThryoidExpert #ThyroidSurgeon #HeadandNeckSurgeon #SurgicalOncologist #ParathyroidSurgeon #CancerSurgeon #Hyperthyroidism #Goiter #GravesDisease #ToxicNodularGoiter #PlummersDisease #ThyroidNodules #Miami #MountSinaiMedicalCenter








 Rodrigo Arrangoiz MS, MD, FACS, FSSO
