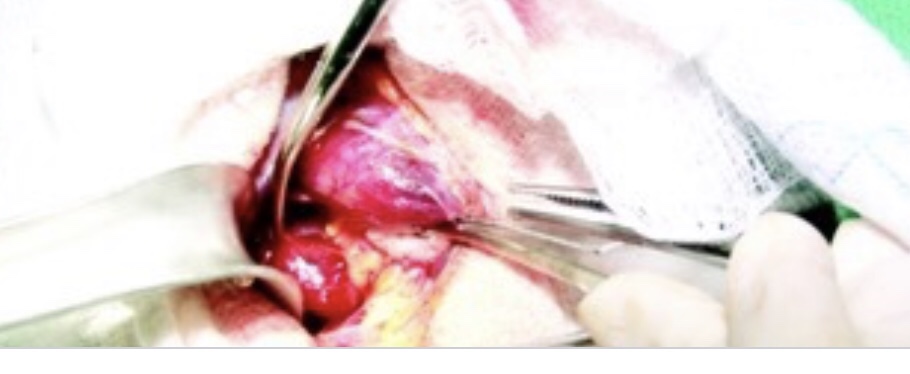
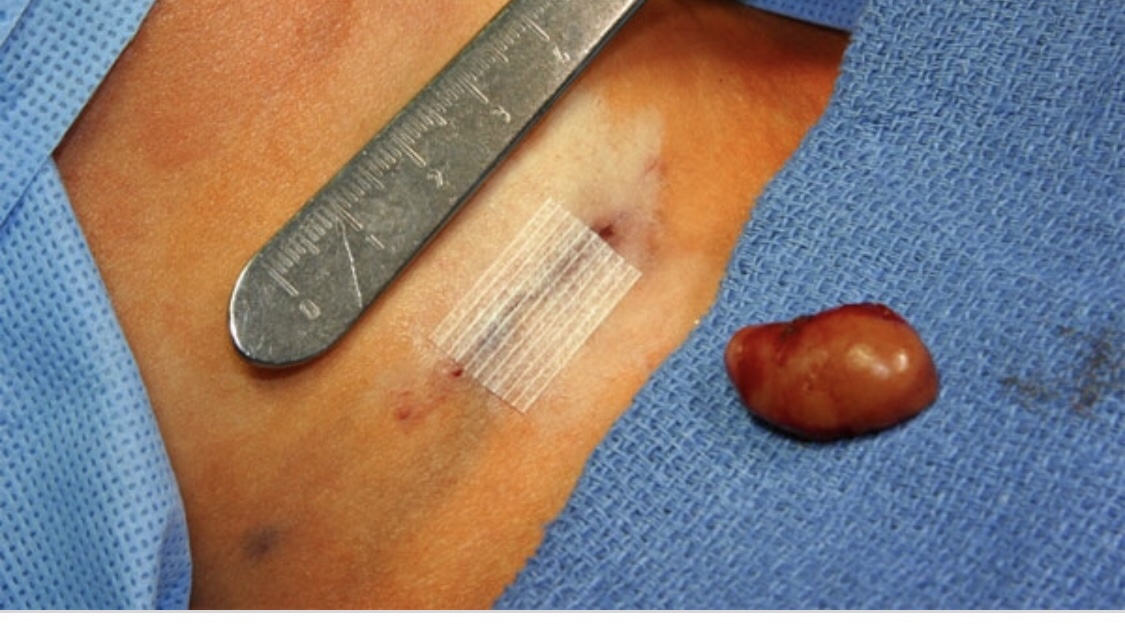
Physical Examination in a Patient with Multinodular Goiter

  • After documentation of thyroid size:
    • The examiner should note the:
      • Consistency and fixation of the mass:
        • Especially with respect to the larynx and trachea
  • Estimation of goiter size by physical examination:
    • Is clearly an inaccurate method of assessment:
      • Jarlov et al. found substantial errors in the clinical assessment of thyroid size as compared with ultrasonographic assessment
  • Estimated weight based on the physical examination:
    • Generally underestimates multinodular goiter weight:
      • By 25 to 50 g
  • The larynx (landmarks include thyroid notch and anterior cricoid arch) and trachea should be examined for:
    • Deviation from the midline:
      • Typically, cervical goiter will deviate the larynx and trachea to the contralateral side
  • The neck must be examined for:
    • Adenopathy as well as scarring:
      • From past thyroid and other neck surgery
    • Jugular distention and subcutaneous venous redistribution should be noted:
      • Although this may be present with large benign cervical or substernal goiter:
        • True superior vena cava syndrome is generally due to malignant thyroid disease and warrants careful scanning and evaluation
  • It is imperative in all patients with goiter that the larynx be examined:
    • Roughly 2% of patients with goiter present with vocal cord paralysis in the setting of benign disease and no prior neck surgery:
      • Vocal cord paralysis without a history of past thyroid surgery:
        • Implies invasive thyroid malignancy until proved otherwise:
          • It should be noted, however, that benign goiter has also been associated with vocal cord paralysis:
            • Presumably through stretch:
              • Which may recover postoperatively
      • Certainly, such a preoperative finding focuses the surgeon’s attention on the extreme importance of preserving the contralateral RLN
    • The laryngeal examination in patients with large cervical goiter:
      • Can be difficult if there is edematous or redundant supraglottic mucosa, laryngeal compression and deviation, and hypopharyngeal crowding resulting from goitrous extrinsic compression
    • Symptomatic assessment of the voice, like symptomatic assessment of the airway, does not predict objective findings in patients with goiter and should not replace the laryngeal exam:
      • Michel noted in his series of substernal goiters that although hoarseness was described in 26%:
        • Vocal cord paralysis was only found in 3%
          • I recommend that all patients with goiter undergo preoperative laryngeal examination
  • Substernal Goiter
    • In many ways the history and physical examination for patients with substernal goiter overlaps significantly with those for patients with cervical goiter
    • As cervical goiter progresses substernally:
      • Given the restriction of the bony confines of the thoracic inlet:
        • It increasingly compromises the airway
    • In short, substernal goiter evolution is strongly correlated with tracheal deviation:
      • The development of regional airway symptoms, and radiographic airway compression
    • Buckley and Stark noted that:
      • Although the maximum tracheal deviation with substernal goiter usually occurs at the thoracic inlet:
        • It may occasionally occur farther inferiorly
    • Larger surgical series of substernal goiter:
      • Show 70% to 80% of substernal goiter patients:
        • Are symptomatic at presentation:
          • Cervical mass is noted in 69% to 97% of the cases:
            • 10% to 30% of substernal goiter patients:
              • Have no significant palpable cervical abnormality
          • Respiratory symptoms in 42% to 96% of the cases
          • Dysphagia in 26% to 60% of the cases
          • Acute airway presentation in 1% to 5%
          • 3% to 7% present with vocal cord paralysis
        • 4% to 50% are asymptomatic at presentation:
          • Wax and Briant have noted that, with careful questioning:
            • Up to one third of patients who are “asymptomatic” admit to symptoms
      • Pemberton’s sign is described as the development of head and neck venous engorgement with facial congestion, plethora, and venous distention with arms raised over the head:
        • It is sometimes expanded to include the development of transient respiratory insufficiency
        • Pemberton’s sign is thought to indicate goiter extension into the thoracic inlet, with secondary relative venous and airway obstruction
          • Only 4.4% of patients with substernal goiter present with a positive Pemberton’s sign
      • Substernal goiters can also present with:
        • Neck and upper chest pain 
        • Rarely has been associated with:
          • Hematemesis secondary to downhill esophageal varices:
            • Without signs of portal hypertension
          • Abscess formation
          • Horner’s syndrome
          • Chylothorax:
            • Secondary to thoracic duct obstruction
          • Transient ischemic attacks:
            • Through “thyroid steal syndrome”
          • Venous thrombosis
          • Intubation injuries:
            • Especially to the posterior tracheal membranous wall
        • Laryngeal shift to the side of a dominant cervical goiter:
          • Suggests contralateral substernal goiter and requires axial imaging of the neck and chest
        • Similarly, laryngeal shift without any palpable cervical findings suggests substernal goiter and similarly requires axial neck and chest imaging
        • Finally, substernal goiter is suspected when the clavicle intervenes before the inferior extent of the thyroid mass can be palpated

#Arrangoiz #ThyriodSurgeon #ThyroidExpert #HeadandNeckSurgeon #CancerSurgeon #ThyroidDisease #ThyroidCancer #MultinodularGoiter #Goiter #SubsternalGoiter #CASO #CenterforAdvancedSurgicalOncology

EDEMA

  • Intubation generally proceeds well in patients with large cervical and substernal goiters:
    • But occasionally it can be difficult
  • When difficult, anesthesia induction and intubation can represent a dramatic and life-threatening process:
    • Given the fact that emergent or “under local” tracheotomies:
      • Generally are not options because of the mass of the overlying goiter
  • In patients with goiter:
    • There may be evidence of substantial laryngeal deviation and perhaps vocal cord paralysis at intubation
  • The surgeon who performs the preoperative laryngoscopy should convey all information regarding the appearance of the:
    • Larynx, presence of deviation, and vocal cord paralysis to the anesthesia staff
    • Both the surgeon and the anesthesiologist should review the preoperative CT scans and examine the patient together before induction:
      • The method of intubation and the size of the tube and contingency plans can be discussed and decided upon through these discussions
  • Typically, a straightforward induction with transoral intubation can be performed:
    • Laryngeal deviation generally does not represent a problem, and tracheal compression generally yields to a reasonably sized endotracheal tube
  • An alternative and safe method that we favor is an:
    • Awake, sitting up, fiberoptic trans-nasal intubation:
      • This is especially a reasonable course of action if there is any doubt as to the adequacy of a sedated mask anesthesia airway, particularly if the larynx is significantly deviated by the cervical component of the goiter
  • Newer video laryngoscopes are also an excellent adjunct for intubation in such patients
  • Maximum tracheal compression in cervical and substernal goiter:
    • Usually occurs at the thoracic inlet but may be present further distally
  • As previously noted, tracheal compression by benign goiter typically yields to a reasonably sized endotracheal tube:
    • One exception is when there is malignant infiltration of the trachea, especially if there is intraluminal disease:
      • In these circumstances, transoral bronchoscopic intubation with bronchoscopic core-out can lead to satisfactory airway
  • Once again, preoperative CT scanning empowers the surgeon
  • Vigilance and recognition of non-thyroid factors, such as:
    • Jaw and tongue size, anteriorly positioned larynx, and available degree of head extension:
      • Are also important determinants of difficult intubation
  • Experience has shown that a significant problem in patients with large cervical or substernal goiters:
    • Especially with bilateral circumferential goiters:
      • Is the development of laryngeal edema with initial intubation attempts by anesthesia
      • The larynx, which represents the extreme distal end of the airway projected into the hypopharynx:
        • Likely has chronically reduced venous and lymphatic drainage as a result of a large, constricting bilateral goiter:
          • Such a larynx is easily made edematous with multiple unsuccessful intubation attempts:
            • This edema can last weeks postoperatively:
              • Sometimes requiring tracheotomy, which usually can be removed after such edema resolves:
                • It is therefore best to intubate once correctly
  • Intubation problems, although rare, can quickly spell disaster
  • The propensity for laryngeal edema from intubation attempts with goiter has been emphasized in the case reports of Hassard:
    • In there series of 200 patients with goiter, they encountered difficult intubation in only four cases (2%)
    • There were no significant predictors of difficult intubation, including size, substernal extension, preoperative compressive symptoms, or radiographic presence of tracheal deviation or compression
    • Tracheotomy was performed in only 3% of patients and was done electively at the time of thyroidectomy
      • Tracheotomy was performed either because of concern about laryngeal edema from multiple intubation attempts or in cases where vocal cord dysfunction was in question in cases without neural monitoring, especially if one vocal cord was known to be paralyzed preoperatively
      • With neural monitoring, greater certainty exists as to the functional status of both nerves during surgery

#Arrangoiz #ThyroidSurgeon #ThyroidExpert #HeadandNeckSurgeon #CancerSurgeon #MultinodularGoiter #Goiter #SubsternalGoiter #CASO #CenterforAdvancedSurgicalOncology
Papillary Thyroid Cancer: Is Surgery Always Necessary?

👉After receiving a diagnosis of papillary thyroid cancer, intuitively, the thought has been that surgery is the next step.

👉While this was the standard in the past, we now know that in specific situations immediate surgery may not be necessary.

👉The incidence of thyroid cancer has increased significantly over the last three decades in large part due to tumors being identified incidentally on imaging studies. It is important to note that despite the increased rate of detection, the mortality rate from thyroid cancer remains very low and unchanged. Therefore, many of these cancers are low risk, and if left alone, would likely not pose a threat to the patient. There has been significant research looking at monitoring low risk thyroid cancers without surgery especially when surgically removing the tumor could potentially do more harm than good. This monitoring approach without surgical intervention is known as active surveillance.

👉In general, to be eligible for active surveillance: the tumor should be ≤ 1cm -1.5cm, there should not be any evidence of lymph node metastases, there should not be suspicion of more aggressive subtypes such as tall cell or sclerosing variant papillary thyroid cancer, and the tumor should not be located near a vulnerable area where growth could compromise important structures such as the trachea or the recurrent laryngeal nerve.

👉Active surveillance should be done at a medical center with a multidisciplinary approach and ultrasound expertise. Active surveillance typically entails monitoring with ultrasound every 6 months initially with extension of the surveillance interval over time.

👉While undergoing surveillance, if there is significant growth (≥3mm) of the nodule, evidence of lymph node involvement, extension into adjacent structures, or change in patient preference, then surgical intervention is recommended.

👉Surgery at time of disease progression has been shown to have the same excellent prognosis. There have been ongoing prospective studies on active surveillance over the course of the last twenty years that have shown a low rate of progression (10-15%) and no deaths or development of distant metastasis during active surveillance.

👉The decision to pursue active surveillance is a shared decision between the patient and the physician after discussion of the risks and benefits based on each patient’s unique circumstances. Additional factors when considering active surveillance include: cost and time associated with appointments needed for surveillance, age of patient, medical comorbidities, and the possible increased emotional burden or anxiety that can result from opting to not remove the cancer at time of initial diagnosis.

👉The “best” treatment strategy will differ depending on each patient, so I hope that this information encourages discussion between patients and their endocrinologists to help decide which treatment option is best for them.

References:
1. Sugitani I, Ito Y, Takeuchi D, Nakayama H, Masaki C, Shindo H, Teshima M, Horiguchi K, Yoshida Y, Kanai T, Hirokawa M, Hames KY, Tabei I, Miyauchi A. Indications and Strategy for Active Surveillance of Adult Low-Risk Papillary Thyroid Microcarcinoma: Consensus Statements from the Japan Association of Endocrine Surgery Task Force on Management for Papillary Thyroid Microcarcinoma. Thyroid. 2021 Feb;31(2):183-192.
2. Molinaro E, Campopiano MC, Pieruzzi L, Matrone A, Agate L, Bottici V, Viola D, Cappagli V, Valerio L, Giani C, Puleo L, Lorusso L, Piaggi P, Torregrossa L, Basolo F, Vitti P, Tuttle RM, Elisei R. Active Surveillance in Papillary Thyroid Microcarcinomas is Feasible and Safe: Experience at a Single Italian Center. J Clin Endocrinol Metab. 2020 Mar 1;105(3):e172–80.
3. Tuttle RM, Alzahrani AS. Risk Stratification in Differentiated Thyroid Cancer: From Detection to Final Follow-up. J Clin Endocrinol Metab. 2019 Mar 15;104(9):4087–100.
4. Tuttle RM, Fagin JA, Minkowitz G, Wong RJ, Roman B, Patel S, Untch B, Ganly I, Shaha AR, Shah JP, Pace M, Li D, Bach A, Lin O, Whiting A, Ghossein R, Landa I, Sabra M, Boucai L, Fish S, Morris LGT. Natural History and Tumor Volume Kinetics of Papillary Thyroid Cancers During Active Surveillance. JAMA Otolaryngol Head Neck Surg. 2017 Oct 1;143(10):1015-1020.
5. Miyauchi A. Clinical Trials of Active Surveillance of Papillary Microcarcinoma of the Thyroid. World J Surg. 2016 Mar;40(3):516-22.
6. Ito Y, Miyauchi A, Inoue H, Fukushima M, Kihara M, Higashiyama T, Tomoda C, Takamura Y, Kobayashi K, Miya A. An observational trial for papillary thyroid microcarcinoma in Japanese patients. World J Surg. 2010 Jan;34(1):28-35.
7. ATA Thyroid Patient Information- Microcarcinomas of the Thyroid Glandhttps://www.thyroid.org/microcarcinomas-thyroid-gland/

#Arrangoiz #ThyroidSurgeon #ThyroidExpert #CancerSurgeon #ThyroidCancer #SurgicalOncologist #CASO #CenterforAdvancedSurgicalOncology

Cervical Goiter – History

  • The history of goitrous growth and associated symptoms is critical for determining surgical candidacy:
    • This history should be obtained not only from the patient but also from his or her family
  • Regional symptoms should be addressed relating to:
    • Respiration
    • Phonation
    • Swallowing
    • Presence of globus (lump sensation)
  • As Pemberton emphasized in 1921:
    • Symptoms associated with goiter may be positionally induced
    • Positions that may provoke goiter regional symptomatology include being:
      • Supine
      • Arms raised (as when reaching for an upper cabinet),
      • Extreme neck extension
      • Extreme neck flexion (as with reading a book in bed)
      • Turning the head to the extreme left or right
        • Patients thus need to be questioned about positional provocation of regional symptoms
  • In addition, the family needs to be questioned about nocturnal symptoms:
    • As symptoms may manifest initially in the setting of recumbency and upper airway relaxation during sleep
  • Symptoms may also be associated with exercise and increased oxygen demands
  • A history of preceding upper respiratory tract infection may produce dyspnea in a patient with long-standing tracheal obstruction secondary to goiter:
    • Through new laryngotracheal mucosal edema
  • Patients with cervical or substernal goiter may present with:
    • Cough
    • Dyspnea
    • Foreign-body sensation
    • Neck tightness
    • Change in collar size
    • Wheezing:
      • Some patients may come to the head and neck surgeon with a misdiagnosis of asthma or chronic obstructive pulmonary disease (COPD)
  • Patients with large cervical and substernal goiter:
    • Approximately 25% of patients were asymptomatic
  • Symptoms of hypothyroidism and hyperthyroidism should be reviewed:
    • Hyperthyroidism may slowly evolve in patients with multinodular goiter or may develop acutely in response to significant iodine load such as with CT scan contrast (Jod-Basedow phenomenon) or with the introduction of iodized salt in endemic goiter regions
  • A history of migration from an area of endemic goiter should be obtained, as well as a history of exposure to known goitrogens, notably iodine and lithium
  • A family history of thyroid disease should be obtained

#Arrangoiz #ThyroidSurgeon #ThyroidExpert #HeadandNeckSurgeon #CancerSurgeon #MultinodularGoiter #Goiter #SubsternalGoiter #CervicalGoiter #CASO #CenterforAdvancedSurgicalOncolgy

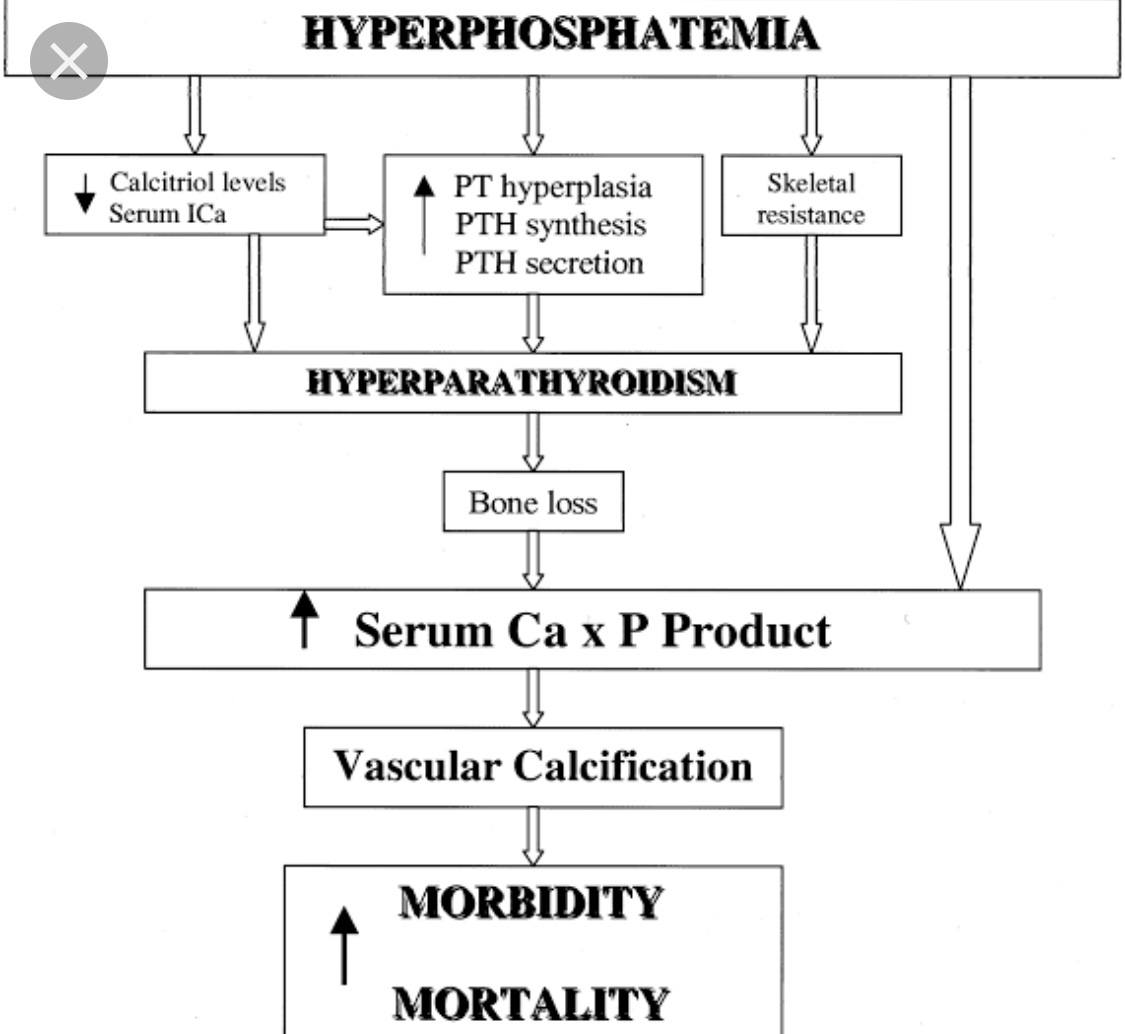
Hiperparatiroidismo y Riesgo de Infarto del Corazón

👉Los cambios en el calcio y el fosfato que resultan del hiperparatiroidismo renal pueden aumentar la calcificación de las arterias y provocar ataques cardíacos y accidentes cerebrovasculares – Dr. Rodrigo Arrangoiz

👉Aprenda más en https://www.atherosclerosis-journal.com/article/S0021-9150(18)31349-2/fulltext

CheckYourCalcium (realízate un calcio total en sangre).

👉Para más información: http://www.hiperparatiroidismo.info

#CheckYourCalcium #Arrangoiz #ParathyroidExpert #ParathyroidSurgeon #Hiperparatiroidism #Hipercalcemia #CheckYourCalcium #HeadandNeckSurgeon #CASO

Isolated Mediastinal Goiter (Substernal Goiter Type III)

  • Although rare, thyroid glands within the mediastinum may exist without connection to the normal cervical orthotopic gland:
    • Such purely isolated mediastinal goiters represent only 0.2% to 3% of all goiters requiring surgical treatment
  • Such lesions are important to recognize because unlike all other types of substernal goiters:
    • Blood supply of the isolated mediastinal goiter may be through purely mediastinal arteries (including the aorta, subclavian, internal mammary, thyrocervical trunk, and innominate) and veins:
      • This is extremely important in planning their surgical resection
  • This entity is best termed isolated mediastinal goiter:
    • Other terms have been used, including aberrant mediastinal and ectopic mediastinal goiter
  • Three explanations exist for isolated mediastinal goiter:
    • Embryologic fragmentation of the thyroid anlagen with hyperdescent, likely associated with cardiac and great vessel descent, may explain some cases of isolated mediastinal goiter
    • Alternatively, isolated mediastinal goiter may form as an exophytic nodule, through progressive attenuation of the nodule-thyroid stalk
    • Finally, the isolated mediastinal goiter may form as a parasitic nodule representing a thyroid tissue fragment implant in the upper mediastinum from past goiter surgery:
      • I have seen such implants also within the peri-thyroid area and posterior to the upper cervical segment of the carotid artery

#Arrangoiz #ThyroidSurgeon #ThyroidExpert #HeadandNeckSurgeon #CancerSurgeon #HeadandNeckSurgeon #MultinodularGoiter #SubsternalGoiter #CASO #CenterforAdvancedSurgicalOncology
Substernal Goiter: Type II Posterior Mediastinal Goiters

  • Most surgical and radiographic series suggest that substernal goiters affect:
    • The anterior mediastinum in approximately 85% of patients:
      • Extension into the anterior mediastinum brings the thyroid:
        • Anterior to the subclavian and innominate vessels and anterior to the RLN
      • The relationship of the anterior mediastinal goiter to the RLN is as in the normal cervical gland:
        • That is, that the nerve is deep
    • The posterior mediastinum in approximately 15% of patients:
      • When substernal goiter expands to the posterior mediastinum:
        • It excavates the region posterior to the trachea, pushing the trachea anteriorly and splaying the great vessels anteriorly:
          • The thyroid then comes to rest in a space posterior to the innominate vein, carotid sheath contents, innominate and subclavian arteries, RLN, and inferior thyroid artery
      • Of importance, the relationship of the thyroid gland and the RLN is reversed as compared with the normal cervical orthotopic gland-RLN relationship:
        • The RLN is ventral to the inferior component of the thyroid and, if not recognized early on, can be stretched or cut by even the most meticulous thyroid surgeon
        • The nerve can also be entrapped between components of the posterior mediastinal goiter; even in these circumstances, a portion of the goiter will be deep to the RLN:
          • Such posterior mediastinal goiters can come to rest in a space bounded inferiorly by the azygous vein, posteriorly by the vertebral column, laterally by the first rib, medially by the trachea and esophagus, and anteriorly by the carotid sheath, subclavian and innominate vessels, superior vena cava, and phrenic and recurrent laryngeal nerves
  • Posterior mediastinal goiter (type IIA):
    • Can occur ipsilateral to the cervical thyroid gland of origin or may come to rest through retrotracheal extension in the contralateral thorax (substernal goiter type IIB)
  • Extension to the right thorax is more commonly seen as a result of:
    • Aortic arch and associated branch vessels obstructing the left posterior mediastinal descent pathway
  • Contralateral thoracic extension in the posterior mediastinum may occur either:
    • Behind the trachea and esophagus (IIB1) or between trachea and esophagus (IIB2)
  • Axial CT scanning and barium swallow help to determine this pattern
  • Generally the right chest caudal extension:
    • Is limited at the level of the azygous arch

#Arrangoiz #HeadandNeckSurgeon #ThyroidSurgeon #ThyroidExpert #MultinodularGoiter #SubsternalGoiter #CASO #CenterforAdvancedSurgicalOncology
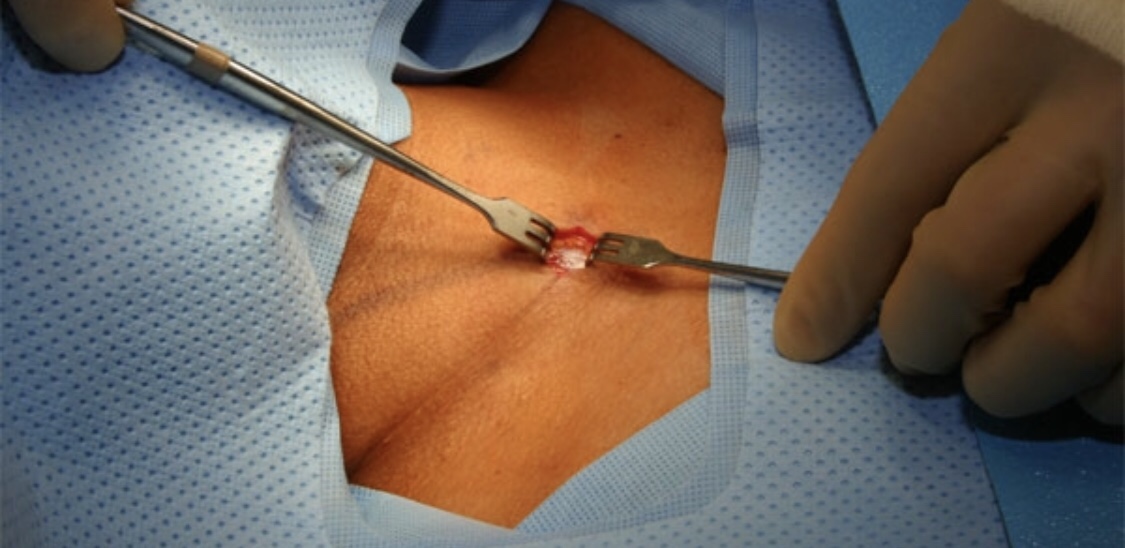
Hipercalcemia Hipocalciurica Familiar

👉 Una de las causas de hiperparatiroidismo primario persistente puede ser la Hipercalcemia hipocalciúrica familiar (FHH) no reconocida causada por una mutación del gen CaSR, lo que lleva a niveles bajos de calcio en la orina de 24 horas.

👉Más información: https://www.ncbi.nlm.nih.gov/pubmed/30449544

👉CheckYourCalcium (realízate un calcio total en sangre).

👉Para más información: http://www.hiperparatiroidismo.info

# CheckYourCalcium #Arrangoiz #ParathyroidExpert #ParathyroidSurgeon #Hiperparatiroidism #Hipercalcemia #CheckYourCalcium #HeadandNeckSurgeon #SociedadQuirurgica

Parathyroidectomy

👉Operative cure rates of 95% to 98% with complication rates of 1% to 2% are possible when parathyroidectomy is performed by experienced surgeons.” – Dr. Rodrigo Arrangoiz

👉Para más información: http://www.hiperparatiroidismo.info

#Arrangoiz #ParathyroidExpert #ParathyroidSurgeon #Hiperparatiroidism #Hipercalcemia #HeadandNeckSurgeon #SociedadQuirurgica #Hiperparatiroidismo #ExpertoenParatiroides #CirujanodeParatiroides

Definition of Goiter

  • Both greatest diameter and goiter weight have been used to define thyroid enlargement:
    • In studies, methods for determining goiter size range from:
      • Physical examination measured in centimeters, to physical examination estimated in grams, to surgical specimen measured in centimeters or grams
      • Preoperative imaging diameters may also be used
  • The definition of goiter varies substantially among reports:
    • McHenry 80 g as the threshold value
    • Russell 100 g as the threshold value
    • Clark 200 g as the threshold value
  • Studies investigating radioiodine treatment for multinodular goiter:
    • Often define significant goiter as:
      • Greater than 100 g
  • Hegedus, Nygaard, and Hansen found that goiter surgical specimens:
    • Averaged:
      • 30 g for unilateral resection
      • 64 g for bilateral resection
  • Katlic, Grillo, and Wang reported that:
    • The average weight of substernal goiter was:
      • 104 g (range 25 to 357 g)
      • Greatest diameter averaging 9 cm (range 5 to 19 cm)
  • In a series of more than 200 cervical and substernal goiters treated at Massachusetts Eye and Ear Infirmary and Massachusetts General Hospital:
    • The mean weight was 143 g
    • The mean goiter size was 10.5 cm
  • The World Health Organization (WHO) 1960 grading system for clinical assessment of goiter defines:
    • Stage 0 as no enlargement
    • Stages 1 to 3 describe progressive goiter enlargement:
      • Stage 1A:
        • Includes patients with palpable abnormalities
      • Stage 1B:
        • Includes patients with palpable and visual abnormalities with the neck in extension
      • Stage 2:
        • Is defined as a goiter that is visible with the neck in neutral position
      • Stage 3:
        • As a goiter that is able to be visualized at a considerable distance
  • The WHO 1994 goiter classification system is more streamlined:
    • Grade 0:
      • Is defined as no palpable or visual abnormality
    • Grade 1:
      • Is defined as a palpable thyroid mass that is not visualized with the neck in neutral position
    • Grade 2:
      • As a visually apparent mass with the neck in neutral position
  • Substernal GoiterSynonyms:
    • Substernal goiter and its subtypes have been termed:
      • Retrosternal, subclavicular, intrathoracic, mediastinal, aberrant, wandering, and spring goiter, as well as goiter mobile and goiter plongeant
  • Numerous definitions and classification schemes have been proposed for substernal goiter:
    • Lahey and Swinton defined substernal goiter as:
      • A “gland in which the greatest diameter of the intrathoracic component by x-ray was well below the upper aperture of the thoracic inlet”
    • Crile, in 1939, simply defined substernal goiter as:
      • A lesion extending to the aortic arch
    • Lindskog and Goldenberg in 1957 defined substernal goiter as:
      • A goiter whose lower border radiographically reaches the transverse process of the fourth thoracic vertebra or lower
    • Katlic, Grillo, and Wang described substernal goiter as:
      • When greater than 50% of the goiter is present substernally
    • Sanders et al. defined substernal goiter as:
      • That which requires mediastinal exploration and dissection for removal
  • Substernal classification schemes:
    • Higgins based his classification scheme on the percentage of goiter in the neck versus the percentage of goiter in the chest with:
      • Greater than 50% in the neck being described as:
        • Substernal
      • Greater than 50% in the chest as:
        • Partially intrathoracic
      • Greater than 80% in the chest as:
        • Completely intrathoracic
    • Cho, Cohen, and Som offered a grading system relating grade to percentage of goiter within the chest:
      • Grade I is defined as 0% to 25% of the goiter within the chest
      • Grade II as 26% to 50% of the goiter within the chest
      • Grade III as 51% to 75% of the goiter within the chest,
      • Grade IV as greater than 75% of the goiter within the chest
    • Shahian offered an interesting and detailed classification scheme:
      • Type I substernal goiter is associated with the anterior mediastinal extension:
        • Type IA involves “isolated” anterior mediastinal disease
        • Type IB involves “extensive” substernal involvement
      • Type II involves posterior mediastinal involvement:
        • Type IIA being isolated posterior mediastinal goiter
        • Type IIB posterior mediastinal goiter with ipsilateral extension relative to the thyroid lobe of origin
        • Type IIC contralateral extension relative to the thyroid lobe of origin:
          • C1 being retrotracheal
          • C2 being retroesophageal course
  • A classification system for substernal goiters is most useful when it takes into account the features of substernal goiters that must be appreciated to extract them safely:
    • Substernal goiter simply as those goiters that are associated with substernal extension such that the thoracic component requires mediastinal dissection to facilitate extraction
    • All substernal goiters require axial computed tomographic (CT) scanning to differentiate between the various subtypes
    • Such differentiation provides tremendously useful surgical information

#Arrangoiz #ThyroidSurgeon #ThyroidExpert #HeadandNeckSurgeon #CancerSurgeon #EndocrineSurgery #MultinodularGoiter #SubsternalGoiter #CASO #CenterforAdvancedSurgicalOncology