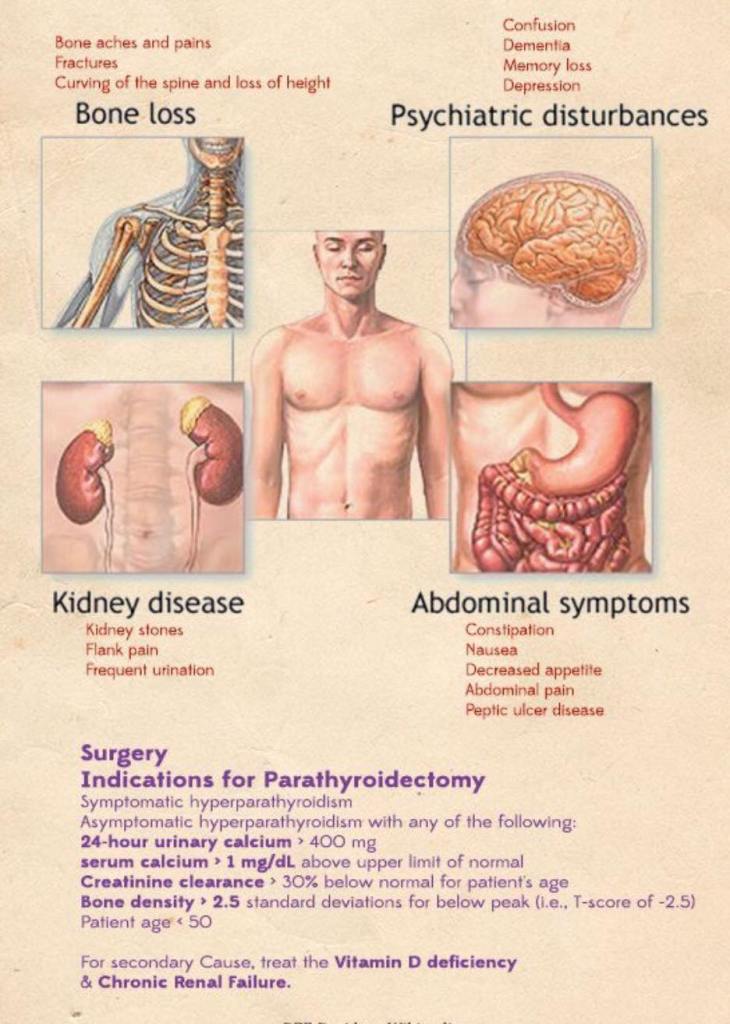
Blog

Guidelines for the Management of Asymptomatic Primary Hyperparathyroidism

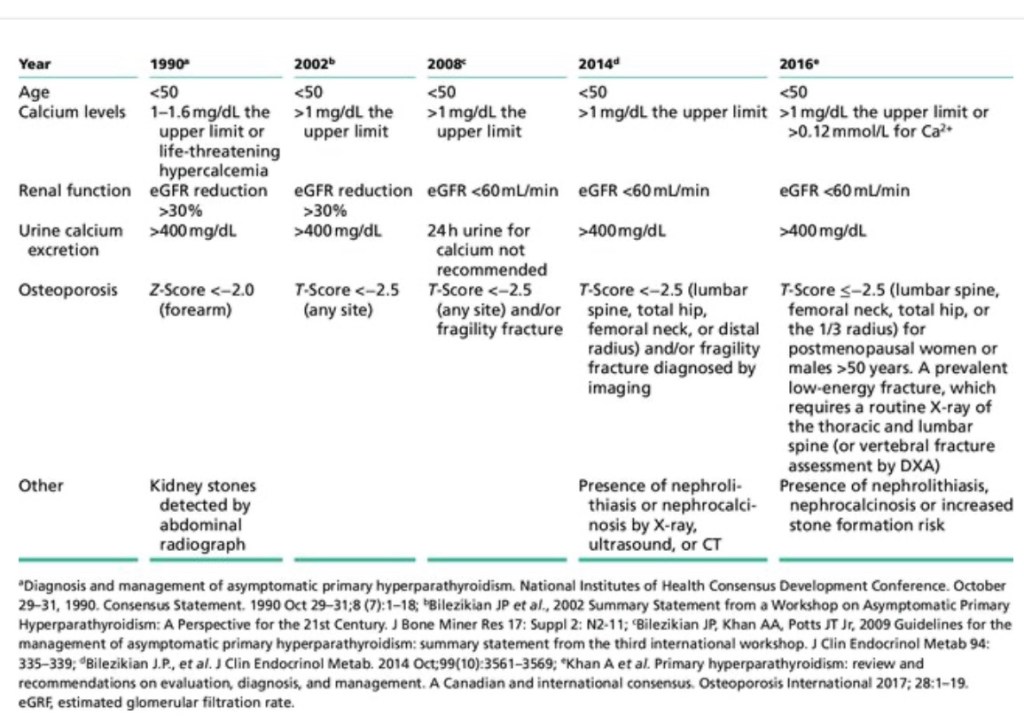
  • In 2014, the fourth international workshop released guidelines for the surgical management of asymptomatic PHPT
  • Guidelines for surgery in asymptomatic PHPT include:
    • Age less than:
      • 50 years old
    • A serum calcium measurement:
      • 1.0 mg/dL (0.25 mmol/L) above the upper limit of normal
    • Bone mineral density by dual-energy x-ray absorptiometry (DXA):
      • With a T-score < −2.5 at lumbar spine, total hip, femoral neck, or distal 1/3 radius
      • Vertebral fracture on x-ray, computed tomography (CT), magnetic resonance imaging (MRI)
    • 24-h urine for calcium:
      • > 400 mg/day (>10 mmol/day)
    • Increased risk of stone formation on biochemical stone risk analysis, or the presence of nephrolithiasis or nephrocalcinosis on x-ray, ultrasound, or CT
  • For patients with PHPT who do not undergo surgery:
    • Monitoring guidelines include at minimum:
      • Obtaining an annual serum calcium
      • DXA every 1 to 2 years
      • Annual estimated glomerular filtration rate (eGFR) / serum creatinine

#Arrangoiz #ParathyroidSurgeon #ParathyroidExpert #Hypercalcemia #PHPT #Hyperparathyroidism #PrimaryHyperparathyroidism #EndocrineSurgery #HeadandNeckSurgeon #CancerSurgeon #Surgeon #Teacher #Miami #Mexico #MountSinaiMedicalCenter #MSMC

Margins in Ductal Carcinoma In Situ

  • The standard adequate margin for patients with DCIS treated with breast-conserving surgery followed by whole-breast radiation is:
    • 2 mm:
    • Negative margins halve the risk of ipsilateral breast tumor recurrence (IBTR) compared with positive margins (defined as ink on DCIS)
  • A 2 mm margin minimizes the risk of IBTR relative to narrower negative margin widths:
    • However, larger margins (> 2 mm) do not significantly decrease IBTR
  • In 2016, margin guidelines related to the treatment of non-invasive breast cancer (e.g., DCIS) in the setting of breast-conservation therapy were developed by the Society of Surgical Oncology, American Society for Radiation Oncology, and the American College of Surgeons in a similar manner:
    • A consensus statement released by a multidisciplinary panel included the optimal margins for pure DCIS and mixed tumors (invasive and non-invasive components within the same tumor) in the setting of breast conservation:
      • Results from the meta-analysis showed that a 2 mm margin decreases the risk of IBTR in pure DCIS compared to closer negative margins:
        • This differs from the previous margin recommendation for invasive cancer, which remains no ink on tumor
      • In the setting of DCIS with micro-invasion (no focus of invasive disease larger than 1 mm):
        • The multidisciplinary panel recommends a 2 mm margin:
          • As these lesions have similar rates of IBTR as pure DCIS
      • However, in the setting of mixed tumors (invasive cancer with a DCIS component):
        • The recommendation for negative margins remains no ink on tumor:
          • As patients with mixed disease are treated as invasive cancer and therefore receive systemic therapy more often than pure DCIS patients
  • Patients with positive margins after breast-conserving surgery:
    • Should undergo re-excision:
      • Patients for whom adequate surgical margins cannot be achieved with lumpectomy:
        • Total mastectomy should be performed
  • Complete axillary lymph node dissection should not be performed in the absence of evidence of invasive cancer or proven axillary metastatic disease in women with apparent pure DCIS:
    • However, a small proportion of patients with apparent pure DCIS will be found to have invasive cancer at the time of their definitive surgical procedure:
      • Therefore, a sentinel lymph node biopsy should be strongly considered if the patient with apparent pure DCIS is to be treated with mastectomy or with excision in an anatomic location compromising the performance of a future sentinel lymph node procedure
  • References
    • Morrow M, Van Zee KJ, Solin LJ, et al. Society of Surgical Oncology-American Society for Radiation Oncology-American Society of Clinical Oncology consensus guideline on margins for breast-conserving surgery with whole-breast irradiation in ductal carcinoma in situ. J Clin Oncol. 2016;34(33):4040-4046.
    • Breast cancer. National Comprehensive Cancer Network. 2018. https://www.nccn.org/professionals/physician_gls/pdf/breast.pdf. Accessed September 9, 2018.
#Arrangoiz #BreastCancer #BreastSurgeon #SurgicalOncologist #DCIS #Margins #MountSinaiMedicalCenter #MSMC #Miami #Mexico

Local Treatment for Ductal Carcinoma In Situ

  • Local treatment for ductal carcinoma in situ (DCIS) involves:
    • Mastectomy or breast-conserving therapy:
      • Which consists of partial mastectomy:
        • Followed in most cases by adjuvant radiation therapy
    • Sentinel lymph node biopsy (SLNB) is not indicated for most patients undergoing breast-conserving therapy for DCIS:
      • Because DCIS is a preinvasive lesion, axillary nodes are rarely involved:
        • Even in cases of extensive multifocal high-grade disease
  • If invasive breast cancer is identified after a breast-conserving surgery is performed for DCIS:
    • SLNB can be performed as a second procedure
  • If a mastectomy is performed as the initial procedure:
    • A sentinel node biopsy should be performed in the event of an occult invasive cancer
  • Radiation therapy alone is not given for DCIS:
    • Although there are ongoing clinical trials comparing active surveillance to surgery with or without endocrine therapy:
      • These are reserved for low- and intermediate-grade DCIS and are not yet considered standard of care
  • References
    • Virnig BA, Tuttle TM, Shamliyan T, Kane RL. Ductal carcinoma in situ of the breast: a systematic review of incidence, treatment, and outcomes. J Natl Cancer Inst 2010; 102:170.
    • Lyman GH, Giuliano AE, Somerfield MR, et al. American Society of Clinical Oncology guideline recommendations for sentinel lymph node biopsy in early-stage breast cancer. J Clin Oncol. 2005;23(30):7703-7720.
    • Intra M, Rotmensz N, Veronesi P, et al. Sentinel node biopsy is not a standard procedure in ductal carcinoma in situ of the breast: the experience of the European Institute of Oncology on 854 patients in 10 years. Ann Surg. 2008;247(2):315-319.
    • Brennan ME, Turner RM, Ciatto S, et al. Ductal carcinoma in situ at core-needle biopsy: meta-analysis of underestimation and predictors of invasive breast cancer. Radiology. 2011;260(1):119-128.
    • Youngwirth LM, Boughey JC, Hwang ES. Surgery versus monitoring and endocrine therapy for low-risk DCIS: The COMET Trial. Bull Am Coll Surg. 2017;102(1):62-63.
#Arrangoiz #BreastSurgeon #BreastCancer #CancerSurgeon #SurgicalOncology #MountSinaiMedicalCenter #MSMC #Miami #Mexico

Epidemiology and Etiology of Primary Hyperparathyroidism (PHPT)

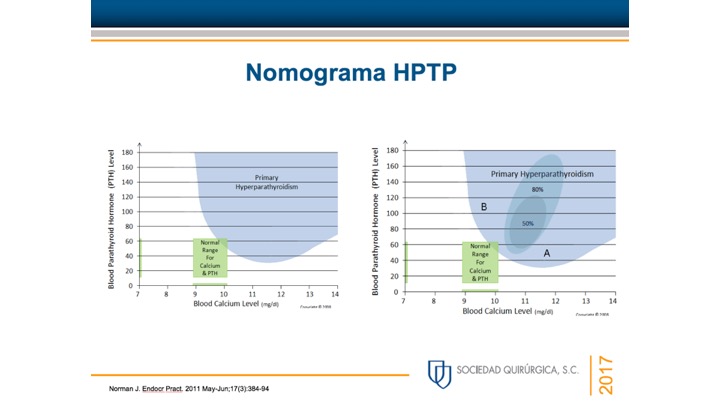
  • PHPT is defined as hypercalcemia or widely fluctuating levels of serum calcium levels:
    • Resulting from the inappropriate or autogenous secretion of PTH by one or more parathyroid glands:
      • In the absence of a known or recognized stimulus
  • The most common cause of hypercalcemia in the outpatient setting is PHPT:
    • With approximately 100,000 new cases per year reported in the United States
  • Since the advent of routine laboratory testing:
    • The prevalence of the disease has increased from 0.1% to 0.4%:
      • One to seven cases per 1000 adults
  • In a study by Yeh et al., the incidence of PHPT fluctuated between:
    • 36.3 and 120.2 cases per 100,000 women-years
    • 13.4 and 35.6 in 100,000 men-years
  • PHPT may present at any age:
    • With the vast majority of cases occurring in patients older than 45 years of years
  • Women have consistently made up the preponderance of cases:
    • With a female-to-male ratio of:
      • 3:1 to 4:1
    • Based on a population based study from Rochester Minnesota:
      • The higher incidence of this could be secondary (hypothetically) to estrogen deficiency after menopause that reveals underlying HPT
  • The precise origin of PHPT is unknown:
    • Although exposure to low-dose therapeutic ionizing radiation and familial predisposition account for some cases:
      • Irradiation for acne could have accounted for a 2 to 3-fold increase in the incidence of this disease at some point in time, and a 4-fold increase was noted in survivors of the atomic bomb
    • Schneider et al., in their study of 2555 patients followed for 50 years, even low doses of radiation exposure during the teenage years was associated with a slight risk of developing PHPT:
      • In this study a dose response was documented in people receiving external-beam radiotherapy for benign diseases before their 16th birthday
    • The latency period for the development of PHPT after radiation exposure is longer than that for the development of thyroid tumors:
      • With most cases occurring 30 to 40 years after exposure
    • Patients who have been radiated have similar clinical manifestations and serum calcium levels when compared to patients without a history of radiation exposure:
      • However, the former tend to have higher PTH levels and a higher incidence of concomitant thyroid neoplasms
    • Certain medications have been implicated in the development of hypercalcemia:
      • Lithium therapy has been known to shift the set point for PTH secretion in parathyroid cells:
        • Thereby resulting in elevated PTH levels and mild hypercalcemia
        • Lithium stimulates the growth of abnormal parathyroid glands in vitro and also in susceptible patients in vivo
        • Unusual metabolic features associated with lithium use include:
          • Low urinary calcium excretion
          • Normal cyclic AMP excretion
          • Lack of calcic nephrolithiasis
        • The mechanism probably results from lithium linking with the calcium sensing receptor on the parathyroid glands:
          • Resulting in PTH secretion
      • Elevated serum calcium levels have been associated with thiazide diuretic:
        • The overall annual age- and sex-adjusted (to 2000 U.S. whites) incidence was:
          • 7.7 (95% CI, 5.9 to 9.5) per 100,000 individuals
        • The average 24-hour plasma calcium concentrations are increased with thiazide diuretic use:
          • But the mean 24-hour PTH levels remain unchanged in subjects with normal baseline PTH levels and no evidence of hypercalciuria
        • Thiazides diuretics have several metabolic effects that may contribute to increased calcium levels:
          • A decrease in urine calcium excretion is the most likely cause:
            • But in some cases diuretic use has been associates with a metabolic alkalosis:
              • That could increase the total serum calcium levels through a pH-dependent increase in protein-bound calcium
            • Although plasma 1,25 (OH) vitamin D levels are unchanged:
              • Increased intestinal calcium absorption in response to thiazide diurectic use has been noted and could also contribute to an increase in serum calcium
          • One last possible explanation for the elevated serum calcium levels associated with thiazide diuretic use is hemoconcentration associated with dieresis
    • Numerous genetic abnormalities have been identified in the development of PHPT, including anomalies in tumor suppressor genes and proto-oncogenes. Specific DNA mutations in a parathyroid cell may confer a proliferative advantage over normal neighboring cells, thus allowing for clonal growth.:
      • Large populations of these altered cells containing the same mutation within hyper functioning parathyroid tissue suggest that such glands are a result of clonal expansion
      • The majority of PHPT cases are sporadic
      • Nonetheless, PHPT also occurs within the spectrum of a number of inherited disorders such as:
        • Multiple endocrine neoplasia syndromes (MEN):
          • MEN type 1 (Wermer Syndrome
          • MEN type 2A (Sipple Syndrome)
        • Isolated familial HPT
        • Familial HPT with jaw-tumor syndrome
      • All of these syndromes are inherited in an:
        • Autosomal dominant fashion

#Arrangoiz #ParathyroidSurgeon #ParathyroidExpert #Hyperparathyroidism #PrimaryHyperparathyroidism #CancerSurgeon #EndocrineSurgery #Teacher #Surgeon #HeadandNeckSurgeon #SurgicalOncologist #ParathyroidAdenoma #Hypercalcemia #ElevatedCalciumLevels #Miami #MountSinaiMedicalCenter #MSMC #Mexico #Hialeah

Generalities of Primary Hyperparathyroidism (PHPT)

  • Primary hyperparathyroidism (PHPT) is seen in:
    • 0.1% to 0.5% of the adult population
  • It is the most common cause of hypercalcemia (high calcium level) in the general population
  • It is about three to four times more common in women than men (3:1 to 4:1)
  • Patients are usually older, with an average age at presentation of 65 years (most cases are over 45 years)
  • Learn more at:

#Arrangoiz #ParathyroidSurgeon #ParathyroidExpert #Hyperparathyroidism #PrimaryHyperparathyroidism #CancerSurgeon #EndocrineSurgery #Teacher #Surgeon #HeadandNeckSurgeon #SurgicalOncologist #ParathyroidAdenoma #Hypercalcemia #ElevatedCalciumLevels #Miami #MountSinaiMedicalCenter #MSMC #Mexico #Miami #Hialeah

Hyperparathyroidism

👉Primary hyperparathyroidism most commonly occurs in women over the age of 45, however, ANYONE can develop it.

👉Therefore, anyone found to have high blood calcium levels should be evaluated for primary hyperparathyroidism.

#Arrangoiz #ParathyroidSurgeon #ParathyroidExpert #HeadandNeckSurgron #CheckYourCalcium #Miami #Mexico #MountSinaiMedicalCenter

Julio es el mes de la conciencia de la enfermedad paratiroidea!

👉Julio es el mes de la conciencia de la enfermedad paratiroidea!

👉Ayude a correr la voz y cuéntenos sobre su experiencia con la enfermedad paratiroidea.

👉 ¿Cómo se enteró del hiperparatiroidismo por primera vez? ¿Te diagnosticaste a ti mismo?

👉 ¿Pudiste diagnosticar a un amigo porque notaste las señales?

👉¡Cuéntanos sobre eso! Y si diagnosticaste a un amigo, envíelo a Rodrigo Arrangoiz, miembro de Sociedad Quirúrgica SC experto en el manejo del hiperparatiroidismo.

👉 Para obtener más información, vaya a http://www.hiperparatiroidismo.info

#Arrangoiz #ParathyroidExpert #ParathyroidSurgeon #Hiperparatiroidismo #Hipercalcemia #CheckYourCalcium #HeadandNeckSurgeon #EndocrineSurgeon #CirujanodeTumoresdeCabezayCuello #CirugiaEndocrina #CirugiaParatiroides #Hypercalcemia #Hyperparathyroidism #MountSinaiMedicalCenter #MSMC #Miami #Mexico

https://rodrigoarrangoizmd.wordpress.com/2019/07/04/julio-es-el-mes-de-la-conciencia-de-la-enfermedad-paratiroidea/

  • Absolute contraindications to breast-conserving therapy include:
    • Prior radiation therapy to the breast or chest wall
    • Breast cancer early in pregnancy that would necessitate radiation therapy during pregnancy
    • Diffuse suspicious, malignant-appearing microcalcifications
    • Widespread disease that precludes negative margins with a satisfactory cosmetic result
  • Retrospective reviews have shown that patients with collagen vascular diseases, specifically scleroderma:
    • Are at increased risk of radiation toxicities, even with modern techniques:
      • Therefore, the presence of scleroderma in this patient would be a relative contraindication for breast-conserving surgery in this patient
  • There have been attempts to allow for breast-conserving surgery for selected patients with multifocal or multicentric disease:
    • Retrospective data suggest that although patients with multifocal or multicentric disease have increased risk of local recurrence and lower disease-free survival:
      • This finding is independent of the type of surgery performed
  • The Alliance Z11102 study sought to prospectively determine whether patients with multiple ipsilateral breast cancers could safely undergo breast-conserving surgery:
    • Initial report in 2018 showed that breast-conserving surgery was feasible in 93% of patients:
      • This could be accomplished in one operation in 67% of cases
    • Data regarding local regional recurrence will be forthcoming
  • Percutaneous ablation techniques such as cryoablation have promising potential for less-invasive management of breast cancer:
    • However, it is not recommended for multicentric disease
      • Large multicenter randomized clinical trials are needed to determine long-term efficacy
  • References
    • Morrow M, Strom EA, Bassett LW, et al. Standard for breast conservation therapy in the management of invasive breast carcinoma. CA Cancer J Clin. 2002;52(5):277-300.
    • Breast cancer. National Comprehensive Cancer Network. 2018. https://www.nccn.org/professionals/physician_gls/pdf/breast.pdf. Accessed September 9, 2018.
    • Zaremba N, Tamkus D, DiCarlo L, Herman J, Martin M, Bumpers HL. The dilemma of breast cancer treatment and existing collagen vascular disease: a case of scleroderma and review of the literature. Breast J. 2016;22(4):451-455.
    • Alm El-Din MA, Taghian AG. Breast conservation therapy for patients with locally advanced breast cancer. Semin Radiat Oncol. 2009;19(4):229-235.
    • Rosenkranz KM, Ballman K, McCall L, Kubicky C, Cuttino L, Le-Petross H, et al. The feasibility of breast-conserving surgery for multiple ipsilateral breast cancer: an initial report from ACOSOG Z11102 (Alliance) Trial. Ann Surg Oncol. 2018;25(10):2858-2866.
    • Lanza E, Palussiere J, Buy X, et al. Percutaneous image-guided cryoablation of breast cancer: a systematic review. J Vasc Interv Radiol. 2015;26(11):1652-1657.
#Arrangoiz #BreastSurgeon #CancerSurgeon #SurgicalOncologist #MountSinaiMedicalCenter #MSMC #Miami #Mexico

Trends of Axillary Treatment in Sentinel Node-Positive Breast Cancer Patients Undergoing Mastectomy

  • During the last decade, the necessity to perform axillary lymph node dissection (ALND) in clinically node-negative (cN0) patients with sentinel lymph node metastases (SLN+) is debated worldwide:
    • For patients with early breast cancer undergoing breast-conserving therapy (BCT), the ACOSOG-Z0011 trial has allowed for avoidance of unnecessary axillary lymph node dissection (ALND) in patients with 1–2 positive SLNs without compromising outcome
  • The AMAROS trial investigated axillary radiotherapy (RT) versus ALND in patients with tumor-affected SLNs and showed that axillary RT could serve as a safe alternative to ALND with less morbidity
  • Since 2012, both national and international guidelines suggest no further axillary treatment in patients meeting the Z0011 criteria or advocate regional radiotherapy (RT) as alternative therapy for ALND
  • As patients treated with mastectomy were not included in the Z0011 and underrepresented in the AMAROS trial (with only 18% receiving mastectomy), evidence regarding the omission of ALND in this subset of patients is scarce
  • In a Dutch study, which included 10,633 SLN+ patients with cT1 to T3 breast cancer who underwent mastectomy, the frequency of ALND decreased from 78% in 2009 to 10% in 2018. In patients with micrometastasis (N1mi) and isolated tumor cells (N0itc), ALND was soon abandoned, whereas 20% of patients diagnosed with ≥ N1a disease still underwent ALND at the end of the study period. Over the same period, postmastectomy radiotherapy (PMRT) increased from 4% to 49%. The increase of PMRT was merely seen in patients with ≥ N1a disease, from 2% to 70%, showing ALND is mostly replaced with PMRT in this group of patients. Besides the association between the degree of metastatic lymph node involvement and the performance of ALND, factors such as age, differentiation grade, tumor subtype, and hospital type affected the performance of ALND.
    • Factors associated with a higher chance of ALND performance were age < 40 years, lobular tumor type, basal-like tumor type, receiving chemotherapy, and treatment outside an academic institution
  • The present data illustrate a strong reduction in the performance of ALND in SLN+ patients undergoing mastectomy. Recently, the results of the SINODAR-ONE trial, which included a substantial proportion of SLN+ patients treated by mastectomy (25%) showed excellent regional control among SLN+ patients who received no further local treatment
  • Currently, there are two more ongoing trials evaluating the oncological safety of omitting axillary therapy in node-positive patients treated by mastectomy (the POSNOC trial and the SENOMAC trial)
  • The observed tendency among clinicians to deescalate axillary surgery in the present study suggests that clinicians felt comfortable enough to avoid ALND in this subset of patients despite the limited evidence
  • Long-term follow-up results from the aforementioned trials, possibly supported by outcome data from national registries, may not only provide more robust support for avoiding surgical staging of axillary lymph nodes, but may also help to better delineate the indication for radiotherapy when ALND is omitted
  • References
    • Giuliano AE, Ballman KV, McCall L, et al. Effect of axillary dissection vs no axillary dissection on 10-year overall survival among women with invasive breast cancer and sentinel node metastasis: the ACOSOG Z0011 (Alliance) Randomized Clinical Trial. JAMA. 2017;318(10):918–26.Article PubMed PubMed Central Google Scholar
    • Donker M, van Tienhoven G, Straver ME, et al. Radiotherapy or surgery of the axilla after a positive sentinel node in breast cancer (EORTC 10981–22023 AMAROS): a randomised, multicentre, open-label, phase 3 non-inferiority trial. Lancet Oncol. 2014;15(12):1303–10.Article PubMed PubMed Central Google Scholar
    • Tinterri C, Gentile D, Gatzemeier W, et al. Preservation of axillary lymph nodes compared with complete dissection in T1–2 breast cancer patients presenting one or two metastatic sentinel lymph nodes: the SINODAR-ONE multicenter randomized clinical trial. Ann Surg Oncol. 2022;29(9):5732–44.Article PubMed Google Scholar
    • Goyal A, Mann GB, Fallowfield L, et al. POSNOC-POsitive Sentinel NOde: adjuvant therapy alone versus adjuvant therapy plus clearance or axillary radiotherapy: a randomised controlled trial of axillary treatment in women with early-stage breast cancer who have metastases in one or two sentinel nodes. BMJ Open. 2021;11(12):e054365.Article PubMed PubMed Central Google Scholar
    • de Boniface J, Frisell J, Andersson Y, et al. Survival and axillary recurrence following sentinel node-positive breast cancer without completion axillary lymph node dissection: the randomized controlled SENOMAC trial. BMC Cancer. 2017;17(1):379.
#Arrangoiz #CancerSurgeon #BreastSurgeon #SurgicalOncologist #MountSianiMedicalCenter #MSMC #Mexico #Miami

Generalities of Hyperparathyroidism

  • Single gland adenoma is the most common cause:
    • (75% to 90% of the cases of PHPT
  • Lower pole adenomas (in relation to the thyroid):
    • Are more common than are upper pole adenomas
  • The average size of a parathyroid gland is:
    • 6 mm X 4 mm X 2 mm
  • The sizes of a parathyroid adenoma range from:
    • 1 cm to 3 cm
  • The normal weight of a parathyroid gland is:
    • Approximately 40 mg to 50 mg
  • The weight of parathyroid adenomas vary between:
    • 553.7 +/- 520.5 mg (range, 66-2536)
  • Ectopic glands can be present in:
    • 4% to 16% of cases
  • PHPT is caused by:
    • The enlargement of a single parathyroid gland or parathyroid adenoma in approximately 75% to 90% of the cases
    • Multi-disease is seen in 15% to 25% of the cases:
      • Double adenomas:
        • Are seen in approximately 2% to 12% of the cases
      • Triple adenomas:
        • In less than 1% the cases (0.2%)
      • Four adenomas or parathyroid gland hyperplasia:
        • In less than 3% to 15% of the cases
    • Parathyroid carcinoma as the cause of PHPT is extremely rare in most parts of the world (~1%)
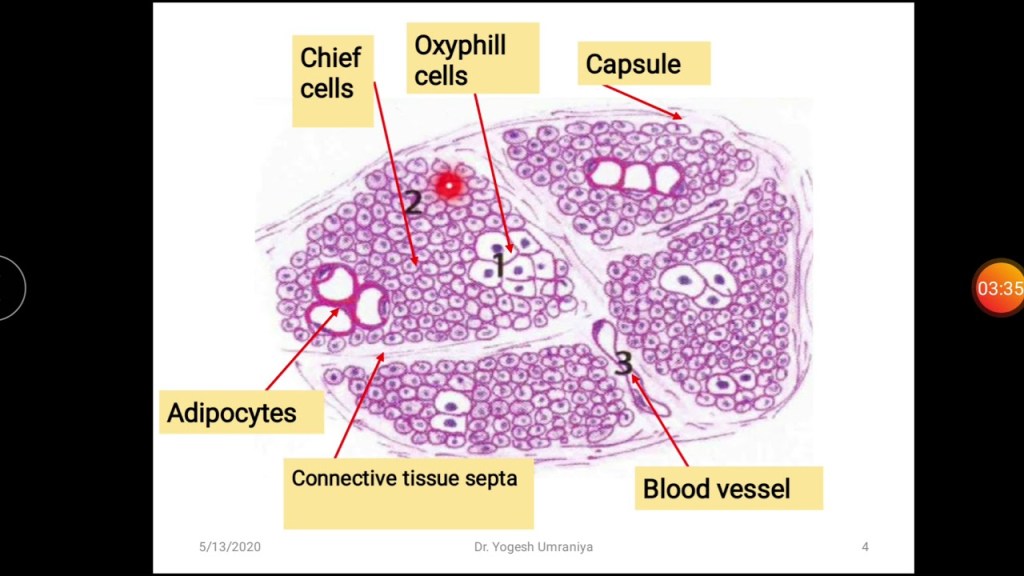
  • Most parathyroid adenomas consist of parathyroid chief cells:
    • They are usually encapsulated
    • In 50% of the cases they are surrounded by normal parathyroid tissue
  • Some adenomas, nevertheless, are composed of oxyphil cells
    • These adenomas are usually larger than chief cell adenomas
  • Parathyroid adenomas are sometimes located within the thymus:
    • They express a parathyroid-specific gene:
      • GCMB:
        • Contrasting with the normal thymus:
          • Which does not express neither PTH nor GCMB
  • In a study by Ruda et al:
    • 20, 225 patients with PHPT:
    • Parathyroid hyperplasia accounted for approximately six percent of cases
    • In parathyroid hyperplasia all four glands are enlarged:
      • With the lower glands typically being larger than the upper ones
      • The glands are usually composed of chief cells
      • Clear cell hyperplasia is very rare:
        • And is the only form in which the upper glands are larger than the lower ones

#Arrangoiz #ParathyroidSurgeon #ParathyroidExpert #HeadandNeckSurgeon #CancerSurgeon #EndocrineSurgery #Hyperparathyroidism #MountSinaiMedicalCenter #MSMC #Miami #Mexico