
Blog

Pathophysiology of Primary Hyperparathyroidism (PHPT)

  • In primary hyperparathyroidism due to adenomas:
    • The normal feedback on parathyroid hormone production by extracellular calcium seems to be lost:
      • Resulting in a change in the set point
  • In primary hyperparathyroidism from parathyroid hyperplasia:
    • An increase in the cell numbers is probably the cause of the change in the set point
  • The chronic excessive resorption of calcium from bone caused by excessive parathyroid hormone can result in:
    • Osteopenia
    • In severe cases, this may result in osteitis fibrosa cystica:
      • Which is characterized by subperiosteal resorption of the distal phalanges, tapering of the distal clavicles, salt-and-pepper appearance of the skull, and brown tumors of the long bones
        • This is not commonly seen now
  • In addition, the chronically increased excretion of calcium in the urine:
    • Can predispose to the formation of renal stones
  • The other symptoms of hyperparathyroidism:
    • Are due to the hypercalcemia itself:
      • And are not specific to hyperparathyroidism
    • These can include:
      • Muscle weakness
      • Fatigue
      • Volume depletion
      • Nausea and vomiting
      • In severe cases, coma and death
    • Neuropsychiatric manifestations are particularly common and may include:
      • Depression
      • Confusion
      • Subtle deficits that are often characterized poorly and may not be noted by the patient (or may be attributed to aging)
    • Increased calcium can increase gastric acid secretion, and persons with hyperparathyroidism:
      • May have a higher prevalence of peptic ulcer disease
    • Rare cases of pancreatitis have also been attributed to hypercalcemia
  • A prospective cohort study by Ejlsmark-Svensson et al:
    • Reported that in patients with primary hyperparathyroidism, quality-of-life questionnaire scores were significantly lower:

      • In association with moderate-severe hypercalcemia:
        • Than in relation to mild hypercalcemia:
          • However, quality of life did not seem to be related to the presence of organ-related manifestations of primary hyperparathyroidism, such as osteoporosis, renal calcifications, and renal function impairment
          • This suggests that hypercalcemia is the primary driver of an impaired quality of life

#Arrangoiz #PrimaryHyperparathyroidism #Hyperparathyroidism #Hypercalcemia #ParathyroidSurgeon #ParathyroidExpert #HeadandNeckSurgeon #EndocrineSurgery #MSMC #MountSinaiMedicalCenter #Mexico #Miami

Postoperative Radioactive Iodine (RAI) use in ATA Intermediate-Risk Differentiated Thyroid Cancer (DTC)

  • Postoperative radioactive iodine (RAI) use in ATA intermediate-risk differentiated thyroid cancer (DTC):
    • With stratification into low‑intermediate and high‑intermediate subsets
  • Evidence Base Overview:
    • No randomized trials specifically focus on RAI impact in ATA intermediate-risk patients
    • Evidence is primarily retrospective:
      • Using multivariate, propensity-adjusted analyses, registry data (SEER), cohort series, and a few prospective studies
  • ATA Intermediate‑Risk Definition:
    • The 2015 ATA guidelines (1) classified patients as intermediate-risk if they exhibit:
      • Microscopic extrathyroidal extension (ETE)
      • Vascular invasion
      • Clinical N1 or > 5 pathologic N1 with nodes < 3 cm
      • Aggressive histotypes (e.g., Hobnail, tall cell, insular)
      • RAI-avid foci outside thyroid bed
      • Multifocal microcarcinoma with ETE and BRAF mutation 
  • Within this, it’s helpful to subdivide into (most likely will appear in the new 2025 ATA guidelines):
    • Low-intermediate:
      • A single low-volume risk feature:
        • Microscopic ETE
        • Small-volume N1a
    • High-intermediate:
      • Multiple or higher-risk features, such as:
        • ≥ 5 nodes
        • Vascular invasion
  • Observational and Registry Data:
    • SEER Registry Studies (2,3):
      • Showed improved overall survival following RAI in:
        • N1 disease
        • pT3 (or > 4 cm)
        • Aggressive histology 
      • However:
        • Absolute benefit is small in patients < 45 years (~ 1%) vs larger in older patients (~ 4%) (3)
    • Single‑Center Cohorts:
      • Mayo Clinic (4) (20‑year follow-up):
        • Found no impact on outcomes for node-positive with MACIS < 6 
      • One Hong Kong study (5):
        • Showed better lymph node recurrence-free survival post-RAI in:
          • N1b or nodes > 1 cm
  • Retrospective Low–Intermediate Series (6) (Italy, 2024):
    • RAI reduced recurrence by 42%:
      • 9.6% vs 15.9% using inverse‑probability regression in patients with ≥ 2 intermediate risk factors 
  • Polish Prospective RAI Dose Trial (Arch Med Sci, 2022): (7)
    • Intermediate-risk group receiving 60 vs 100 mCi:
      • Had similar excellent response (~ 85%), low structural recurrence (~ 6.5%), and excellent long-term outcomes 
  • Prospective / Clinical Trials:
    • No RCTs isolating intermediate-risk exist:
      • However, the rhTSH + RAI Prep trial included many intermediate-risk patients (n ≈ 307) and found non-inferiority of rhTSH vs withdrawal for RAI effectiveness (8)
  • Guideline Position Statements:
    • The 2015 ATA guidelines recommend selective use of RAI in intermediate-risk DTC based on individual risk features, with a weak recommendation and low-quality evidence (1)
    • The 2022 European Thyroid Association / EANM consensus also supports personalized RAI use in this group, prioritizing shared decision-making and individual risk-benefit assessment (9)
  • Clinical Take‑Home Points:
    • Selective RAI yields a survival / recurrence benefit:
      • Strongest in older patients or those with > 1 intermediate risk feature
    • Low-intermediate risk (e.g., single small node, microscopic ETE):
      • RAI benefit is less definitive:
        • Consider active surveillance vs low-dose RAI
      • High‑intermediate risk (multi-node, vascular invasion, aggressive histology):
        • More likely to benefit:
          • RAI recommended:
        • Dose considerations:
          • 60 mCi sufficient for intermediate risk (Polish RCT)
        • rhTSH prep is validated
        • Shared decision-making essential, given evidence limitations and QoL trade-offs
  • Recommendation Framework:
    • Low‑intermediate (one minor feature, younger age):
      • Discuss omission vs low-dose RAI (e.g., 60 mCi + rhTSH) with surveillance plan
    • High‑intermediate (multi-factor, older age):
      • Offer RAI routinely; evidence supports 60 to 100 mCi
    • Shared consent vital, addressing patient goals, comorbidities, and center’s surveillance capabilities
  • References:
    • 1. Haugen BR, et al. 2015 ATA Management Guidelines for Adult Patients with Thyroid Nodules and Differentiated Thyroid Cancer. Thyroid. 2016;26(1):1–133.
    • 2. Nixon IJ, et al. The impact of RAI on survival in intermediate-risk patients: SEER analysis. Ann Surg Oncol. 2012;19(6):2025–33.
    • 3, Haymart MR, et al. Radioactive iodine in thyroid cancer: SEER-based outcomes. JAMA. 2011;306(7):721–8.
    • 4. Mazzaferri EL, et al. Management of differentiated thyroid cancer: Mayo Clinic experience. J Clin Endocrinol Metab. 2001;86(4):1447–63.
    • 5. Lam AK, et al. RAI impact on lymph node recurrence: Hong Kong cohort study. Cancer. 2005;103(5):920–9.
    • 6. Prete A, et al. Benefit of RAI in intermediate-risk DTC patients with multiple features. Endocrine. 2024;84(1):123–131.
    • 7. Piciu D, et al. Prospective evaluation of 60 vs 100 mCi in intermediate-risk thyroid cancer. Arch Med Sci. 2022;18(4):1002–1012.
    • 8. Mallick U, et al. Preparation for RAI: rhTSH vs withdrawal in low- and intermediate-risk patients. Lancet. 2012;379(9825):823–830.
    • 9. Luster M, et al. EANM/ETA consensus on RAI therapy in thyroid cancer. Eur J Nucl Med Mol Imaging. 2022;49(1):13–25.

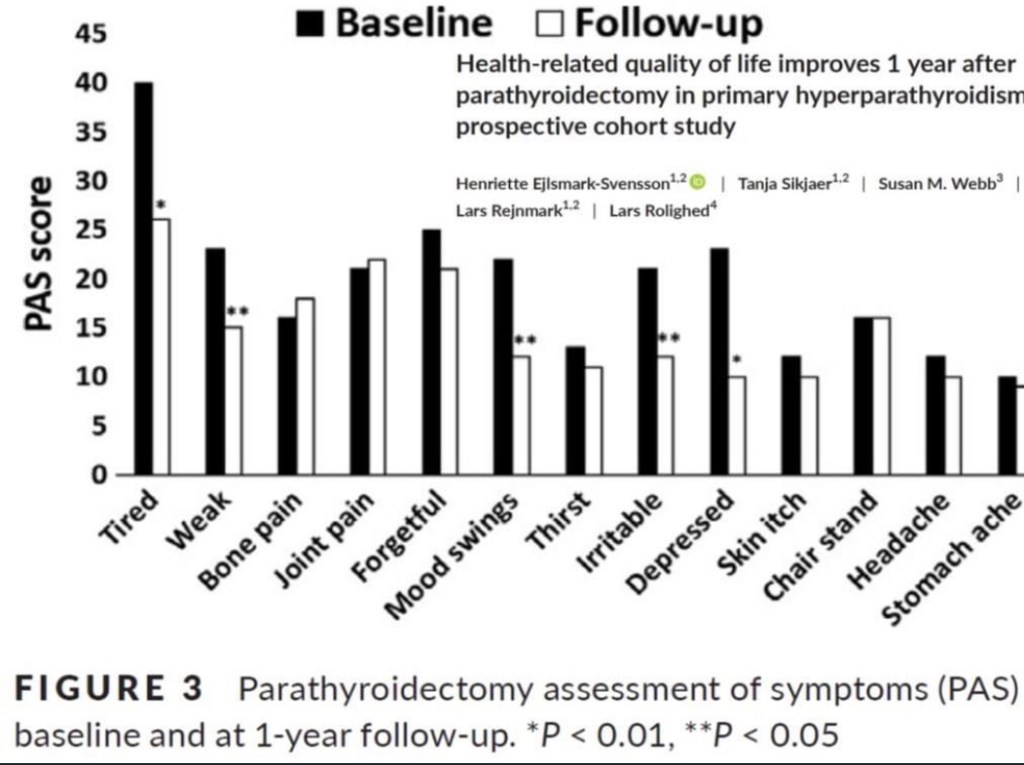
Parathyroid Awareness Month

Health‐related quality of life commonly improves following parathyroidectomy for primary hyperparathyroidism.

https://www.ncbi.nlm.nih.gov/pubmed/30267589

#CheckYourCalcium #JAM2020 American #Arrangoiz #ParathyroidSurgeon #EndocrineSurgery #ParathyroidExpert #HeadandNeckSurgeon #MountSinaiMedicalCenter MSMC #Miami #Mexico

The Delphi Criteria for Advanced Disease in Thyroid Cancer

  • The Delphi criteria for advanced disease in thyroid cancer:
    • Refer to a consensus-based set of clinical, pathological, and radiological features:
      • Developed by expert panels (often using the Delphi method):
        • To define what constitutes advanced thyroid cancer
    • These criteria help guide decision-making:
      • In terms of treatment strategies, referral to tertiary centers, and inclusion in clinical trials
  • While there is no universal single set of “Delphi criteria” adopted globally for thyroid cancer:
    • Multiple Delphi panels have been convened in recent years to create consensus on what features define advanced or aggressive disease
  • Below is a synthesis of key features commonly included in such panels and used in high-level consensus guidelines:
    • ATA, NCCN, and expert Delphi studies
  • Delphi-Based Criteria for Advanced Thyroid Cancer:
    • Clinical Features:
      • Age > 55 years:
        • For differentiated thyroid cancer (DTC)
      • Rapid tumor growth
      • Hoarseness or vocal cord paralysis
      • Dysphagia or airway compression
      • Distant metastases:
        • Lung, bone, brain
      • Recurrent or persistent disease after initial therapy
    • Pathological Features:
      • High-risk histologies:
        • Poorly differentiated thyroid carcinoma
        • Anaplastic thyroid carcinoma
        • Hürthle cell carcinoma with widely invasive features
        • Tall cell, hobnail, or columnar variants of PTC
        • Extensive vascular invasion
        • Extrathyroidal extension:
          • Especially gross
        • Incomplete resection margins:
          • R2 or R1
    • Radiological Features:
      • Evidence of invasion into adjacent structures::
        • Trachea, esophagus, larynx, recurrent laryngeal nerve, carotid artery
      • Radiographic evidence of unresectability
      • Distant metastases confirmed via CT, MRI, or PET / CT
    • Molecular/Functional Criteria:
      • RAI-refractory disease:
        • Based on functional imaging and response
      • Presence of high-risk mutations:
        • TERT promoter
        • TP53
        • BRAF + TERT
      • High FDG-avidity on PET scan:
        • Often correlates with aggressiveness
    • Biochemical Markers:
      • Rapidly rising thyroglobulin levels post-thyroidectomy and RAI
      • Elevated Tg levels with negative RAI uptake:
        • Suggesting RAI-refractory disease
  • Notable Delphi Studies / Consensus Papers:
    • Tuttle RM et al., Memorial Sloan Kettering Cancer Center: Clinical criteria for RAI-refractory DTC
    • American Thyroid Association (ATA) 2015 Guidelines: Use a similar risk stratification model that incorporates many of these features
    • NCCN Guidelines (latest version): Lists features of unresectable, progressive, or symptomatic disease requiring systemic therapy
    • Molecular Oncology Tumor Boards have also developed decision-making algorithms based on Delphi consensus

Hunry Bone Syndrome Post-Parathyroidectomy

  • After initial parathyroidectomy, reported rates of moderate postoperative hypocalcemia range from 5% to 47%:
    • However, permanent hypoparathyroidism and severe hypocalcemia due to hungry bone syndrome are rare

#Arrangoiz #ParathyroidSurgeon #ParathyroidExpert #Hyperparathyroidism #PrimaryHyperparathyroidism #CancerSurgeon #EndocrineSurgery #Teacher #Surgeon #HeadandNeckSurgeon #SurgicalOncologist #ParathyroidAdenoma #Hypercalcemia #ElevatedCalciumLevels #Miami #MountSinaiMedicalCenter #MSMC #Mexico #Hialeah

ESTIMABL 2 Trial in Thyroid Cancer (NCT01837745)

  • Trial Overview – ESTIMABL2 (NCT01837745):
    • Is a French, multicenter, phase III randomized trial investigating the necessity of post-thyroidectomy radioactive iodine (RAI) in patients with low-risk DTC:
      • Defined as intrathyroidal papillary carcinomas ≤ 1 cm (pT1a-m) or 1 to 2 cm (pT1b), with no suspicious lymph nodes on preoperative neck ultrasound (N0 / Nx)
    • All underwent total thyroidectomy (with or without prophylactic central neck dissection) and were randomized at 2 to 5 months post-op to:
      • RAI group:
        • 1.1 GBq (30 mCi) after rhTSH preparation
      • No‑RAI group:
        • Surveillance only 
    • Follow-up Protocol:
      • 3-year endpoint:
        • Thyroglobulin (Tg) and anti-Tg antibodies annually, neck ultrasound in alternating years
    • Event definition:
      • Need for further radioactive iodine or surgery:
        • Due to abnormal uptake, ultrasound changes, Tg rise, or antibody surge
      • Non-inferiority margin:
        • 5% difference in event-free survival 
    • Primary (3-Year) Results:
      • Evaluable patients:
        • 729 (FU: 367; RAI: 362)
        • Events:
          • 18 (4.9%) in surveillance vs 15 (4.1%) in RAI
        • Event-free survival:
          • 95.1% (no RAI) vs 95.9% (RAI)
          • Difference 0.8% (95% CI –3.3% to 1.8%) → non-inferiority confirmed 
    • Secondary interventions (surgery / RAI):
      • 6 (1.6%) vs 9 (2.5%)
  • 5-Year Long-Term Outcomes:
    • Evaluable at 5 years:
      • 698 patients
    • Event-free survival:
      • No RAI: 93.2%
      • RAI: 94.8%
        • Difference: 1.6% (90% CI –4.5 to 1.4%)
          • Remains within non-inferiority bounds 
  • Quality of response:
    • Surveillance group had higher rates of “excellent response” (83.3% vs 75.6%) and fewer indeterminate results 
  • Clinical Implications for Surgeons:
    • Omission of adjuvant RAI in strictly defined ATA low-risk patients (pT1, cN0, complete surgery, normal Tg and US) is safe and effective, even at 5 years
    • Non-inferiority margin of 5% comfortably met at both 3 and 5 years, a robust outcome
    • Superior biochemical and imaging outcomes in the surveillance arm suggest less overdiagnosis and overtreatment
    • Reduces patient burden:
      • Avoids radiation, isolation, and enhances convenience
    • Supports tailored management:
      • RAI can be reserved for cases with unfavorable histology, remnant tissue on US, or rising Tg / antibodies
  • Recommendations for Practice:
    • Strict selection is essential:
      • Only patients with pT1 N0 / Nx, complete surgery, and negative post-op US are eligible for RAI omission
    • Omit RAI in these low-risk patients, with follow-up consisting of Tg, TgAb, and periodic neck ultrasound
    • Reserve RAI for patients with adverse features:
      • Aggressive histology
      • Tg rise
      • Suspicious imaging
    • Discuss care pathway in MDT rounds, highlighting QoL gains and similar oncologic outcomes
    • Educate patients:
      • Provide clear rationale and plan for surveillance to avoid anxiety over omitted therapy
  • Final Takeaways:
    • The ESTIMABL2 trial delivers strong evidence that surveillance alone post-thyroidectomy is a safe, effective, and patient-centric strategy in carefully selected ATA low-risk DTC patient:
      • Offering similar long-term outcomes to standard RAI treatment, with additional QoL and diagnostic benefits

Hypercalcemia and Thiazide Diuretic Use

👉Elevated serum calcium levels have been associated with thiazide diuretic use and need to be differentiated from primary hyperparthyroidism – Dr. Rodrigo Arrangoiz

👉The overall annual age- and sex-adjusted (to 2000 U.S. whites) incidence of hypercalcemia due to thiazide diuretic use was 7.7 (95% CI, 5.9 to 9.5) per 100,000 individuals.

👉The average 24-hour plasma calcium concentrations are increased with thiazide diuretic use, but the mean 24-hour PTH levels remain unchanged in subjects with normal baseline PTH levels and no evidence of hypercalciuria.

👉Thiazides diuretics have several metabolic effects that may contribute to increased calcium levels:

  • A decrease in urine calcium excretion is the most likely cause.
  • In some cases of diuretic use metabolic alkalosis can occur that could cause an increase in total serum calcium levels through a pH-dependent increase in protein-bound calcium.
  • Although plasma 1,25 (OH) vitamin D levels are unchanged, increased intestinal calcium absorption in response to thiazide diurectic use has been noted and could also contribute to an increase in serum calcium.
  • One last possible explanation for the elevated serum calcium levels associated with thiazide diuretic use is hemoconcentration associated with diuresis.

👉CheckYourCalcium (realízate un calcio total en sangre).

#CheckYourCalcium #Arrangoiz #ParathyroidExpert #ParathyroidSurgeon #Hiperparatiroidism #Hipercalcemia #CheckYourCalcium #HeadandNeckSurgeon #MountSinaiMedicalCenter #MSMC #Miami #Mexico #Hyperparathyroidism

👉 Para obtener más información sobre el hiperparatiroidismo:

https://s3.amazonaws.com/academia.edu.documents/48239291/Current_Thinking_in_Hyperparathyroidism.pdf?response-content-disposition=attachment%3B%20filename%3DCurrent_Thinking_in_Hyperparathyroidism.pdf&X-Amz-Algorithm=AWS4-HMAC-SHA256&X-Amz-Credential=AKIAIWOWYYGZ2Y53UL3A%2F20190724%2Fus-east-1%2Fs3%2Faws4_request&X-Amz-Date=20190724T015127Z&X-Amz-Expires=3600&X-Amz-SignedHeaders=host&X-Amz-Signature=9633131723dc3e5fa1671838123524ae980c0bfb31e4a92be406b43a103bc355

ESTIMABL1 Trial Overview

  • Title:
    • Outcome after ablation in patients with low‑risk thyroid cancer (ESTIMABL1)
  • Design:
    • A multicenter, randomized, open-label, phase III equivalence trial:
      • Across 24 centers in France (2007 to 2010)
  • Population:
    • 752 adults with low-risk papillary or follicular differentiated thyroid cancer (DTC) post-total thyroidectomy
  • Randomization (1:1:1:1) into four groups:
    • RAI dose:
      • Low (1.1 GBq / ~30 mCi) vs High (3.7 GBq / ~100 mCi)
    • TSH stimulation:
      • rhTSH injections vs thyroid hormone withdrawal
  • Primary Endpoint:
    • Successful remnant ablation at 6 to 10 months:
      • Defined as stimulated thyroglobulin ≤ 1 ng/mL and no residual tissue on ultrasound
  • Initial and Long-Term Efficacy:
    • 6 to 10 Month Ablation Success:
      • ~ 92% across all groups:
        • With equivalence between:
          • Low and high dose
          • rhTSH vs withdrawal
    • 5.4-Year Median Follow-Up (n = 726):
      • 98% had no evidence of disease (715 / 726)
      • 11 patients had evidence of persistent or recurrent disease (structural or biochemical)
        • Recurrence was evenly distributed across RAI dose and stimulation method:
          • Indicating no impact of strategy on long-term outcomes
  • Prognostic Predictors:
    • Stimulated thyroglobulin at ablation:
      • Was predictive of eventual disease status and ablation success:
        • Patients with higher thyroglobulin were more likely to have persistent disease regardless of group
    • No lymph node stratification influence or stimulation method effect was observed
  • Clinical Implications:
    • Low-dose RAI (1.1 GBq) with rhTSH is validated as standard of care:
      • Equivalent efficacy with better patient experience
    • ATA 2015 guidelines endorse this strategy for low-risk DTC:
      • Simplified staging and reduced toxicity
    • No impact on long-term disease-free survival:
      • Supports tailored management based on disease biology rather than RAI intensity
  • Evidence Synthesis:
    • Meta-analysis of RCTs (> 1,500 patients, 4 to 10 years follow-up):
      • Confirms no difference in long-term recurrence between 1.1 GBq and 3.7 GBq (OR 0.93, 95% CI 0.53–1.63)
    • Similar equivalence was seen between rhTSH vs hormone withdrawal and across centers (France & UK)
    • HiLo trial results align, confirming comparable recurrence rates with low-dose RAI and rhTSH
  • Surgical Take-Home Points:
    • Remnant ablation using low-dose RAI + rhTSH is effective and minimizes side effects compared to high-dose or withdrawal strategies
    • Stimulated thyroglobulin at post-op ablation is a stronger predictor of recurrence than RAI dose or preparation method
    • No difference in long-term disease-free survival across dose or stimulation arms supports risk-adapted RAI use
    • Multidisciplinary protocols should adopt low-dose rhTSH-based ablation for ATA low-risk patients, reserving higher dose only for select cases (e.g., unresected tissue, aggressive pathology)
    • Surveillance strategies:
      • Regular ultrasound + Tg on levothyroxine; use stimulated Tg selectively for indeterminate findings

Parathyroid Awareness Month

👉Negative preoperative imaging does not exclude patients from surgery for hyperparathyroidism.

👉Experienced parathyroid surgeons have high cure rate (95%) with or without preoperative localization.

👉https://doi.org/10.1210/jc.2002-021095

#CheckYourCalcium #Arrangoiz #ParathyroidSurgeon #PararhyroidExpert MountSinaiMedicalCenter #MSMC #Miami #Mexico #HeadandNeckSurgeon #Hyperparathyroidism

Guidelines on the Use of Radioactive Iodine in Low-Risk Thyroid Cancer

  • American Thyroid Association (ATA) Low-Risk of Recurrence Overview:
    • Patients considered low-risk (pre- or post-operative):
      • Intrathyroidal papillary thyroid cancer ≤ 4 cm:
        • T1 to T2
      • No clinical nodal involvement:
        • N0 or minimal N1a
      • No distant metastasis (M0)
      • No aggressive histologic variants
      • No gross extrathyroidal extension
  • Core Randomized Trials:
    • ESTIMABL1 (2012, France):
      • Design:
        • 2 × 2 factorial randomized control trial (RCT):
          • Comparing low-dose (1.1 GBq) vs high-dose (3.7 GBq) radioactive iodine (RAI), and rhTSH stimulation vs thyroid hormone withdrawal for remnant ablation
      • Primary Outcome:
        • Remnant ablation success at 6 to 10 months:
          • ~92% to 95%
        • 5‑Year Follow-Up (2018):
          • 98% no evidence of disease
          • No differences between RAI dose or preparation method 
      • Clinical Meaning:
        • Low-dose RAI + rhTSH is as effective as high-dose with withdrawal
        • Lower toxicity, better patient convenience:
          • Incorporated in ATA 2015 guidelines (New Guidelines Coming Out Fall 2025)
    • HiLo (UK, Mallick et al., 2012):
      • Design:
        • Similar to ESTIMABL1:
          • Compared low- vs high-dose plus rhTSH vs withdrawal
      • Outcome:
        • Comparable ablation success and low recurrence rates 
    • ESTIMABL2 (France, 2022):
      • Design:
        • RCT of low-dose RAI (1.1 GBq) vs no RAI, post-total thyroidectomy in low-risk DTC
      • 3-Year Results:
        • Recurrence:
          • 2.7% (no RAI) vs 1.9% (RAI); non-inferior 
      • Commentary:
        • Non-inferiority holds even at lowest end of risk spectrum:
          • Upholds omission in select patients
    • IoN (“Iodine or Not”) Trial (UK, Lancet June 2025):
      • Design:
        • Phase II / III RCT randomizing 504 low-risk DTC patients to RAI vs no RAI
      • 5-Year Data:
        • 98% disease-free without RAI vs 96% with RAI
        • Omitting RAI improved quality of life and reduced isolation burden 
      • Significance:
        • Largest definitive trial confirming RAI omission is safe in ATA low-risk patients
    • Additional Evidence and Observational Data:
      • Long-term observational studies (> 8 years):
        • Show high remission and low recurrence with low-dose RAI 
      • Meta-analyses and reviews echo findings:
        • Low-dose or no RAI yields excellent oncologic outcomes in strictly low-risk DTC
  • Clinical Take‑Home Points for Surgeons:
    • Low-dose (1.1 GBq) RAI is sufficient for remnant ablation when RAI is used
    • rhTSH is preferred for patient comfort
    • RAI omission is safe in ATA low-risk cases:
      • Per ESTIMABL2 and IoN with:
        • ~ 98% disease-free survival at 5 years
      • QoL benefit and reduced isolation burden when RAI is not used:
        • Especially relevant for younger, family-centered patients
    • ATA 2015 guidelines:
      • Support selective RAI omission, reinforced by current trials
    • Surgical completeness matters:
      • Trials include total thyroidectomy with low /absent nodal burden
      • Partial thyroidectomy or residual disease was excluded
    • Follow-up protocol:
      • Stringent ultrasound and thyroglobulin monitoring essential when omitting RAI
  • Practical ATA-Based Approach:
    • Very Low / Low Risk ATA:
      • Intrathyroidal ≤ 4 cm
      • N0 to N1a
      • No vascular invasion:
        • Omit RAI:
          • Active surveillance with US + Tg (with / without rhTSH)
      • If ablation desired (e.g., Tg monitoring ease):
        • Use 1.1 GBq + rhTSH
    • Intermediate Risk:
      • Minimal extrathyroidal extension
      • > 5 involved nodes:
        • Consider selective RAI at low dose:
          • Decision individualized based on risk tolerance
  • Summary:
    • In ATA-defined low-risk DTC:
      • Low-dose RAI + rhTSH is as effective as high-dose or withdrawal methods
    • Importantly, omission of RAI does not compromise outcomes and offers QoL and cost benefits
    • Surveillance replaces ablation, with triggers reserved for structural or biochemical recurrence
#Arrangoiz #CancerSurgeon #ThyroidSurgeon
