Blog

Thyroid Cancer Pathology ATA 2025 Thyroid Cancer Guidelines Part 1

  • Throughout the American Thyroid Association (ATA) 2025 Thyroid Cancer Guidelines:
    • The 5th edition of the WHO Classification of Thyroid Tumors has been utilized for descriptions of the types of non-anaplastic follicular cell-derived thyroid carcinomas and NIFTP
  • Approximately 90% of thyroid cancer cases are well differentiated and are classified based on the predominant histomorphology:
    • However, they now also can be categorized based on their molecular profiles
  • Four main types of DTC include:
    • Follicular thyroid carcinoma (FTC)
    • Invasive encapsulated follicular variant of papillary thyroid carcinoma (IEFVPTC)
    • Papillary thyroid carcinoma (PTC)
    • Oncocytic thyroid carcinoma (OTC)
  • PTC is the most common type of DTC:
    • PTC is typically indolent and associated with excellent long-term survival:
      • 96% at 5 years
      • 93% at 10 years
      • Greater than 90% at 20 years
    • Overall, mortality rates for PTC are:
      • 1% to 6.5%
    • Overall recurrence rate of 15% to 35%:
      • Tumor recurrence typically occurs in the:
        • Tumor bed
        • Cervical lymph nodes
        • Distant sites (rarely)
    • PTCs have characteristic nuclear features:
      • Core elements fall into three buckets (per WHO 5th ed. framework and modern scoring systems):
        • Size / shape/ crowding:
          • Nuclear enlargement
          • Elongation / ovality
          • Overlapping / crowding
          • Pseudostratification at the papillary edges
            • These are low-power cues to look closer
        • Membrane irregularities:
          • Nuclear grooves (longitudinal folds)
          • Intranuclear cytoplasmic pseudoinclusions (INCIs):
            • Round, sharply circumscribed, eosinophilic inclusions:
              • Caused by cytoplasmic invagination
          • Irregular nuclear contours / notches
          • Notes for practice:
            • Grooves are sensitive but not specific
            • INCIs are more specific for PTC when true (focus and multiple planes help)
        • Chromatin changes:
          • Chromatin clearing with peripheral margination:
            • The classic “Orphan Annie-eye” look
          • Fine (“powdery”) chromatin with micronucleoli
          • Apparent thickened nuclear membrane on H&E
          • Clearing can be mimicked by Hashimoto thyroiditis or fixation artifact:
            • So it needs to be interpreted with the full nuclear constellation
      • How pathologists operationalize this:
        • In follicular-patterned lesions (e.g., NIFTP vs infiltrative FV-PTC), a 3-category nuclear score is applied:
          • Size / shape
          • Membrane irregularities
          • Chromatin features
        • A score ≥ 2 supports PTC-type nuclear features
        • NIFTP requires papillary-type nuclei (score ≥ 2) and strict architectura l/ invasion criteria
      • WHO 2022 emphasizes first deciding whether PTC-type nuclei are present before subtyping;
        • This step drives nomenclature:
          • Low-risk neoplasm vs malignancy
      • Molecular correlations you’ll see in reports:
        • BRAF V600E–driven tumors (classic / tall-cell subtypes):
          • Tend to show florid nuclear features:
            • Grooves (longitudinal folds)
            • INCIs
            • Glassy nuclei
        • RAS-mutated follicular-patterned tumors:
          • Often have subtler nuclei
      • Papillary thyroid carcinomas (PTC) can present as:
        • Infiltrative and encapsulated tumors
      • Molecular studies have shown that most PTCs (90%) develop by:
        • The activation of a Mitogen-Activated Protein Kinase (MAPK) pathway-event:
          • This activation occurs via mutually exclusive mutations in:
            •  BRAF or RAS oncogenes
        • A subset of PTCs is acquired by gene fusions involving:
          • Rearranged during transfection (RET) or (less commonly) other receptor tyrosine kinases
        • Oncogenic mutations at BRAFV600E:
          • Are the most common in PTC
        • A minority can show non-V600E mutations:
          • Such as BRAFK601E or BRAF fusions
        • The IEFVPTC is an encapsulated and invasive follicular-patterned tumor:
          • Based on its tendency for vascular invasion, distant metastasis, and molecular profile:
            • It can behave similarly to FTC
  • Histologically, FTCs are encapsulated follicular patterned tumors:
    • Without the nuclear features of PTC
    • They are characterized by the presence of:
      • Vascular:
        • Limited or extensive
      • Capsular invasion:
        • Vascular invasion involving vessels within the tumor capsule
      • Widely invasive:
        • Extensive invasion of the thyroid parenchyma beyond the tumor capsule
    • These tumors are mostly driven by activating mutations in:
      • RAS oncogenes (NRAS > HRAS > KRAS), PAX8::PPARγ fusions, EIF1AX mutations, PIK3CA mutations, or loss of PTEN expression:
        • BRAFV600E and RET fusions typically are not seen in FTC
      • Expression of PAX8::PPARγ fusions oncoprotein:
        • Occur in 25% of FTC:
          • In which the thyroid transcription factor PAX8 drives the expression of PPARγ:
            • A receptor involved in adipocyte biology
      • Mutations in DICER1:
        • Which encodes a ribonuclease in the processing of microRNA precursors:
          • Occur in RAS-like thyroid neoplasms and are prevalent in FTC
        • DICER1 mutations can also be seen in subsets of PTC, differentiated high-grade thyroid carcinoma (DHGTC), poorly differentiated thyroid carcinoma (PDTC), and anaplastic thyroid carcinoma (ATC)
  • With greater recognition of the unique genomic features of OTC (previously known as Hürthle cell carcinoma) and different clinical behavior from classical forms of FTC:
    • These tumors are now considered a third form of DTC:
      • Rather than a subtype of FTC in the current WHO classification:
        • They account for ∼ 3% of all DTC
    • An “oncocyte” is an enlarged polygonal cell with an abundant granular eosinophilic cytoplasm, round nuclei with even chromatin pattern, and prominent nucleoli:
      • As defined by WHO:
        • Oncocytic neoplasms are usually encapsulated and composed of ≥ 75% oncocytic cells
      • Oncocytic features can be identified in some PTC or FTC cells at lower frequencies
    • Most of these tumors are larger in size; however, smaller tumors can be identified
    • Like FTC, the presence of invasive characteristics:
      • Tumor capsule and / or vascular invasion:
        • In an encapsulated oncocytic neoplasm:
          • Is diagnostic of OTC
      • OTCs can be classified as:
        • Minimally invasive
        • Encapsulated angio-invasive
        • Widely invasive
    • Genomically, OTCs are characterized typically by:
      • A near-haploid genome
      • Mitochondrial DNA mutations:
        • Commonly involving genes encoding Complex 1 of the mitochondrial respiratory chain
      • Mutations in DAXX and ATRX:
        • Involved in telomere length
      • OTCs can also have mutations that activate:
        • Mammalian target of rapamycin (mTOR) and MAPK signaling
      • Like PTC and FTC:
        • More aggressive OTCs can have mutations in the:
          • TERTpromoter or TP53
      • Clinically, some studies have shown that OTCs have a greater tendency toward lymph node metastases while retaining a predilection for distant metastases, and unlike FTC:
        • OTCs often are not radioiodine-avid despite retaining other differentiated features:
          • Such as Tg secretion and TSH receptor expression
  • The 5th edition of the WHO Classification of Thyroid Tumors:
    • Also introduces a new category of high-grade follicular cell derived, non-anaplastic carcinoma that includes:

      • PDTC and DHGTC.
    • By molecular analysis, poorly differentiated thyroid cancer and DHGTC:
      • Harbor driver mutations in BRAF (BRAFV600E) and RAS genes:
        • In some cases may show gene fusions:
          • Often RET and NTRK3
      • Additional mutations in the:
        • TERT promoter, PIK3CA, and TP53 are commonly identified
    • DHGTC has been defined by certain authors as a:
      • “Thyroid malignancy” that is recognized as DTC but in which certain histological and cytopathologic features are present that justify the lesion being classified as “high-grade”
      • The DHGTCs are invasive, high-grade carcinomas:
        • That show one of the following two histological features:
          • Mitotic count ≥ 5 per 2 mm2
          • Tumor necrosis
    • By contrast, thyroid carcinomas classified as PDTC are follicular cell-derived tumors that show a minor component of DTC (papillary, follicular, oncocytic):
      • Show solid and / or insular growth pattern with presence of either:
        • Necrosis or ≥ mitotic count of 3 per 2 mm2, and lack the usual histological characteristics and aggressiveness of ATC
    • In both cases, clinical behavior is considered:
      • Intermediate between DTC and ATC

Induction TPF Followed by Concomitant Treatment versus Concomitant Treatment Alone in Locally Advanced Head and Neck Cancer: A Phase II–III Trial

  • Citation: Ghi MG et al. Induction TPF followed by concomitant treatment versus concomitant treatment alone in locally advanced head and neck cancer: a phase II–III trial. Annals of Oncology, 1 September 2017; 28(9): 2206–2212. DOI: 10.1093/annonc/mdx299
  • Key Findings:
    • Design:
      • A randomized phase II–III study comparing:
        Induction TPF (docetaxel, cisplatin, 5‑FU) followed by concomitant treatment (either chemoradiation [CCRT] or cetuximab/RT),
        versus concomitant treatment alone (CCRT or cetuximab/RT without induction)
    • Participants:
      • 414 patients analyzed (206 in the induction arm, 208 in the no‑induction arm)
    • Outcomes (median follow-up ~ 44.8 months):
      • Overall Survival (OS):
        • Significantly improved with induction:
          • Hazard Ratio (HR) 0.74; 95% CI, 0.56–0.97; P = 0.031
      • Progression-Free Survival (PFS):
        • Significantly better in the induction (IC) arm (P = 0.013)
      • Complete Response Rates:
        • Higher in the induction arm (P = 0.0028)
      • Locoregional Control:
        • Also significantly improved (P = 0.036)
      • Treatment Compliance:
        • Not adversely affected by induction therapy 
  • Summary for Head and Neck Surgeons
    • Publication:
      • This is an official, peer-reviewed publication, no longer merely an abstract
    • Significance:
      • It remains the only phase II–III trial reporting a statistically significant survival benefit (OS, PFS), better response rates, and improved locoregional control when adding TPF induction before chemoradiation, without harming treatment compliance
    • Clinical Interpretation:
      • These results strengthen the hypothesis that carefully administered TPF induction can offer meaningful benefit:
        • But they differ from the negative phase III findings of PARADIGM and DeCIDE
      • This raises important questions about variations in trial populations, concurrent treatments (cisplatin vs. cetuximab), and trial settings
    • Regulatory and Guideline Context:
      • While promising, broader adoption must weigh this one positive study against other evidence
      • Induction TPF remains non-standard but can be considered within multidisciplinary discussions:
        • Especially for patients with high-risk features or when organ preservation is a priority


Gruppo di Studio Tumori della Testa e del Collo (GSTTC) in Head and Neck Cancer

  • Background:
    • While major phase III trials in North America (PARADIGM, DeCIDE):
      • Failed to demonstrate a survival benefit for induction chemotherapy (IC) with docetaxel, cisplatin, 5-FU (TPF) before chemoradiation:
        • Italian investigators from the Gruppo di Studio Tumori della Testa e del Collo (GSTTC):
          • Reported the only positive phase III trial in this setting
  • GSTTC Trial Findings (abstract form):
    • Design:
      • Randomized phase III trial comparing TPF induction chemotherapy:
        • Follow by CRT vs CRT alone in patients with locally advanced HNSCC
    • Results (as reported in abstract form):
      • Improved progression-free survival (PFS) in the induction arm
      • Superior overall survival (OS) compared with CRT alone
      • Benefit appeared most pronounced in patients with:
        • High-risk, bulky, or unresectable disease
      • Publication status:
        • Results have only been presented in abstract form, not yet fully peer-reviewed or published, limiting their integration into international guidelines
  • Interpretation and Clinical Implications:
    • Consistency issue:
      • Unlike GSTTC, large U.S. trials (PARADIGM, DeCIDE) were negative:
        • Raising questions about patient selection, trial design, and population differences
    • Potential value:
      • The GSTTC data suggest that selected patients:
        • Those with high tumor burden or unfavorable disease biology may benefit from TPF induction before CRT
    • Guideline stance:
      • Induction chemotherapy with TPF is not standard of care but can be considered in high-risk or organ-preservation cases within multidisciplinary discussion
    • Take-home point:
      • GSTTC provides the only phase III evidence suggesting a survival advantage with induction:
        • But the lack of full peer-reviewed publication and discordant international trial results prevent broad adoption
  • Summary sentence for surgeons:
    • The GSTTC phase III trial remains the only study to report superior outcomes with TPF induction followed by CRT versus CRT alone, though its abstract-only publication and contrast with negative U.S. trials mean that CRT alone continues as the standard, with induction reserved for carefully selected high-risk patients

PARADIGM and DeCIDE Trials in Head and Neck Cancer

  • Background:
    • Both PARADIGM and DeCIDE were phase III randomized trials that evaluated the role of induction chemotherapy (IC) followed by chemoradiation versus chemoradiation alone:
      • In patients with locally advanced head and neck squamous cell carcinoma (HNSCC)
  • Trial Findings:
    • PARADIGM Trial (Haddad et al., 2013):
      • Compared IC (docetaxel, cisplatin, 5-FU) followed by CRT vs. CRT alone
      • No overall survival (OS) benefit was seen for the IC arm
      • The control arm (CRT alone) performed better than expected:
        • Narrowing potential differences
      • Trial closed early due to poor accrual (145 patients instead of 300+ planned)
    • DeCIDE Trial (Cohen et al., 2014):
      • Also tested induction chemotherapy followed by CRT vs. CRT alone in advanced HNSCC with high-risk features
      • It failed to show significant improvement in OS or progression-free survival (PFS)
      • Similar to PARADIGM, poor accrual and favorable outcomes in the control arm limited conclusions
  • Key Takeaways for Surgeons:
    • Negative Results:
      • Neither trial demonstrated a survival advantage for adding induction chemotherapy before CRT
    • Reasons for Negativity:
      • Poor accrual:
        • Underpowered to detect meaningful differences
      • Unexpectedly favorable outcomes in control arms:
        • CRT alone did better than historical benchmarks
    • Clinical Implication:
      • CRT alone remains the standard of care for most patients with locally advanced HNSCC:
        • IC is not routinely recommended outside of select cases:
          • Organ preservation
          • Laryngeal /hypopharyngeal cancers
          • Where rapid tumor shrinkage is needed
    • Ongoing Relevance:
      • These trials highlight the challenges of large cooperative studies in HNSCC and the importance of accrual in detecting real benefits
  • Summary Sentence:
    • The PARADIGM and DeCIDE trials did not demonstrate a survival benefit for induction chemotherapy in head and neck cancer:
      • Largely due to poor accrual and unexpectedly strong results in the control arms:
        • Confirming that CRT alone remains the standard of care for most patients

Induction Chemotherapy (IC) in Head and Neck Cancer

  • With the advent of taxanes in the 1990’s:
    • A series of phase I / II trials used paclitaxel or docetaxel for induction chemotherapy (IC) for head and neck cancer came out
  • While taxane and platinum doublets:
    • Have not shown outstanding results (Singh et al., 2022):
      • Adding docetaxel to cisplatin and 5-FU or cisplatin, 5-FU, and leucovorin:
        • Produced response rates exceeding 80% (Monnerat et al., 2002)
  • Later, several phase 3 trials:
    • Caused the three-drug combination TPF:
      • Docetaxel 75 mg/m2 IV on day 1, cisplatin 75 to 100 mg/m2 IV on day 1, and 5-fluorouracil 750 to 1000 mg/m2 IV on days 1 to 4 or 5:
        • To become the standard regimen for IC:
          • This included the cardinal TAX 323 / EORTC 24971 (Vermorken et al., 2007) and TAX 324 (Posner et al., 2007) trials:
            • Which demonstrated the superiority of TPF over PF in terms of:
              • Progression free survival (PFS)
              • Overall survival (OS)
              • Local control
              • Organ preservation
              • Quality of life
                • In resectable and unresectable head and neck cancers
  • The addition of taxanes to PF induction chemotherapy for patients with stage III or IV disease with no distant metastases:
    • Yields superior outcomes compared with PF alone
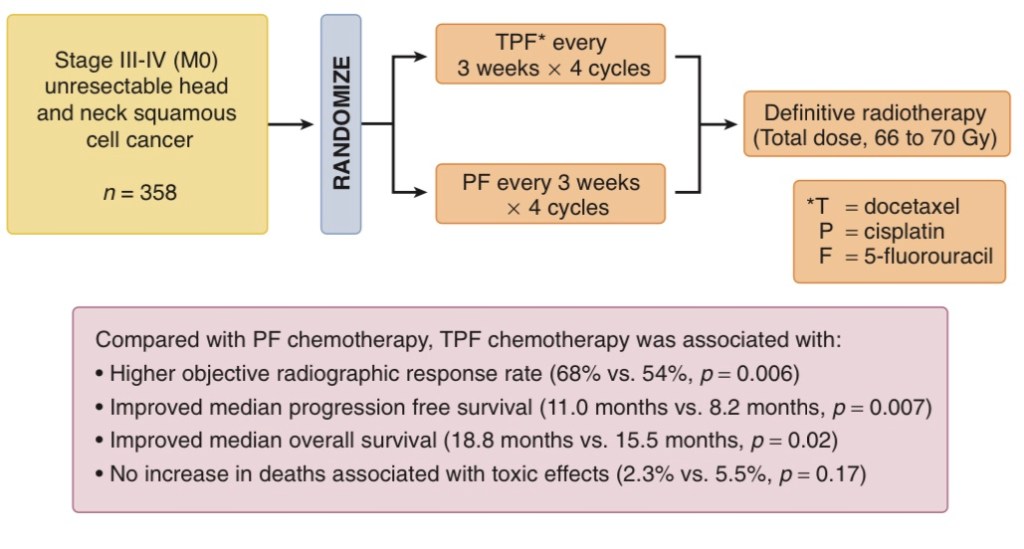
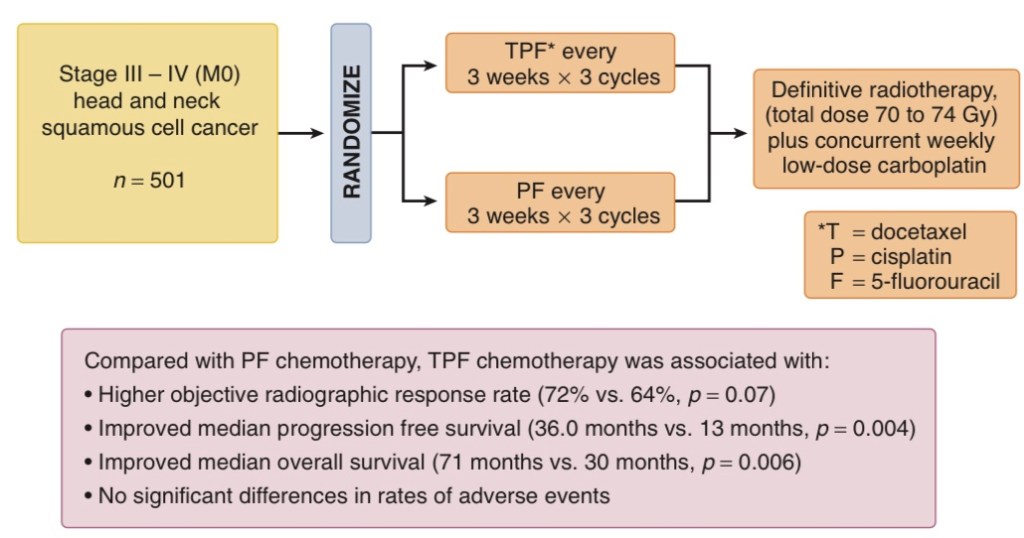
  • The TAX 323 and TAX 324 studies randomly assigned patients to:
    • Three cycles of PF versus three cycles of TPF
    • In both studies, the total dose per cycle of 5-FU was reduced in the TPF regimens compared with the PF regimens
    • TAX 323 / EORTC 24971:
      • Was restricted to patients with unresectable disease
      • Subtle differences in the dose and schedule of cisplatin and 5-FU existed in the TPF regimens in these two studies
      • After induction chemotherapy:
        • Patients received definitive radiation therapy alone in TAX 323 or with concurrent weekly carboplatin (area under the curve of 1.5) in TAX 324
  • Both studies demonstrated superior outcomes with TPF compared with PF
  • In TAX 323:
    • Overall response rates after induction chemotherapy:
      • 37% versus 26%:
        • Were significantly higher for patients treated with TPF versus PF
  • In TAX 324:
    • The overall response rates after induction chemotherapy:
      • 72% versus 64%, p = .07
    • 3-year overall survival were superior for the TPF group:
      • 62% versus 48%
  • These results are consistent with those of a randomized trial reported by Hitt and colleagues:
    • That evaluated the addition of paclitaxel to cisplatin and 5-FU in patients with stage III or IV disease without distant metastasis:
      • The addition of paclitaxel yielded a significant improvement in response rate to induction chemotherapy and a trend toward improvement in overall survival
  • These trials, however, were not designed to compare the strategy of induction chemotherapy followed by chemoradiation versus primary chemoradiation
  • Several phase III randomized clinical trials that followed failed to demonstrate a significant efficacy advantage with this sequential approach
    • (Cohen et al., 2014; Haddad et al., 2013; Hitt et al., 2014)
  • The negative results in the PARADIGM and DeCIDE trials:
    • Have been attributed to poor accrual and unexpected favorable outcomes in the control arms (Cohen et al., 2014; Haddad et al., 2013), and the Spanish Head and Neck Cancer Cooperative Group (TTCC) study has only been reported with relatively short follow-up (Hitt et al., 2014)
  • The only positive phase III clinical trial demonstrating superior outcomes with TPF induction followed by chemoradiation over chemoradiation alone:
    • Was reported in abstract form by Italian investigators from Gruppo di Studio Tumori della Testa e del Collo (GSTTC)
  • Taken together, these results suggest that more investigation is required to better elucidate the benefit of induction chemotherapy, and perhaps more importantly better defining the patient population who benefits from the sequential approach
  • In Tax 323 TPF was used with a reduced dose form:
Design and results of the TAX 324 induction chemotherapy trial. (Adapted from Posner M, Hershock DM, Blajman CR, et al: Cisplatin and fluorouracil alone or with docetaxel in head and neck cancer. New Engl J Med 2007;357:1705–1715.)
  • Nevertheless, the details of TAX trials showed that toxicities were high in both regimens:
    • For instance, at least 70% of subjects on TPF and about half of PF patients experienced grade 3 and 4 neutropenia in both trials
  • While subjects in TAX 323 received a sequential schedule, that was IC followed by RT rather than CCRT:
    • In Tax 324 patients proceeded with carboplatin with RT
  • A critical commentary:
    • Emphasized on the percentage of patients who were ultimately treated off-protocol in the TPF, and PF arms:
      • Which were 21%, and 24% respectively:
        • It is assumed that this observation likely reflects greater response rates of taxane-based regimens, rather than the more favorable tolerance of the TPF treatment (Haddad and Posner, 2009)
        • Supposedly, some of these subjects of both trials who were not treated with concurrent chemotherapy may have been disadvantaged in receiving alternative treatments
        • Also, almost half of the patients in these trials were diagnosed with oropharyngeal cancer which is believed to have a more favorable prognosis, so the results of these trials might not be generalizable (Tural and Kilickap, 2013)
  • The update of MACH-NC with the inclusion of taxane trials:
    • Showed that the addition of taxane to PF caused:
      • A 7.4% rise of OS in favor of TPF
    • This showed great promise, however, remarkably, only half of the patients on TPF went through concomitant chemotherapy as planned and about a third did not start RT in the TPF arm
    • Additionally, TPF induction was not compared to CCRT in this study (Blanchard et al., 2013)
  • In the most recent 2021 update on MACH-NC with a follow-up of 9.2 years:
    • The superiority of CCRT alone over the addition of IC was once again confirmed:
      • The OS benefit of 0.83 [0.79;0.86] with an absolute benefit of 6.5% and 3.6% at 5 and 10 years, respectively:
        • However, it failed to prove any survival benefit for TPF induction compared to CCRT alone:
          • These data are inconsistent with those reported for PF, which had shown superior survival when compared to CCRT (Lacas et al., 2021)
  • A secondary finding of the MACH-NC report was rates of locoregional and distant failures per treatment type (Pignon et al., 2009):
    • The hazard ratio for death was 0.81 [0.78;0.86] by CCRT and 0.96 for the addition of IC but with an insignificant confidence interval ranging from 0.9 to 1.02
    • Their indirect comparison revealed an improvement in both local (HR, 0.74; 95% CI, 0.70–0.79; P = 0.001), and distant failure, (HR, 0.88; 95% CI, 0.77–1.00; P = 0.04):
      • In the CRT group, whereas, IC did not affect locoregional control but particularly reduced metastases (HR, 0.73; 95% CI, 0.61–0.88; P = 0.001):
        • The impact on reduced tumor dissemination did not cause survival benefit by IC regimens but instead, a higher local control seems to be causative for the significant survival benefit with CCRT alone compared to the addition of IC
#Arrangoiz #HeadandNeckSurgeon #CancerSurgeon #SurgicalOncologist #MountSinaiMedicalCenter #MSCM #Miami #Mexico #HeadandNeckCancer

Cisplatin and Fluorouracil Alone or with Docetaxel in Head and Neck Cancer

TAX 324 Trial

  • A randomized phase three trial of the treatment of squamous-cell carcinoma of the head and neck:
    • Compared induction chemotherapy with docetaxel plus cisplatin and fluorouracil (TPF) with cisplatin and fluorouracil (PF):
      • Followed by chemoradiotherapy
  • Squamous-cell carcinoma of the head and neck:
    • Accounts for 5% of newly diagnosed cancers in adults in the United States and 8% of cancers worldwide
    • The disease is potentially curable at an early stage, but most patients present with locally advanced disease
  • After standard therapy (surgery and radiation):
    • Only 30% to 50% of patients with locally advanced disease:
      • Live for three years
    • Locoregional recurrences or distant metastases develop in 40% to 60% of them
  • Various strategies to improve outcomes by coordinating chemotherapy with surgery and radiotherapy have been tried:
    • But the optimal schedule for integrating chemotherapy into the management of this disease has yet to be defined
  • Although chemoradiotherapy (radiotherapy plus concurrent chemotherapy) has become the standard of care for patients with unresectable squamous-cell carcinoma of the head and neck and for organ preservation:
    • Induction chemotherapy with cisplatin and fluorouracil (PF) also has benefits in this disease
  • A comprehensive meta-analysis showed that induction chemotherapy (i.e., chemotherapy as the initial treatment) with PF:
    • Significantly improved the rate of survival at 5 years:
      • As compared with standard radiotherapy plus surgery in patients with locally advanced disease
  • Docetaxel (Taxotere, Sanofi-Aventis) has substantial activity when administered alone in patients with recurrent or incurable disease
  • In phase 1 and phase 2 studies of docetaxel plus cisplatin and fluorouracil (TPF) in the treatment of locally advanced squamous-cell carcinoma of the head and neck, including phase 2 studies of treatment with curative intent:
    • Clinical and pathological response rates have been high and survival has been prolonged
  • Two phase 3 trials in which induction chemotherapy with TPF or PF was followed by radiotherapy (the European Organization for Research and Treatment of Cancer [EORTC] 24971 / TAX 323 study by Vermorken et al.) or chemoradiotherapy (TAX 324) in locally advanced disease have now been completed
  • Results of the TAX 324 study here
  • METHODS:
    • They randomly assigned 501 patients (all of whom had stage III or IV disease with no distant metastases and tumors considered to be unresectable or were candidates for organ preservation):
      • To receive either TPF or PF induction chemotherapy:
        • Followed by chemoradiotherapy with weekly carboplatin therapy and radiotherapy for 5 days per week
    • The primary end point was overall survival
  • RESULTS:
    • With a minimum of 2 years of follow-up (≥ 3 years for 69% of patients):
      • Significantly more patients survived in the TPF group than in the PF group:
        • Hazard ratio for death, 0.70; P=0.006)
      • Estimates of overall survival at 3 years were 62% in the TPF group and 48% in the PF group:
        • The median overall survival was 71 months and 30 months, respectively (P=0.006)
      • There was better locoregional control in the TPF group than in the PF group (P=0.04):
        • But the incidence of distant metastases in the two groups did not differ significantly (P=0.14)
      • Rates of neutropenia and febrile neutropenia were higher in the TPF group
      • Chemotherapy was more frequently delayed because of hematologic adverse events in the PF group
  • CONCLUSIONS:
    • Patients with squamous-cell carcinoma of the head and neck who received docetaxel plus cisplatin and fluorouracil induction chemotherapy plus chemoradiotherapy had a significantly longer survival than did patients who received cisplatin and fluorouracil induction chemotherapy plus chemoradiotherapy
    • ClinicalTrials.gov number, NCT00273546. opens in new tab

Introduction of the American Thyroid Association 2025 Thyroid Cancer Guidelines

  • Clinical Management Principles:
    • Dictionary and Definitions:
      • Several terms are utilized throughout the guidelines in different sections and recommendations
  • Important definitions used by the committee are included below:
    • General definitions:
      • Active surveillance:
        • The ongoing observation or active monitoring of a known or suspected primary, intrathyroidal, low-risk DTC with serial imaging as an alternative to upfront surgical intervention
        • This is a type of expectant management and is only appropriate for a subset of low-risk DTCs (see Recommendation 11)
        • This does not pertain to persistent or recurrent thyroid cancer, in which case the term “monitoring” is employed (see below)
        • Some proportion of patients who undergo active surveillance may be recommended to pursue thyroid surgery if there is concern for disease progression or based on patient preference
      • Disease monitoring:
        • Monitoring for biochemical (elevated level of serum Tg) and / or structural persistence or recurrence of disease (as confirmed by imaging and / or biopsy) following the diagnosis and initial treatment (surgery – RAI) of thyroid cancer
        • It is deployed to evaluate patients for disease progression and inform the type and timing of interventions deemed appropriate
      • Response to therapy:
      • Response assessment is performed after intervention:
        • Either for initial or clinically persistent / recurrent disease (see Recommendation 29 and Table 9 of the ATA 2025 Guidelines)
      • Excellent response:
        • No biochemical or structural evidence of persistent thyroid cancer (i.e., remission)
      • Indeterminate response:
        • The presence of nonspecific findings on imaging; mildly elevated serum Tg levels; or positive, but stable or declining, anti-Tg antibody (TgAb) levels in persons who have undergone total thyroidectomy with or without RAI
        • Most patients in this category prove to have a “good” clinical response to therapy, especially if they have a low risk of clinical recurrence, and findings are nonspecific
        • However, those at intermediate or high risk of clinical recurrence based on histopathologic and staging characteristics in this category:
          • May have higher rates of recurrence
      • Biochemically incomplete response:
        • Elevated serum Tg concentrations or rising TgAb levels without radiological evidence of structural recurrence in persons who have undergone total thyroidectomy with or without RAI
      • Structurally incomplete response:
        • Structural evidence of disease recurrence (by imaging or biopsy), usually in conjunction with elevated Tg and / or TgAb levels
      • Persistent or recurrent disease:
        • See Recommendation 29 and Table 9 of the ATA 2025 Guidelines
      • Clinically persistent disease:
        • Biochemical or structural evidence of disease within 90 days of initial therapy (or intervention for persistent disease)
      • Clinically recurrent disease:
        • Biochemical or structural disease subsequently identified in patients previously deemed to have an excellent response following therapy
        • Clinically recurrent disease likely represents progression of residual disease that is below the lower limits of detection
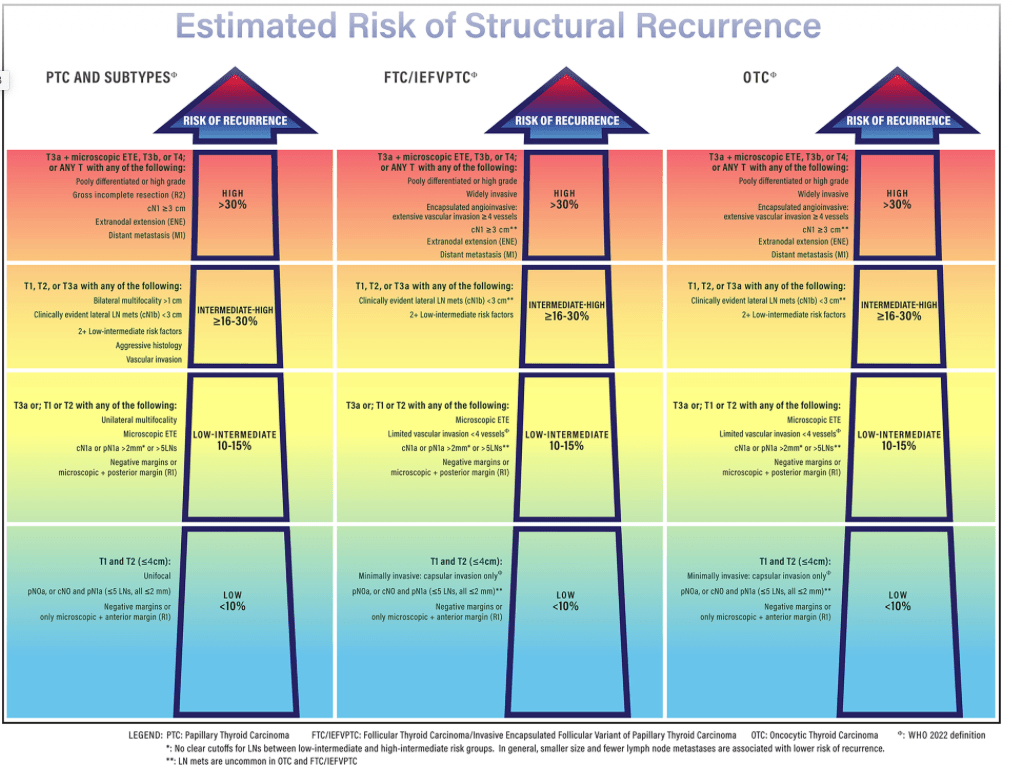
      • Risk of recurrence:
        • They use the term “recurrence” to mean clinical recurrence, recognizing that most recurrences reflect growth of residual disease to clinically detectable levels (Figure )
        • An overall assessment of risk of biochemical or structural recurrence determined by incorporating a combination of factors:
          • Histopathologic characteristics of the resected tumor, American Joint Committee on Cancer (AJCC) staging, imaging, molecular analysis of tumor, and response to therapy at subsequent evaluation
        • For the purpose of these guidelines, categories are designated as:
          • Low (< 10%) risk of recurrence
          • Low Intermediate (10% to 15%) risk of recurrence
          • Intermediate-high (≥ 16% to 30%) risk of recurrence
          • High (> 30%) risk of recurrence
ATA 2025 Risk of Recurrence for PTC, FTC, and OTC. *Lymph metastases are uncommon in OTC and FTC/IEFVPTC. FTC, follicular thyroid carcinoma; IEFVPTC, invasive encapsulated follicular variant of papillary thyroid carcinoma; OTC, oncocytic thyroid carcinoma; PTC, papillary thyroid carcinoma.
  • Treatment Definitions:
    • Extent of surgery definitions (ATA website definitions):
      • Total thyroidectomy: 
        • Surgical removal of the entire thyroid gland
      • Near-total thyroidectomy:
        • Intended extent of resection for thyroid cancer is total thyroidectomy:
          • But a small remnant may be left for a specific reason (usually confidence in nerve preservation)
      • Lobectomy or hemithyroidectomy with or without isthmusectomy: 
        • Surgical removal of one lobe (half) of the thyroid with or without the isthmus
      • Subtotal thyroidectomy: 
        • Surgical removal of almost all of the thyroid gland, leaving 3 to 5 g of thyroid tissue with the intent of maintaining adequate thyroid hormone production:
          • This operation is not recommended if the diagnosis of thyroid cancer is known preoperatively
        • Completion thyroidectomy: 
          • Surgical removal of the remnant thyroid tissue following procedures of less than total or near-total thyroidectomy
    • Extent of lymphadenectomy definitions:
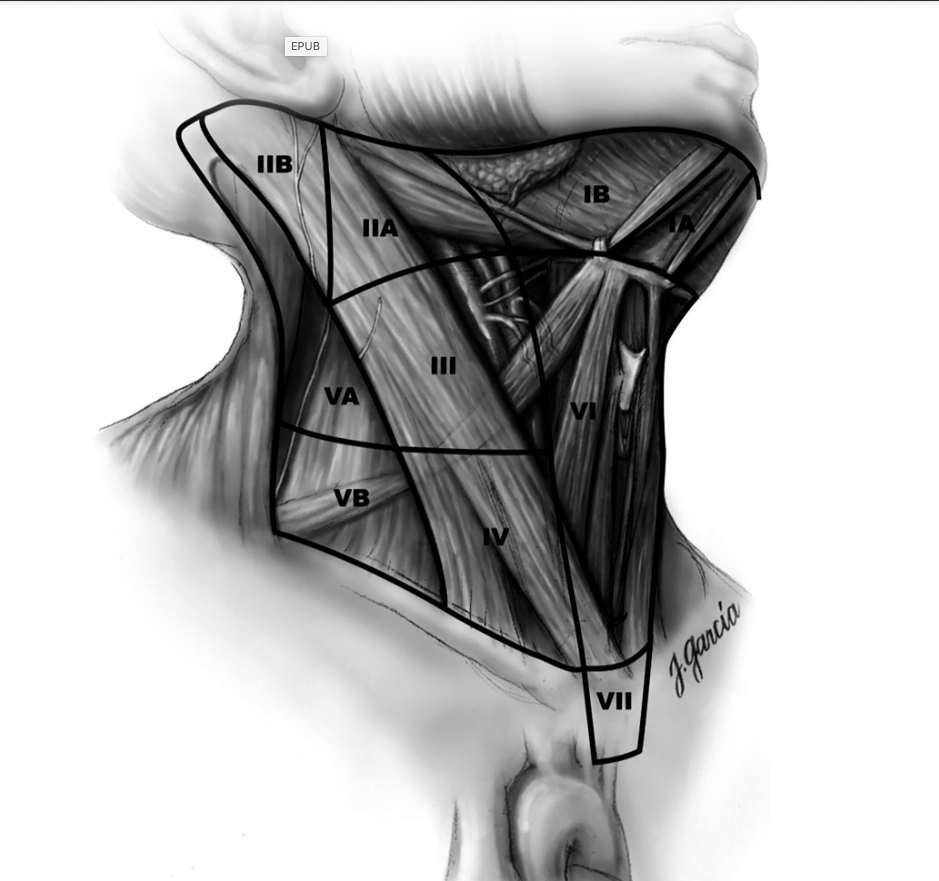
      • Central neck dissection:
        • Central neck lymph nodes include Levels VI and VII (Figure)
        • Central neck dissection is a comprehensive removal of pretracheal and prelaryngeal lymph nodes, along with at least one paratracheal nodal basin
        • It can be unilateral or bilateral; the laterality and extent of dissection should be documented at the time of operation in addition to surgical intent (therapeutic vs. prophylactic)
      • Therapeutic neck dissection:
        • It implies that metastatic nodal disease is apparent clinically preoperatively or intraoperatively by examination and / or imaging, cN1a
      • Prophylactic neck dissection:
        • It implies that no metastatic nodes are detected by examination or imaging preoperatively or intraoperatively, cN0
      • Lateral neck dissection:
        • Full compartment dissection of the lateral cervical neck lymph nodes in Levels IIA, III, IV, and VB ipsilateral to the tumor and performed for clinical evidence of metastatic involvement
        • Dissection of Levels I, IIB, and VA are not regularly performed but can be considered based on findings suggestive of metastatic disease in these compartments (Figure)
      • Completeness of surgical resection:
        • The goal of surgery is to remove safely as much thyroid cancer as possible
        • To define the completeness of resection, the AJCC created definitions that are used in these guidelines to facilitate communications
        • An R0 resection:
          • Means that the surgical margin is microscopically negative for residual tumor
        • An R1 resection:
          • Means that there is no residual macroscopic tumor but that microscopically positive margins still demonstrate the presence of tumor
        • An R2 resection:
          • Means that gross (macroscopic) disease remains post-surgery
Nodal levels with corresponding anatomical landmarks.
  • 131I, RAI administration definitions:
    • Remnant ablation:
      • RAI administration to destroy benign remnant thyroid tissue following total or near-total thyroidectomy
    • Adjuvant therapy:
      • RAI administration to destroy suspected (but not identified) remaining thyroid cancer following total or near-total thyroidectomy
    • Therapeutic treatment:
      • RAI administration to treat known residual or recurrent thyroid cancer, either initially or with subsequent progression of thyroid cancer after total or near-total thyroidectomy
    • Thyrotropin suppression therapy:
      • Use of thyroid hormone to suppress serum thyrotropin (TSH) concentrations below the normal range based on the risk of recurrence and / or response to therapy

ATA 2025 Thyroid Cancer Guidelines Recommendation # 7

  • Recommendation #7 from ATA 2025 Guidelines:
    • Preoperative neck ultrasound to evaluate cervical lymph nodes in the central and lateral neck compartments as well as for gross extrathyroidal extension is recommended for all patients undergoing surgery for malignant cytologic or molecular findings:
      • Strong recommendation, Moderate certainty evidence
    • Ultrasound-guided FNA of sonographically suspicious lymph nodes greater than 8 to 10 mm in the smallest diameter should be performed to confirm malignancy if this would change management:
      • Strong recommendation, Moderate certainty evidence
    • The addition of FNA-Tg washout in the evaluation of suspicious cervical lymph nodes may be performed in select preoperative patients, but interpretation may be dif cult in patients with an intact thyroid gland:
      • Conditional recommendation, Low
        certainty evidence
  • Differentiated thyroid cancer (DTC), and particularly PTC:
    • Involves cervical lymph nodes in 20% to 50% of patients in most series using standard
      pathological techniques:
      • These metastases may be present even when the primary tumor is small and intrathyroidal
    • The frequency of micrometastases (less than 2 mm) may approach 90%, depending on the sensitivity of the detection method:
      • However, the clinical implications
        of micrometastases are likely less significant compared with macrometastases:
        • They do not appear to affect survival when they are in the central neck
        • They also do not appear to increase recurrence
  • Preoperative ultrasound identifies suspicious cervical adenopathy in:
    • 20% to 31% of cases:
      • Potentially altering the surgical approach:
        • In as many as 20% of patients
    • It has significantly less clinical utility in identifying central neck lymph nodes:
      • Due to the presence of the overlying thyroid gland
  • Sonographic features suggestive of abnormal metastatic lymph nodes include:
    • Enlargement
    • Loss of the fatty hilum (odds ratio [OR] 1.9)
    • A rounded rather than oval shape:
      • Long axis / short axis ≤ 2; OR 1.6
    • Hyperechogenicity (OR 5.4)
    • Cystic change (OR 71.8)
    • Calcifications (OR 6.2)
    • Peripheral vascularity or abnormal blood flow (OR 3.8)
  • No single sonographic feature has adequate sensitivity for detecting lymph nodes with metastatic thyroid cancer; however:
    • Cystic change:
      • Has the highest odds of malignancy
    • Absence of a fatty hilum, cystic changes, microcalcifications, abnormal vascularity, and cortical hyperechogenicity are all independent features of metastatic lymph nodes:
      • With a high specificity of 87% to 99.6%
    • Absence of a fatty hilum has the highest sensi-
      tivity but low specificity at 66.4%
  • The location of the lymph nodes also may be useful for decision-making:
    • Metastatic lymph nodes are much more likely to occur in Levels III, IV, and VI than in Level II:
      • Although this may not be true for PTC tumors arising in the upper pole of the thyroid:
        • Which have a higher propensity to produce skip metastases to Levels II and III
  • Confirmation of malignancy in lymph nodes
    with a suspicious sonographic appearance:
    • Is achieved by ultrasound-guided FNA aspiration for cytology and / or measurement of Tg in the needle washout (FNA-Tg):
      • Tg washout is a helpful adjunct to FNA:
        • Particularly in cases where the lymph nodes are cystic, cytological evaluation of the lymph node is inadequate, or the cytological and sonographic evaluations disagree:
          • Example – normal cytological biopsy of a large lymph node with microcalcifications
      • False positive Tg washout may occur:
        • Particularly in lymph nodes in the central compartment when the thyroid gland is still present
          • But it remains valid in the presence of positive serum TgAb
        • Recommendation 31 reviews the role of
          FNA-Tg washout in lymph nodes in the postoperative setting
      • Data are limited to support a definitive FNA-Tg threshold for diagnosis of a metastatic lymph node
      • A systematic review and meta-analysis showed that FNA cytology with FNA-Tg washout has a negative predictive value (NPV) of 99.4% and accuracy of 86.8% in the evaluation of pathological-appearing lymph nodes:
        • If the FNA-Tg level is 1.0 ng/mL or lower, then the NPV approximates 100%
        • However, non-metastatic lymph nodes can have concentrations as high as 32 ng/mL
        • Accuracy, specificity, positive predictive value (PPV), and NPV are significantly higher if the FNA-Tg threshold is 28.5 ng/mL
      • Another systematic review analyzed 22 studies with 2,670 suspicious lymph nodes during thyroid nodule workup or PTC follow-up:
        • Found that the highest sensitivity was observed with a FNA-Tg cut-off of 1 ng/mL and the highest specificity was observed with a cutoff of 40 ng/mL:
          • In this study, other factors that influenced the accuracy of FNA-Tg included TSH suppression, presence of serum Tg, and methodologic differences in Tg measurement
      • Another study found the presence of serum TgAb interferes with circulating serum Tg
        measurement:
        • But does not appear to interfere with FNA-Tg measurements
      • Further studies are needed to determine an optimal FNA-Tg threshold to diagnose metastatic lymph nodes
  • In addition to assessing for pathological lymph nodes:
    • Ultrasound evaluation of the thyroid gland to gauge gross extrathyroidal extension is important for surgical planning:
      • As this typically demonstrates indication for RAI and therefore total thyroidectomy
  • If there is evidence of more advanced locoregional disease:
    • Additional imaging with computed tomography (CT) may be useful
    • While ultrasound is more specific for nodal disease:
      • CT is more sensitive:
        • The combination of both may increase diagnostic accuracy
      • In view of the higher cost of CT compared with ultrasound, the associated radiation exposure, and potent risks of intravenous contrast administration in specific populations:
        • It is important to determine the imaging needs on an individual patient basis
      • Accurate staging is important for determining the prognosis and tailoring treatment for patients with DTC:
        • However, unlike many tumor types, the presence of metastatic disease does not obviate the need for thyroidectomy:
          • Because distant metastatic disease may respond to RAI therapy, removal
            of the thyroid as well as the primary tumor and accessible loco-regional disease is an important component of initial treatment for most patients with distant metastatic disease

Thyroid Surgery Volumen and Outcomes

images-1

  • Introduction: Although the association between annual surgeon total thyroidectomy volume and clinical outcomes is well established, published methods typically group surgeons into volume categories. The volume-outcomes association is likely continuous, but little is known about the point at which the annual surgeon procedure volumes begin to be associated with a decrease in complication rates.
  • Multiple studies have demonstrated the relationship between surgeon volume and improved patient outcomes.

  • This is no different for thyroid surgery; when procedures are performed by high-volume surgeons, patients have decreased rates of endocrine-specific complications (e.g., transient and permanent hypoparathyroidism and recurrent laryngeal-nerve injury), shorter hospital stays, and lower rates of readmission.

  • Previous studies have varied with respect to the definition of a high-volume surgeon, ranging from a threshold of 30 to 100 thyroidectomies per year:

    • One recent study demonstrated that the likelihood of experiencing a complication decreased with increased surgeon volume, up to 26 total thyroidectomies per year.


  • The intent of the current study was to examine the association between surgeon volume and patient outcomes for total thyroidectomy, with the hypothesis that the optimal threshold is continuous, with no defined cut point defining a high-volume surgeon.

Presentation1

2019 Jul 25. doi: 10.1001/jamaoto.2019.1752


¿Quién debe realizar cirugía de tiroides?

  • Generalmente debe ser cirujanos con sub-especialidades que tiene un volumen alto de casos por año:
    • No es ideal un cirujano general que realizar muy pocos casos al año
  • Estas sub-especialidades son:
    • Cirugia oncológica
    • Cirugia de cabeza y cuello
    • Cirugia endocrina
  • Les dejo la respuesta de Ashok R. Shaha, MD, FACS (profesor MSKCC / IFHNOS) en su presentación que dio en el Keynote Lectura del American Head and Neck Society:

prof_739_20190417135234

  • Rodrigo Arrangoiz MS, MD, FACS, FSSO miembro de Mount Sinai Medical Center cumple con los requisitos señalados por el Dr. Shaha:
    • El Dr. Arrangoiz tiene entrenamiento en: Cirugía de tumores de cabeza y cuello, cirugía endocrina, y cirugía oncológica.
  •  Su entrenamiento es el siguiente:

    • Tumores de Cabeza y Cuello / Cirugía Endocrina: Fox Chase Cancer Center

image-49

  • Tumores de Cabeza y Cuello / Cirugía Endocrina:IFHNOS / Memorial Sloan Kettering Cancer Center


Cirugía Oncológica Compleja: Fox Chase Cancer Center

image-39


  • Cirugia General y Gastrointestinal:
    • Michigan State University

images

  • Maestría en Ciencias de Investigación:Drexel University

image-40

  • El Dr. Arrangoiz esta certificado por:El Colegio Americano de Cirugía

Unknown

  • El Dr. Arrangoiz es: Fellow del Colegio Americano de Cirugía


El Dr. Arrangoiz es:

Fellow de la Sociedad de Cirugia Oncológica:

Unknown

  • Es miembro de la American Thyroid Association

Unknown

rodrigo.arrangoiz@gmail.com

Introduction of the American Thyroid Association 2025 Thyroid Cancer Guidelines

  • Differentiated thyroid cancer (DTC) includes papillary, follicular, and oncocytic carcinomas:
    • Comprising the vast majority (> 90%) of all thyroid cancers
  • In the United States:
    • It is estimated that there were 44,020 new cases of thyroid cancer in 2024:
      • Compared with 37,200 in 2015 when the last American Thyroid Association (ATA) guidelines were published
  • The yearly incidence tripled from 4.9 per 100,000 in 1975 to:
    • 14.3 per 100,000 in 2015
  • Approximately 25% of the new thyroid cancers diagnosed in 1988 to 1989 were < 1 cm:
    • Compared with 39% of the new thyroid cancer diagnoses in 2008 to 2009:
      • This shift to earlier detection / diagnosis correlates with the increasing use of neck ultrasonography and other imaging along with the advent of ultrasound-guided fine needle aspiration (FNA)
  • The incidence of thyroid cancer, and particularly small thyroid cancers:
    • Has reduced in the United States since 2014:
      • This change in incidence trajectory is likely a reflection of the adoption of guidelines’ recommendations from the ATA and other organizations discouraging FNA of small nodules < 1 cm in the absence of abnormal lymph nodes or local invasion:
        • Due to the overall outstanding prognosis associated with these tumors and weighed against the potential risks of unnecessary treatment
  • In addition to changes in the management of early-stage thyroid cancer:
    • Prior guidelines introduced criteria to enhance initial decision-making and a response framework following interventions to facilitate further management decisions:
      • These have been validated since the prior guidelines, enabling adoption in clinical practice
  • There have been major advances in understanding the molecular causes of thyroid cancer development and progression that have created newly approved treatment options for subsets of patients:
    • Published data in these and other areas require serial updates of existing guidelines to facilitate clinical care
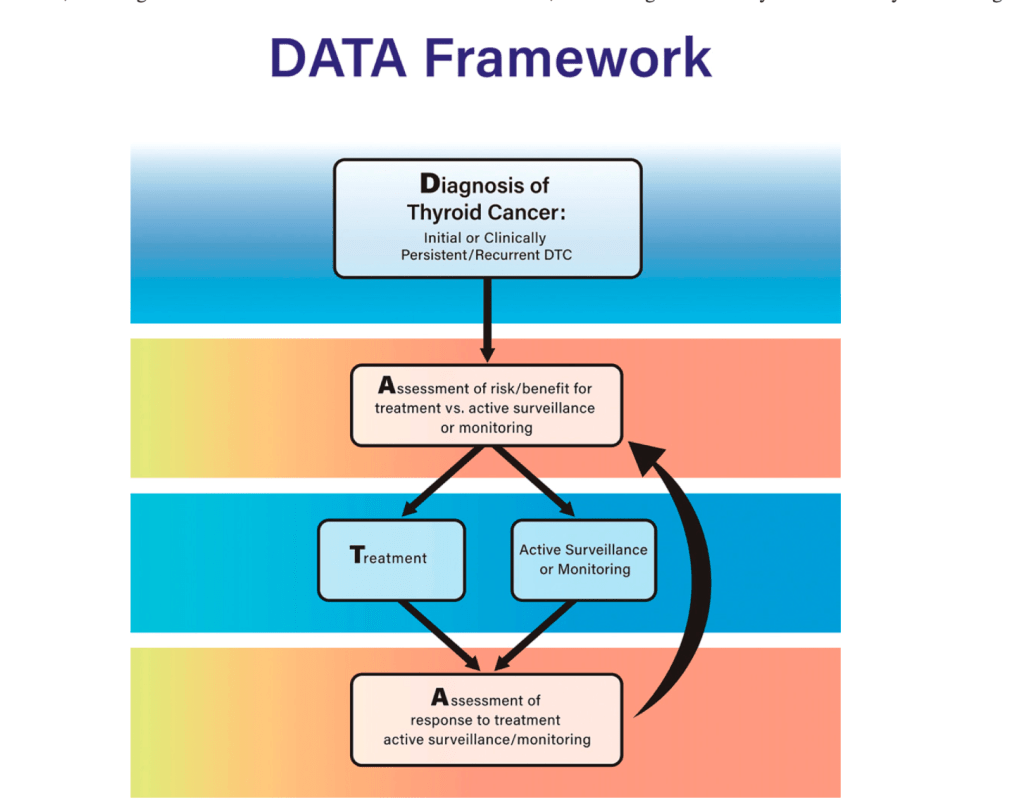
  • In the current guidelines, an approach to clinical decision-making is introduced based upon the individual patient and clinician journey with thyroid cancer:
    • Which they term DATA:
      • Diagnosis
      • Risk / benefit Assessment
      • Treatment decisions
      • Response Assessment
  • This approach begins at the initial diagnosis of thyroid cancer, the diagnosis of residual disease or a clinical recurrence:
    • It includes assessment to determine whether a particular intervention is appropriate based on risks and benefits as well as individual patient factors:
      • When multiple possible management strategies are available, the framework supports identification of the best treatment option
  • Then, after intervention, an assessment of response using the 2025 ATA risk assessment tool is deployed to determine whether more treatment or monitoring is appropriate
  • The clinician and the patient can use this DATA framework to help make clinical decisions from diagnosis through the patient’s entire disease course.
Overall DATA framework for clinical management.
  • In 1996, the ATA published treatment guidelines for patients with thyroid nodules and DTC:
    • Over the last 25 to 30 years, there have been remarkable advances in knowledge affecting the diagnosis and treatment of DTC, but clinical controversy continues to exist in many areas
    • In the end, the goal is to provide individualized therapy for each patient based on the best application of clinical data to their unique case:
      • For example, a less aggressive approach would be recommended for individuals with early stage DTC who have an excellent prognosis or for individuals at higher risk of side effects, while a more aggressive approach would be recommended for those patients with higher risk disease or those with inadequate response to initial therapy
Rodrigo Arrangoiz, MD (Oncology Surgeon)