Blog

Support for Omitting SLNB in Some Early Breast Cancers

  • Sentinel Lymph Node Biopsy Omission in Early Breast Cancer:
    • Insights from the INSEMA Trial
  • Recent findings from the INSEMA trial offer robust evidence supporting the omission of sentinel lymph node biopsy (SLNB) in select patients with low-risk, early-stage invasive breast cancer undergoing breast-conserving surgery (BCS).
  • Presented by Toralf Reimer, PhD, at the 2024 San Antonio Breast Cancer Symposium (SABCS) and published in the New England Journal of Medicine, the trial demonstrates no significant compromise in survival outcomes when SLNB is omitted in these patients.
  • Among clinically node-negative women with stage T1 or T2 breast cancer, the 5-year invasive disease-free survival (DFS) rates were comparable:
    • 91.9% in patients omitting SLNB and 91.7% in those who underwent SLNB (HR: 0.91; 95% CI: 0.73–1.14).
  • Overall survival (OS) rates were also similar, estimated at 98.2% without SLNB and 96.9% with SLNB.
  • Trial Design and Key Results:
    • The INSEMA trial enrolled 5,502 patients with clinically node-negative, hormone receptor-positive, HER2-negative invasive breast cancer (T1 / T2, tumor size ≤ 5 cm). Following BCS and whole-breast irradiation, patients were randomized to SLNB or no axillary surgery.
      • Median follow-up: 73.6 months
      • Axillary recurrence:
      • Slightly higher in the no-SLNB group (1.0% vs. 0.3%):
        • Though the absolute numbers were low
      • Distant relapse rates:
        • Identical at 2.7% in both groups
      • Morbidity:
        • Omitting SLNB significantly reduced rates of lymphedema (5.7% vs. 1.8%), arm mobility restrictions (3.5% vs.
          and pain with arm or shoulder movement (4.2% vs. 2.0%).
          • Context Within Ongoing De-Escalation Trials
            • The INSEMA trial is one of four ongoing studies exploring the omission of axillary surgery in select patients with early-stage breast cancer. These include:
              • SOUND trial: Published results demonstrated no difference in 5-year DFS or OS between patients undergoing or omitting axillary surgery for small (≤ 2 cm) breast tumors.
              • BOOG 2013-08 and NAUTILUS trials: Expected to further validate and refine patient selection criteria for omitting axillary surgery.
            • Clinical Implications
            • The INSEMA trial strengthens the case for omitting SLNB in carefully selected patients, particularly for tumors ≤ 2 cm. However, the continued role of SLNB as a staging tool in certain patients and the need for shared decision-making with multidisciplinary teams.
            • This trial represents a key milestone in an ongoing paradigm shift, aligning with earlier data (e.g., Danish Breast Cancer Cooperative Group studies from the 1980s) that suggested no survival benefit from extensive axillary node removal.
            • Conclusion:
              • The findings from the INSEMA trial provide compelling evidence supporting deescalation of axillary surgery in early-stage breast cancer, with a significant reduction in morbidity and no compromise in survival outcomes.
              • Further results from ongoing trials such as BOOG 2013-08 and NAUTILUS will likely cement this strategy as standard practice for patients with low axillary disease burden.


SOUND Trial Summary

  • Title:
    • Axillary Surgery in Breast Cancer Patients With Negative Axillary Ultrasound: The SOUND Randomized Clinical Trial
  • Published:
    • 2023 in JAMA Oncology
      • ClinicalTrials.gov ID: NCT02167490
  • Location:
    • Italy, Spain, Switzerland, Chile (18 hospitals)
  • Study Objective:
    • To evaluate whether sentinel lymph node biopsy (SLNB):
      • Can be safely omitted in women:
        • With early-stage, clinically node-negative breast cancer with negative axillary ultrasound (AUS), without compromising oncologic outcomes
  • Patient Population:
    • Women with:
      • Unifocal invasive breast cancer:
        • Tumor ≤ 2.0 cm (cT1)
      • Clinically and ultrasound-negative axilla
      • Undergoing breast-conserving surgery
      • No neoadjuvant therapy
    • Tumor types:
      • Majority were hormone receptor-positive, HER2-negative
  • Study Design:
    • Randomized, phase 3, non-inferiority trial
    • Two arms:
      • SLNB group:
        • Underwent sentinel lymph node biopsy
      • Observation group:
        • No axillary surgery
    • Primary endpoint:
      • 5-year distant disease-free survival (DDFS)
    • Secondary endpoints:
      • Overall survival (OS)
      • Disease-free survival (DFS)
      • Axillary recurrence
      • Quality of life
  • Non-inferiority was met for the primary endpoint (DDFS)
  • Clinical Implications:
    • In women with small tumors (≤ 2 cm) and negative axillary ultrasound:
      • SLNB can be omitted without compromising distant disease-free or overall survival
    • Supports a less invasive approach and aligns with the de-escalation of axillary surgery trend in breast cancer care
  • Leads to fewer surgical complications:
    • Lymphedema, seroma, pain
  • Limitations:
    • Results apply only to women with:
      • Negative axillary ultrasound and early-stage, low-risk tumors
    • Not applicable to:
      • Mastectomy patients
      • Multifocal tumors
      • Patients receiving neoadjuvant therapy
  • Conclusion:
    • The SOUND trial confirms that routine sentinel lymph node biopsy can be safely omitted in selected patients with early-stage breast cancer and negative axillary ultrasound:
      • Supporting a shift toward minimally invasive surgical strategies in modern breast cancer management

SENOMAC Trial in Breast Cancer

  • Design and who was included:
    • Multicenter randomized contral trial (RCT):
      • Setting:
        • Sweden, Denmark, Germany, Greece, Italy
      • Patients:
        • cN0, cT1 to cT3 tumors with 1 to 2 SLN macrometastases:
          • BCS or mastectomy allowed
        • Extra capsular extension (ECE) and cT3 permitted
        • SENOMAC did allow patients who had SLNB before neoadjuvant systemic therapy (NAST) to be enrolled if cN0 and with ≤ 2 SLN macrometastases:
          • Randomization was recommended before starting NAST
      • Randomized SLNB only vs cALND:
        • Adjuvant therapy and radiation therapy (RT) per national guidelines
      • Size and surgery type:
        • N=2766 enrolled:
          • Per-protocol N=2540:
            • SLNB 1335
            • cALND 1205
          • Mastectomy ≈ 36% in each arm:
            • SLNB 490 / 1335
            • cALND 430 / 1205
      • Radiation usage (key to applicability):
        • RT including nodal volumes given to ~ 90% in both arms:
          • SLNB 89.9%; cALND 88.4%
        • Quality assessment (QA) check showed:
          • 99.3% concordance for breast / chest-wall fields and 96.6% for nodal targets
  • Endpoints and follow-up:
    • Primary endpoint = OS (pending):
      • In 2020 the Data and Safety Monitoring Board (DSMB):
        • Switched the primary endpoint to overall survival (OS):
          • To declare non-inferiority on OS, the trial needs 190 deaths:
            • At last analysis there weren’t enough events:
              • So OS is not yet formally tested
      • They still report 5-yr OS estimates:
        • ≈ 92.9% vs 92.0%
    • Reported prespecified secondary endpoint:
      • RFS; NI margin HR upper bound < 1.44
    • Median follow-up:
      •  46.8 months
  • Results (per-protocol)
    • 5-yr RFS: 
      • 89.7% (SLNB) vs 88.7% (cALND):
        • HR 0.89 (95% CI 0.66–1.19) → non-inferior
    • 5-yr OS: 
      • 92.9% (SLNB) vs 92.0% (cALND)
    • Breast cancer (BC)-specific survival: 
      • 97.1% (SLNB) vs 96.6% (cALND)
    • Regional recurrences were rare:
      • Axilla alone in 3 patients
      • Axilla + infraclavlavicular 2 patients
      • Supraclavicular / infraclavicualar, internal mammary nodes (IMN), parasternal 1 each (locations unknown in 4)
    • Local and distant events similar between arms
    • Stage migration: 
      • Among primary-surgery patients,:
        • cALND upstaged more often (pN2 – 9.9%, pN3 – 3.0%) vs SLNB-only (pN2 – 0.5%):
          • Without outcome benefit
        • Additional non-SLN metastasis on cALND in 34.5% overall:
          • If 1 SLN macrometatases:
            • 31.3% had more positive nodes
          • If 2 macrometastases:
            • 51.3% had more positive nodes
  • Toxicity / PROs:
    • At 1 year:
      • Randomized SENOMAC PRO analysis:
        • SLNB-only patients reported less arm pain / symptoms and better function than cALND
    • Post-hoc (Lancet Oncol 2024):
      • Focused on abemaciclib eligibility:
        • To prevent 1 iDFS event at 5 yrs via identifying ≥ pN2-pN3 with cALND:
          • ~ 104 cALNDs would be needed:
            • Causing severe / very severe arm dysfunction in ~ 9 / 104 at 1 year:
              • Discourages ALND purely to find pN2-pN3 for CDK4/6 indication
  • Why it matters (esp. mastectomy):
    • ≈ 36% mastectomy:
      • With comprehensive nodal RT common:
        • Omitting cALND preserved control and survival and minimized arm morbidity:
          • Supports SLNB-only + RNI / PMRT for 1 to 2 SLN macrometastases after mastectomy
  • One-liner: 
    • SENOMAC shows that in cN0 patients with 1 to 2 SLN macrometastases including mastectomy cases:
      • SLNB – only with planned nodal RT is non-inferior to cALND for oncologic outcomes and substantially reduces arm morbidity
  • Summary:
    • Why this trial had what it adds: 
      • Prior trials (ACOSOG Z0011, AMAROS) had power / RT-field uncertainties and underrepresented subgroups
      • SENOMAC purposely broadened eligibility (included mastectomy, ECE, T3, and men) to validate omission of cALND in a larger, more representative cohort
    • Consistency with prior evidence: 
      • Findings align with AMAROS and OTOASOR (no oncologic advantage to cALND; morbidity higher with ALND)
      • Ongoing / related trials (e.g., POSNOC; INSEMA’s second randomization) are noted for context
    • Generalizability: 
      • Age distribution mirrors real-world Nordic populations, supporting external validity
      • Inclusion of substantial mastectomy volume improves applicability beyond BCS-only settings
    • RT practice in the trial: 
      • Adjuvant RT followed national guidelines:
        • ~ 90% received nodal RT
      • Data entry matched actual RT plans well (good concordance):
        • Though granular nodal-level dose / field details were not yet available at reporting
    • Limitations called out by authors:
      • Shorter follow-up relative to late-recurring luminal cancers
      • Very few men enrolled (n≈10), limiting sex-specific analyses
      • Trial under-enrolled vs target:
        • But event counts and narrow CIs yield precise estimates for NI
      • Higher withdrawal in the ALND arm, though unlikely to affect conclusions given size and balance
    • Bottom line : 
      • For cN0 cT1 to cT3 patients with 1 to 2 SLN macrometastases who receive modern systemic therapy and (typically) comprehensive nodal RT:
        • Omitting cALND maintains disease control with less arm morbidity
      • Results support replacing routine cALND with SLNB ± RNI / PMRT:
        • While acknowledging the need for longer follow-up and more granular RT-field reporting

In p16+ Oropharyngeal Squamous Cell Carcinoma (OPSCC) – Does any Efficacy Endpoint Favor Cetuximab-RT over Cisplatin-RT?

  • In p16+ OPSCC, does any efficacy endpoint favor cetuximab-RT over cisplatin-RT?
    • Best answer: 
      • No
    • Why: 
      • Neither OS, PFS, nor LRC improved with cetuximab:
    • When to deviate: 
      • Only with absolute cisplatin ineligibility PMC:
        • Discuss RT + cetuximab (Bonner) or altered-fractionation RT
    • Pitfalls: 
      • Extrapolating the Bonner 2006 RT + cetuximab vs RT-alone result:
        • To cisplatin-eligible patients is incorrect New England Journal of Medicine
        • Bonner:
          • 5-yr OS 45.6% with RT + cetuximab vs 36.4% RT alone:
            • Not a comparison to cisplatin
      • Under-discussing ototoxicity / renal toxicity risks with cisplatin:
        • Document shared decision-making when deviating
    • Numbers: 
      • RTOG – 1016 (NI trial, Lancet 2019):

        • 5-yr OS:  84.6% cisplatin vs 77.9% cetuximab (non-inferiority failed; cetuximab inferior) 

        • PFS and LRC: both significantly worse with cetuximab (PFS HR ≈ 1.72; LRF HR ≈2.05) Oral Cancer Foundation+1

        •  
      • De-ESCALaTE HPV (Lancet 2019):

        • ~ 2-yr OS:  97.5% cisplatin vs 89.4% cetuximab (HR ~ 5.0)

        • Recurrence: higher with cetuximab (HR ~ 3.4)

        • Severe toxicity rates overall similar — no compensatory safety win. 

Rodrigo Arrangoiz, MD (Oncology Surgeon)

Step-by-Step Expansion of Leukocyte Recruitment

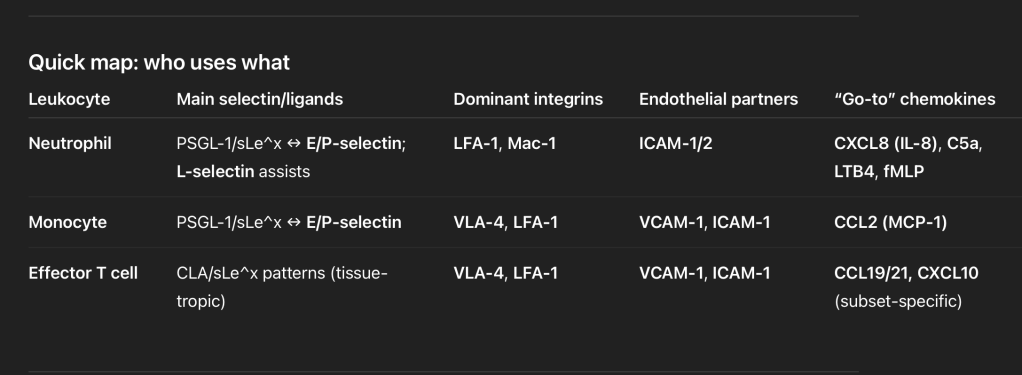
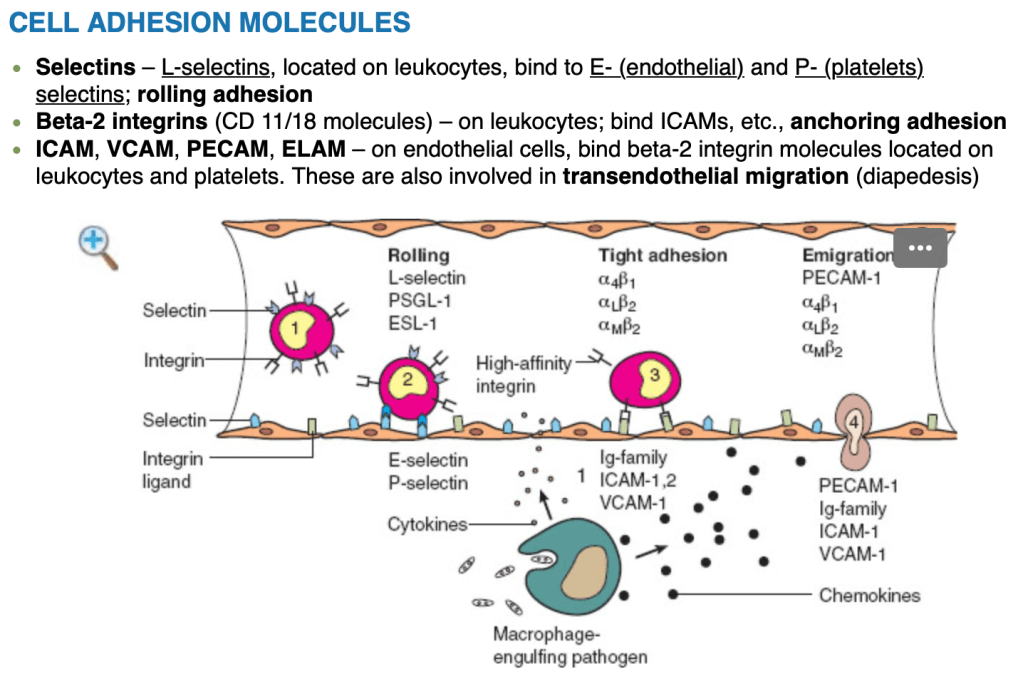
  • Tethering and Rolling (milliseconds–seconds):
    • What happens: 
      • Fast blood flow makes first contact fleeting:
        • Cells need “molecular Velcro” that works under shear.
      • Selectins on endothelium: 
        • E-selectin:
          • Induced by TNF-α / IL-1
        • P-selectin:
          • Rapidly mobilized from Weibel–Palade bodies
          • Also on platelets
      • Ligands on leukocytes: 
        • PSGL-1 and other sialyl-Lewis^x (sLe^x):
          • Decorated glycoproteins
        • L-selectin (CD62L) is on leukocytes:
          • Not endothelium:
            • It helps secondary capture / rolling:
              • Leukocyte–leukocyte interactions
                • Binds Peripheral Node Addressin on High Endothelial Venules (PNAd on HEVs)
        • Mechanics: 
          • “Catch bonds” let cells roll, sampling endothelium for activating cues
        • ✅ Fix to your line: 
          • Rolling is mainly:
            • E-selectin / P-selectin (endothelium) ↔ sLe^x/PSGL-1 (leukocyte)
          • L-selectin:
            • Is leukocyte-borne:
              • It augments rolling
          • P-selectin:
            • Is not on neutrophils
  • Chemokine-Triggered Integrin Activation (“inside-out”):
    • What happens: 
      • Endothelial-bound chemokines (on heparan sulfates:
        • For example:
          • CXCL8 /IL-8 (neutrophils), CCL2 / MCP-1(monocytes):
            • Bind GPCRs (CXCR1/2, CCR2…), engaging Gαi → Rap1 → talin / kindlin:
              • To flip integrins into high-affinity and clustered states
      • Key integrins switched on:
        • β2 family: 
          • LFA-1 (αLβ2; CD11a/CD18)
          • Mac-1 (αMβ2; CD11b/CD18).
        • β1 family: 
          • VLA-4 (α4β1):
            • Prominent in monocytes / lymphocytes
  • Firm Arrest and Adhesion Strengthening (seconds–minutes):
    • Counter-receptors on endothelium:
      • ICAM-1 / ICAM-2 ↔ LFA-1 / Mac-1 (β2)
      • VCAM-1 ↔ VLA-4 (β1)
    • Outside-in signaling:
      • Through engaged integrins stiffens the cytoskeleton (actin remodeling via Rho / Rac / Cdc42) and spreads the cell, locking it in place
  • Intraluminal Crawling:
    • Arrested leukocytes crawl “upstream” under shear to junctions, mainly using Mac-1 ↔ ICAM-1:
      • This helps them find permissive exit sites
  • Diapedesis (Transendothelial Migration):
    • Two routes:
      • Paracellular (most common):
        • Through junctions
      • Transcellular: 
        • Through individual endothelial cells
    • Adhesion molecules guiding the crossing:
      • PECAM-1 (CD31), JAM-A/B/C, CD99, ESAM:
        • Mostly homophilic interactions at junctions
      • Transient loosening of VE-cadherin adherens junctions (kinase signaling) opens a path
    • Basement membrane and pericytes:
      • Leukocytes use integrins (e.g., α6β1, αvβ3) and proteases (MMP-2/-9, elastase) to breach matrix and pericyte sheaths, aiming for naturally “low-expression regions” of laminins / collagens
    • Interstitial Chemotaxis → Focus of Infection / Injury:
      • Once in tissue, cells follow gradients of:
        • Chemokines: 
          • CXCL8 (neutrophils), CCL2 (monocytes), CCL19/21 (lymphocyte homing)
        • Lipid mediators: 
          • LTB4, PGE₂ (context-dependent)
        • Complement & danger cues: 
          • C5a, fMLP from bacteria
  • Exam pearls
  • Sequence to memorize: 
    • Selectin-mediated rolling → chemokine GPCR signal → integrin activation → firm adhesion → crawling → diapedesis → chemotaxis
  • Inside-out vs outside-in:
    • Chemokines activate (inside-out) integrins
    • Integrin engagement stabilizes and signals (outside-in)
  • Platelets matter: 
    • Platelet P-selectin can recruit leukocytes to thrombi (immunothrombosis)
  • Tissue tropism: 
    • VLA-4 ↔ VCAM-1 is big for monocytes / lymphocytes
    • Neutrophils lean on β2 integrins
Leukocyte recruitment. (1) Circulating leukocytes express integrins in a low-affinity conformation. (2) Exposure to activated endothelium leads to rolling, which is mediated by L-selectin and P-selectin on the neutrophil and E-selectin on the endothelium. (3) Leukocyte exposure to cytokines released by macrophages phagocytosing pathogens induces a high-affinity integrin conformation. Tight leukocyte—endothelial adhesion involves integrin engagement with counter-ligand expressed on the endothelium. (4) Subsequent exposure to chemokines leads to diapedesis, which is further mediated by the family of β1- and β2-integrins.

What is the Optimal Operative Approach for DTC RECOMMENDATION 15 from the ATA 2025 Guidelines

  • When resection is performed for patients with thyroid cancer ≤ 2 cm without gross extra-thyroidal extension (cT1) and without metastases (cN0M0):
    • The initial surgical procedure should be a thyroid lobectomy:
      • Unless there are bilateral cancers or other indications to remove the contralateral lobe:
        • Strong recommendation, Moderate certainty evidence
  • For patients with low risk, unilateral thyroid cancer > 2 and ≤ 4 cm (cT2N0M0):
    • Thyroid lobectomy may be the preferred initial surgical treatment due to significantly lower risk and side effects:
      • However, the patient and treatment team may adopt total thyroidectomy to enable RAI administration and / or enhance follow-up based on disease features, suspicious contralateral nodularity, and / or patient preferences
    • When thyroid lobectomy is offered as initial treatment, counsel the patient about the possibility of conversion to total thyroidectomy or need for subsequent completion thyroidectomy if higher-risk factors emerge intraoperatively or postoper-
      atively:
      • Conditional recommendation, Low-moderate
        certainty evidence
  • For patients with thyroid cancer > 4 cm (cT3a), cancer of any size with gross extra-thyroidal extension (cT3b or cT4), or clinically apparent metastatic disease to lymph nodes (cN1) or distant sites (cM1):
    • The initial surgical procedure should include a total thyroidectomy with gross removal of all primary tumor and node dissection unless there are contraindications to this procedure
      • Strong recommendation, Moderate
        certainty evidence

RTOG-0920 (NRG-RTOG 0920)

  • Who was studied?
    • Population: 
      • Completely resected, intermediate-risk HNSCC of:
        • Oral cavity, oropharynx, or larynx:
          • Hypopharynx excluded
      • Intermediate-risk factors included any of: 
        • Pernineural invasion (PNI)
        • Lymphovascular ivasion (LVI)
        • ≥ 2 lymph nodes (LNs) (all < 6 cm) or one LN > 3 cm (no extranodal extension (ENE))
        • Close margin(s) < 5 mm or focally positive then re-resected negative
        • pT3 to pT4a primary, or T2 oral cavity with DOI > 5 mm ozarkscancerresearch.org
      • Key baseline notes: 
        • Majority HPV-negative (~ 80%)
        • Oral cavity ~ 64%
        • EGFR high expression in ~ 85%(assayed for stratification, not a requirement) NRG Oncology+1
    • Study design and treatment:
      • Randomization (1:1): 
        • PORT alone vs PORT + cetuximab
      • PORT: 
      • Cetuximab regimen: 
        • 400 mg/m² loading, then 250 mg/m² weekly x 6 during RT + 4 weekly doses post-RT (total 11) ozarkscancerresearch.org
      • Primary endpoint: 
        • Overall survival (OS) in all randomized / eligible
          • Pre-specified plan to test in HPV-negative subgroup
      • Secondary endpoints: 
        • Disease-free survival (DFS), toxicity, others PubMed
    • Results (median follow-up ~ 7.2 years):
      • Primary endpoint (OS): Negative:
        • OS HR 0.81; one-sided p=0.075 (did not meet significance)
        • 5-yr OS: 
      • Secondary endpoint (DFS): Positive
        • DFS HR 0.75; one-sided p=0.017
        • 5-yr DFS: 
          • 71.7% (PORT+cetuximab) vs 63.6% (PORT)
      • Toxicity:
        • Acute grade 3 to 4: 
          • 70.3% (PORT+cetuximab) vs 39.7% (PORT); p<0.0001:
        • Late grade 3 to 4: 
          • 33.2% vs 29.0%, p=0.31 (no significant increase)
        • No grade-5 events NRG Oncology
      • Quality of life: 
        • A dedicated RTOG-0920 QoL analysis was presented at ASCO 2025:
          • Aligns with the toxicity profile (no long-term penalty reported in the abstract listing). ASC Publications+1
  • Interpretation (how to use this):
    • For HPV-negative, intermediate-risk patients who are not ideal candidates for high-dose cisplatin (remember cisplatin is reserved for high-risk ENE+ / positive-margin per RTOG 9501/EORTC 22931 era):
      • Adding cetuximab to PORT is a reasonable option to improve DFS without increasing late toxicity:
        • With trade-off of substantially higher acute toxicity
        • OS was not improved PubMed+1
        • HPV-positive:
          • No signal of benefit:
            • Do not extrapolate a DFS advantage here. PubMed
    • Sites: 
      • Data are particularly representative for oral cavity primaries (largest stratum) Red Journal
  • Practical selection checklist (tumor board quick hits):
    • Use PORT + cetuximab consideration when ALL are true:
      • HPV-negative HNSCC (oral cavity / oropharynx / larynx)
      • Intermediate-risk features as per protocol list above
      • No ENE or positive margins:
        • Those are high-risk → cisplatin-based CRT
      • Patient not a good candidate for cisplatin (comorbidities, renal / hearing issues)
      • Accepts higher acute toxicity risk and closer supportive care during RT ozarkscancerresearch.org+2PubMed+2
  • Key trial specs (at a glance):
    • NCT00956007; Opened Nov 2009, closed Mar 2018; n=577 eligible. NRG Oncology+1
    • IMRT mandatory; p16 testing required for oropharynx; EGFR IHC collected (stratification/analysis). ozarkscancerresearch.org
  • Citation anchors:
    • Machtay M, et al. JCO 2025;43(12):1474–1487. Epub Jan 22, 2025. (Primary publication.) PubMed
    • NRG Oncology press summary with HRs, 5-yr estimates, and toxicity breakdown. NRG Oncology
    • Protocol (2016) schema/eligibility for exact intermediate-risk feature definitions and cetuximab dosing. ozarkscancerresearch.org
    • Additional baseline composition (oral cavity %, EGFR high) from earlier abstract. Red Journal

What did the Meta-Analysis of Chemotherapy in Head and Neck Cancer (MACH-NC) Actually Showed?

  • Takeaway: 
    • Concomitant chemotherapy + radiation therapy (RT):
      • Yields a statistically significant OS benefit vs RT alone:
        • HR ~ 0.83; ~ 6.5% 5-yr OS gain:
          • Driven by improved locoregional control
      • Induction alone or adjuvant alone did not improve OS
  • Use: 
    • This underpins cisplatin-CRT as the default curative standard
  • Refs: 
    • Lacas et al., MACH-NC (Radiother Oncol 2021; PMC)
  • What it is individual-patient data meta-analysis updating the MACH-NC database:
    • To 107 RCTs / 19,805 patients:
      • Accrued 1965 to 2012
    • Updated median follow-up:
      • 6.6 years
    • Endpoints:
      • OS, EFS, 120-day mortality, loco-regional failure (LRF), distant failure (DF), cancer vs non-cancer deaths Groningen Research Portal+1
    • Results by timing of chemotherapy:
      • Concomitant chemoradiotherapy (CRT) vs loco-regional therapy alone:
        • Overall survival: 
          • HR 0.83 (95% CI 0.79–0.86):
            • Absolute OS gain + 6.5% at 5 yr and + 3.6% at 10 yr (≈ NNT ~ 15 at 5 yr)
        • EFS:
          • HR 0.80 with + 5.8% at 5 yr
        • No increase in 120-day mortality:
        • Patterns of failure: 
          • Marked LRF reduction (sub-HR 0.71)
          • No DF effect (HR 1.04)
          • Survival benefit driven by lower cancer mortality (HR 0.79; − 9.8% at 5 yr):
        • Regimen effects: 
          • Greatest effect for platinum-containing polychemotherapy (EFS HR 0.74)
          • Smallest for non-platinum monochemotherapy (HR 0.86)
          • Benefit consistent across eras and RT modalities Groningen Research Portal
    • Induction chemotherapy (before RT / CRT):
      • OS and EFS: 
        • No significant benefit:
          • OS HR 0.96
          • EFS HR 0.96
        • DF decreases (HR 0.76):
          • But no LRF improvement (sub-HR 1.07)
        • Benefit attenuates with worse performance status Groningen Research Portal
    • Adjuvant chemotherapy (after loco-regional therapy):
      • OS and EFS: 
        • No benefit:
          • OS HR 1.02
          • EFS HR 0.98
      • Early mortality: 
        • Higher 120-day mortality (HR 1.89, p=0.0003)
        • Some reduction in LRF (sub-HR 0.84) and DF(HR 0.77) without survival gain Groningen Research Portal
    • Direct head-to-head concomitant vs induction (same drugs):
      • Across eight comparisons (n=1,214), concomitant is superior: 
        • OS HR 0.84 (≈ + 6.2% absolute OS at 5 yr)
        • EFS HR 0.85
        • LRF HR 0.86
      • Indirect comparisons concur (interaction p<0.0001) Groningen Research Portal
    • Subgroups and modifiers:
      • Age: 
      • Performance status: 
      • HPV / smoking: 
    • Practical takeaways:
      • For curative, non-metastatic HNSCC:
        • The only timing with proven OS benefit is concomitant chemo with RT
        • Expect ~ 6% to 7% absolute 5-yr OS gain:
      • Induction doesn’t improve OS vs loco-regional therapy alone (despite fewer distant mets)
      • Adjuvant chemo doesn’t improve OS and raises early mortality risk Groningen Research Portal+1
      • Within concomitant therapy:
        • Platinum-containing regimens carry the strongest signal:
  • Limitations the paper notes:
    • Trials span 1965 to 2012:
      • Staging, RT techniques, supportive care evolved
      • Still, no interaction by accrual period and sensitivity analyses were consistent
      • HPV data were largely unavailable. Groningen Research Portal
  • Citation (free full text): 
    • Lacas B, Carmel A, Landais C, et al. MACH-NC update—107 RCTs, 19,805 pts. Radiother Oncol. 2021;156:281-293. PMC8386522. Key effect sizes and table are in the PDF’s Table 1 and text (OS/EFS/120-day mortality/LRF/DF). 

What to Monitor During Chemoradiation CRT with Cisplatin for Head and Neck Cancer?

  • What to monitor (and when):
    • Before starting (≤ 7 days prior):
      • BMP / eGFR + electrolytes: 
        • Cr, BUN, Mg, K, Ca, Na, PO₄
      • Urinalysis if concern for renal injury
        • Why: 
          • Baseline renal reserve; cisplatin causes salt wasting (especially Mg) and AKI eviQ
      • CBC with differential:
      • Audiology (baseline audiogram):
      • Medication review and vitals / weight.:
        • Hold / avoid nephrotoxins:
          • NSAIDs, IV contrast, aminoglycosides
        • Assess fluid status eviQ
      • Antiemetic plan (cisplatin = high emetic risk):
    • Each cisplatin day (same day or within 24 to 48 hour before dose):
      • BMP / eGFR + Mg / K / Ca / Na / PO₄ and CBC
        • Act: 
          • Replete Mg (often 10 mmol MgSO₄ pre-hydration) and correct K / Ca before dosing
          • If eGFR ↓ or SCr ↑:
            • Evaluate per KDIGO, hydrate, and hold / modify eviQ
      • Hydration status and urine output:
        • Act: 
          • Use isotonic saline pre / post hydration:
            • Typical total 2.5 to 3.0 L around infusion
          • Routine mannitol not required:
            • Consider only for very high-dose eviQ
      • Symptom screen: 
        • Tinnitus, hearing change, paresthesias, nausea / vomiting, cramps (hypo-Mg), mucositis, dysphagia
        • Act:
    • Weekly during RT (even if cisplatin is q3-weekly):
      • BMP / eGFR + Mg / K / Ca (at least weekly), CBC weekly, weight, I/Os
        • Why:
          • Catch AKI and hypomagnesemia early
          • Track cytopenias and dehydration eviQ+1
      • Audiology: 
        • Repeat before each cycle (q3-weekly) or sooner if symptoms; for weekly cisplatin, obtain symptom-triggered or mid-course checks per local protocol American Academy of Audiology+1
  • What to do with common issues?
    • Rising creatinine / suspected AKI:
      • Trigger: 
        • ≥ 0.3 mg/dL increase or ≥ 1.5 × baseline (KDIGO stage 1+):
          • Hold cisplatin, hydrate (NS), replete Mg / K, stop nephrotoxins, reassess in 24 to 72 hours
      • Escalate care by stage Merck Manuals+1
    • Hypomagnesemia (very common):
      • Prevention / correction:
        • Include MgSO₄ in pre-hydration (e.g., 10 mmol in 1 L NS) and replete as needed:
          • Mg protects against cisplatin nephrotoxicity eviQ+1
    • Emesis despite prophylaxis
    • Ototoxicity symptoms (tinnitus, high-frequency loss):
      • Action: 
  • Hydration—practical template (adjust per institution):
    • Pre-hydration: 
      • 1 L NS over ~ 60 min with 10 mmol MgSO₄
    • Cisplatin infusion: 
      • 1 L NS over ~ 60 min (institutional)
    • Post-hydration: 
      • 1 L NS over ~ 60 min:
        • Encourage oral fluids (≥ 500 mL if tolerated)
    • Mannitol / diuretics:
      • Not routine; consider case-by-case (e.g., very high-dose)  eviQ
  • One-look table (what/why/act);
    • BMP / eGFR + Mg / K / Ca / Na / PO₄ (baseline and weekly):
      • Nephrotoxicity / salt wasting → hydrate, replete Mg / K, hold if AKI eviQ
    • CBC weekly: 
      • Myelosuppression → delay / modify if grade ≥ 3, treat per protocol DailyMed
    • Audiogram baseline ± before each cycle / PRN: 
    • Antiemetics each dose: 
  • Bottom line: 
    • Weekly labs (BMP / eGFR, Mg / K / Ca) + CBC
    • Disciplined hydration with Mg supplementation
    • Symptom-triggered audiology are the pillars that prevent missed AKI, hypomagnesemia, cytopenias, and ototoxicity during CRT with cisplatin

Complement Cascade

  • Complement System:
    • The complement cascade is a system of immune proteins:
      • That activates in a cascade-like fashion:
        • To fight infection and promote tissue repair:
          • But also contributes to inflammation and disease when overactivated
    • It works via three pathways (classic, lectin, alternative):
      • That converge to create inflammatory fragments called:
        • Anaphylatoxins and form a membrane attack complex (MAC) that can kill pathogens
    • Beyond infection:
      • Complement plays roles in clearing cellular debris, facilitating tissue regeneration, and regulating neuronal function:
        • But inappropriate activation can cause:
          • Chronic pain, autoimmune disease, and organ damage
    • Pathways and Triggers:
      • Each pathway initiates the cascade through different triggers but ultimately leads to the same outcomes: 
        • Classical Pathway: 
          • Activated by the binding of antibodies (like IgG and IgM) to antigens:
            • On the surface of a pathogen
        • Lectin Pathway: 
          • Initiated when mannose-binding lectin (MBL):
            • Binds to carbohydrate structures on bacterial cell walls 
        • Alternative Pathway: 
          • Triggered by the direct binding of complement components to foreign surfaces, such as pathogens, without the need for antibodies 
      • Classical pathway (antibody-dependent):
        • Trigger: 
          • C1q, a component of the C1 protein complex:
            • Binds to an antibody-antigen complex:
              • On a pathogen surface
            • The C1 complex is composed of:
              • C1q, C1r, and C1s
        • Cascade:
          • C1r and C1s are activated:
            • Which then cleave complement proteins C4 and C2
            • The larger fragments, C4b and C2b (also called C2a):
              • Bind together to form the classical pathway’s C3 convertase (C4b2b) 
        • Antigen – antibody complexes:
          • Best: 
            • IgM:
              • Then IgG1 / IgG3
        • Early components unique to this pathway: 
          • C1 (C1q, C1r, C1s), C2, C4
        • C1 protein complex:
          • Needs Ca²⁺:
            • To stay assembled
      • Lectin pathway (antibody-independent; same cascade as classical after C4):
        • Trigger: 
          • The pattern recognition molecule:
            • Mannose-binding lectin (MBL) or ficolins:
              • Bind to specific carbohydrate patterns (like mannose) on the surface of pathogens
        • Cascade:
          • This binding activates MBL-associated serine proteases (MASPs):
            • Which are functionally similar to C1r and C1s
          • The MASPs cleave C4 and C2:
            • Forming the same C3 convertase (C4b2b) used by the classical pathway 
        • Mannose-binding lectin (MBL) or ficolins binding microbial sugars:
          • Enzymes: 
            • MASP-1 / MASP-2 cleave C4 and C2:
              • Merges with classic pathway a:
                • C3 convertase (C4b2a)
      • Alternative pathway (antibody-independent; tickover on surfaces):
        • Trigger: 
          • This pathway is always active at a low level through a “tickover” mechanism:
            • Where C3 is spontaneously hydrolyzed
          • It is further activated when C3b, a fragment of C3:
            • Binds directly to the surface of a pathogen or foreign material
        • Cascade:
          • Factor B binds to the surface-bound C3b and is then cleaved by Factor D to form C3bBb:
            • The alternative pathway’s C3 convertase
          • The protein properdin stabilizes this complex:
            • Amplifying the cascade
          • This pathway also acts as an amplification loop for the classical and lectin pathways
        • Spontaneous C3 hydrolysis on microbial / endotoxin surfaces:
          • Amplified by Factor B, Factor D, Properdin (P)
          • Note: 
            • Mg²⁺ is required for Factor B binding to C3b
            • Properdin stabilizes the convertase
        • Common note: 
          • C3:
            • Common to and is the convergence point for the three pathways
      • The final, common pathway:
        • All three initiation pathways converge to form a C3 convertase:
          • Which ultimately leads to the creation of the:
            • Membrane attack complex (MAC) 
        • C3 cleavage:
          • A C3 convertase cleaves C3 into two pieces:
            • C3a:
              • A small fragment that acts as a potent:
                • Anaphylatoxin, triggering inflammation
            • C3b:
              • A larger fragment that acts as an opsonin, or “tag,” marking the pathogen for destruction
              • It also attaches to the C3 convertase to create a C5 convertase
        • C5 cleavage:
          • The C5 convertase cleaves C5 into C5a (a potent anaphylatoxin and chemoattractant) and C5b
        • Membrane Attack Complex (MAC):
          • The C5b fragment recruits and assembles the remaining complement proteins (C6, C7, C8, and multiple C9 molecules):
            • To form a cylindrical pore in the pathogen’s membrane:
              • This pore disrupts the cell’s osmotic balance:
                • Causing it to lyse and die
      • C3 / C5 Convertases (know these cold):
        • Classical / Lectin pathway:
          • C3 convertase: 
            • C4b2a
          • C5 convertase: 
            • C4b2a3b
        • Alternative pathway:
          • C3 convertase: 
            • C3bBb:
              • Stabilized by Properdin / P
          • C5 convertase: 
            • C3bBb3b
        • Effector Functions (the “what does each piece do?”):
          • Anaphylatoxins: 
            • C3a, C4a, C5a:
              • ↑ vascular permeability
              • Vasodilation
              • Bronchoconstriction
              • Mast cell / basophil degranulation
            • Potency: 
              • C5a > C3a >> C4a (C4a is weak)
          • Chemotaxis (especially neutrophils): 
            • C5a is the major chemoattractant:
              • C3a contributes mainly as anaphylatoxin
            • C5a drives:
              • Leukocyte recruitment
              • Adhesion up-regulation
              • Oxidative burst
          • Opsonization: 
            • C3b (and iC3b), C4b
            • Coat pathogens (marks them for destruction):
              • CR1 / CR3 on phagocytes bind → enhanced phagocytosis
          • Membrane Attack Complex (MAC): 
            • C5b to C9
            • C5b:
              • Nucleates assembly with C6, C7, C8, C9 (polymerizes) → pore → osmotic lysis (classically Neisseria)
        • Ion Requirements (exam-friendly correction):
          • Classical and Lectin Pathway: 
            • Ca²⁺ required for C1qrs (classical) and MBL – MASP (lectin) complexes:
              • Mg²⁺ also involved downstream
          • Alternative pathway: 
            • Mg²⁺ essential for Factor B – C3b interaction and convertase formation:
              • So: not “Mg for both pathways”:
                • Only – Classical / Lectin need Ca²⁺
                • Alternative needs Mg²⁺ (and Properdin)
        • Regulation (why we don’t self-destruct):
          • C1 inhibitor (C1-INH): 
            • Blocks C1r / C1s and MASPs 1/2 (MASP-1 / MASP-2 cleave C4 and C2):
              • Turns off classic / lectin pathways early
          • Factor H and Factor I: 
            • Inactivate C3b (→ iC3b) on host cells:
              • Factor H prefers sialic acid – rich self surfaces
          • DAF / CD55: 
            • Disrupts C3 / C5 convertases on host cells
          • CD59 (Protectin): 
            • Blocks C9 polymerization:
              • Prevents MAC on self cells
          • Clinical Correlates (high-yield):
            • C1-INH deficiency → Hereditary angioedema:
              • Bradykinin-mediated edema:
                • ACE inhibitors worsen
              • Treat with C1-INH concentrate, bradykinin pathway blockers
            • C2 deficiency (most common classic pathway deficiency):
              • SLE-like disease, recurrent sinopulmonary infections
            • C3 deficiency:
              • Recurrent severe pyogenic infections:
                • Especially encapsulated bacteria; immune complex disease.
            • Terminal complement (C5 to C9) deficiency:
              • Recurrent Neisseria (meningitidis, gonorrhoeae)
            • DAF / CD55 or CD59 deficiency (e.g., PNH via PIGA mutation):
              • Intravascular hemolysis, hemoglobinuria, thrombosis
              • Treat with C5 inhibitors:
                • Eculizumab / ravulizumab
            • Factor H / I abnormalities:
              • Atypical HUS, C3 glomerulopathy
          • Laboratory Assessment:
            • CH50:
              • Total classic pathway function:
                • Low in classic component defects or terminal pathway defects
            • AH50:
              • Total alternative pathway function
            • Heat-labile:
              • Complement activity falls if serum is mishandled / warmed
        • Quick “Apply It” Pearls:
          • Suspected meningococcemia with recurrence:
            • Check terminal complement (C5 to C9)
          • Recurrent pyogenic infections with low C3:
            • Evaluate classic / alternative convertase regulation
          • Episodic angioedema without urticaria:
            • Think C1-INH deficiency
          • Autoimmunity in a young patient + low early classic components (C1q/C2/C4) → screen for complement deficiencies
        • One-Page Memory Map:
          • Triggers:
            • Classic pathway: 
              • IgM / IgG immune complexes → C1qrs (Ca²⁺)
            • Lectin pathway: 
              • MBL / ficolin (MASPs) → C4, C2
            • Alternative pathway: 
              • C3 tackover + B, D, Properdin (Mg²⁺)
            • Convertases:
              • Classic / Lectin: 
                • C4b2a (C3), C4b2a3b (C5)
              • Alternative:
                • C3bBb (C3), C3bBb3b (C5)
            • Effectors:
              • Opsonins: 
                • C3b/iC3b (± C4b)
              • Anaphylatoxins: 
                • C5a > C3a >> C4a
              • Chemotaxis: 
                • C5a
              • MAC: C5b to C9
            • Regulators: 
              • C1-INH, Factor H / I, DAF (CD55), CD59
            • Deficiencies (buzzwords): 
              • C1-INH—HAE
              • C2—SLE-like
              • C3—pyogenic infections
              • C5–C9—Neisseria
              • DAF/CD59—PNH
              • Factor H/I—aHUS