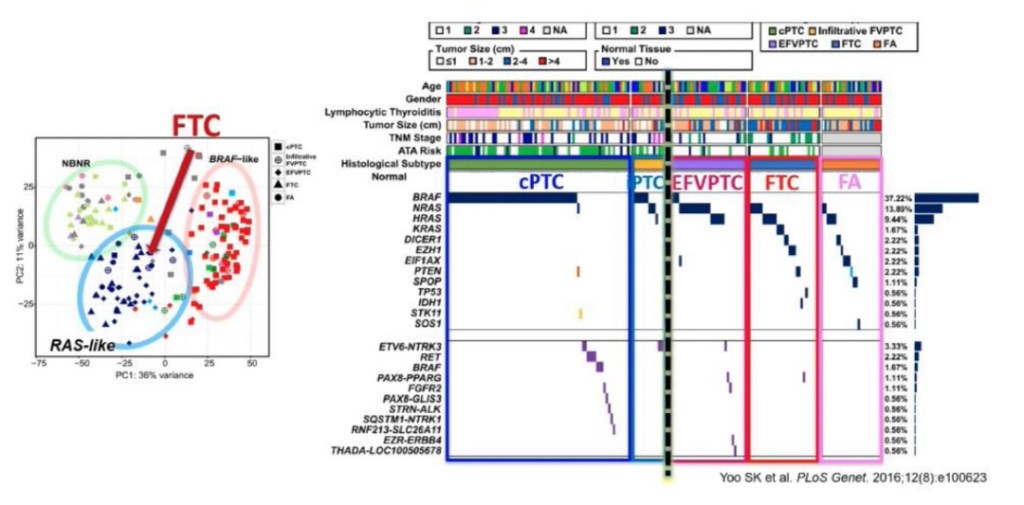
Follicular Thyroid Carcinoma (FTC)

  • The second most common type of thyroid cancer is:
    • Follicular thyroid carcinoma (FTC)
  • Fundamentally all follicular carcinomas are:
    • RAS-like tumors
  • There profile is different from classic PTC because:
    • They do not have BRAF mutations:
      • Most of them have RAS and RAS-like mutations
  • Yoo S.K et al, from Korea showed that the genetic profile of follicular carcinomas:
    • Is very similar to follicular adenomas because they are related tumors
    • Most FTC originate from a FA and eventually break through the capsule and become carcinomas
  • In encapsulated follicular variant of PTC:
    • Their molecular profile is much closer to a FA and FTC than to classic PTC
  • Infiltrative follicular variant of PTC:
    • Has a molecular profile that is more like classic PTC than FTC
  • The biologic difference between follicular pattern RAS-like tumors and classic PTC:
    • Is the infiltrative growth pattern (Figure)
    • The difference between these tumors:
      • Is not only phenotypically based on gross pattern, but also based on biological and clinical differences;
        • Because follicular pattern RAS-like tumors:
          • Retain avidity to radioactive iodine
        • BRAF-like tumors (classic PTC and infiltrative follicular variant of PTC):
          • Have the classic features of PTC
          • They are infiltrative
          • They spread to lymph nodes first and later to distant sites
          • They lose the expression of genes associated with thyroid differentiation
        • RAS-like tumors (FA, FTC, NIFTP, and invasive encapsulated follicular variant of PTC):
          • May or may not have nuclear features of PTC
          • They are encapsulated
          • They spread to distant sites (rarely to lymph nodes)
          • They retain expression of genes associated with thyroid differentiation

Graph exemplifying the difference between follicular pattern RAS-like tumors and classic PTC,
which is the infiltrative growth pattern.

Transcriptomic Classification of Thyroid Cancer

  • The trans-genomic classification of thyroid cancer, particularly papillary thyroid carcinoma (PTC):
    • Has significant clinical implications, as it enables personalized diagnosis, prognosis, and treatment strategies
  • Recent studies have identified molecular subtypes of PTC based on genomic and transcriptomic profiling:
    • Which provide insights into tumor behavior and therapeutic responses
  • Key Molecular Subtypes
    • Immune-Enriched Subtype (Subtype 2):
      • High immune infiltration and overexpression of immune checkpoints
      • Potential candidates for immunotherapy.
    • BRAF-Enriched Subtype (Subtype 4):
      • Associated with aggressive features like:
        • Extrathyroidal extension
        • Advanced TNM stages
    • Enriched in MAPK and PI3K / AKT signaling pathways:
      • Suggesting targeted therapy options
    • Stromal Subtype (Subtype 3):
      • High stromal content with distinct microenvironmental features
    • CNV-Enriched Subtype (Subtype 6):
      • Characterized by copy number variations with unique genetic drivers
  • Clinical Implications:
    • Prognostic Value:
      • Molecular subtypes correlate with survival outcomes
      • Type 3 subtypes (high-risk):
        • Show poorer progression-free survival compared to Type 1 (low-risk)
    • Therapeutic Guidance:
      • Subtypes like the Immune-Enriched or Ras-like Type 1:
        • May benefit from immunotherapy or radioactive iodine (RAI) therapy, respectively
      • BRAF-mutant subtypes:
        • May require targeted tyrosine kinase inhibitors due to RAI resistance
    • Preoperative Decision-Making:
      • Genomic classifiers applied to fine needle aspirates can help stratify patients for active surveillance or surgery
    • Tailored Treatments:
      • Understanding subtype-specific pathways enables the development of novel therapies, such as EZH2 inhibitors for aggressive subtypes
  • This classification system bridges the gap between molecular biology and clinical practice, paving the way for precision medicine in thyroid cancer management

Molecular Characteristics of Differentiated Thyroid Cancer (DTC)

  • Differentiated thyroid cancer (DTC):
    • Which includes papillary thyroid carcinoma (PTC), follicular thyroid carcinoma (FTC), and oncocytic thyroid carcinoma (OTC):
      • Is characterized by specific molecular alterations that affect key signaling pathways:
        • The mitogen‑activated protein kinase (MAPK) pathway
        • Phosphatidylinositol 3 – kinase – protein kinase B (PI3K-AKT) pathway 
  • Key Genetic Alterations:
    • Papillary Thyroid Carcinoma (PTC):
      • BRAF Mutations:
        • Found in 45% to 75% (29% to 83%) of PTCs, particularly the BRAF V600E mutation (62% if the cases):
          • Which activates the MAPK pathway:
        • It is associated with aggressive features like extrathyroidal extension and advanced stage
      • RET / PTC Rearrangements:
        • Present in 10% to 20% (2.5% to 73%) of PTCs
        • These fusions also activate the MAPK pathway
      • RAS Mutations:
        • Occur in ~10% to 15% of PTCs:
          • Often in follicular-variant PTC
      • TERT Promoter Mutations:
        • Found in advanced cases
        • They are often co-mutated with BRAF V600E:
          • Indicating worse prognosis
    • Follicular Thyroid Carcinoma (FTC):
      • RAS Mutations:
        • Predominantly found (~30% to 50%)
        • Driving tumorigenesis via the MAPK and PI3K / AKT pathways
      • PAX8 / PPARγ Rearrangements:
        • Seen in ~30%
        • These are unique to FTC and are mutually exclusive with RAS mutations
    • Other Mutations Across DTC:
      • NTRK 1/3 Fusions:
        • Rare (~1% to 3%) but significant in some PTCs
      • PI3K / AKT Pathway Alterations:
        • Common in advanced or dedifferentiated cases
  • Molecular Subtypes of PTC:
    • Recent studies have identified four molecular subtypes based on transcriptomic and genomic profiling:
      • Immune-Enriched Subtype (Subtype 2):
        • Characterized by:
          • High immune infiltration
          • Overexpression of immune checkpoints
      • BRAF-Enriched Subtype (Subtype 4):
        • Associated with:
          • BRAF mutations
          • Advanced TNM stage
          • Aggressive behavior
      • Stromal Subtype (Subtype 3):
        • Features high stromal content and distinct gene expression
      • CNV-Enriched Subtype (Subtype 6):
        • Defined by somatic copy number variations
  • Pathway Dysregulation:
    • MAPK Pathway:
      • Activated by:
        • BRAF, RAS (intracellular signal
          transducers)
        • RET /PTC and NTRK 1/3 mutations (cell-membrane receptor tyrosine kinases:
          • Leading to increased tumor proliferation
    • PI3K / AKT Pathway:
      • Frequently altered in FTC and advanced DTC:
        • Contributing to tumor growth and survival
    • TSHR cAMP Pathway:
      • Altered in FTC through mutations like:
        • TSHR or GNAS
  • Prognostic Implications:
    • Co-occurrence of BRAF V600E and TERT promoter mutations significantly worsens outcomes
    • Molecular profiling aids in risk stratification, guiding treatment decisions such as targeted therapies
  • Therapeutic Implications:
    • Targetable alterations include:
      • BRAF inhibitors for BRAF-mutant tumors
      • RET inhibitors for RET fusion-positive cancers
      • Immune checkpoint inhibitors for immune-enriched subtypes
    • Molecular understanding of DTC provides a foundation for personalized treatment approaches and improved prognostication

COMET (Comparing an Operation to Monitoring, with or without Endocrine Therapy) in DCIS

  • The COMET (Comparing an Operation to Monitoring, with or without Endocrine Therapy) trial:
    • A randomized clinical trial, investigated whether active monitoring is non-inferior to standard treatment (surgery with or without radiation) for low-risk DCIS (ductal carcinoma in situ):
      • Finding that active monitoring is a viable option
  • Study Purpose:
    • The COMET trial aimed to determine if active monitoring, which involves close surveillance with surgery only if DCIS progresses to invasive cancer:
      • Is as effective as the standard treatment of surgery (lumpectomy or mastectomy) with or without radiation and / or hormone therapy for women with low-risk DCIS
  • Study Design:
    • The COMET trial was a randomized controlled trial, meaning participants were randomly assigned to:
      • Either active monitoring or guideline-concordant care (surgery with or without radiation)
  • Eligibility:
    • The study included women aged 40 and older with low-risk DCIS:
      • Defined as grade 1 or 2, hormone receptor-positive, HER2-negative, with no signs of invasive cancer, and the diagnosis confirmed by at least two pathologists
  • Key Findings:
    • After 24 months of follow-up:
      • The two-year cumulative rate of invasive ipsilateral breast cancer was 5.9% in the guideline-concordant care arm and 4.2% in the active monitoring arm:
        • The difference met the threshold for noninferiority:
          • Meaning that neither treatment was deemed inferior to the other
  • Implications:
    • The results suggest that active monitoring is a valid alternative to surgery for women with low-risk DCIS, potentially reducing overtreatment and improving quality of life
  • Patient-Reported Outcomes:
    • The study also found that overall health-related quality of life remained stable from baseline to 2 years and did not differ significantly between the two treatment arms
  • Funding:
    • The COMET study was funded by the Patient-Centered Outcomes Research Institute (PCORI), the Breast Cancer Research Foundation (BCRF), and other organizations
  • Study Location:
    • The study was conducted across multiple sites in the United States

Benign Follicular Cell-Derived Thyroid Tumors

  • Clinically, the term ‘goiter’ relates to an enlarged thyroid gland:
    • A finding that is associated with various neoplastic and non-neoplastic disorders
  • Goiter often presents as:
    • A nodular and rarely as a diffuse process
  • Most agree that the terms ‘colloid nodules,’ ‘multinodular goiter,’ ‘adenomatous goiter’ and ‘multinodular hyperplasia’:
    • Often used by pathologists are not reflective of the underlying pathology besides the mere confirmation of clinical findings
    • Molecular analyses of individual nodules
      in such cases have revealed that a good proportion of goitrous nodules is:
      • Monoclonal and represents neoplastic
        proliferations
        :
        • Making it impossible to distinguish between non-neoplastic and benign neoplastic follicular neoplasms i.e. adenomas on the basis of morphology alone (Mete & Asa 2012)
    • In addition, most of the adenomatous nodules
      encountered in patients with DICER1, PTEN and PTEN-like syndromes (Harrer et al. 1998a,b, Derwahl & Studer 2002):
      • Also represent multiple follicular adenomas (Wasserman et al. 2018, Cameselle-Teijeiro et al. 2021):
        • Therefore, an umbrella term of ‘follicular nodular disease’ (FND):
          • Has been proposed in the latest WHO classification, to avoid the above-mentioned issues (Baloch et al. 2022)
  • In the 2017 WHO classification scheme of thyroid
    neoplasms:
    • Follicular adenoma was the only entity
      included in the benign follicular cell-derived tumors:
      • However, in the fifth edition, ‘follicular adenoma with papillary architecture’ (previously termed as papillary adenomatous / hyperplastic nodule) is also included in the benign neoplasm category
    • Follicular adenoma with papillary architecture:
      • Is a well-demarcated and non-invasive, often encapsulated tumor with intra-follicular centripetal papillary growth, and the lesional cells lack nuclear features of papillary thyroid carcinoma (PTC) (Mete & Asa 2012, Baloch et al. 2022)
      • These tumors are often associated with autonomous hyperfunction:
        • May therefore appear as hot or warm nodules on radionuclide thyroid scan (Mete & Asa 2012)
      • Molecular analyses have shown that these are driven by:
        • TSHR, GNAS or EZH1 mutations and alterations that activate the protein kinase
          A
          (PKA) pathway (Parma et al. 1993, Gozu et al. 2010)
      • These tumors may also occur in the setting of McCune–Albright and Carney complex syndromes:
        • Both are PKA pathway-related conditions driven by GNAS and PRKAR1A mutations, respectively (Kamilaris et al. 2019, Nosé et al. 2022)
      • Moreover, non-functional follicular adenomas with papillary architecture:
        • Can harbor DICER1 mutations, and a subset of these have been reported in association with DICER1 syndrome (Wasserman et al. 2018, Cameselle-Teijeiro et al. 2021, Juhlin et al. 2021):
          • Thus, the association between thyroid function and related tumor syndromes
            makes the distinction between these tumors clinically significant
      • Furthermore, a diagnosis of oncocytic
        follicular adenoma:
        • Requires >75% of tumor cells to exhibit oncocytic features (Baloch et al. 2022)
        • Overall, oncocytic thyroid tumors represent a distinct entity of thyroid neoplasms, supported by specific genetic aberrations
          including:
          • Mitochondrial DNA mutations and increased copy number alterations (Gopal et al. 2018, Doerfler et al.
            2021, McFadden & Sadow 2021)

Etiology / Pathogenesis of Medullary Thyroid Cancer

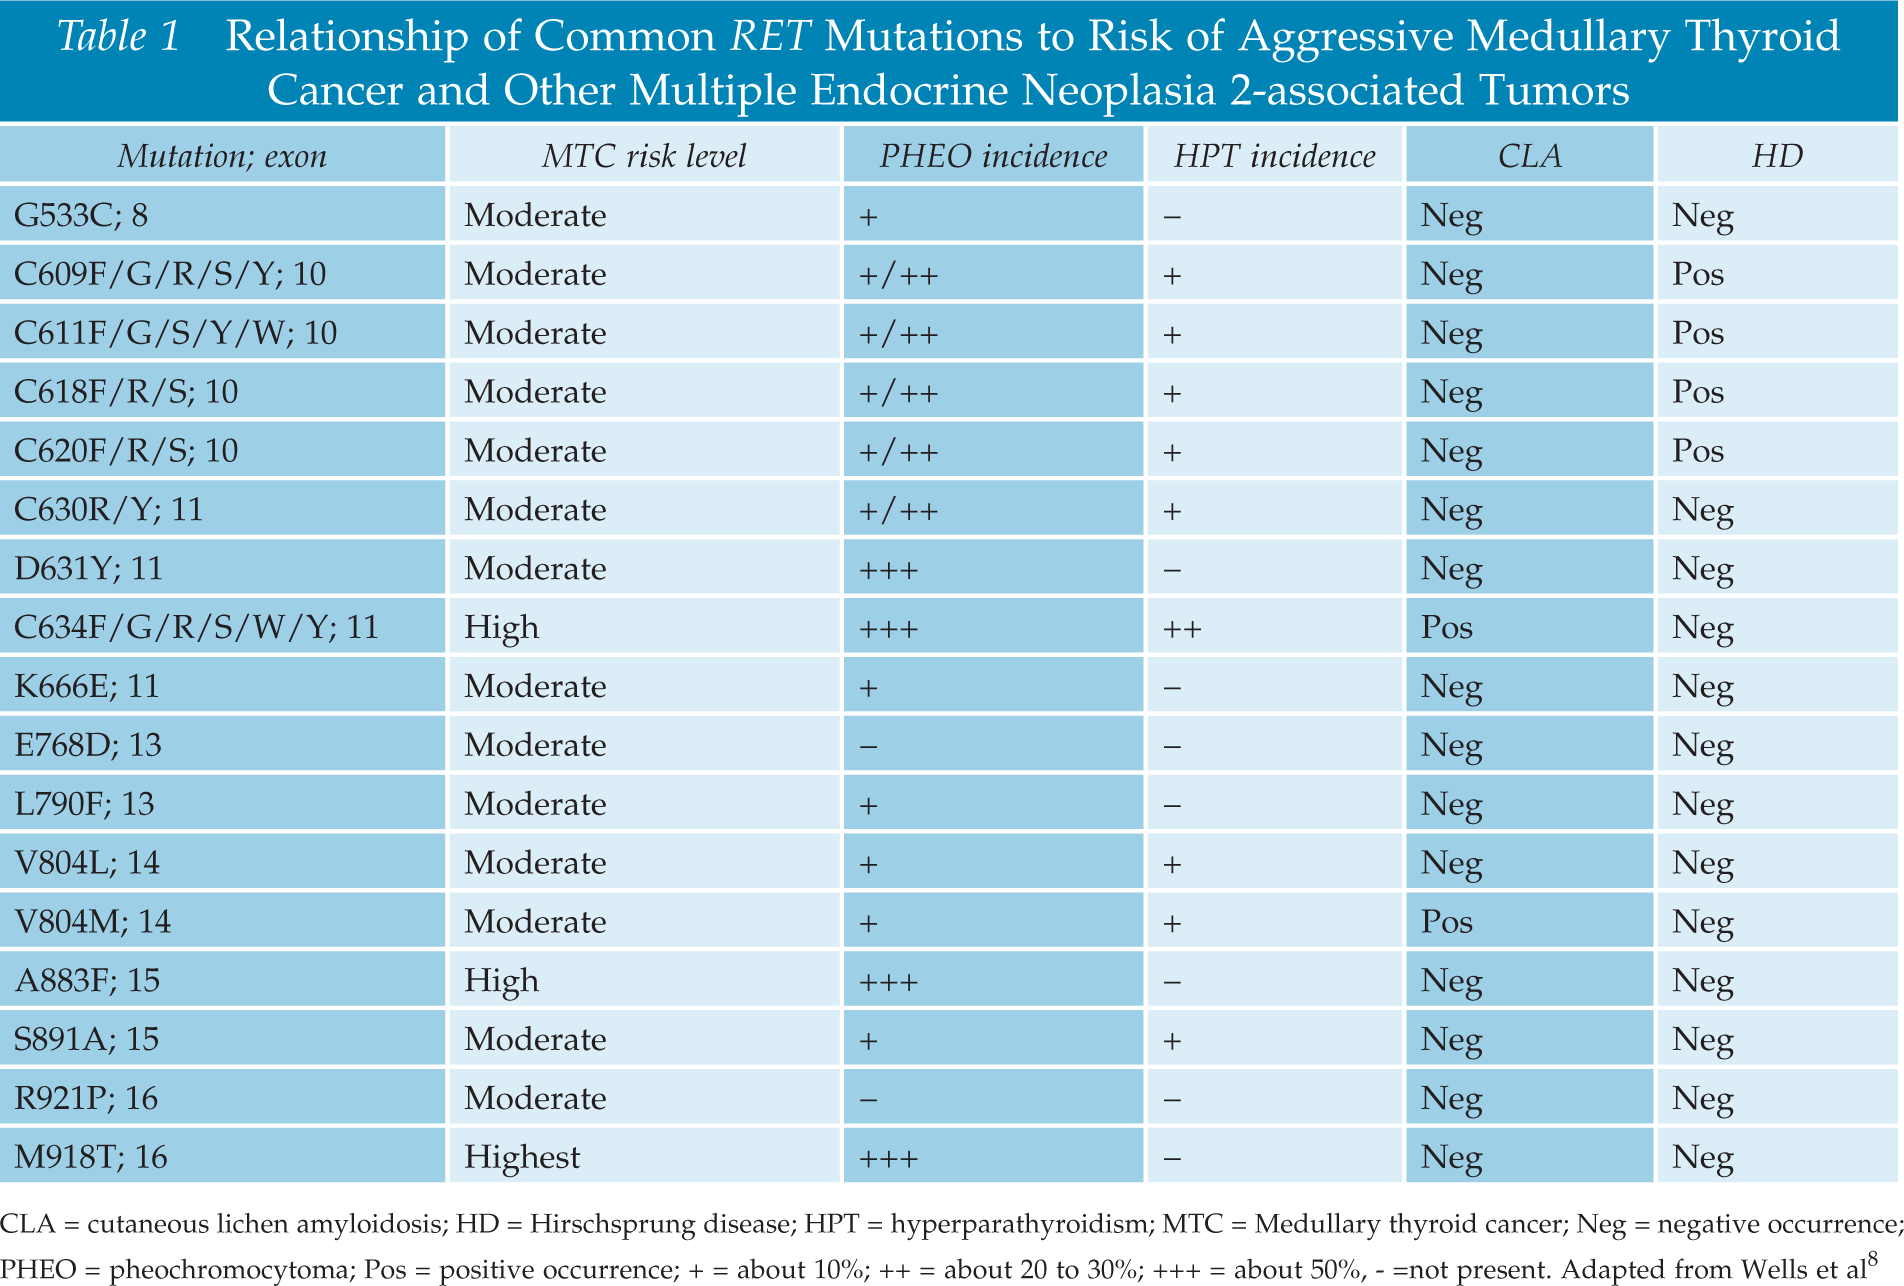
Relationship of Common RET Mutations to Risk of Aggressive MTC

cropped-18403652_10206829497335208_5004404657991480104_n1.jpg

  • What is Head and Neck Surgery?:
    • It is a surgical sub-specialty that deals mainly with benign and malignant tumors of the head and neck region, including:
      • The scalp, facial region, eyes, ears, nose, nasal fossae, paranasal sinuses, oral cavity, pharynx (nasopharynx, oropharynx, hypopharynx), larynx (supraglotic larynx, glottis larynx, subglotic larynx), thyroid gland, parathyroid gland, salivary glands (parotid glands, submandibular glands, sublingual glands, minor salivary glands), soft tissues of the neck, skin of the head and neck region.
        • The head and neck surgeon’s work area:Does not cover tumors or diseases of the brain and other areas of the central nervous system or those of the cervical spine:This is the neurosurgeon field.
    • Among the diagnostic procedures performed by the head and neck surgeon,  are the following:
      • Nasopharyngolaryngoscopy:
        • Performed to examine, evaluate and, possibly perform a biopsy, of oral cavity, pharyngeal and laryngeal lesions.
    • The surgeries most commonly performed by the head and neck surgeon are:
      • Total or near total thyroidectomies
      • Hemithryoidectomies (lobectomies)
      • Comprehensive neck dissections
      • Selective neck dissections
      • Maxillectomies:
        • Total maxillectomy
        • Subtotal maxillectomy
        • Infrastructure maxillectomy
        • Suprastructure maxillectomy
        • Medial maxillectomy
      • Mandibulectomy:
        • Segmental
        • Marginal
      • Tracheostomy
      • Salivary gland surgeries:
        • Parotid gland operations:
          • Limited superficial parotidectomy with identification and preservation of the facial nerve
          • Superficial parotidectomy with identification and preservation of the facial nerve
          • Near total parotidectomy with identification and preservation of the facial nerve
          • Total parotidectomy
        • Submandibular gland resection
        • Sublingual gland resection
      • Resection of tumors of the oral cavity:
        • Glossectomy
        • Resection of the floor of the mouth tumors
      • Resection of tumors of the pharynx
      • Resection of tumors of the larynx
      • Split-thickness skin grafts
      • Full-thickness skin grafts
      • Sentinel lymph node mapping and sentinel lymph node biopsy
      • Resection of malignant skin tumors (BCC, SCC, melanoma) of the head and neck region
  • The formation of the head and neck surgeon includes mastering the following subjects:
    • Surgical Anatomy
    • History and Basic Principles of Head and Neck Surgery
    • Epidemiology, Etiology, and Pathology of Head and Neck Diseases
    • Diagnostic Radiology of the Head and Neck Region
    • Tumors of the Scalp, Skin and Melanoma
    • Eyelids and Orbit
    • Nasal Cavity and Paranasal Sinuses
    • Skull Base and Temporal Bone
    • Lips and Oral Cavity
    • Pharynx and Esophagus
    • Larynx and Trachea
    • Cervical Lymph Nodes
    • Thyroid and Parathyroid Glands
    • Salivary Glands
    • Neurogenic Tumors and Paragangliomas
    • Soft Tissue Tumors
    • Bone Tumors and Odontogenic Lesions
    • Reconstructive Surgery
    • Oncologic Dentistry and Maxillofacial Prosthetics
    • Principles of Radiation Oncology
    • Principles of Chemotherapy
    • Molecular Oncology, Genomics and Immunology
    • Nutrition
    • Biostatistic


  • Rodrigo Arrangoiz MS, MD, FACS a head and neck surgeon / endocrine surgeon / surgical oncologist and is a member of Sociedad Quirúrgica S.C at the America British Cowdray Medical Center in Mexico City:


prof_739_20190417135234

  • Rodrigo Arrangoiz MS, MD, FACS:
    • Is a member of the American Head and Neck Society

img_4750

    • He is a member of the American Thyroid Association:

Unknown

Training:

• General surgery:

• Michigan State University:

• 2004 al 2010

• Surgical Oncology / Head and Neck Surgery / Endocrine Surgery:

• Fox Chase Cancer Center (Filadelfia):

• 2010 al 2012

• Masters in Science (Clinical research for health professionals):

• Drexel University (Filadelfia):

• 2010 al 2012

• Surgical Oncology / Head and Neck Surgery / Endocrine Surgery:

• IFHNOS / Memorial Sloan Kettering Cancer Center:

• 2014 al 2016

#Arrangoiz

#Teacher

#Surgeon

#Cirujano

#ThyroidExpert

#ThyroidSurgeon

#CirujanodeTiroides

#ExpertoenTiroides

#ExpertoenParatiroides

#Paratiroides

#Hiperparatiroidismo

#CancerdeTiroides

#ThyroidCancer

#PapillaryThyroidCancer

#SurgicalOncologist

#CirujanoOncologo

#CancerSurgeon

#CirujanodeCancer

#HeadandNeckSurgeon

#CirugiaEndocrina

#CirujanodeTumoresdeCabezayCuello

#OralCavityCancer

#Melanoma

Medullary Thyroid Cancer Awareness Month

👉Two articles published by a Rodrigo Arrangoiz on medullary thyroid cancer

http://www.remedypublications.com/american-journal-of-otolaryngology-and-head-and-neck-surgery-abstract.php?aid=218

https://s3.amazonaws.com/academia.edu.documents/57472024/final_published_paper.pdf?response-content-disposition=attachment%3B%20filename%3DMedullary_Thyroid_Carcinoma_Literature_R.pdf&X-Amz-Algorithm=AWS4-HMAC-SHA256&X-Amz-Credential=AKIAIWOWYYGZ2Y53UL3A%2F20200302%2Fus-east-1%2Fs3%2Faws4_request&X-Amz-Date=20200302T210556Z&X-Amz-Expires=3600&X-Amz-SignedHeaders=host&X-Amz-Signature=d78d7b605c8a3e8c49d59b7d9545a3f645b1aa4ff1cbda4f57fb4e274bb30849

#Arrangoiz #ThyroidSurgeon

#ThyroidExpert

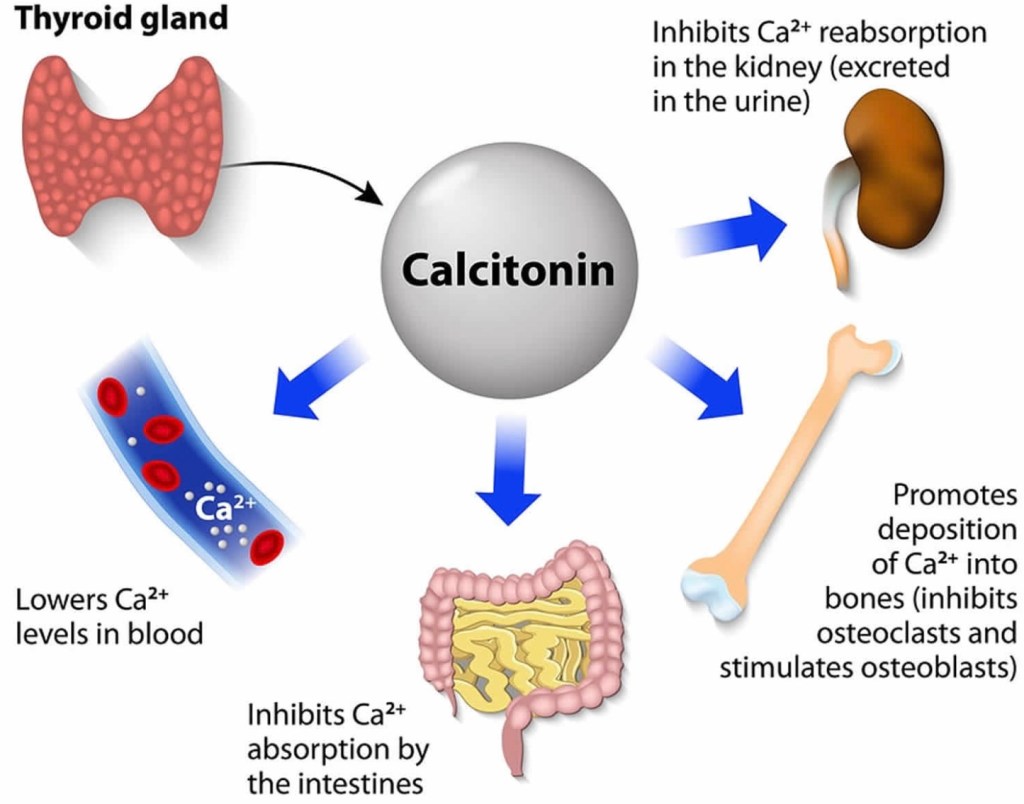
Calcitonin

  • Calcitonin:
    • Is produced by the:
      • Parafollicular cells / C-cells of the thyroid gland:
        • Works to oppose the actions of PTH
    • It helps lower ionized calcium levels:
      • Primarily in two ways:
        • First, it inhibits osteoclast-mediated bone resorption
        • Second, it inhibits resorption of calcium and phosphate by the kidney
  • Calcitonin:
    • Has no direct effects on:
      • Intestinal absorption
      • Osteoblast-mediated bone formation
  • It is also used in the treatment of hypercalcemic crisis:
    • 4 IU/kg subcutaneously / intramuscularly
  • It acts quickly (24 to 48 hours):
    • Is more effective when used in combination with glucocorticoids
  • Finally, calcitonin is a useful marker:
    • With regard to surveillance in medullary thyroid carcinoma

#Arrangoiz #Calcitonin #ParathyroidSurgeon #ParathyroidExpert #CalciumHemostasis #Teacher #Surgeon #HeadandNeckSurgeon #CancerSurgeon #MSMC #MountSinaiMedicalCenter #Miami #Mexico

Diagnosis of Medullary Thyroid Carcinoma (MTC)

  • The diagnosis of medullary thyroid cancer (MTC):
    • Is usually made after fine-needle aspiration (FNA) biopsy in a patient who has a solitary thyroid nodule (or a dominant nodule within a multinodular goiter):
      • The sensitivity of FNA is 50% to 80%:
        • Although higher sensitivity can be obtained by the addition of immunohistochemical staining for calcitonin
  • If the clinical suspicion for MTC is high:
    • Patient with diarrhea, flushing, and a thyroid nodule:
      • Calcitonin can be measured in the washout of the FNA biopsy needle:
        • Although this may not be readily available in many commercial laboratories
  • In some cases:
    • The diagnosis of MTC is made after thyroid lobectomy for a suspicious or indeterminate FNA biopsy:
      • Surgical specimens from patients with MTC show:
        • Spindle-shaped and frequently pleomorphic cells without follicle development:
          • Because these cells originate from the calcitonin-producing parafollicular C cells of the thyroid
      • The use of serum calcitonin screening to complement ultrasound and FNA in the routine diagnosis of thyroid nodules is controversial in the United States:
        • Measurement of serum calcitonin has not been a part of the routine evaluation of patients with thyroid nodules in the United States:
          • The high frequency of falsely elevated serum calcitonin values, the inability to confirm the high calcitonin by pentagastrin stimulation in the United States, and the accuracy of FNA biopsy: would argue against a change in this recommendation
        • Further, occasional patients with locoregional metastases or locally invasive MTC will have normal unstimulated serum calcitonin concentrations
  • In some countries (eg, European countries) where pentagastrin is available, however, serum basal and stimulated calcitonin levels are routinely used in the evaluation of thyroid nodules to facilitate the preoperative diagnosis of MTC
  • Differential Diagnosis:
    • The differential diagnosis in a patient presenting with a neck mass:
      • Is extensive and varies with the age of the patient at presentation
    • The majority of these masses represent benign thyroid nodules and cysts
    • Neck masses that are not of thyroidal origin may be from:
      • Congenital
      • Vascular anomaly
      • Inflammatory:
        • Lymph node enlargement
      • Other neoplastic:
        • Primary or metastatic disease disorders
  • In addition to medullary thyroid cancer (MTC):
    • Elevated calcitonin results may also be seen in patients with:
      • Hypercalcemia
      • Hypergastrinemia
      • Neuroendocrine tumors
      • Renal insufficiency
      • Papillary and follicular thyroid carcinomas
      • Goiter
      • Chronic autoimmune thyroiditis
      • Prolonged treatment with:
        • Omeprazole (greater than two to four months)
        • Beta blockers
        • Glucocorticoids:
          • Has been associated with hypercalcitoninemia
  • In addition, the presence of heterophilic antibodies to calcitonin:
    • Can falsely elevate serum calcitonin levels 
  • Elevated carcinoembryonic antigen (CEA) levels can also occur in patients with:
    • Heterophilic antibodies
    • Gastrointestinal tract inflammatory disease
    • Benign lung disease
    • Non-thyroid malignancies
    • Cigarette smoking
  • Evaluation:
    • For patients diagnosed with medullary thyroid cancer (MTC) on the basis of cytologic evaluation of a thyroid nodule:
      • Evaluation should include:
        • Measurement of serum calcitonin, carcinoembryonic antigen (CEA), ultrasonography of the neck (if not already performed), genetic testing for germline RET mutations, and biochemical evaluation for coexisting tumors, especially pheochromocytoma
        • Serum calcitonin and CEA:
          • The serum calcitonin and carcinoembryonic antigen (CEA) concentrations should be measured in patients diagnosed with MTC on the basis of cytologic evaluation of a thyroid nodule
          • These tests can establish that the tumor is capable of hypersecreting the hormones and, if so, the values can be compared with postoperative values
      • Postoperatively:
        • Results may provide a prognostic factor or indicate biochemical cure
  • In a study of 226 patients with MTC:
    • Preoperative serum calcitonin concentrations:
      • Where significantly correlated with tumor size in both the sporadic and familial cases
    • In addition, among 45 patients who had a preoperative serum calcitonin concentration of 50 pg/mL or less:
      • 44 had normal concentrations after surgery:
    • In contrast, only 50 of 120 patients with preoperative serum calcitonin concentrations higher than 50 pg/mL had normal concentrations after surgery
  • In a second study of 224 patients with MTC:
    • 62% of patients without nodal metastases had normal calcitonin postoperatively:
      • 10% of node positive patients had normal postoperative calcitonin levels
  • Assessment of calcitonin and CEA doubling times postoperatively:
    • Provides sensitive markers for progression and aggressiveness of metastatic MTC:
      • Postoperative calcitonin doubling time was a prognostic factor for survival in a study of 65 patients followed for 3 to 30 years:
        • Ten-year survival was: 8%, 37%, and 100% for doubling times:
          • Under six months, between six months and 24 months, and greater than 24 months, respectively
  • Radiologic evaluation:
    • MTC can spread by:
      • Local invasion or metastasis:
        • Within the neck or distantly
    • When MTC is diagnosed by fine-needle aspiration (FNA) biopsy:
      • Ultrasonography of the neck is indicated to look for cervical lymph node involvement
    • For patients with local lymph node metastases on ultrasound or with preoperative serum basal calcitonin > 500 pg/mL (indicating high risk of local or distant metastatic disease):
      • Additional imaging is required to assess for metastatic disease:
        • In this setting, based con literature review I suggest cross-sectional imaging including:
          • Chest computed tomography (CT)
          • Neck CT with IV contast
        • Three-phase contrast-enhanced liver CT or contrast-enhanced liver magnetic resonance imaging (MRI)
        • Axial MRI, and bone scintigraphy:
          • In patients suspected of having skeletal metastases
          • MRI may be superior to other imaging modalities
    • I do not recommend 18-fluoro-2-deoxyglucose positron emission tomography (FDG-PET) imaging or somatostatin receptor imaging:
      • For routine initial screening for metastatic disease:
        • The sensitivity of FDG-PET scanning for detecting metastatic disease is variable:
          • But improves with higher calcitonin levels
          • Sensitivity 78% versus 20% for basal calcitonin value greater than or less than 1000 pg/mL, respectively
      • The use of radionuclide imaging with 111-In-octreotide or 99m-Tc-DMSA:
        • Is not currently recommended for routine initial screening for metastatic disease
        • However, three patients have been described who had regional and distant metastases of MTC detected by somatostatin receptor scintigraphy but not by CT scan
      • How to select patients with a negative CT scan to undergo somatostatin receptor scintigraphy is not clear:
        • Scanning may be more useful in localizing residual or recurrent disease after primary therapy
  • Genetic screening in sporadic MTC:
    • Germline RET testing:
      • In all patients with newly diagnosed C cell hyperplasia or apparently sporadic MTC:
        • Initial germline testing in patients with C cell hyperplasia or apparently sporadic MTC should include:
          • Sequencing of exons 10, 11, and 13 through 16 of the RET gene
        • Sequencing of the remaining exons in the RET gene should be considered in patients with:
          • Clinical features or family history highly suggestive of hereditary medullary syndromes who demonstrate no mutations in exons 10, 11, or 13 through 16
  • While it is possible for clinicians to directly order genetic testing from reference laboratories:
    • It is strongly encourage to have a consultation with genetic counselors who are familiar with both the ethical issues and legal informed consent requirements (which can vary significantly in different regions) that are involved in germline testing
  • When the index patient is positive for a germline mutation:
    • Family members should be offered genetic counseling and genetic screening
  • An important question is what proportion of patients with apparently sporadic MTC have unsuspected germline mutations in the RET proto-oncogene (the underlying defect in MEN2) and, therefore, have heritable disease:
    • Studies of unselected patients with MTC have found, on average:
      • That approximately 6% to 7%  (range 1.5% to 24%) have germline RET mutations
    • In one report, 35 of 482 patients (7.3%) with apparently sporadic MTC had mutations, and in 18 of these 35:
      • Gene carriers were identified in relatives
  • 75% of the familial medullary cases:
    • Had no prior family history:
      • A much higher percentage (approximately 60%) of patients with sporadic MTC have somatic (acquired) mutations in the RET gene within the tumor cells:
        • These mutations are present only in the tumor cells and are not detected by standard genetic testing (ie, using leukocyte DNA)
    • The presence of somatic RET mutations correlate with:
      • Lymph node metastases
      • Persistent disease
      • Lower survival
    • However, in one study:
      • Only mutations in exons 15 and 16 of the RET gene were associated with the worse prognosis:
        • While those in other exons had a more indolent course
  • Since it is unclear how knowledge of a specific somatic (acquired) RET mutation should impact clinical management:
    • I do not routinely test tumor samples
  • Testing for coexisting tumors:
    • Most patients require biochemical evaluation for coexisting tumors (particularly pheochromocytoma and hyperparathyroidism) prior to thyroidectomy:
      • Even when genetic screening is performed preoperatively:
        • The results are rarely known prior to surgery
    • For patients with unknown RET mutational status and for patients who have a germline RET mutation:
      • Serum calcium:
        • To rule out hyperparathyroidism requiring concomitant surgical intervention
      • Plasma fractionated metanephrines:
        • As the initial screen for pheochromocytoma):
          • Normal plasma fractionated metanephrines values exclude a symptomatic catecholamine-secreting neoplasm
          • Mildly elevated values of normetanephrine could be falsely positive in which case additional evaluations including 24-hour urinary fractionated metanephrines, catecholamines, and adrenal imaging may be required to effectively rule in or rule out pheochromocytoma prior to surgery
          • Adrenal imaging should not be performed unless there is biochemical evidence suggesting a possible pheochromocytoma
  • In a patient with negative RET proto-oncogene testing and no family history of MEN2 syndrome:
    • Biochemical testing for coexisting tumors is typically not required
  • What is Head and Neck Surgery?:
    • It is a surgical sub-specialty that deals mainly with benign and malignant tumors of the head and neck region, including:
      • The scalp, facial region, eyes, ears, nose, nasal fossae, paranasal sinuses, oral cavity, pharynx (nasopharynx, oropharynx, hypopharynx), larynx (supraglotic larynx, glottis larynx, subglotic larynx), thyroid gland, parathyroid gland, salivary glands (parotid glands, submandibular glands, sublingual glands, minor salivary glands), soft tissues of the neck, skin of the head and neck region. The head and neck surgeon’s work area:Does not cover tumors or diseases of the brain and other areas of the central nervous system or those of the cervical spine:
        • This is the neurosurgeon field
  • Among the diagnostic procedures performed by the head and neck surgeon,  are the following: Nasopharyngolaryngoscopy:
    • Performed to examine, evaluate and, possibly perform a biopsy, of oral cavity, pharyngeal and laryngeal lesions.
  • The surgeries most commonly performed by the head and neck surgeon are: Total or near total thyroidectomies
  • Hemithryoidectomies (lobectomies)
  • Comprehensive neck dissections
  • Selective neck dissections
  • Maxillectomies: Total maxillectomy
  • Subtotal maxillectomy
  • Infrastructure maxillectomy
  • Suprastructure maxillectomy
  • Medial maxillectomy
  • Mandibulectomy: Segmental
  • Marginal
  • Tracheostomy
  • Salivary gland surgeries: Parotid gland operations: Limited superficial parotidectomy with identification and preservation of the facial nerve
  • Superficial parotidectomy with identification and preservation of the facial nerve
  • Near total parotidectomy with identification and preservation of the facial nerve
  • Total parotidectomy
  • Submandibular gland resection
  • Sublingual gland resection
  • Resection of tumors of the oral cavity: Glossectomy
  • Resection of the floor of the mouth tumors
  • Resection of tumors of the pharynx
  • Resection of tumors of the larynx
  • Split-thickness skin grafts
  • Full-thickness skin grafts
  • Sentinel lymph node mapping and sentinel lymph node biopsy
  • Resection of malignant skin tumors (BCC, SCC, melanoma) of the head and neck region
  • The formation of the head and neck surgeon includes mastering the following subjects: Surgical Anatomy
  • History and Basic Principles of Head and Neck Surgery
  • Epidemiology, Etiology, and Pathology of Head and Neck Diseases
  • Diagnostic Radiology of the Head and Neck Region
  • Tumors of the Scalp, Skin and Melanoma
  • Eyelids and Orbit
  • Nasal Cavity and Paranasal Sinuses
  • Skull Base and Temporal Bone
  • Lips and Oral Cavity
  • Pharynx and Esophagus
  • Larynx and Trachea
  • Cervical Lymph Nodes
  • Thyroid and Parathyroid Glands
  • Salivary Glands
  • Neurogenic Tumors and Paragangliomas
  • Soft Tissue Tumors
  • Bone Tumors and Odontogenic Lesions
  • Reconstructive Surgery
  • Oncologic Dentistry and Maxillofacial Prosthetics
  • Principles of Radiation Oncology
  • Principles of Chemotherapy
  • Molecular Oncology, Genomics and Immunology
  • Nutrition
  • Biostatistic
  • Rodrigo Arrangoiz MS, MD, FACS a head and neck surgeon / endocrine surgeon / complex surgical oncologist and is a member of Mount Sinai Medical Center, in Miami Beach, Florida
  • Rodrigo Arrangoiz MS, MD, FACS:
    • Is a member of the American Head and Neck Society
    • He is a member of the American Thyroid Association
  • Training:
    • General surgery:
      • Michigan State University:
      • 2004 al 2010
  • Surgical Oncology / Head and Neck Surgery / Endocrine Surgery:
    • Fox Chase Cancer Center (Filadelfia):
      • 2010 al 2012
  • Masters in Science (Clinical research for health professionals):
    • Drexel University (Filadelfia):
    • 2010 al 2012
  • Surgical Oncology / Head and Neck Surgery / Endocrine Surgery:
    • IFHNOS / Memorial Sloan Kettering Cancer Center:
      • 2014 al 2016

Clinical Presentation of Medullary Thyroid Carcinoma

  • Sporadic MTC (75% of all cases):Typically occurs between the fourth to sixth decade of life:However, patients with hereditary disease:Present earlier
    • Patients with MTC who present with a palpable thyroid nodule:70% will have cervical lymphadenopathy
      • 15% to 20% will have palpable cervical lymphadenopathy.
    • Pain or aching:Is also a common symptom of MTC
    • Local tumor invasion may produce symptoms of:Dysphagia, dyspnea, or dysphonia
    • Patients with extensive metastatic disease frequently develop:Diarrhea:Which may result from:Increased intestinal motility and impaired intestinal water and electrolyte flux:Due to high calcitonin levels
      • About 2% to 4% of patients develop:Cushing syndrome:As a result of ectopic production of ACTH
  • Classic MEN2A is the most common variant of MEN2 (95% of the cases):Most patients carry germline RET mutations in:Codons 609, 611, 618, or 620 of exon 10
      • Codon 634 of exon 11
    • Almost all patients develop MTC:But pheochromocytomas have the highest penetrance in patients with:Codon 634 mutations:52% by age 50
          • 88% by age 77
        • These adrenal tumors:Are almost always benign
          • Are usually multicentric
          • Are associated with diffuse adrenal nodular hyperplasia
      • HPT:Is usually mild and may involve one to four parathyroid glands.
        • RET codon 634 mutations:Are associated with a penetrance of up to 30% for PHPT, whereas it ranges from 2 to 12% for the remaining mutations.
  • Cutaneous lichen amyloidosis (CLA):Can occur sporadically or in an inherited manner:Either separately or in the context of MEN2A
    • The skin lesions of CLA in MEN2A:Are most apparent in the dermatomes corresponding to T2 to T6:Scapular region of the back
    • The classic symptom is:Itching:That worsens in times of stress
        • Improves with sun exposure
    • The lesions are incited by notalgia paresthetica:A sensory neuropathy of the dorsal spinal nerve:May occur prior to MTC
    • CLA is almost exclusively found in patients with:The codon 634 mutations (exon 11)
      • Although cases have also been reported in patients with:Codon 804 mutations
      • Pheochromocytomas and PHPT in CLA patients:Occur at frequencies similar to classic MEN2A
  • In patients with MEN2B:MTC often presents in infancy and is usually highly aggressive
    • Approximately 75% to 90% of MEN2B cases occur in patients:Having de novo RET mutations:Whereas 10% to 25% occur in families with:Known history of MEN2B
    • About 95% of MEN2B individuals:Have codon M918T mutations (exon 13) – Highest risk (HST)The remaining 5% have codon A883F mutations (exon 15) – High risk (H):The MTCs in codon A883F tend to be less aggressive
    • Pheochromocytomas develop in:About 50% of MEN2B patients
    • These individuals also have a typical appearance that includes:Eye abnormalities:Thickened and everted eyelids
        • Mild ptosis
        • Thickened corneal nerves
      • Marfanoid body habitus
      • Long narrow facies
      • Pes cavus
      • Pectus excavatum
      • High-arched palate
      • Scoliosis
      • Slipped capital femoral epiphyses
      • Mucosal neuromas
      • Diffuse ganglioneuromatosis of the aerodigestive tractLeading to bloating, intermittent constipation, diarrhea, and even intestinal obstruction
    • Some patients have atypical MEN2B:Which presents later in life:Around 20 to 30 years of age:These patients have double RET germline mutations:Occurring in tandem on the same allele:Usually V804M and either Y806C, S904C, E805K, or Q781R 


prof_739_20190417135234

  • Rodrigo Arrangoiz MS, MD, FACS:
    • Is a member of the American Head and Neck Society

img_4750

    • He is a member of the American Thyroid Association:

Unknown

Training:

• General surgery:

• Michigan State University:

• 2004 al 2010

• Surgical Oncology / Head and Neck Surgery / Endocrine Surgery:

• Fox Chase Cancer Center (Filadelfia):

• 2010 al 2012

• Masters in Science (Clinical research for health professionals):

• Drexel University (Filadelfia):

• 2010 al 2012

• Surgical Oncology / Head and Neck Surgery / Endocrine Surgery:

• IFHNOS / Memorial Sloan Kettering Cancer Center:

• 2014 al 2016

#Arrangoiz

#Teacher

#Surgeon

#Cirujano

#ThyroidExpert

#ThyroidSurgeon

#CirujanodeTiroides

#ExpertoenTiroides

#ExpertoenParatiroides

#Paratiroides

#Hiperparatiroidismo

#CancerdeTiroides

#ThyroidCancer

#PapillaryThyroidCancer

#SurgicalOncologist

#CirujanoOncologo

#CancerSurgeon

#CirujanodeCancer

#HeadandNeckSurgeon

#CirugiaEndocrina

#CirujanodeTumoresdeCabezayCuello

#OralCavityCancer

#Melanoma